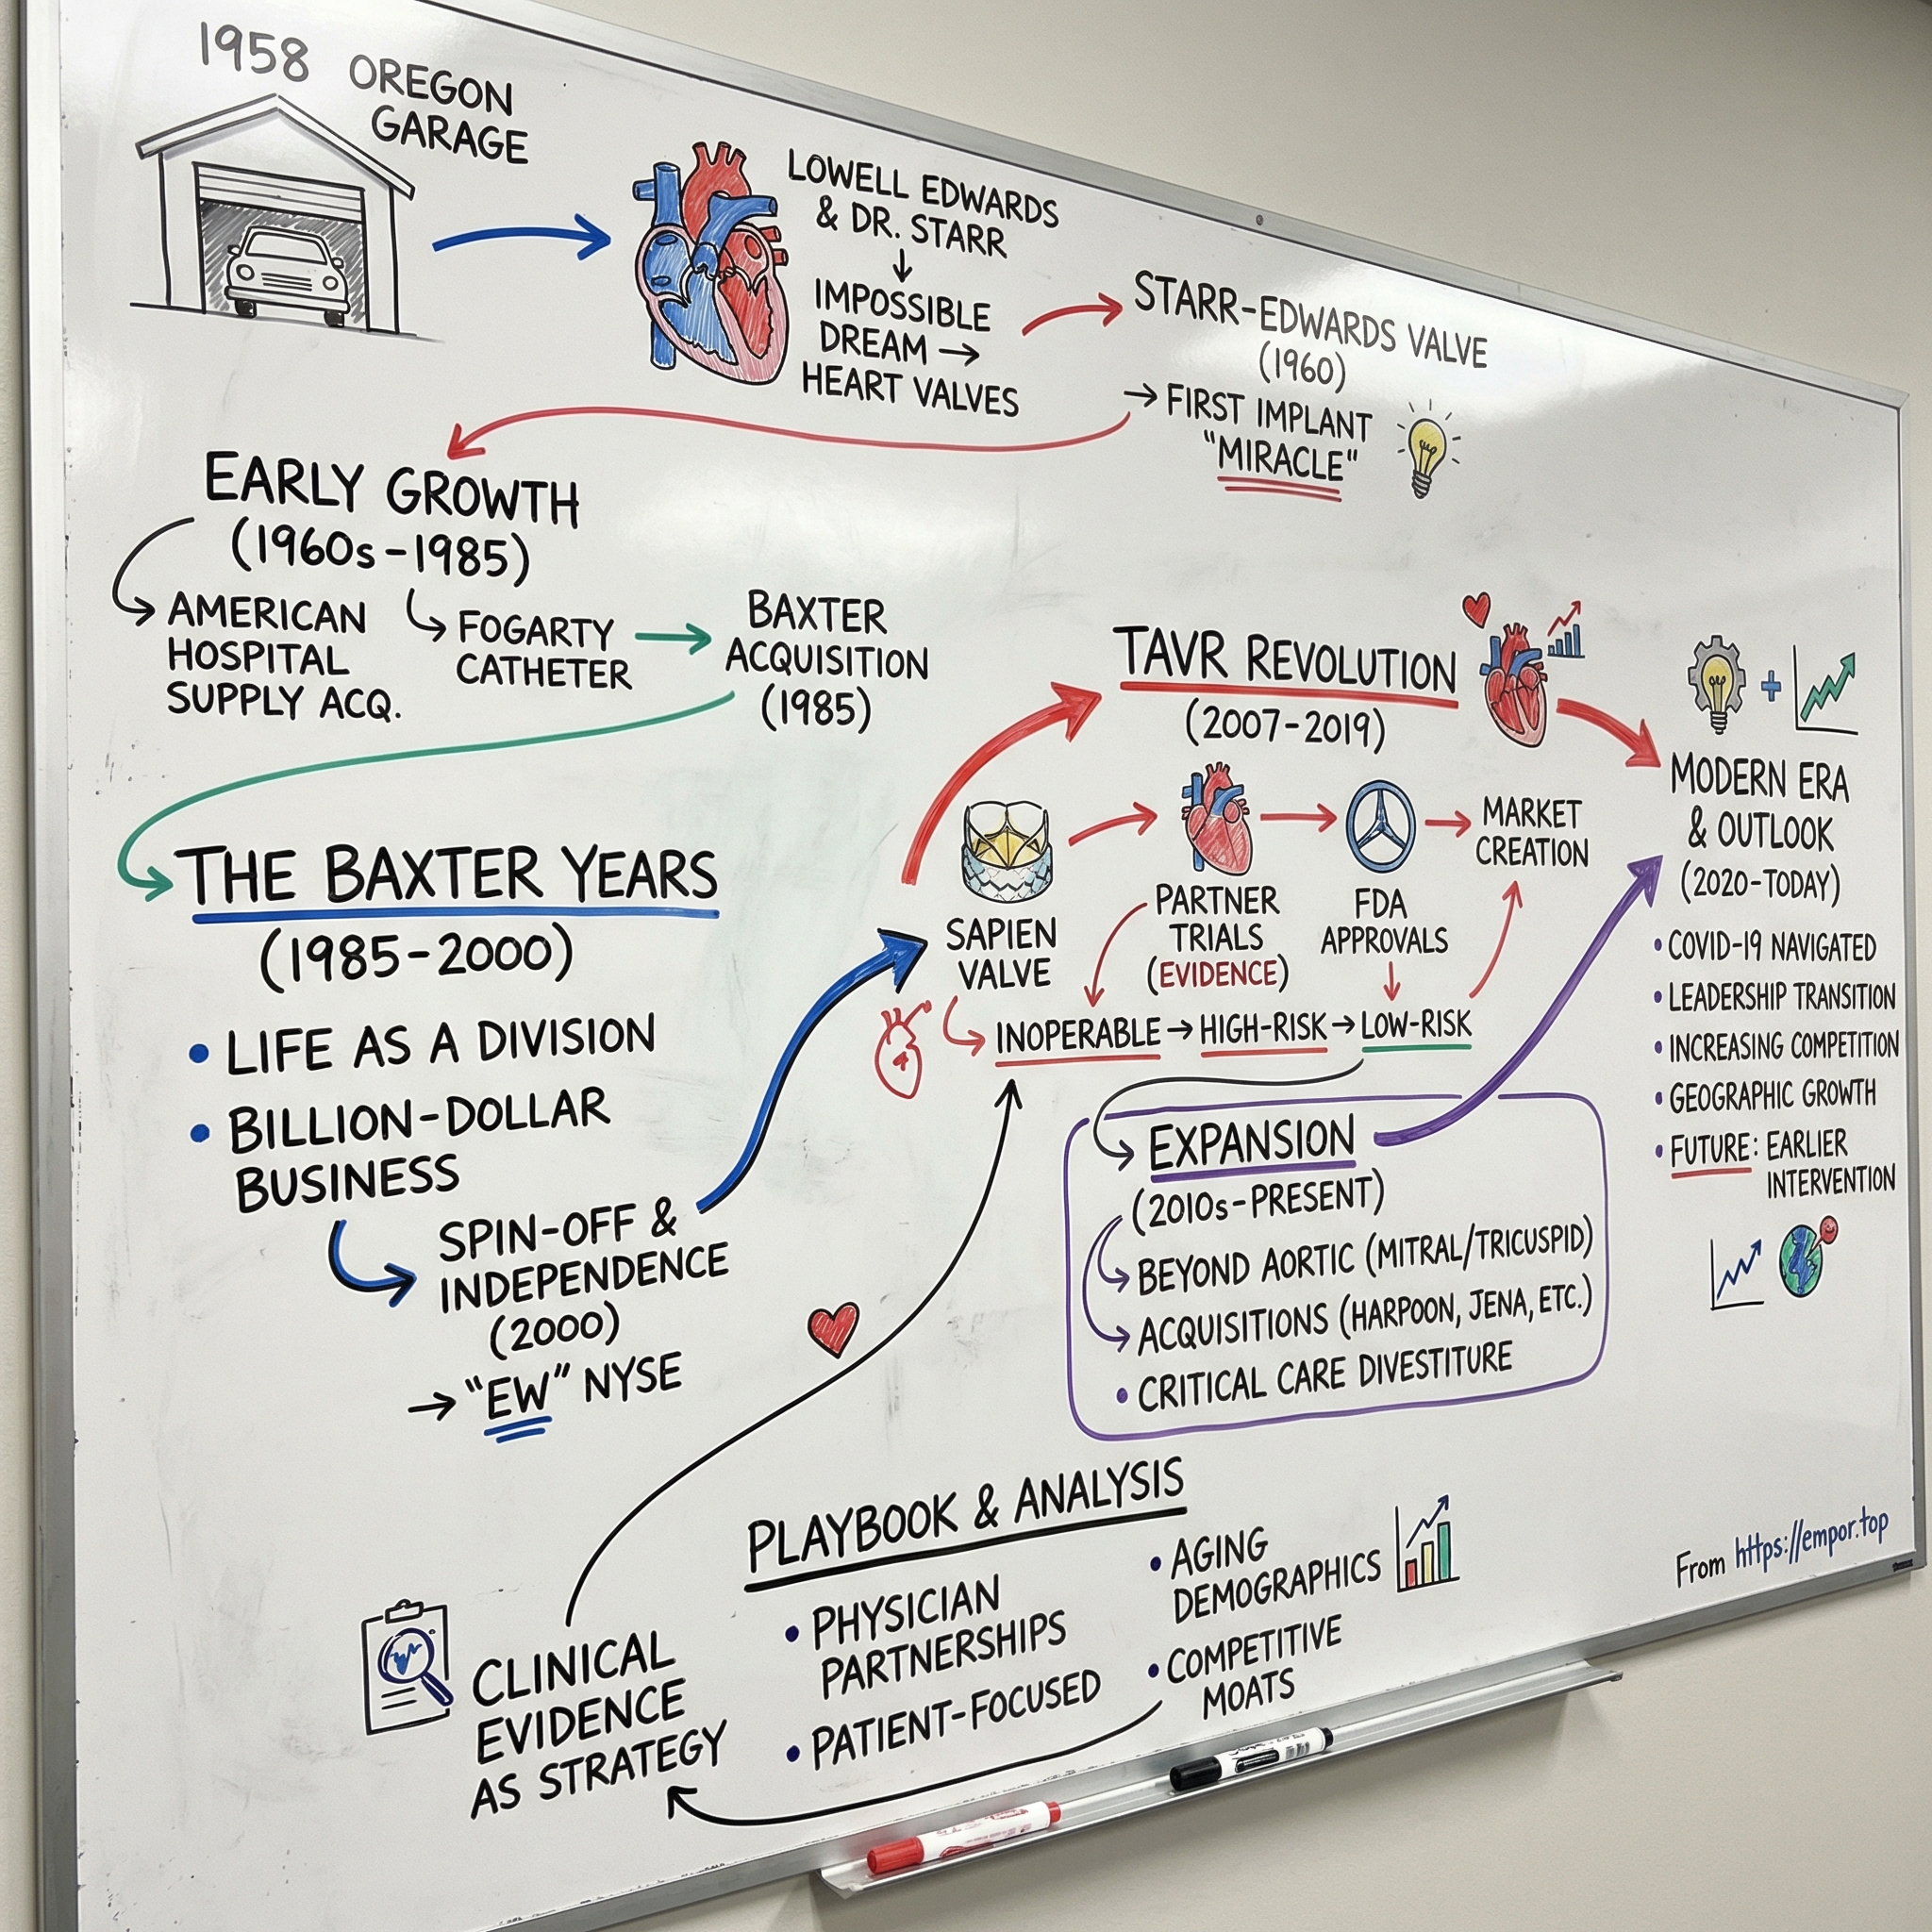
Edwards Lifesciences: The Heart Valve Innovation Story
I. Introduction & Episode Roadmap
There is a particular kind of company that investors often overlook because it operates behind a wall of medical acronyms. Edwards Lifesciences Corporation, listed on the New York Stock Exchange under the ticker EW, is one of them. Mentioning "TAVR"—transcatheter aortic valve replacement—at a dinner party might elicit blank stares. Explaining the procedure, however, changes the dynamic: a surgeon threads a collapsed artificial valve through an artery in a patient's leg, positions it inside a failing aortic valve, inflates a balloon to expand it, and enables the patient to walk out of the hospital the next day. That catheter-based procedure forms the core of the business.
Edwards operates as a structural heart disease pure-play with a market capitalization of roughly $40 billion, generating over $6 billion in annual revenue at gross margins between the high-70s and low-80s. That margin profile, typically associated with software firms, is earned by hand-sewing cow tissue onto metal frames.1 Unlike diversified medical technology peers, Edwards focuses exclusively on cardiac valve therapies rather than branching into spinal implants, diabetes pumps, or diagnostic testing.
This analysis examines a central question facing a business of this scale: how did a retired hydraulic fuel-pump engineer's quest to build a mechanical heart—funded with $5,000 out of a Southern California workshop—become the dominant franchise in transcatheter valve therapy, and why, at the peak of that dominance, is the company navigating the most complex growth reset in its twenty-six years as a public entity?
Both dynamics shape the current investment case. The overarching narrative highlights five key structural chapters:
Category creation, twice. Edwards did not merely enter the heart valve market; it helped establish the sector in 1960 by co-developing the first commercially successful prosthetic valve implanted in a human. Forty-four years later, the company repeated the pattern by acquiring a speculative startup and committing more than 15% of annual revenue to develop catheter-based valve replacement, aiming to replace open-heart surgery.
The conglomerate escape. From 1966 to 2000, the business operated as a subsidiary inside larger conglomerates—first American Hospital Supply, then Baxter International. A pivotal structural shift occurred when Edwards spun off to become an independent company, allowing management to allocate capital directly toward unproven transcatheter therapies rather than competing for budget as a line item on a distributor's P&L.
Clinical data as the moat. The PARTNER trial series—a multi-decade, multi-thousand-patient randomized clinical program—serves as a primary competitive moat. Replicating a comparable clinical database requires nearly a decade and hundreds of millions of dollars, during which Edwards continues to accumulate long-term patient follow-up data.
The reset. In July 2024, Edwards shares fell approximately 31% in a single session—among the largest one-day declines in large-cap medtech history—because management reduced its TAVR growth outlook by a few hundred basis points.4 Two months later, the company sold its Critical Care monitoring division to Becton Dickinson for $4.2 billion in cash.[^4] Having built a substantial war chest, management subsequently encountered antitrust regulatory hurdles that restricted spending on prime acquisition targets.
The management test. Bernard Zovighian assumed the CEO role in 2023 following a twenty-three-year tenure by his predecessor. Executive execution will be evaluated not on the inherited TAVR franchise, but on whether the company's transcatheter mitral and tricuspid valve portfolio matures into a genuine second growth engine.
Evaluating each of those claims requires examining both the company's historical achievements and its ongoing strategic challenges, starting in that Southern California workshop.
 Subscribe on LinkedIn
II. The Founding Story: Lowell Edwards & Dr. Albert Starr
In a Santa Ana, California workshop in the late 1950s, Miles Lowell Edwards worked among lathes and technical drawings. In his late fifties and officially retired, Edwards had built a career as an engineer in hydraulics, fuel pumps, and aviation components, accumulating 63 patents along the way.
He had a personal motivation stemming from childhood: a bout of rheumatic fever, a streptococcal infection that scarred heart valves and often led to premature valvular failure. Having spent decades designing pumps to move fluids under pressure, Edwards viewed the human heart through an engineering lens. He reasoned that because the heart functions as a pump, an artificial mechanical heart could be built.
Edwards set out to build a complete mechanical heart in his workshop during an era when open-heart surgery was still in its infancy.
The surgeon who said no
In 1958, Edwards presented his concept to Dr. Albert Starr, a 32-year-old cardiac surgeon at what is now Oregon Health & Science University. Starr listened to the proposal for a total artificial heart and offered a practical redirection: a total artificial heart was decades away, but designing a single replacement valve was achievable.
This advice proved pivotal. The initial breakthrough stemmed not from the engineer's original ambition, but from a clinician narrowing the scope to a device that could be manufactured, clinically tested, and safely implanted in a patient. Edwards accepted the redirection.
The initial capital commitment was $5,000 in 1958—a modest sum used to address a medical challenge that eventually laid the groundwork for a multi-billion-dollar global industry.
Solving the problem nobody could solve
The engineering requirements for an implantable valve were formidable, helping to explain the high gross margins the business commands decades later. A replacement heart valve must open and close roughly 100,000 times a day for decades inside a warm saline environment actively hostile to synthetic materials. Three primary failure modes had defeated previous attempts:
Hemolysis — the mechanical destruction of red blood cells as they pass through moving parts. Blood is a suspension of fragile living cells, and turbulent flow paths rupture them.
Thrombosis and rejection — the body's natural tendency to form blood clots on synthetic surfaces, creating a continuous risk of stroke.
Mechanical wear — structural failure of hinges or moving parts after millions of cycles, leading to sudden valvular failure.
Edwards addressed these challenges using principles of fluid dynamics rather than biological tissue: a silicone rubber ball enclosed within a metal cage. Forward blood pressure pushed the ball out of its seat to allow flow, while backpressure seated the ball to seal the valve. The design eliminated hinges and flexible leaflets.
In September 1960, Starr implanted the Starr-Edwards silastic ball-and-cage valve in the mitral position of a 52-year-old patient. The patient survived, marking the first commercially reproducible prosthetic heart valve implant in medical history. Some early recipients lived with their original devices for decades, including one documented patient who retained the same functional valve for 48 years.
The durability of this early device demonstrated that mechanical valve engineering could provide long-term therapeutic solutions.
Building the commercial machine
Edwards Laboratories established manufacturing in Santa Ana and developed a clinical sales model that became standard across the medical technology industry. Selling an implantable valve required intensive clinical education rather than conventional sales techniques.
Company representatives—trained clinical specialists—proctored procedures and assisted surgical teams inside operating rooms. Product development was conducted directly with physicians, and valve models carried the names of collaborating surgeons alongside the company brand.
This approach built institutional trust between Edwards and cardiac surgical teams. It also created a high-touch support model, as surgical procedures routinely required technical assistance from field representatives.
After operating as an independent enterprise for six years, Edwards Laboratories attracted acquisition interest from a major distributor.
The collaboration between Lowell Edwards and Albert Starr established a defining culture within the firm. Edwards deferred to clinicians on medical requirements, while Starr deferred to engineering expertise on technical feasibility. This approach guided subsequent product lines, including the Carpentier-Edwards, Cosgrove-Edwards, and Starr-Edwards series, where the collaborating surgeon's name preceded the company name.
This model created a durable asset: an established reputation among cardiac surgeons that Edwards prioritized physician-led design. In a market where hospitals serve as the economic buyer but surgeons act as key clinical decision-makers, that trust provided long-term commercial advantages. However, as transcatheter valve replacement emerged decades later, this surgeon-centric foundation created strategic friction when Edwards needed to engage interventional cardiologists—a distinct medical specialty with competing clinical domain boundaries.
III. The Conglomerate Era: American Hospital Supply & Baxter
In 1966, American Hospital Supply Corporation acquired Edwards Laboratories for approximately $11 million, renaming it American Edwards Laboratories. Externally, the acquisition provided the California innovator immediate access to a nationwide hospital distribution network. Internally, it initiated a 34-year period during which the business operated as a subsidiary within larger corporate entities—a structural dynamic that shaped its R&D priorities and capital allocation decisions for decades.
What the conglomerate got right
The conglomerate era enabled Edwards to expand beyond a single product line. Under American Hospital Supply, the business established a systematic platform for commercializing physician-led innovations.
The Fogarty catheter. Dr. Thomas Fogarty developed a balloon-tipped catheter designed to pass through blood vessels, inflate, and retract to extract blood clots without requiring major open vascular surgery. The technology established the foundation for subsequent balloon-based interventional procedures, including the delivery mechanisms later adapted for transcatheter valve replacement.
The Swan-Ganz catheter. Drs. Jeremy Swan and William Ganz created a flow-directed pulmonary artery catheter that allowed real-time hemodynamic monitoring of intra-cardiac pressures in conscious patients. The device established the field of modern hemodynamic monitoring and formed the foundation of Edwards' Critical Care division, which the company later sold to Becton Dickinson in 2024 for $4.2 billion.
Three of the company's four core franchises followed a consistent strategy: identify physician-invented concepts outside mainstream surgical practice, engineer them into standardized, manufacturable medical devices, and co-brand the resulting products alongside the inventing clinicians.
Baxter, and the capital allocation problem
In 1985, Baxter International acquired American Hospital Supply for approximately $3.8 billion, converting American Edwards into Baxter's Cardiovascular Group.
By the late 1990s, the division generated nearly $1 billion in annual revenue across an established clinical portfolio, including Bentley oxygenators, Carpentier-Edwards tissue valves, Cosgrove-Edwards annuloplasty rings, Fogarty catheters, Research Medical products, Starr-Edwards mechanical valves, and Swan-Ganz catheters. Each franchise maintained strong market positions in its respective surgical niche.
Despite this commercial footprint, the division faced internal capital allocation constraints. Baxter's core operations centered on high-volume, lower-margin hospital supplies, such as intravenous solutions, dialysis equipment, and commodity consumables. These businesses required continuous capital for manufacturing scale and logistics efficiency, yielding predictable short-term returns. By contrast, the Cardiovascular Group operated as a high-margin, specialized business requiring substantial, long-term research and development expenditures with uncertain commercial timelines.
When competing within a unified corporate budget, high-volume commodity divisions typically secure capital allocations over speculative, long-horizon medical device projects. For Edwards, funding a decade-long development program for transcatheter valve replacement—a concept then viewed skeptically by many cardiac surgeons—was difficult to justify under a conglomerate capital model focused on quarterly consolidated margins.
The decision to let go
By 1999, Baxter strategic planning prioritized core biopharmaceutical, renal, and hospital supply operations. Because selling the Cardiovascular Group would generate taxable gains and transfer key franchises to competitors, Baxter elected to spin off the business to shareholders in 2000 as an independent public company, Edwards Lifesciences.
Corporate breakups of this structure often unlock valuation multiple expansion and operational focus. Separating a high-margin, research-intensive medical device business from a capital-intensive parent enables management to direct cash flow toward multi-year clinical research programs rather than competing for internal corporate funding.
This capital reallocation proved crucial, but the 34 years under conglomerate ownership carried significant opportunity costs. Between 1966 and 2000, interventional cardiology emerged as a distinct discipline. Coronary balloon angioplasty entered clinical practice in 1977, followed by commercial coronary stents in the 1990s. Although Edwards possessed both heart valve manufacturing capabilities and balloon catheter expertise through its Fogarty franchise, the company did not combine these technologies to pioneer transcatheter valve replacement internally. Instead, an independent European venture ultimately commercialized the initial transcatheter aortic valve concept.
This delay illustrates how corporate capital structures shape product development. Division leadership operating under conglomerate margin targets faces structural disincentives to fund disruptive technologies that risk cannibalizing established surgical product lines or requiring protracted regulatory trials. The long-term cost of capital rationing inside a conglomerate rarely appears on an income statement as a write-off; it manifests when outside innovators pioneer an emerging product category.
IV. The Spin-Off & The Transcatheter Bet: Michael Mussallem & SAPIEN
On March 31, 2000, Baxter shareholders received one share of Edwards Lifesciences for every five Baxter shares they held, and the ticker EW began trading on the New York Stock Exchange. Revenue at separation was approximately $1 billion. The chairman and chief executive was Michael A. Mussallem, a chemical engineer who spent his career inside Baxter and would lead Edwards for the next twenty-three years.2
The initial period following the spin-off focused on operational stabilization rather than strategic expansion. Edwards inherited complex tax allocation agreements with Baxter, legacy product liability liabilities from earlier device lines, and the necessity of building corporate infrastructure as a standalone public entity. However, Mussallem recognized that while the core surgical heart valve business generated dependable cash flow with steady, mid-single-digit growth, it could not serve as the sole catalyst for long-term enterprise expansion.
The $125 million bet on a French cardiologist's heresy
In 2002, French interventional cardiologist Alain Cribier performed a groundbreaking procedure on a patient with severe calcific aortic stenosis who was considered ineligible for open-heart surgery. Cribier threaded a collapsed valve mounted on a balloon catheter through an artery into the heart, expanded it within the diseased native valve, and secured it in place.
Recognizing the commercial potential, Cribier and Dr. Martin Leon established Percutaneous Valve Technologies (PVT) to develop the catheter-based therapy. In 2004, Edwards acquired PVT for $125 million plus milestone payments.2
The structural difference between surgical and transcatheter approaches explains the clinical significance of the acquisition. Traditional valve replacement requires a sternotomy, cardiopulmonary bypass, and extended intensive care recovery. The transcatheter approach passes a collapsible frame through an artery, expanding it inside the existing valve structure to anchor the new device without opening the chest cavity. For elderly or frail patients facing severe aortic stenosis, this less invasive method offered a therapeutic option where none previously existed.
The internal fight
The acquisition met with internal resistance. In 2004, transcatheter valves remained an unproven technology facing widespread skepticism from cardiac surgeons—Edwards' primary customer base for four decades. The therapy proposed shifting procedures from surgical operating rooms to catheterization laboratories managed by interventional cardiologists, directly challenging established professional boundaries.
Despite internal pushback, Mussallem allocated over 15% of annual revenue to research and development at a time when commercial adoption was years away and no established market existed. Rather than a purely speculative venture, the decision reflected a calculated capital allocation strategy by an enterprise dedicated exclusively to structural heart therapies. Free from conglomerate oversight, management reasoned that if transcatheter valve replacement succeeded, securing category leadership would yield long-term competitive advantages.
PARTNER: turning a device into a standard of care
To commercialize the technology, Edwards launched the PARTNER trial series, one of the most comprehensive randomized clinical trial programs in medical device history.
PARTNER Cohort B, reported in 2010, evaluated patients with severe aortic stenosis who were ineligible for surgery and limited to medical management. The trial demonstrated an absolute reduction in one-year mortality of approximately 20 percentage points for transcatheter replacement compared to standard care, establishing clear clinical efficacy in high-risk populations.
The trial design itself served as a durable competitive moat. Edwards structured PARTNER as a randomized controlled trial following a progressive risk profile. The program began with inoperable patients—where clinical need was greatest and comparative efficacy clearest—and sequentially expanded into lower-risk patient populations as safety data accumulated. Each cohort's clinical results provided the regulatory and empirical foundation for subsequent trials.
This sequential approach created structural barriers for late entrants, who were required to replicate extensive clinical trials against an established transcatheter standard of care rather than non-surgical medical management.
The regulatory progression reflected this clinical sequence: - November 2011 — FDA approval of the Edwards SAPIEN valve for inoperable patients. - 2012 — expansion to high-surgical-risk patients. - 2016 — expansion to intermediate-risk patients. - August 2019 — approval of SAPIEN 3 and SAPIEN 3 Ultra in low-risk patients.[^12]
The 2019 low-risk approval expanded the addressable market significantly, establishing transcatheter replacement as a primary treatment option for the majority of aortic stenosis patients. Financially, TAVR transformed Edwards from a niche surgical manufacturer into a high-margin growth enterprise, generating a total shareholder return of more than 2,000% from its spin-off through its 2021 market peak.
However, this transition also signaled a shift in the business model. As transcatheter therapy expanded from a last-resort intervention to the standard of care, the addressable indication runway approached saturation. Subsequent top-line expansion depended increasingly on procedure volumes within existing indications, exposing Edwards to hospital capacity constraints and healthcare system bottlenecks.
Additionally, the concentration of financial returns highlights a strategic consideration for investors. While Mussallem's twenty-three-year tenure produced exceptional shareholder value, those returns stemmed primarily from the initial TAVR investment. Concurrent efforts to develop transcatheter mitral and tricuspid therapies faced longer development timelines and less predictable clinical outcomes. Consequently, evaluating Edwards' long-term growth profile requires distinguishing between the historical success of its aortic franchise and the execution risk inherent in expanding into adjacent structural heart markets.
V. Core Business Architecture & Segment Economics
To understand what Edwards is in 2026, start with what it deliberately stopped being.
In June 2024, Edwards agreed to sell its Critical Care product group — the hemodynamic monitoring business built on the Swan-Ganz lineage, including the HemoSphere platform — to Becton, Dickinson and Company for $4.2 billion in cash.6 The transaction closed on September 3, 2024.[^4]
Think about the symbolism. Edwards sold the direct commercial descendant of one of its founding inventions. The Swan-Ganz catheter had been in the portfolio, in one corporate parent or another, since the 1970s. Selling it was an explicit declaration: this company is now structural heart and nothing else.
That leaves three segments.
TAVR: the engine, maturing
Transcatheter aortic valve replacement generated approximately $4.49 billion in 2025, growing around 9% year over year, representing roughly three-quarters of company revenue.1 The flagship is the SAPIEN 3 Ultra RESILIA system.[^12]
The unit economics are where this gets interesting. A TAVR valve system carries a US average selling price in the range of roughly $30,000 to $32,500 — and gross margins on it exceed 80%. That is not a typo, and it is not gouging in any simple sense: the price reflects a decade of trial spend amortized across the installed base, the clinical support model embedded in every procedure, and the fact that the alternative — open-heart surgery — costs the health system substantially more in operating room time, ICU days, and complications.
Which points at the real customer economics. The hospital is not buying a valve; it is buying throughput. A TAVR procedure under conscious sedation runs roughly 45 to 60 minutes in a catheterization lab. Surgical aortic valve replacement consumes four to six hours of operating room time plus an intensive care stay. For a health system reimbursed on a diagnosis-related group basis, the transcatheter procedure converts a resource-intensive, low-margin surgical case into a high-throughput procedural case. Hospitals adopted TAVR aggressively not merely because it was better medicine — though it was — but because it was better capacity management.
Remember that, because it cuts both ways.
The pricing question deserves one more beat, because it is where the bear case tends to start. Is a $30,000 valve durable pricing or an invitation? The defensible answer is that TAVR pricing has held remarkably well for a decade in a two-player market — which tells you the competition has been fought on clinical evidence and operator preference rather than discount sheets. That discipline is a feature of the industry's structure, not a law of nature. It persists as long as the two platforms remain clinically differentiated enough that hospitals cannot treat them as interchangeable. The moment outcomes converge to the point where a procurement committee can credibly say "either one works for this patient," the negotiation changes character entirely. Nothing in the current data says that moment has arrived. Nothing says it cannot.
TMTT: the growth story that must work
Transcatheter Mitral and Tricuspid Therapies generated $550.6 million in 2025, up approximately 56% year over year, with management guiding to $740–$780 million in 2026 and a stated ambition of over $2.0 billion by 2030.1
Three products carry it. PASCAL Precision performs edge-to-edge repair — clipping together the leaflets of a leaking mitral or tricuspid valve so they seal. EVOQUE replaces the tricuspid valve entirely; it received FDA approval in February 2024 as the first transcatheter tricuspid valve replacement system cleared in the United States.[^10] SAPIEN M3 extends the transcatheter replacement concept to the mitral position.
Why is the tricuspid valve suddenly interesting after being ignored for a century? Because it was genuinely ignored. Severe tricuspid regurgitation — the "forgotten valve" leaking backward — was long treated as a condition you manage with diuretics until the patient's liver and kidneys fail. Surgical repair carried high mortality in this frail population, so referral patterns simply never developed. EVOQUE creates a therapy where none existed, which is the purest form of category creation.
But categories created from zero grow from zero, and they grow slowly at first, because the bottleneck is not the device — it is the referral pathway, the imaging expertise required to assess these anatomies, and reimbursement.
The percentage growth rate here needs careful handling. Fifty-six percent growth on a $350 million base is a different fact from 56% growth on a $3 billion base, and the segment is closer to the former. At roughly 9% of company revenue, TMTT would need to roughly quadruple to reach the stated 2030 ambition — implying sustained growth in the mid-to-high 20s annually for five straight years, off a base that is itself still being built. That is achievable. It is not assured, and the guidance range management provided for 2026 implies a deceleration from 2025's rate, which is the normal arithmetic of a scaling business and should not be mistaken for a stumble when it appears in the numbers.
Surgical Structural Heart: the quiet anchor
The legacy surgical business contributed roughly $1.0 billion, about 17% of sales, growing at mid-single digits. Its products — the INSPIRIS RESILIA aortic valve, the KONECT RESILIA tissue conduit — carry the proprietary RESILIA anti-calcification tissue treatment.
This segment does something underappreciated: it funds the experiments. It is a high-margin, low-drama cash generator that also keeps Edwards embedded with cardiac surgeons — the other half of the "Heart Team" that must sign off on every transcatheter case.
The Heart Team, and why it constrains everything
Regulatory and reimbursement frameworks in the United States require that TAVR decisions involve both an interventional cardiologist and a cardiothoracic surgeon. This was designed as a patient-safety mechanism and it functions as one. It also functions as a throughput ceiling: every case requires two scarce specialists, a cath lab slot, a pre-procedure CT scan, an echocardiogram, and a structural heart coordinator to shepherd the patient through.
Edwards can manufacture as many valves as the world wants. It cannot manufacture cath lab hours. For investors, that is the single most important structural insight about this business, and in 2024 the market learned it the hard way.
VI. Competitive Landscape, Industry Structure & The 7 Powers
Strip away the clinical vocabulary and the global structural heart market is an oligopoly with one clear leader and one serious challenger.
Medtronic is the principal TAVR rival, holding roughly 30–35% of the global market with its self-expanding Evolut platform, including Evolut FX and Evolut PRO+. The architectural difference matters clinically and competitively: Edwards' SAPIEN is balloon-expandable—the valve is crimped onto a balloon and deployed through inflation, yielding a precise, controlled placement. Medtronic's Evolut is self-expanding—made of nitinol, a shape-memory alloy that unfurls to its programmed geometry as it leaves the sheath. Self-expanding valves handle certain anatomies better and offer superior hemodynamics in small annuli; balloon-expandable valves offer more predictable positioning and historically lower pacemaker rates. Neither wins outright, and both maintain devoted clinician followings.
Abbott leads mitral repair with MitraClip, the product that established transcatheter edge-to-edge repair as a category and against which PASCAL competes directly. Abbott also fields Navitor in TAVR and TriClip in tricuspid, making it Edwards' most complete competitive mirror.
Boston Scientific markets the ACURATE neo2 TAVR platform, concentrated primarily in Europe and selected international markets.
Testing the 7 Powers, not reciting them
Hamilton Helmer's 7 Powers framework is useful here only if applied critically rather than as a box-checking exercise.
Process Power — strong, and genuinely hard to copy. Edwards' valves are manufactured by hand-sewing bovine pericardial tissue onto cobalt-chromium frames, with the tissue treated using the proprietary RESILIA anti-calcification process. This is not a patent that expires; it is accumulated manufacturing know-how—tissue selection, chemical treatment protocols, and the skill of trained craftspeople. A competitor cannot reverse-engineer a finished valve to replicate the underlying process. Peers have needed years to approach equivalence. Verdict: real.
Cornered Resource — real, but decaying at the edges. The PARTNER dataset is a genuine asset: over fifteen years of randomized, multi-center evidence with durability follow-up out to ten years. A new entrant needs roughly $500 million and seven to ten years to build a comparable evidentiary base. But note the limit—Medtronic has also run large randomized programs and also possesses long-term data. The cornered resource excludes startups, but it does not exclude the incumbent duopolist. Verdict: real against new entrants, largely neutralized against Medtronic.
Switching Costs — moderate, and frequently overstated. Operators are trained and proctored on a specific deployment technique; moving from balloon-expandable to self-expanding requires different sizing logic, sheath management, and pacing protocols. That creates operational friction, but not true lock-in. Many high-volume centers deliberately maintain expertise in both platforms to match device design to patient anatomy—and dual-platform centers are precisely the ones with negotiating leverage. Verdict: friction, not a wall.
Scale Economies — present in an unusual form. The clinical specialist model places Edwards personnel physically inside catheterization labs. At scale, this provides a field coverage advantage—denser presence, faster response, and better case support than a subscale entrant can afford. However, it is a variable cost that scales with procedure volume rather than revenue, meaning it fails to deliver classic operating leverage. Verdict: a distribution moat that remains expensive to maintain.
Counter-Positioning — the most-claimed and least-proven. The argument holds that pure-play focus enables Edwards to commit roughly 17–18% of revenue to structural heart R&D while Medtronic and Abbott split capital across diverse medical portfolios. That focus is real, but counter-positioning in Helmer's sense requires that the incumbent be unable to respond without damaging its own core business. Nothing prevents Medtronic from funding structural heart adequately—and it has done so repeatedly. Pure-play focus provides genuine organizational alignment and speed, but it is not a structural trap for diversified competitors. Verdict: overstated as counter-positioning; real as organizational focus.
Brand — real among physicians, irrelevant to patients. Sixty-six years of surgeon relationships represent a genuine asset among clinical decision-makers. However, brand equity alone does not restrain a hospital procurement committee conducting a competitive tender.
Porter's five forces, briefly
New entrants: very low threat. Capital and clinical trial requirements are prohibitive, and the regulatory evidence threshold rises continuously. Buyers: moderate to high, and rising. Group purchasing organizations and European national tender systems apply persistent pricing pressure; physician preference mitigates but does not eliminate this constraint. Suppliers: low. Bovine pericardium is sourced under closed-herd controls—a quality and traceability requirement rather than a pricing bottleneck. Substitutes: low for the core indication; untreated severe aortic stenosis carries roughly 50% two-year mortality, and open surgical replacement is significantly more invasive. Rivalry: high but disciplined. Edwards and Medtronic compete on clinical data and operator preference far more than on headline pricing—a structural feature that preserves segment profitability, provided it does not deteriorate.
The uncomfortable synthesis: Edwards' moat is formidable against new entrants, but far less protective against its primary competitor. That dynamic was manageable while the category grew at double digits, but it became a central question as market expansion moderated.
One additional structural feature governs how this duopoly behaves. Neither Edwards nor Medtronic benefits from a price war, because the binding constraint on procedure volume is not price—it is clinical capacity. In traditional markets, price cuts expand overall demand. Here, lower prices cannot drive incremental market expansion, because volume is rationed by catheterization lab availability and Heart Team scheduling rather than device cost. A price discount simply transfers margin to hospitals without increasing procedure counts. This capacity constraint underpins pricing discipline, making it more durable than mere tactical restraint. Crucially, it also means pricing discipline could weaken if healthcare system capacity constraints ease—an economic paradox where operational expansion in hospital throughput could inadvertently pressure device pricing.
VII. The Modern Era: CEO Bernard Zovighian & Capital Allocation Inflection
In May 2023, after twenty-three years under Michael Mussallem, Edwards handed the chief executive role to Bernard J. Zovighian, a twenty-year company veteran who had previously run the Transcatheter Mitral and Tricuspid business and, before that, Critical Care. Scott Ullem remained chief financial officer.
Succeeding a long-tenured CEO is among the most demanding transitions in corporate leadership. Zovighian inherited a business at its peak, characterized by a dominant franchise, a pristine balance sheet, and a valuation premised on the assumption that the prior decade's growth momentum would persist. Fourteen months later, that assumption faced a sharp re-evaluation.
July 24, 2024
On that day, Edwards reported second-quarter results that missed revenue expectations and, more consequentially, reduced full-year TAVR growth guidance from a range of 8–10% down to 5–7%.4
The stock fell approximately 31% in a single session, erasing roughly $16 billion in market value.4
The arithmetic illustrates a fundamental market repricing. Management trimmed the growth outlook on roughly three-quarters of revenue by three percentage points, yet equity markets erased nearly a third of the company's valuation. That divergence signaled that investors were repricing a core narrative rather than a single quarterly forecast—shifting from viewing Edwards as a high-visibility secular compounder to viewing it as a maturing franchise with an unproven second act.
What actually happened
Management attributed the deceleration primarily to hospital capacity constraints rather than weakening patient demand. Catheterization lab scheduling was saturated, echocardiography and CT workups faced backlogs, and structural heart coordinators—specialized nurses who shepherd patients through the pathway—were in short supply. Simultaneously, hospitals were prioritizing competing procedural categories for operating rooms and staff. Layered on top was incremental competitive pressure from Medtronic's Evolut FX platform.4 On the earnings call, executive framing emphasized hospital-side operational bottlenecks, asserting that underlying TAVR demand remained intact—a claim that sell-side analysts pressed repeatedly, probing whether competitive share loss was being under-weighted relative to capacity.7
Evaluating this explanation reveals two competing perspectives. In support of management's thesis, the capacity constraint aligns with the structural requirement for dual-specialist Heart Teams, a bottleneck corroborated by hospital staffing data. Conversely, after years of framing TAVR as a vast, underpenetrated market, shifting the narrative to throughput constraints introduced an explanation difficult to verify in the short term. It also partially downplayed competitive dynamics, which received less emphasis from executives than from analytical inquiries.
Ultimately, management's capacity diagnosis was substantially accurate, though incomplete in addressing competitive dynamics. However, the critical test of executive credibility lay in execution. Rather than treating the bottleneck as an external excuse, Edwards responded by investing in hospital workflow support, funding clinical coordinator roles, and expanding referral support. Concurrently, management accelerated a broader strategic restructuring.
The pure-play pivot, and the cash
The divestiture of the Critical Care division had been arranged prior to the July earnings announcement and closed shortly thereafter, generating $4.2 billion in cash proceeds and leaving Edwards with essentially no net debt.[^4]6 Management subsequently deployed this capital into adjacent structural heart opportunities:
Innovalve Bio Medical (July 2024), acquired for approximately $300 million in cash, added early-stage transcatheter mitral valve replacement technology.
Endotronix (July 2024), acquired to enter pulmonary artery pressure monitoring for heart failure management via the Cordella system—a sensor implanted in the pulmonary artery that allows clinicians to detect rising pressures days before clinical decompensation.
Both acquisitions represent early-stage assets that do not contribute materially to near-term revenue. They function as strategic options whose long-term value will depend on commercialization progress versus potential goodwill impairments over a multi-year horizon.
The Endotronix acquisition presents a notable strategic juxtaposition relative to the stated pure-play focus. Edwards completed the divestiture of its Critical Care monitoring unit on the principle that monitoring fell outside its structural heart mandate, yet acquired a distinct monitoring platform weeks later, arguing that outpatient heart failure management represents an adjacent opportunity. While acute ICU hemodynamic monitoring and chronic outpatient sensing involve distinct commercial models, the dual transactions highlight how strategic definitions of core focus were adapted within a single quarter.
The antitrust wall
As management sought to expand its structural heart footprint, capital deployment encountered regulatory resistance.
In July 2024, Edwards agreed to acquire JenaValve Technology for $945 million. JenaValve's platform targeted transcatheter treatment of aortic regurgitation—a leaking aortic valve rather than a narrowed one—an indication with no approved transcatheter option in the United States, and one where Edwards' balloon-expandable design faced anatomical limitations due to the lack of calcified anchoring structures.
The Federal Trade Commission filed a lawsuit to block the deal, asserting that Edwards was acquiring its primary prospective competitor in aortic regurgitation, while noting that Edwards had separately acquired rights to JC Medical, another AR-focused developer. In January 2026, a U.S. District Court granted the FTC a preliminary injunction blocking the merger.[^5] Edwards subsequently cancelled the $945 million transaction.5
In July 2026, the FTC secured a $12 million civil penalty against Edwards for failing to report the JC Medical transaction under Hart-Scott-Rodino premerger notification requirements.[^6]
While a $12 million penalty is immaterial relative to the company's cash reserves, the enforcement action carries broader governance implications. The regulatory finding that a transaction was structured in a manner that bypassed premerger review signals heightened antitrust scrutiny and raises questions regarding regulatory compliance discipline during aggressive capital deployment.
Compensation and governance
In 2025, Zovighian's total compensation reached approximately $17.5 million, with over 90% structured as performance-based pay tied primarily to long-term equity metrics, including relative total shareholder return and return on invested capital.2 Executive stock ownership guidelines mandate holding 50% of net vested shares until designated ownership multiples are satisfied.
Aligning compensation with relative TSR and ROIC provides structural accountability against capital allocation efficiency. However, evaluating relative TSR against a broad medtech index leaves performance benchmarks sensitive to sector-wide valuation cycles alongside company-specific operational execution.
VIII. Historical Falsification Layer: Testing Thesis Claims
The investment case for Edwards rests on four load-bearing claims. Testing each against the company's operational record reveals where the bull case holds—and where disconfirming evidence requires a narrower perspective.
Claim 1: TAVR is a durable double-digit secular growth franchise
The disconfirming evidence is management's own guidance. The 2024 reduction in TAVR growth guidance from 8–10% to 5–7% was not an external shock; it signaled to investors that constraints on the dominant franchise were structural and largely outside the company's direct control.4 Growth decelerated to the mid-single digits during that period, and the market's reaction—a 31% single-day decline—reflected recognition that hospital capacity limits were binding.
Evaluating the evidence: This evidence is material, directly involves the core business under current management, and carried substantial valuation consequences rather than representing a routine quarterly variation.
Verdict: The claim is rejected in its strong form and survives only in a narrowed version. TAVR is not a double-digit secular grower. It is a high-market-share franchise bounded by global structural heart procedural capacity—a variable Edwards influences through hospital support but does not control. A rebound to approximately 9% growth in 2025 demonstrated that deceleration was not terminal, but it does not restore the original double-digit growth thesis.
What would confirm or falsify the narrowed claim: Sustained TAVR volume growth above 8% across multiple consecutive quarters following clinical guideline updates that incorporate EARLY TAVR trial data for asymptomatic patients. If expanding the eligible patient population fails to drive growth beyond high single digits, the procedural capacity ceiling will be confirmed as binding.
Claim 2: Edwards can replicate the TAVR playbook in mitral and tricuspid
This claim carries the greatest valuation weight and has the longest operational record of disconfirming evidence.
The evidence: Edwards' initial transcatheter mitral replacement program, Fortis, was halted in 2015 following thrombus formation issues. The company acquired Harpoon Medical in 2017 for approximately $100 million to pursue beating-heart mitral repair, which required years to yield commercial contributions. Development timelines for SAPIEN M3 similarly extended beyond early projections. Collectively, Edwards has pursued transcatheter mitral therapies for over a decade with modest commercial revenue relative to the capital invested.
The underlying anatomical challenge: The aortic valve is a symmetric, heavily calcified ring, providing a rigid anchoring surface for balloon-expanded frames. By contrast, the mitral valve is an asymmetric, soft, dynamically moving structure lacking a calcified anchor and attached to the ventricular wall by delicate chordae. Deploying a prosthetic device in the mitral position carries the risk of obstructing the left ventricular outflow tract, creating a far more complex fluid-dynamics and engineering problem than aortic valve replacement.
Evaluating the evidence: Over an eleven-year span, product development across mitral indications highlights structural engineering hurdles that differ fundamentally from the aortic experience.
Verdict: The claim is narrowed substantially. Edwards has demonstrated execution capability in adjacent structural heart categories, evidenced by EVOQUE's approval as a first-in-class tricuspid therapy and the segment's 56% revenue expansion in 2025.1[^10] However, development history refutes the assumption that TMTT can match TAVR's adoption trajectory. The segment represents a multi-year clinical progression where tricuspid therapy leads mitral development, and where success in tricuspid replacement does not directly solve the distinct anatomical challenges of the mitral valve.
Falsification metric: TMTT achieving a $2.0 billion annual revenue run-rate by 2030 with positive segment operating margins. The margin qualification is critical: expanding segment revenue while remaining cash-flow negative would fail to replicate the financial characteristics of the TAVR franchise.
Claim 3: Disciplined M&A can buy growth in adjacent indications
The evidence is definitive and recent. The regulatory block of the JenaValve transaction was not a protracted negotiation or temporary delay; a federal court granted a preliminary injunction, leading Edwards to abandon the acquisition.[^5]5 The Federal Trade Commission subsequently imposed a $12 million civil penalty for Hart-Scott-Rodino filing omissions.[^6]
Verdict: The claim is rejected for late-stage assets in aortic therapies. The antitrust enforcement logic—that Edwards holds a dominant market position in transcatheter aortic replacement and sought to acquire its primary prospective competitor in an adjacent aortic indication—applies to future attempts to purchase advanced aortic assets. For late-stage aortic targets, external acquisition channels are effectively closed.
Capital deployment is restricted primarily to early-stage, venture-style acquisitions, exemplified by the Innovalve transaction. While such early-stage deals remain below antitrust thresholds, they are unlikely to yield material commercial revenue for several years. Consequently, financial models must treat enterprise growth as predominantly organic.
Falsification metric: Meaningful commercial revenue contribution from Innovalve and Endotronix without triggering goodwill or intangible asset write-downs. Impairment charges on either asset would indicate that capital from the Critical Care divestiture was deployed into unproductive development options.
Claim 4: Patents and IP prevent competitor entry
The evidence: Edwards and Medtronic engaged in multi-jurisdictional patent litigation for years, ultimately resolving their disputes in 2014 through a cross-licensing settlement rather than market exclusion. Patent enforcement failed to prevent competitor entry, as Medtronic subsequently captured approximately one-third of the global TAVR market.
Verdict: The claim is rejected. Intellectual property in transcatheter valves functions as a licensing mechanism and negotiating tool rather than an entry barrier. Primary competitive protection stems from clinical trial databases, specialized manufacturing expertise, and physician proctoring networks. Consequently, patent protection does not serve as a primary moat element in the investment thesis.
Falsification metric: Sustained global TAVR market share above 60% against competing platforms such as Evolut FX and Navitor. A drop in market share below the mid-50% range would indicate that clinical evidence and training moats are experiencing erosion.
IX. Analysis & Bear vs. Bull Case
Stripping away strategic frameworks leaves two central questions for investors: what drives Edwards' next phase of growth, and what factors could derail it?
Why it wins
Indication expansion into asymptomatic disease. The EARLY TAVR trial targeted a patient population largely overlooked by traditional clinical practice: individuals with severe aortic stenosis who have not yet developed symptoms. Standard care has historically relied on watchful waiting, monitoring patients until symptoms manifest before intervening. Clinical guidelines shifting toward earlier intervention would expand the eligible patient pool significantly by capturing severe cases that currently go unreferred. Asymptomatic indication expansion represents the largest identifiable catalyst for incremental TAVR volume and offers a potential offset to hospital capacity constraints, as elective procedures for healthier patients are easier to schedule. However, expanding the addressable population does not automatically resolve underlying throughput bottlenecks, as procedure expansion remains constrained by available catheterization laboratory hours and specialized personnel.
Tricuspid as genuine first-mover territory. EVOQUE holds a unique market position as the first system to secure FDA approval for transcatheter tricuspid valve replacement.[^10] In a category lacking an established standard of care, the pioneer offering an approved device and clinical training program defines referral pathways, imaging protocols, and physician adoption patterns. Establishing early clinical infrastructure creates a structural advantage as tricuspid therapy adoption expands.
Balance sheet optionality. Edwards maintains essentially no net debt, several billion dollars in cash and investments following its Critical Care divestiture, and annual R&D expenditure reinvestment at roughly 17% to 18% of revenue.1[^4] This liquidity profile allows the company to fund internal research and clinical development for years without relying on external capital markets, while providing flexibility to repurchase shares during valuation downturns. While balance sheet strength does not directly generate top-line growth, it mitigates solvency and refinancing risks during strategic transitions.
Manufacturing and supply chain resilience. Edwards operates a specialized tissue supply chain utilizing closed-herd bovine sourcing with full origin traceability, supported by a specialized manufacturing workforce requiring years of training in precision hand-sewing. During global supply chain disruptions in the early 2020s, vertically integrated tissue valve operations demonstrated greater resilience than medical technology peers reliant on contract electronics suppliers. This operational control has contributed to gross margin stability across broader industry input-cost pressures.
What breaks it
A persistent capacity ceiling. If developed-market TAVR growth stabilizes at mid-single-digit rates, the enterprise valuation framework shifts permanently. A company historically valued at 35 to 40 times earnings as a secular growth compounder re-rates toward the 20 to 25 times earnings range typical of mature medical technology franchises. The stock's July 2024 market decline illustrated how rapidly multiple compression occurs when growth expectations moderate.
Regulatory constraints on M&A expansion. With regulatory enforcement blocking major acquisitions in the aortic segment, incremental growth within core therapies relies almost entirely on internal research and development. Relying on organic innovation exposes Edwards to extended development timelines while competing against diversified peers like Medtronic, which face fewer structural portfolio concentration risks.
Reimbursement and pricing pressures. U.S. diagnosis-related group payment structures and European national tendering frameworks create continuous downward pressure on medical device pricing. Device pricing exceeding $30,000 alongside gross margins above 80% presents an attractive target for cost-containment initiatives by healthcare systems facing fiscal constraints. While physician preference has historically insulated device pricing, that pricing power risks erosion as clinical outcomes between competing transcatheter platforms converge, with European average selling prices serving as a leading indicator of global pricing trends.
Revenue concentration risk. Generating approximately three-quarters of revenue from a single procedure type leaves the business without a structural hedge against category-specific disruptions. Concentrating capital in structural heart therapies delivers operational focus, but it leaves enterprise cash flows vulnerable to sector-specific demand shocks, regulatory shifts, or competitive inroads in TAVR.
Long-term clinical durability uncertainties. The lowest-probability but highest-consequence risk for an implantable device manufacturer is unexpected long-term structural deterioration. Transcatheter valves are increasingly implanted in younger, lower-risk patients with life expectancies extending two decades or more beyond current ten-year clinical follow-up data. While the RESILIA tissue technology was engineered to retard calcification and initial clinical data remains favorable, definitive fifteen- to twenty-year structural durability profiles in younger cohorts will not emerge until the 2030s. Any adverse durability signal would impact valuation across the entire transcatheter category.
The activist stress test
An institutional activist or focused investor evaluating Edwards' strategy would likely highlight three primary areas of capital allocation and operational performance:
Capital deployment discipline. Following the $4.2 billion sale of Critical Care, Edwards allocated funds into early-stage acquisitions like Innovalve and Endotronix while the $945 million JenaValve transaction was blocked by regulatory intervention. Critics argue that holding substantial cash reserves for speculative early-stage ventures yields suboptimal risk-adjusted returns when large-scale acquisitions face regulatory barriers and internal R&D is already fully funded. While management views early-stage investments as essential pipeline optionality, historical precedents such as the Fortis and Harpoon acquisitions indicate that converting early-stage technologies into commercial revenue requires extended development timelines.
Research and development returns. Annual R&D expenditures approaching $1 billion coincide with mid-to-high single-digit growth in the core TAVR franchise. Optimistic forecasts emphasize that TMTT expansion—growing 56% in 2025—validates this investment trajectory. Conversely, skeptical analyses note that TMTT contributes under 10% of total revenue after more than a decade of capital investment. Validating this R&D productivity depends on whether TMTT achieves meaningful enterprise scale alongside positive segment operating margins.
Guidance transparency and narrative alignment. The divergence between management's pre-2024 growth outlook and the subsequent disclosure of hospital capacity bottlenecks affected market credibility. Subsequent guidance practices have adopted wider forecast ranges and reframed growth around clinical workflow expansion rather than passive market penetration. Reestablishing long-term valuation premiums requires maintaining consistent execution across both favorable and challenging operating environments.
The KPIs that actually matter
Evaluating the long-term investment case requires monitoring three core operational metrics:
1. Constant-currency quarterly TAVR revenue growth. Evaluating TAVR sales trajectory against the 5% to 7% baseline established during the 2024 reset and the high-single-digit growth achieved in 2025 indicates whether hospital capacity bottlenecks are easing, stabilizing, or tightening.
2. TMTT top-line expansion and segment operating margin. Tracking revenue alongside operating margins determines whether TMTT growth reflects sustainable commercial adoption or requires heavy promotional and clinical subsidies to expand market share.
3. Global TAVR market share relative to Medtronic. Market share trajectory serves as the primary indicator of competitive moat strength, particularly in European and Japanese markets where tendering dynamics and platform competition frequently precede U.S. market trends.
X. Playbook: Business & Innovation Lessons
Five transferable lessons emerge from this history, and only one is specific to heart valves.
1. In regulated medicine, the randomized trial is the moat. Patents expire and become cross-licensed, a reality Edwards encountered in its multi-year patent disputes with Medtronic. Proprietary manufacturing expertise provides a baseline advantage, but the primary barrier preventing competitor entry is a decade of prospective, randomized, multi-center clinical data demonstrating long-term durability. Physicians are cautious about adopting unproven implantable devices, and capital alone cannot compress a ten-year follow-up window into three years. For investors, clinical trial expenditure in medical technology—often viewed as a near-term margin drag—frequently represents the construction of a durable competitive moat, provided trials are randomized and outcome-powered rather than observational registries.
2. Category creation requires building the ecosystem, not just the device. Edwards did not commercialize transcatheter aortic valve replacement simply by selling hardware. The company actively established the multi-specialty Heart Team model, funded structural heart coordinator positions within hospitals, constructed global physician training facilities, and placed clinical specialists inside catheterization laboratories. That infrastructure enabled widespread adoption, yet it also created the operational bottleneck that constrained growth in 2024. Establishing a clinical ecosystem does not grant ownership or control over hospital operational capacity, meaning both rapid adoption and procedural ceilings originate from the same structural foundation.
3. The spin-off thesis requires a dedicated capital catalyst. Separating a high-margin, research-intensive medical device division from a lower-margin corporate parent unlocked substantial enterprise value. Under conglomerate ownership at Baxter, internal capital allocation guidelines would rarely have approved the acquisition of Percutaneous Valve Technologies or sustained fifteen years of trial expenditures for PARTNER. However, the success of the spin-off depended on a specific condition: the independent entity possessed an identified, capital-intensive technology that conglomerate capital allocation had suppressed. A corporate spin-off lacking a clear investment catalyst risks creating a smaller standalone entity burdened by higher administrative overhead. Enterprise value was generated by executing the strategic bet; independence provided the corporate governance structure to fund it.
4. Category dominance creates regulatory acquisition limits. Once a specialized medical device maker commands a major share of a therapeutic category, antitrust regulators may restrict acquisitions of prospective competitors in adjacent indications. Furthermore, market definitions can be drawn tightly around specific conditions, as demonstrated when the Federal Trade Commission challenged the acquisition of transcatheter therapies for aortic regurgitation.[^5] Companies approaching high market share must evaluate regulatory limits before entering merger agreements. Market leadership shifts large-scale acquisitions from a primary expansion tool into a regulatory liability, forcing organizations to cultivate internal research and development capabilities before acquisition channels become constrained.
5. Growth trajectories inherit third-party operational constraints. Superior clinical data, device efficacy, and procedural cost-effectiveness cannot bypass physical throughput limits when health systems face facility and staffing bottlenecks. Any enterprise whose product is consumed within a customer's constrained workflow—such as surgical implants requiring specialized catheterization labs, industrial machinery reliant on certified installers, or enterprise software requiring scarce technical consultants—inherits the operational capacity curve of that third party. Evaluating a high-growth franchise requires determining whether end customers possess the physical capacity to absorb doubled procedure or product volume. If operational constraints prevent absorption, market potential figures in corporate presentations describe theoretical demand rather than near-term realizable revenue.
XI. Epilogue & Future Outlook
Return to the constraint that defines this company, because its future trajectory runs straight through it.
Edwards' core challenge in 2026 is not a lack of patient need. Severe aortic stenosis remains widely undiagnosed, and a substantial share of patients presenting with cardiac murmurs are never referred for diagnostic echocardiograms. Instead, the obstacle lies in a narrow patient funnel—from primary care detection, to imaging, to specialist referral, to Heart Team evaluation, and finally to a scheduled catheterization laboratory slot. Edwards controls none of those operational stages.
That bottleneck highlights where the next decade of enterprise value creation must originate, beyond hardware iteration.
Screening. If artificial intelligence applied to routine echocardiograms—or to ordinary stethoscope recordings during primary care visits—can flag severe aortic stenosis earlier and more reliably, the top of the funnel widens. This diagnostic expansion is what renders the EARLY TAVR indication expansion commercially actionable rather than theoretical. However, diagnostic screening lies largely outside Edwards' direct control, representing both an operational risk and a reason it remains unpriced by equity markets. Furthermore, a strategic asymmetry exists: investments that expand the diagnostic funnel benefit competitors like Medtronic and Abbott proportionally to their market share. Funding top-of-funnel screening functions as a shared industry benefit among incumbents, frequently resulting in underinvestment relative to its collective value and prolonging referral bottlenecks.
Heart failure monitoring. The Endotronix acquisition expands Edwards into a business model distinct from single-use surgical and transcatheter implants: continuous physiological monitoring. Pulmonary artery pressure sensing enables clinicians to identify heart failure decompensation before symptoms manifest. Whether Edwards can establish a recurring-revenue monitoring franchise—a commercial model fundamentally different from selling implants to procedural specialists—remains unproven, as nothing in the company's historical record demonstrates that capability.
The Zovighian benchmark. The primary ten-year test for current management is not whether TAVR maintains market share; executive leadership inherited that dominant position, where the principal risk is gradual competitive drift. The critical test is whether Edwards in 2035 becomes a company with multiple billion-dollar franchises across aortic, mitral, tricuspid, and heart failure therapies—or remains a single-therapy enterprise with a well-funded, perpetually promising second act.
As of September 2026, empirical evidence supports neither conclusion definitively. TMTT's revenue expansion rate is impressive, yet its absolute scale remains modest. The tricuspid franchise has achieved commercial momentum, while the mitral franchise remains, after more than a decade, largely ahead of its commercial timeline. The balance sheet provides liquidity, but external acquisition pathways face regulatory limits. The moat remains durable against new entrants, yet offers limited insulation against established category rivals.
This leaves an enterprise that twice helped establish its own industry in a distinct strategic posture: dominant, throughput-constrained, cash-rich, and dependent for future expansion on a demanding clinical progression that tested its initial attempts. Lowell Edwards' founding premise—that the human heart functions as a pump amenable to engineering—sustained the enterprise for sixty-six years. Whether that insight carries the company through its next decade depends on solving operational and diagnostic bottlenecks that extend beyond hardware engineering.
XII. Recent News
September 2024 — Edwards completed the divestiture of its Critical Care product group to Becton, Dickinson and Company for $4.2 billion in cash, finalizing its transition into a pure-play structural heart enterprise.[^4]6
Full-year 2025 results — Total net revenue surpassed $6.0 billion, up approximately 11.5% year over year. Results were driven by $4.49 billion in TAVR sales and $550.6 million from Transcatheter Mitral and Tricuspid Therapies, which grew by 56.4%.1
January 2026 — Edwards terminated its proposed $945 million acquisition of JenaValve Technology after a U.S. District Court granted a preliminary injunction requested by the Federal Trade Commission.[^5]5
July 2026 — Edwards agreed to pay a $12 million civil penalty to resolve Federal Trade Commission allegations regarding Hart-Scott-Rodino premerger notification compliance in connection with its JC Medical transaction.[^6]
References
-
Edwards Lifesciences Investor Relations — Edwards Lifesciences Corporation ↩↩↩↩↩↩
-
Edwards Lifesciences SEC Filings (Form 10-K, 10-Q, DEF 14A) — SEC EDGAR ↩↩↩
-
Edwards Lifesciences 2024 Form 10-K Annual Report — SEC EDGAR, 2025-02-13 ↩
-
Edwards Lifesciences TAVR Growth Slowdown Triggers 31% Stock Drop — MedTech Dive, 2024-07-25 ↩↩↩↩↩
-
Edwards Lifesciences Cancels $945M JenaValve Acquisition Following FTC Court Victory — MedTech Dive, 2026-01-12 ↩↩↩
-
BD to Buy Edwards Lifesciences Critical Care Unit for $4.2 Billion Cash — Reuters, 2024-06-03 ↩↩↩
-
Edwards Lifesciences Earnings Call Transcripts & Reports — The Motley Fool ↩
 LinkedIn
 WhatsApp
 Reddit
 Hacker News
 Email
 Kindle
 RSS Feed
 Spotify
 Apple Podcasts
 Amazon Music
 Audible
 YouTube