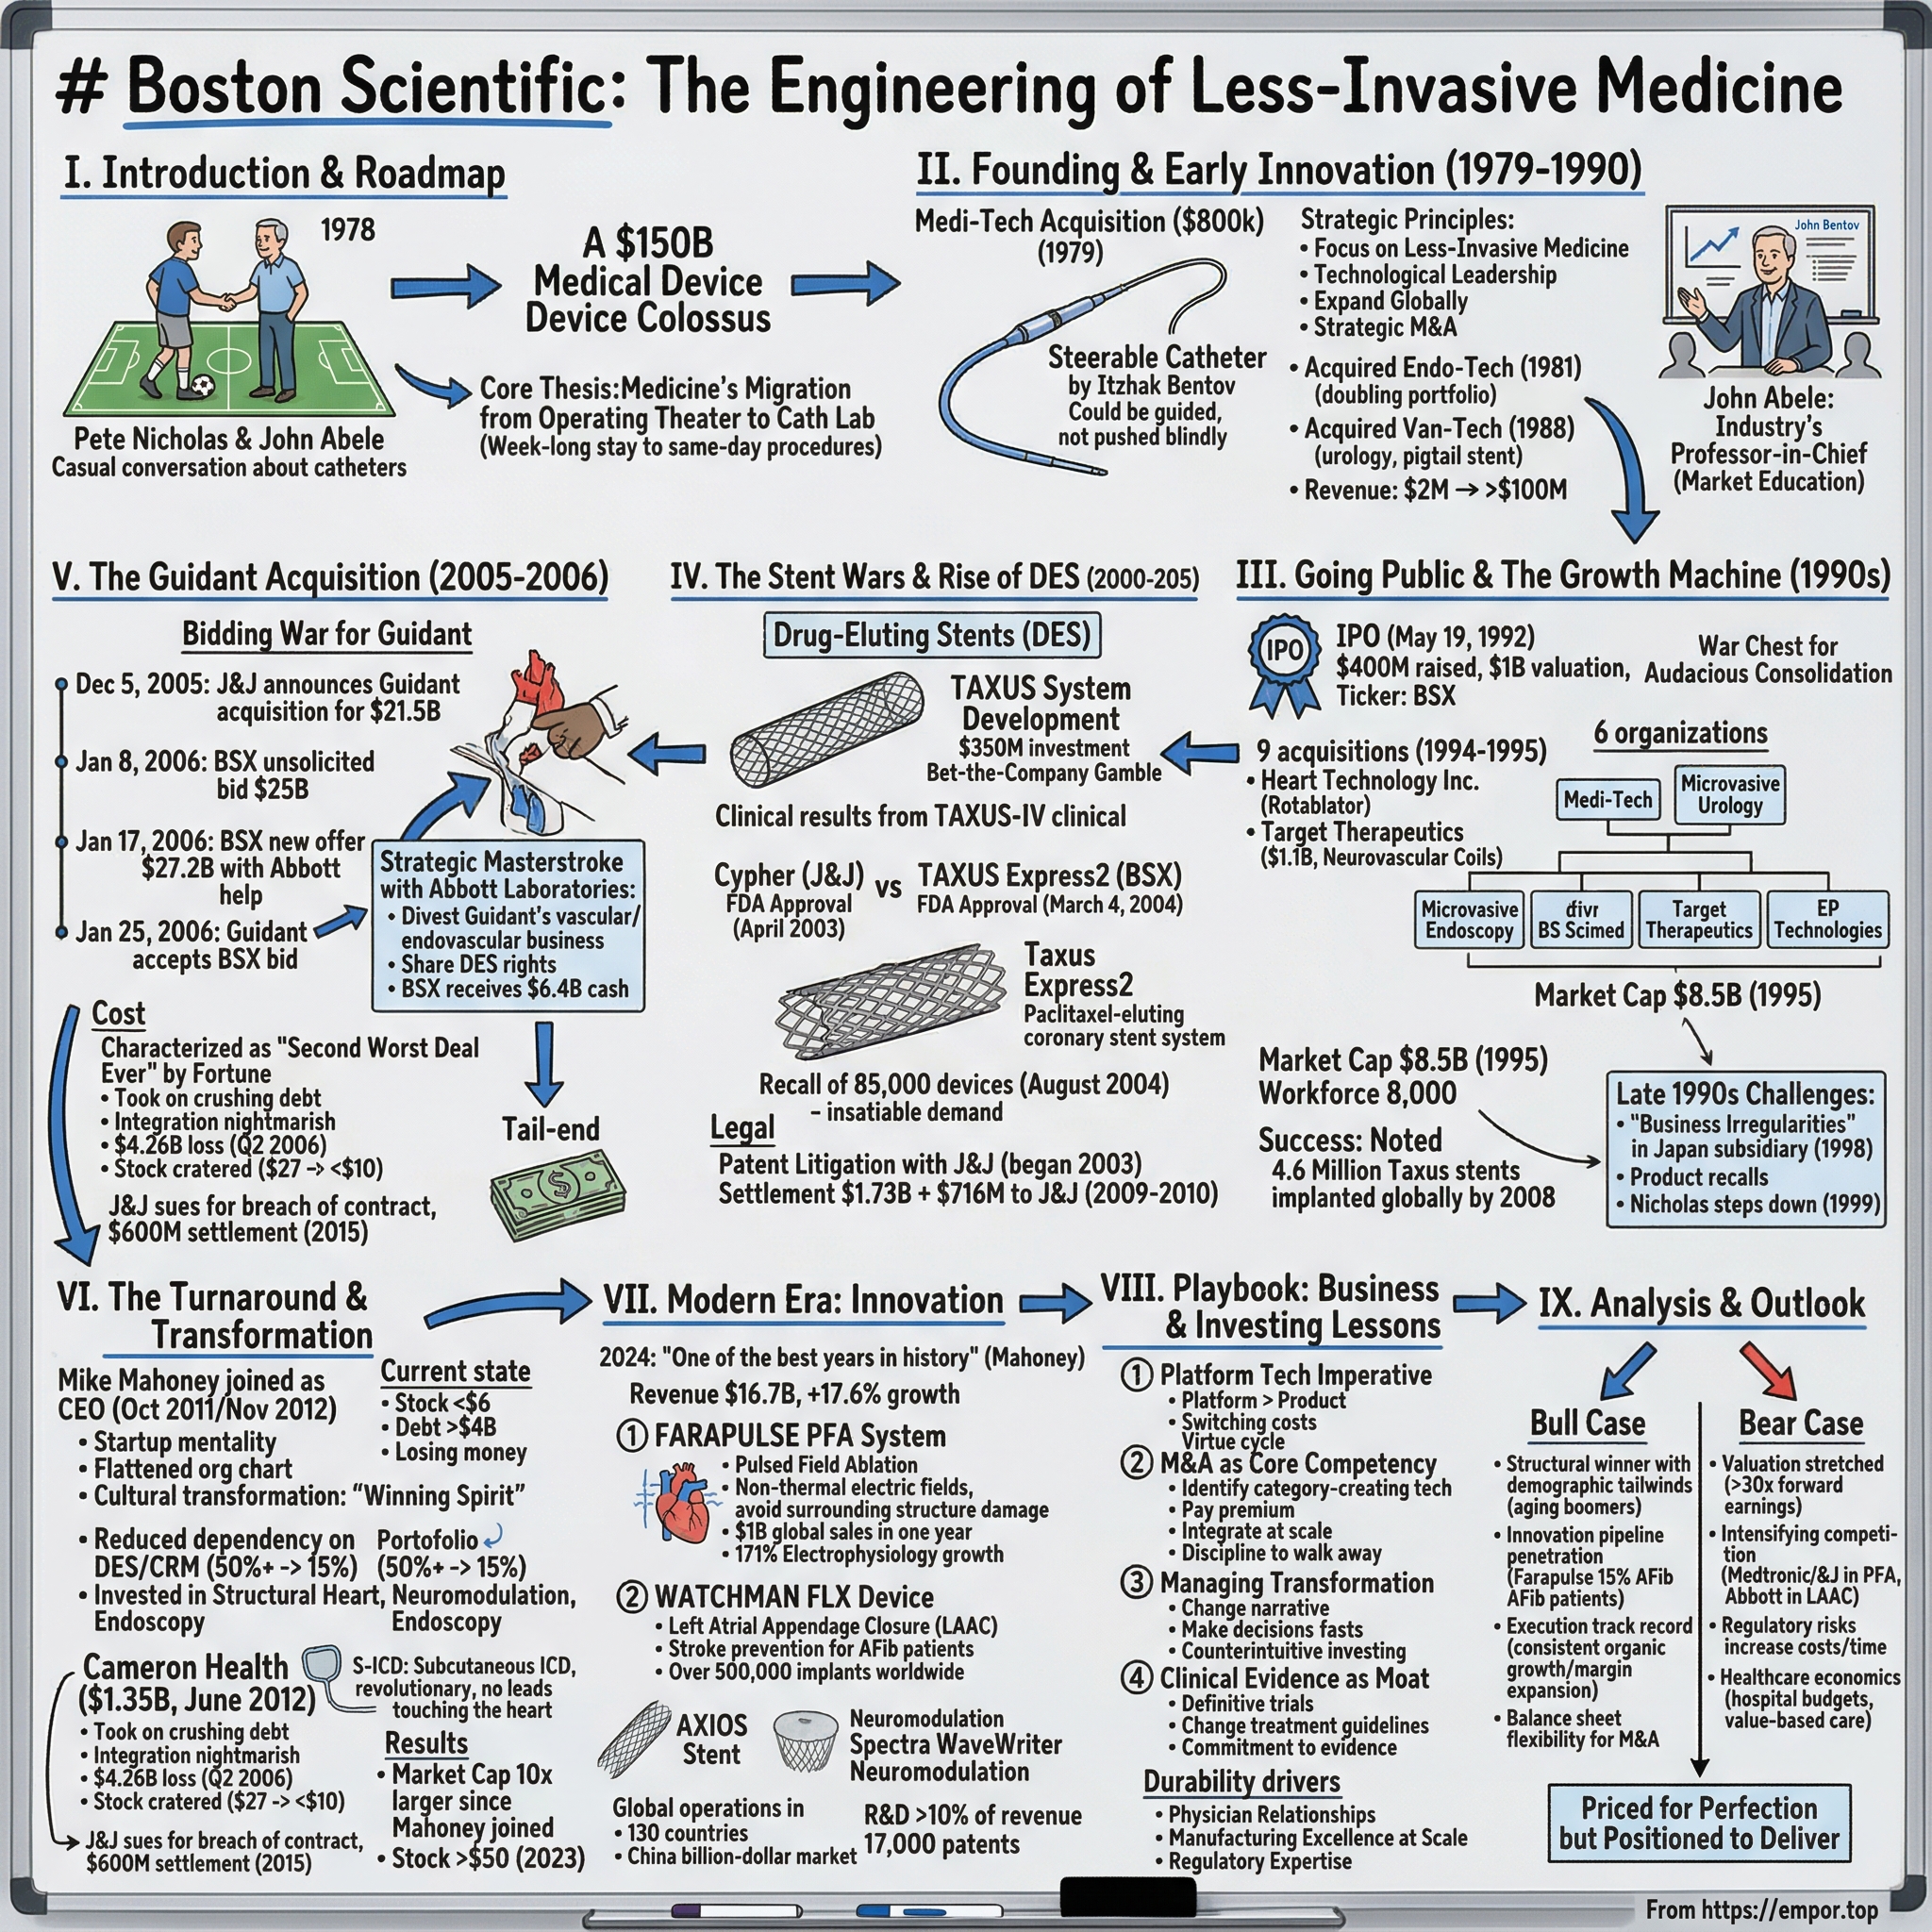
Boston Scientific: The Engineering of Less-Invasive Medicine
I. Introduction & Episode Roadmap
On the morning of August 3, 2026, Michael Mahoney did something he had not done in nearly twelve years as chief executive of Boston Scientific: he bought company stock on the open market. This was not a scheduled 10b5-1 plan sale, an option exercise, or a grant vesting, but a discretionary purchase of 186,240 shares at a weighted average price of $48.33—spending roughly $9.0 million of his own money, as disclosed in a Form 4 filing two days later.1 Mahoney also added 22,119 shares through his 401(k) plan, bringing his direct holding to 1,590,024 shares.1
Context is critical for insider buying, and the backdrop here was stark. Boston Scientific stock had traded as high as $109.50 within the prior twelve months, but on the day Mahoney bought, it was worth less than half that peak.2 A company that had spent a decade as the fastest-growing large-cap operator in medical technology had lost roughly $70 billion in market value over eight months. By the final trading day of August 2026, its market capitalization stood at about $71.5 billion, down from more than $150 billion at its peak.2
The key question for analysts and investors is not the familiar origin narrative: how two founders who met watching their children play soccer in Massachusetts turned an $800,000 catheter business into a $20 billion medical device enterprise.34 That corporate history is well established.
The more pressing question in late 2026 is what the market learned between February and August to reprice Boston Scientific so sharply—and whether the underlying franchise justifies the chief executive's signal of confidence.
The core thesis, and its stress points. Boston Scientific Corporation (NYSE: BSX) has built its business as a pioneer in medical technology category creation. Its core strategic pattern involves replacing open surgical procedures with steerable catheters guided through blood vessels or body lumens under imaging. Biliary drainage, coronary angioplasty, stroke prevention via left atrial appendage closure, and cardiac ablation all fit this framework. In each case, the company either developed or acquired a less-invasive alternative and leveraged its hospital sales force to establish the procedure as a standard of care.
That business model has generated substantial growth, but historical performance demonstrates that its competitive moats can decay rapidly. Twice in twenty years—first with drug-eluting stents and later with pulsed field ablation—Boston Scientific established or led a fast-growing category, only to see competitors enter faster and capture market share more aggressively than management anticipated. The second competitive pressure is unfolding in real time.
The dramatic arc.
- Act I: Polymer catheters, physician co-development, and a 1992 initial public offering that created substantial founder wealth while preserving control.4
- Act II: The drug-eluting stent expansion, the Taxus franchise, and a patent battle with Johnson & Johnson that ultimately cost $1.725 billion.5
- Act III: The $27 billion acquisition of Guidant—a costly bidding war followed by defibrillator recalls, balance-sheet strain, and a decade in which the stock traded below $6.67
- Act IV: The Mahoney-led restructuring from 2012, a pivot toward early-stage venture acquisitions, and major commercial successes with WATCHMAN and FARAPULSE.
- Act V, which altered the company's trajectory: 2026, when revenue growth slowed, management cut financial guidance twice, announced a $14.5 billion acquisition four months after emphasizing a focus on tuck-in transactions, and saw its share price fall by half.8910
The roadmap. Founding and early innovation; the public offering and 1990s expansion; the stent litigation; the Guidant acquisition and recovery; the turnaround under Mahoney; the modern era and pulsed field ablation dynamics; a strategic and moat analysis; bull and bear investment cases; and an examination of earnings calls and investor-day transcripts to evaluate management statements against execution.
The central pattern: Boston Scientific has demonstrated strong capability in establishing new device categories, alongside repeated overestimation of how long it can maintain market exclusivity. This pattern shaped the company's trajectory in 2006, and it defines its situation in 2026.
 Subscribe on LinkedIn
II. The Founding Story & Early Innovation (1979–1990)
The company's origins trace to John Abele, an Amherst College physics and philosophy graduate whose academic background combined technical curiosity with salesmanship. In 1968, while selling medical equipment, Abele partnered with inventor Itzhak Bentov, whose small firm, Medi-Tech, was developing polymer catheters flexible enough to be navigated through blood vessels. Backed financially by Cooper Laboratories, Medi-Tech introduced its first family of steerable catheters in 1969.4
The underlying technical insight was straightforward in concept but demanding in execution: if clinicians could view internal anatomy using X-ray fluoroscopy or ultrasound, they could treat blocked ducts and narrowed arteries without open surgery. The engineering challenge required a catheter shaft stiff enough to transmit torque from the clinician's hand outside the body to the tip inside the chest, yet flexible enough to navigate vessel walls without causing trauma. Manufacturing these devices required precise control over shaft stiffness gradients, braid patterns, radiopaque tips visible under imaging, and ergonomic handles to reduce operator fatigue.
While Abele possessed technical insight and physician relationships, he lacked capital and operational structure. That balance arrived when he met Peter Nicholas while watching their children play soccer.4 Nicholas brought a complementary skill set as a Wharton MBA graduate, former U.S. Navy officer, and executive at Eli Lilly. Their division of labor established a long-standing corporate template: Abele focused on physician relationships and product development, while Nicholas managed capital allocation, corporate structure, and operations.
In 1979, Abele and Nicholas formed Boston Scientific Corporation to acquire Medi-Tech for $800,000, funding the purchase with $500,000 in bank debt and $300,000 from private investors.4 The acquisition gave the founders an operating company with established products and existing customers for a fraction of modern medical technology startup valuations.
In its first year, Boston Scientific generated approximately $2 million in revenue.4 Early demand came primarily from interventional radiologists performing biliary drainage to relieve obstructed ducts and from early peripheral angioplasty procedures. Though modest initial markets, these procedures offered a clear value proposition by replacing open surgery, creating strong incentives for physicians to standardize on Medi-Tech devices.
The clinical moat, built one physician at a time. Rather than relying on traditional marketing, Boston Scientific focused on physician co-development. Engineers observed procedures alongside interventional radiologists and cardiologists, translating feedback on handle ergonomics, shaft kinking, and tip visibility directly into manufacturing adjustments.
This collaborative approach created two durable competitive advantages. First, it built proprietary manufacturing expertise—the precise technical specifications required to produce consistent catheter performance. Second, it established procedural switching costs. Clinicians who performed hundreds of procedures with a specific device developed hands-on familiarity. Switching suppliers introduced operational friction, added procedural time, and potentially increased complication risks.
This clinical switching cost operated at the individual physician level rather than the hospital system level. While defensible against incremental competition, it remained vulnerable to major technology shifts; physicians would readily adopt competing devices that offered clear improvements in procedural speed or safety. Boston Scientific benefited from this dynamic during its expansion in the 1980s, but faced its downside during competitive shifts in 2006 and 2026.
Throughout the 1980s, Boston Scientific grew steadily while remaining closely held by its founders. The company built out four core product lines that later formed its operating divisions, expanding its position in interventional radiology and establishing a presence in cardiology. By maintaining private ownership, it cultivated long-term relationships with pioneering physicians across emerging specialties.
However, scaling the business required broader access to capital—a transition that culminated in the spring of 1992.
III. Going Public & The Growth Machine (1990s)
In May 1992, Boston Scientific listed on the New York Stock Exchange, selling 23.5 million shares at $17 per share to raise $400 million.411
Two details from that offering warrant attention from an investor's perspective beyond the headline capital raised.
The first was retained ownership. After the offering, Nicholas, Abele, and their families retained roughly two-thirds of the equity.11 This structural control meant a public company whose founders held voting control could operate with a multi-year horizon that quarterly-focused peers could not replicate—while also enabling large, rapid decisions without internal friction. Both the advantages and risks of this corporate structure materialized quickly.
The second detail was capital allocation. Rather than directing proceeds into internal research and development programs, Boston Scientific funded an aggressive acquisition strategy.
The operating matrix. Boston Scientific organized itself into focused business units aimed at distinct physician call points: Medi-Tech for radiology and vascular work, Mansfield for cardiology, Microvasive Endoscopy for gastroenterology, and Microvasive Urology.4 The underlying rationale was that selling to interventional radiologists required a distinct sales conversation, clinical evidence base, and product roadmap compared to selling to gastroenterologists—even if both specialties relied on steerable catheters. This "category leadership by call point" structure remains central to the company's operating model; Chief Executive Officer Michael Mahoney described it in similar terms at the 2025 investor day, emphasizing a strategy to be the most meaningful supplier to specific physician specialties rather than the broadest supplier in the industry.12
The shopping spree. Between late 1994 and early 1996, Boston Scientific acquired nine companies in roughly 16 months, deploying approximately $2.5 billion.411 Major transactions included Meadox Medicals for about $400 million and Heart Technology, developer of the Rotablator atherectomy system, for about $450 million.11 The most strategic transaction was SCIMED Life Systems, announced in November 1994 and completed on February 1, 1995. The acquisition established Boston Scientific's leadership in coronary balloon angioplasty and provided the core platform for its subsequent drug-eluting stent franchise.
Financially, deal velocity drove top-line expansion, with annual revenue growing from $449 million in 1994 to $1.2 billion in 1995.11 Strategically, it established a commercial presence across every major interventional specialty. Operationally, however, rapid integration presented severe challenges.
Growing pains, and a lesson in integration. Integrating nine companies in 16 months required unifying nine manufacturing networks, sales cultures, quality management systems, and enterprise resource planning platforms simultaneously. Boston Scientific spent the late 1990s absorbing these additions, experiencing supply chain friction, product recalls, and international expansion strains.
These operational pressures culminated in financial reporting failures. In November 1998, the company disclosed approximately $45 million in questionable sales at its Japanese subsidiary, along with an additional $40 million in improper sales recorded in prior years.411 For a company that had assured investors of smooth integration, revenue-recognition failures in a key international market eroded management credibility.
In response, the board brought in external leadership. In March 1999, James Tobin was named chief executive officer, assuming the role in June as Peter Nicholas transitioned to chairman.411 Tobin, who had previously led Biogen and served in senior management at Baxter International, brought a focus on manufacturing and operational discipline. His mandate focused on stabilizing corporate governance, resolving quality control issues, rectifying Japanese operations, and streamlining manufacturing facilities.
What the 1990s tell an investor. The 1990s established a recurring operational pattern. Under commercial pressure or growth mandates, Boston Scientific's default response has been aggressive, large-scale acquisitions, followed by multi-year absorption periods. The 1994–1995 acquisition campaign secured market positions—most notably through SCIMED—but also led to operational disruption and financial restatements. A decade later, the company would repeat this pattern at ten times the scale.
Tobin's operational restructuring stabilized the business, positioning Boston Scientific by 2003 for the largest commercial market expansion in interventional cardiology history. That expansion delivered market dominance, but the subsequent fallout created severe enterprise risk.
IV. The Stent Wars & Rise of Drug-Eluting Stents (2000–2005)
Understanding why the drug-eluting stent became the most lucrative product category in medical technology requires examining what frequently went wrong with the procedure it replaced.
Balloon angioplasty, in its original form, was straightforward: clinicians threaded a catheter into a narrowed coronary artery, inflated a balloon to crush plaque against the vessel wall, and withdrew the device. While immediately effective, the procedure often failed within months. Insulted by the balloon, the artery frequently recoiled or scarred over—a process known as restenosis—forcing a meaningful portion of patients to return for repeat procedures. The bare-metal stent, a tiny mesh scaffold left inside the vessel, solved recoil. However, it failed to stop scarring, as tissue grew through and over the metal mesh.
The drug-eluting stent addressed this limitation. By coating the metal scaffold in a polymer loaded with a cell-proliferation-inhibiting drug, the device slowly released medication into the vessel wall over several weeks. This prevented scar tissue formation and drastically reduced repeat procedures. Conceptually, it functioned as a time-release pharmacy parked inside a coronary artery—a mechanism that would later create unexpected clinical complications.
Cypher first, Taxus bigger. Johnson & Johnson's Cordis unit reached the market first, launching the sirolimus-eluting Cypher stent in the United States in 2003. Boston Scientific followed in 2004 with the paclitaxel-eluting TAXUS Express² system, built on the SCIMED coronary platform acquired a decade earlier. Taxus rapidly captured market leadership, driving revenue expansion at a pace Boston Scientific had never experienced—and would not replicate until the pulsed field ablation era with FARAPULSE.
The strategic insight lies beyond the headline growth. Boston Scientific succeeded not by entering first, nor by offering a superior antiproliferative drug, but by leveraging catheter deliverability—the precise mechanical engineering required to navigate a stent through tortuous, calcified coronary arteries. This was the SCIMED inheritance, demonstrating that Boston Scientific's core durable advantage rested not on a single therapeutic agent, but on its catheter design and vessel navigation capabilities.
The patent war. What followed was one of the most expensive intellectual property battles in medical device history. Boston Scientific and Johnson & Johnson's Cordis unit engaged in extensive litigation across U.S., Canadian, Belgian, German, French, and Italian courts over stent architecture, drug coatings, and delivery systems. Dating back to 2003, the disputes pitted Boston Scientific's Jang patent against Johnson & Johnson's Palmaz and Gray patents, with Johnson & Johnson alleging infringement by the Express, TAXUS Express, and Liberté stents, while Boston Scientific countered that Cypher, BX Velocity, and Genesis infringed its intellectual property.5
The legal resolution proved costly. In September 2009, Boston Scientific agreed to pay Cordis $716 million to settle 14 lawsuits. On February 1, 2010, the company announced a comprehensive settlement under which it paid Johnson & Johnson $1.725 billion—comprising $1.0 billion in an initial payment and a $745 million letter of credit for the remaining balance and interest.5 For a company already carrying heavy acquisition debt, this settlement represented a major capital drain rather than a minor legal footnote.
Testing the moat: did Taxus actually build one?
The claim, frequently asserted during the expansion and repeated in later retrospectives, held that Taxus established a defensible clinical and intellectual property moat at the center of interventional cardiology.
The evidence reveals a more fragile competitive posture.
First, clinical vulnerability emerged rapidly. In September 2006 at the European Society of Cardiology meeting in Barcelona, a meta-analysis of first-generation drug-eluting stent trials suggested that late stent thrombosis—a blood clot forming inside the stent months or years post-implantation—was more common with drug-eluting stents than with bare-metal scaffolds.13 Although critics contested the methodology, manufacturer datasets presented weeks later at the Transcatheter Cardiovascular Therapeutics (TCT) conference confirmed small but statistically significant increases in late stent thrombosis between years one and four for both major platforms: roughly 0.5% for Taxus and 0.6% for Cypher relative to bare-metal stents, even as both devices maintained significant reductions in repeat revascularization.13
While the absolute incidence rates were low, the market impact was severe. Adoption of drug-eluting stents dropped sharply, cardiologists extended dual antiplatelet therapy regimens, and market valuations across the category contracted. The outcome illustrated a fundamental vulnerability in implantable medical technology: even a low-single-digit safety signal surfacing years after commercial launch can erode a growth premium quickly, as clinicians weigh rare catastrophic complications against procedural convenience.
Second, competitive vulnerability manifested through structural deal concessions. The second-generation everolimus-eluting stent that eventually captured market leadership—Abbott's Xience—entered the market because Boston Scientific divested key vascular assets to Abbott to secure antitrust clearance for acquiring Guidant. Although Boston Scientific retained co-promotion rights to sell the device under its Promus brand, the arrangement softened financial losses while exposing a strategic limitation: the company was marketing a competitor's design rather than leading with proprietary innovation.14
Third, legal liabilities eroded cumulative economic gains. The $1.725 billion settlement paid to Johnson & Johnson absorbed a major share of the cumulative profit generated during the Taxus franchise's peak years.5
The calibrated conclusion. Historical evidence refutes the view that Taxus built a lasting enterprise moat. While Taxus achieved commercial success, it failed to establish long-term market exclusivity. What the episode demonstrated was not a durable monopoly in coronary stents, but a core capability in catheter delivery mechanics—a strength Boston Scientific later redeployed in structural heart and electrophysiology applications. For investors evaluating category leadership claims, the Taxus franchise demonstrates that therapeutic advantages are eventually matched by competitors, whereas engineering capabilities in device delivery and clinical adoption prove more resilient over time.
That distinction would soon face a far larger test.
V. The Guidant Acquisition: The Deal of the Century (2005–2006)
In December 2005, Boston Scientific was a coronary stent manufacturer with one dominant product line and a growing recognition that the drug-eluting stent expansion would not maintain its pace indefinitely. Across medical technology, the most lucrative segment was not coronary stents, but cardiac rhythm management—pacemakers and implantable cardioverter defibrillators. These devices, implanted for up to a decade, commanded high prices from a captive physician referral base and were controlled primarily by Medtronic and Guidant Corporation.
Johnson & Johnson had already agreed to acquire Guidant for $21.5 billion, or $63 per share. When Guidant's defibrillators experienced product safety issues and Johnson & Johnson moved to renegotiate the purchase price downward, an opportunity opened for a competing bidder.
The bidding war. Under Chief Executive Officer James Tobin, Boston Scientific launched an unsolicited bid of $72 per share—approximately $25 billion in total—in January 2006, a proposal larger than Boston Scientific's own market capitalization at the time.6 Johnson & Johnson countered at $71 per share, prompting Boston Scientific to increase its offer. The final merger agreement valued Guidant at $80 per share, or approximately $27 billion.6
The Abbott side-deal. Acquiring Guidant created antitrust conflicts in coronary stents, as both companies operated competing product lines. On January 8, 2006, Boston Scientific structured a regulatory remedy: Abbott Laboratories would purchase Guidant's vascular intervention and endovascular businesses for $4.3 billion—comprising $3.8 billion in cash at closing plus two $250 million payments contingent on U.S. and Japanese regulatory approvals for an everolimus-eluting stent—while extending Boston Scientific a $700 million subordinated note at a 5.25% interest rate.14 Boston Scientific retained shared rights to Guidant's drug-eluting stent portfolio, securing access to everolimus technology under a private-label supply arrangement.14 The Federal Trade Commission mandated these divestitures as a condition of clearing the transaction.14
To finance a defibrillator acquisition, Boston Scientific funded the deal in part by selling stent assets to a competitor and accepting debt financing from that same rival. In doing so, it provided Abbott with the technological foundation to build the everolimus-eluting stent that would later displace Boston Scientific's flagship Taxus platform.
Testing the claim: did Guidant deliver scale power?
The claim: Acquiring Guidant would give Boston Scientific immediate category leadership in both interventional cardiology and cardiac rhythm management, capturing scale economics by selling two major implant lines through a single cardiology sales force.
The disconfirming record is among the most severe in healthcare M&A.
Operational failure was already evident prior to transaction signing. On June 17, 2005—seven months before Boston Scientific's initial bid—Guidant had recalled more than 38,000 implantable defibrillators across its Prizm 2 DR, Contak Renewal, Contak Renewal 2, Ventak Prizm AVT, Vitality AVT, Renewal 3 AVT, and Renewal 4 AVT product lines following at least 45 device failures and two deaths attributed to short circuits.[^15] Compounding the mechanical defects was the company's disclosure record: contemporary reporting established that Guidant had failed to notify physicians promptly of an electrical flaw in the Ventak Prizm 2 DR, having corrected the flaw in units manufactured after mid-2002 without informing clinicians who had already implanted earlier devices.[^15][^16] For an implantable medical device built on trust, non-disclosure damaged clinical credibility far more than product failure alone. Physician confidence in the franchise did not recover on a timeline that supported the acquisition's financial assumptions.
Financial strain followed directly. Boston Scientific funded the $27 billion purchase with a balance sheet designed for a much smaller business, accumulating net debt that it serviced through a period of declining stent prices and emerging safety concerns over late stent thrombosis. Impairments of goodwill and intangible assets accumulated over subsequent years as acquired cash flows fell short of projections. Equity value reflected the damage: a stock that traded in the mid-$40s during the Taxus peak fell to between $5.50 and $6.75 by September and October 2011.2
Litigation added further costs over the next decade. Johnson & Johnson filed suit alleging Guidant had breached its merger agreement, seeking more than $7 billion in damages. On February 17, 2015—nine years after the deal closed—Boston Scientific settled the dispute, with Guidant paying Johnson & Johnson $600 million in two $300 million installments.7
The calibrated conclusion. Historical evidence refutes the claim of scale-driven value creation. Boston Scientific paid a peak valuation for an enterprise whose core asset—physician trust in an implanted device—had been severely compromised by June 2005. It then transferred essential stent technology to a competitor as a condition of regulatory approval, accelerating the decline of its own core business. The transaction's primary risks were legible at signing in public recall disclosures.
The historical precedent has direct relevance to 2026. In January 2026, Boston Scientific announced its largest acquisition since Guidant. Before evaluating that transaction, the subsequent recovery warrants examination—because how the company restructured its balance sheet and rebuilt its pipeline established the executive credibility that management drew upon two decades later.
VI. The Turnaround & Transformation (2012–2020)
In October 2012, Michael Mahoney assumed leadership of a company that was, by most measures, struggling. Revenue growth had stalled, debt leverage was heavy, the inherited cardiac rhythm management business was losing market share, and the share price had spent the preceding year trading in single digits.
Mahoney brought an operational background tailored to the company's challenges. At Johnson & Johnson, he had led the DePuy Synthes orthopedics franchise—a business dependent on surgeon relationships, procedural economics, and sales force execution rather than fundamental scientific breakthroughs. He had previously spent years at GE Healthcare. As a commercial operator experienced in large-scale integration, Mahoney arrived at an organization where the primary challenge was operational discipline rather than clinical ambition. He added the chairman title in 2016.
The operating mandate. Management established a four-part restructuring program focused on strict execution sequencing: reduce balance sheet debt, trim structural selling, general, and administrative expenses, fix or divest underperforming business units, and replace large-scale acquisitions with a venture-style M&A model.
Operating margin expansion became central to the turnaround strategy. Management reported at the company's 2025 investor day that Boston Scientific expanded its adjusted operating margin every year from 2014 onward while simultaneously increasing research and development spending, delivering double-digit adjusted earnings-per-share growth across those years.12 Free cash flow conversion, historically trailing industry peers, recovered to approximately 75% by 2025.12
The venture M&A model. The strategic shift centered on where Boston Scientific deployed capital along the development risk curve.
The Guidant transaction demonstrated that purchasing mature revenue at peak valuation multiples carries severe capital risk, as acquirers pay for growth rates the target has already realized. Mahoney's alternative strategy focused on acquiring or taking minority stakes in early-stage companies before regulatory approval or commercial launch—when clinical and regulatory risks remain embedded in the valuation. Boston Scientific then applied its key operational strengths: a clinical development organization capable of executing large pivotal trials and a global commercial sales force able to introduce approved devices to hospitals and physicians rapidly.
Two early transactions illustrated this approach.
WATCHMAN. On March 3, 2011—prior to Mahoney's appointment, though developed into a commercial platform under his tenure—Boston Scientific acquired Atritech for $100 million in cash, with up to $275 million in contingent milestone payments through 2015.15 Atritech developed a catheter-delivered parachute-shaped implant designed to seal the left atrial appendage, a pouch off the left atrium where blood clots frequently form in patients with atrial fibrillation. For patients who cannot tolerate long-term anticoagulant therapy due to bleeding risks, closing the appendage offers a procedural alternative to pharmaceutical stroke prevention.
At the time of the transaction, the device held a CE mark in Europe but remained investigational in the United States, pending results from the PREVAIL clinical trial.15 The initial $100 million upfront investment yielded a product line that, more than a decade later, generated over $500 million in quarterly revenue.9
S-ICD. On June 8, 2012, Boston Scientific acquired Cameron Health for $150 million upfront, an additional $150 million upon FDA approval, and up to $1.05 billion in potential revenue-based milestones across six years.16 Cameron developed a subcutaneous implantable cardioverter defibrillator positioned entirely beneath the skin. By avoiding transvenous leads inserted into the heart and vasculature—historically the primary point of long-term mechanical failure in conventional defibrillators and a central issue in the Guidant recalls—the device offered a less-invasive structural design. Approximately 1,300 devices had been implanted worldwide when the deal closed.16
The structure of both acquisitions reflected the venture model: modest upfront capital commitments coupled with larger milestone payments contingent on regulatory approval and commercial performance. This milestone-dependent structure capped initial downside risk while preserving access to upside growth, contrasting with the $27 billion purchase of Guidant.
Testing the claim: does venture M&A guarantee category entry?
The claim: Management has maintained that pairing early-stage technology acquisitions with Boston Scientific's clinical and commercial infrastructure reliably establishes category leadership.
The disconfirming record lies in transcatheter aortic valve replacement (TAVR).
TAVR replaces a diseased aortic valve via catheter navigation rather than open-heart surgery, representing one of the largest segments in structural heart therapeutics and long dominated by Edwards Lifesciences and Medtronic. Boston Scientific attempted to enter the TAVR market three times over fifteen years, with none achieving sustained market adoption.
First attempt: Sadra Medical, developer of the repositionable Lotus valve, which Boston Scientific initially supported through a minority investment before acquiring outright in January 2011. Following nearly a decade of clinical development and commercialization, recurrent mechanical issues with the delivery system's locking pin mechanism prompted repeated product recalls. On November 17, 2020, Boston Scientific launched a global voluntary recall of all unused LOTUS Edge inventory and permanently discontinued the platform, ending all associated commercial, clinical, research, and manufacturing operations while recording estimated pre-tax GAAP charges of $225 million to $300 million.[^19]
Second attempt: Symetis, a Swiss structural heart company acquired on May 16, 2017, for $435 million in cash, which added the ACURATE valve platform.17 The ACURATE IDE clinical trial randomized 1,500 severe aortic stenosis patients to receive either the ACURATE neo2 valve or a commercially available Sapien or Evolut valve. Results presented at the Transcatheter Cardiovascular Therapeutics conference on October 30, 2024, failed to meet the primary endpoint: the twelve-month composite rate of death, stroke, or rehospitalization was 14.8% for ACURATE neo2 compared with 9.1% for control devices, missing the non-inferiority margin due to higher rates of paravalvular leakage and valve under-expansion.18 Consequently, on May 28, 2025, Boston Scientific announced the global discontinuation of ACURATE neo2 and ACURATE Prime sales, citing heightened clinical and regulatory requirements.19
Third attempt: On May 18, 2026, Boston Scientific invested $1.5 billion for an approximate 34% equity stake in MiRus, whose SIEGEL balloon-expandable valve is constructed from a nickel-free molybdenum-rhenium alloy and is currently evaluated in the STAR pivotal trial. The transaction includes an exclusive option to acquire the remaining platform for up to $3.0 billion in cash milestone payments upon clinical and regulatory milestones, plus subsequent sales-based royalties.20
The calibrated conclusion. The evidence indicates that venture M&A has succeeded primarily where Boston Scientific's core capabilities in catheter delivery mechanics and procedural workflow resolved the principal engineering challenge, as demonstrated by WATCHMAN and later FARAPULSE. Conversely, the model has struggled where the central obstacle was matching the long-term clinical performance of established structural heart implants. Fifteen years across three discontinued TAVR platforms, a GAAP write-down of up to $300 million, a missed pivotal trial endpoint, and a $1.5 billion equity investment committed to a fourth effort demonstrate that early-stage acquisition does not guarantee market conversion.
The commercial test for the MiRus investment remains ahead: whether the STAR pivotal trial demonstrates non-inferiority against Sapien and Evolut, and whether Boston Scientific subsequently exercises its $3.0 billion acquisition option.
Furthermore, management's public summary of its M&A record requires context. At the September 2025 investor day, Mahoney told investors that across approximately 50 acquisitions during his tenure and a venture portfolio of roughly 45 positions, "there hasn't been one instance where in that quarter or that year we've taken down our operating income margin goals or our EPS targets to absorb a deal that we've done."12 While accurate regarding short-term financial target absorption, that metric measures accounting impact rather than long-term return on invested capital.
VII. Modern Era: Innovation & Category Leadership (2020–Today)
There is a slide Mike Mahoney has shown, in one form or another, at every investor day of his tenure. It plots Boston Scientific's growth against the weighted average growth of its end markets, and the company's line is always above the market's line. On September 30, 2025, standing in front of investors at the 2025 investor day, he made the implicit promise explicit: "if you look backwards over the past six investor days, we have always delivered our investor day targets. And more often than not, beat our investor day targets. So when we talk about investor day, it's not some aspiration that doesn't have balanced upsides and downsides scenarios. It's actually a plan that we intend to at least meet, if not beat."12
The plan he laid out that day was for 10%-plus average organic revenue growth across 2026–2028, against a market he pegged at 9%; roughly 50 basis points of adjusted operating margin expansion per year, putting the company "on the doorstep of 30%" by the end of the period; leveraged double-digit adjusted earnings growth; and 70–80% free cash flow conversion.12 He also described the acquisition philosophy in plain terms: "we're very focused on tuck-in M&A."12
Ten months later, Boston Scientific's 2026 organic growth guidance was 5% to 6%, and the company had announced a $14.5 billion acquisition.108
This section is the story of how a genuinely extraordinary run turned, and what the turn reveals about the durability of what was built.
The peak: what 2024 and 2025 actually looked like
The numbers were not a mirage. For the full year 2025, Boston Scientific reported net sales of $20.074 billion, up 19.9% on a reported basis and 15.8% organic. GAAP net income attributable to common stockholders reached $2.898 billion, or $1.94 per share, against $1.853 billion and $1.25 the prior year — a roughly 56% increase. Adjusted earnings were $3.06 per share. The Cardiovascular segment delivered $13.250 billion, up 23.2%; MedSurg delivered $6.824 billion, up 13.9%, with Endoscopy at $2.916 billion, Urology at $2.709 billion, and Neuromodulation at $1.199 billion.3
Urology's 23.1% growth was substantially inorganic — the Axonics sacral neuromodulation business, acquired for approximately $3.67 billion and closed in November 2024, was inside the base.321 Peripheral interventions carried the contribution from Silk Road Medical's transcarotid artery revascularization franchise — a catheter-based way of treating carotid artery disease to reduce stroke risk — announced at approximately $1.26 billion and closed in September 2024.2223 Neuromodulation carried Relievant Medsystems, acquired for $850 million upfront in a deal announced September 19, 2023, whose Intracept system uses radiofrequency energy to silence the basivertebral nerve in patients with chronic vertebrogenic back pain.24
But the engine of the whole story was electrophysiology, and specifically one product.
FARAPULSE: the mechanism, the money, and the mistake
Cardiac ablation treats atrial fibrillation by destroying the small patches of heart tissue that generate chaotic electrical signals. For two decades the way to destroy that tissue was thermal: radiofrequency energy to burn it, or cryotherapy to freeze it. Both work. Both share a fundamental problem — heat and cold do not respect tissue boundaries. The esophagus sits directly behind the left atrium; the phrenic nerve, which drives the diaphragm, runs nearby. Burn too enthusiastically and you can perforate the esophagus, an rare complication that is frequently fatal.
Pulsed field ablation solves this with a different physics. Instead of thermal energy, it delivers very brief, very high-voltage electrical pulses that punch permanent holes in cell membranes — irreversible electroporation. The useful property is that different tissue types have different sensitivity thresholds to this effect, and cardiac muscle is among the most sensitive. Tune the field correctly and you kill heart muscle cells while leaving the esophagus and nerves essentially intact. It is, in effect, a way of being selectively lethal to exactly one kind of cell.
Boston Scientific did not invent this. It bought it, patiently and cheaply. The company had held a 27% stake in Farapulse since 2014. On June 24, 2021 it exercised its option on the remainder, paying approximately $295 million net upfront plus up to $92 million in clinical and regulatory milestones and revenue-based payments over three years.25 At the time, analysts sized the incremental opportunity at $1–2 billion by 2030, and Boston Scientific was a distant fourth in electrophysiology.25
The clinical case was established by the ADVENT trial, published in the New England Journal of Medicine in 2023, which randomized patients with paroxysmal atrial fibrillation to pulsed field ablation or conventional thermal ablation and found pulsed field non-inferior on both efficacy and safety.26 The FDA approved the FARAPULSE system on January 31, 2024.[^30]
What happened next was one of the fastest device launches in the industry's history. FARAPULSE passed $1 billion in global sales within its first year, treating more than 200,000 atrial fibrillation patients, while the electrophysiology business overall generated $1.9 billion in 2024 — up 138% year on year, with fourth quarter sales of $649 million growing 171%.27 Mahoney credited commercial and supply chain execution and acknowledged, accurately, that "there could be stronger PFA competition in 2025 — a lot of that is out of our hands."27
By the September 2025 investor day, the company disclosed publicly for the first time that FARAPULSE had treated 500,000 patients, described itself as the world leader in pulsed field ablation, and sized the electrophysiology market at $13 billion growing approximately 15% over the plan period.12
The turn
On February 4, 2026, Boston Scientific reported those excellent full-year results and guided 2026 to 10.0–11.0% organic growth with adjusted earnings of $3.43 to $3.49.3 The stock fell about 18% — roughly 11% at the open and a further 7% into the close.28
What spooked investors was not the annual growth rate. It was the sequence. Electrophysiology delivered $890 million in the fourth quarter, up 37.1% year on year but essentially flat against the third quarter's $865 million. WATCHMAN delivered $535 million against $512 million in the third quarter, despite 29.4% growth for the year.28 In a franchise supposedly early in a multi-year adoption curve, sequential flatness is not noise; it is the signature of either market saturation or share loss.
Mahoney's response on that call is worth recording precisely, because it is the benchmark against which everything since should be measured. On market growth he pushed back on competitors' claims: "We think the market in Q4 was closer to 18% to 20% growth rather than some other companies' claim that it was 25%." On competitive position he was unequivocal: "By the end of 2026, we will be the clear PFA market leader." On the left atrial appendage franchise: "We are quite proud of the 29% growth of the franchise."28
Eleven weeks later, on April 22, 2026, the company cut full-year guidance from 10.5–11.5% reported sales growth to 7–8.5%, and adjusted earnings from $3.43–$3.49 to $3.34–$3.41.9 Three business lines were named: electrophysiology, WATCHMAN, and urology. WATCHMAN volume had begun declining in February — the first decline after a year of nearly 30% growth. Electrophysiology had posted a strong quarter in absolute terms, $905 million on 24% growth, but had lost more share than expected to Medtronic, Johnson & Johnson, and Abbott. Urology grew roughly 2% on $646 million.9 Mahoney's framing: "This was a guide down that we, quite frankly, are not proud of, but we think it's the right thing to do."9
Then, on July 29, 2026, they cut again — to 5.5–6.5% reported growth and $3.28–$3.32 in adjusted earnings.10 Second quarter revenue of $5.442 billion had grown 7.0% organically, above the guided range, and adjusted earnings of $0.86 beat the high end, though management attributed the beat primarily to favourable discrete tax items. Adjusted operating margin was 28.4%, up 70 basis points.29 The businesses beneath the headline told the real story: electrophysiology grew 9% globally but only 3% in the United States, offset by 23% internationally; WATCHMAN grew 4% globally, 3% in the U.S.; urology grew 0.8%; cardiac rhythm management declined 2%.29
Mahoney opened with an unusual admission: "This update today is not the outcome we planned or what you have come to expect from us." On the competitive dynamic he was direct: "we did not anticipate the degree of competitive share movement" in the U.S. market. And on the forecasting failure itself: "Market conditions have evolved quickly, and it's been a challenge to forecast effectively."2910
Testing the claim: is FARAPULSE a monopoly?
The claim, widely held through 2025: FARAPULSE gives Boston Scientific a durable, category-defining lead in the largest and fastest-growing market in medical technology.
The disconfirming evidence arrived from three directions simultaneously, and management's own disclosures are the primary source.
First, and most damaging to the thesis, Boston Scientific's success destroyed the runway it was counting on. Pulsed field ablation now represents roughly 80–85% of the U.S. atrial fibrillation ablation market by the company's own estimate.29 When a company's growth comes from converting a market to a new technology, and that conversion is essentially complete, the growth algorithm changes fundamentally: from "take the market from thermal" to "take share from other PFA vendors." Management guided U.S. electrophysiology to flat-to-low-single-digit growth for 2026.29 That is not a monopoly's growth rate.
Second, competitors arrived with structural advantages Boston Scientific cannot easily neutralize. Medtronic's Affera Sphere-9 combines pulsed field and radiofrequency in one catheter integrated with its own mapping system. Johnson & Johnson's VARIPULSE plugs directly into CARTO, the dominant electroanatomic mapping platform in electrophysiology labs — meaning the switching cost that protected Boston Scientific in catheters works in reverse in mapping. Abbott has been ramping its Volt platform. The point is not that any single competitor's catheter is better; it is that the ablation catheter is one component of a workflow, and Boston Scientific does not own the rest of the workflow the way J&J does.
Third, hospital purchasing behaviour. Electrophysiology labs have strong operational reasons to qualify more than one vendor: supply continuity, price leverage, and physician preference heterogeneity within a single practice. Dual-sourcing is the normal end-state of a maturing device category, and it caps any single vendor's share well below monopoly.
The calibrated conclusion. The strong claim is rejected. Boston Scientific remains the pulsed field volume leader — 500,000 patients treated as of September 2025 is a real and hard-to-replicate installed base of physician experience.12 But the economics of leadership have changed from "converting a market" to "defending share in a mature one," and management's own guidance says so. The narrower claim that survives is this: FARAPULSE gives Boston Scientific a top-one-or-two position in a large, still-growing category, at growth rates that will look like the rest of medtech rather than like 2024.
The KPI that tests it going forward is specific: U.S. electrophysiology revenue growth, disclosed each quarter. If U.S. growth stabilizes and reaccelerates toward the market's rate as FARAWAVE Ultra and the OPAL mapping system launch, the narrowed claim holds. If U.S. electrophysiology stays flat or declines while the market grows, share loss is structural rather than transitional.
WATCHMAN and the clinical-evidence trap
The WATCHMAN reversal is a different and in some ways more instructive failure, because it was caused by clinical evidence rather than competition.
The CHAMPION-AF trial, presented at the American College of Cardiology meeting in March 2026, randomized 3,000 atrial fibrillation patients to WATCHMAN FLX or a direct oral anticoagulant. At three years, left atrial appendage closure met non-inferiority on the composite of cardiovascular death, stroke, and systemic embolism, at 5.7% versus 4.8%, and was superior on non-procedural bleeding, at 10.9% versus 19.0%.30
On paper, a win. In practice, an "uneasy" one. The trial showed an unexpectedly higher — though not statistically significant — rate of ischemic strokes in the device arm, 3.2% versus 2.0%, which sits awkwardly against a device sold as stroke prevention. Nearly half of patients in both arms underwent atrial fibrillation ablation, a potential confounder since successful ablation may itself reduce the need for anticoagulation. And the separate CLOSURE-AF trial produced divergent results.30
Boston Scientific's chief medical officer, Dr. Ken Stein, acknowledged on the second quarter call that there was "confusion around CHAMPION" and that referral patterns had shifted toward watch-and-wait.29 Mahoney said the market had "changed dramatically" over six months.10 Standalone WATCHMAN procedures in the U.S. were declining at a mid-teens rate; the company expected global WATCHMAN sales to decline mid-to-high single digits in the second half of 2026, against a September 2025 investor day expectation that the left atrial appendage closure market would grow 20%-plus.2912
The one genuinely encouraging datapoint: concomitant procedures — WATCHMAN implanted during the same session as an ablation — grew more than 60% and now represent about a third of U.S. WATCHMAN volume.29 That is a real structural shift, and it is a direct beneficiary of Boston Scientific owning both the ablation catheter and the occluder. But it is growing off a smaller base than the standalone business it is replacing.
The investor lesson generalizes beyond this company: in device markets, the trial that expands your label can simultaneously contract your market, because it forces the entire referral chain to re-examine an assumption it had stopped questioning. A "positive" trial result is not a commercial result.
Capital allocation in 2026: the promise and the deviation
Set the September 30, 2025 statement — "very focused on tuck-in M&A" — next to what followed.12
On January 15, 2026, Boston Scientific agreed to acquire Penumbra for $14.5 billion, or $374 per share, an approximately 19% premium, structured roughly 73% cash and 27% stock, with the roughly $11 billion cash portion funded from cash on hand and new debt.8 Penumbra makes thrombectomy devices — catheters that mechanically remove blood clots in pulmonary embolism, stroke, and deep vein thrombosis — plus an embolization system, and was expected to generate approximately $1.4 billion of revenue in 2025 with 17%-plus growth.8 The strategic logic is coherent: Mahoney described it as entering "new, fast-growing segments within the vascular space," and the category had been validated by Stryker's $4.9 billion purchase of Inari Medical in 2025.8 Management expects the deal to close in the second half of 2026 and to be slightly dilutive initially.29
On May 18, 2026 came the $1.5 billion MiRus investment described earlier, with a further $3 billion of optional payments.20
Meanwhile the company completed a $2 billion accelerated share repurchase covering 40 million shares, and announced a restructuring program targeting approximately $500 million of run-rate savings by the end of 2029 — over half by the end of 2027 — at a cost of $700–800 million in pre-tax charges spanning 2026 to 2029.2910
An activist reading this sequence would frame it as follows. Within roughly seven months of telling investors that the plan was tuck-in acquisitions and 10%-plus organic growth, management committed approximately $16 billion of capital across one large acquisition and one large minority stake in a market it has already failed in twice, bought back $2 billion of stock at prices well above where the shares subsequently traded, and announced a restructuring program whose savings arrive years after the growth shortfall. Each decision may be individually defensible. The sequence is harder to defend as evidence of the disciplined capital allocation the company claims as a core competency, and it earns a comparison to 2006 that management would prefer to avoid — the difference being that Penumbra's franchise is growing and undamaged, where Guidant's was neither.
The gross debt leverage ratio was 1.9x at December 31, 2025.31 Funding roughly $11 billion of cash consideration for Penumbra will move that materially, into a period of decelerating organic growth. That is the specific interaction an investor should watch: leverage rising as growth falls is the same shape as 2006, even if the magnitudes are far smaller and the acquired asset is far healthier.
The rest of the portfolio, which is doing fine
It would misrepresent the business to describe only the two franchises that broke. Interventional cardiology therapies grew 15% in the second quarter of 2026, driven by coronary therapies, drug-coated balloons, and complex percutaneous coronary intervention. Neuromodulation grew 12.2%, helped by the recently completed Nalu Medical acquisition. Endoscopy grew 7.0%, with the AXIOS stent — an hourglass-shaped, electrocautery-enhanced stent that lets an endoscopist drain a pancreatic fluid collection through the stomach wall without surgery — continuing to anchor the franchise. Asia-Pacific grew 11.2% operationally.29 Mahoney's framing on the call was that roughly 75% of the revenue base continues to grow around 6%, consistent with history.29
That framing is defensible and also revealing. A company growing 75% of its revenue at 6% is a good medical technology company. It is not a 10%-plus organic grower. The 10%-plus algorithm depended on the other 25% compounding at extraordinary rates, and that is precisely the part that broke.
Which brings us to what an investor should actually take from four decades of this history.
VIII. Playbook: Business & Investing Lessons
The 7 Powers, honestly scored
Hamilton Helmer's strategy framework asks a central question: what persistent differential allows a business to earn returns above its cost of capital while competitors actively try to erode them? Applied to Boston Scientific in late 2026, the answers are more nuanced than a year earlier.
Switching costs — real, but operator-level and conditional. An electrophysiologist who has completed hundreds of procedures using FARAPULSE and its FARAVIEW visualization system has invested substantial time in mastering that workflow. Switching to a competitor costs valuable procedure time in a catheterization lab where throughput is the primary operating metric. Yet 2026 demonstrated that operator loyalty is not an impenetrable moat. U.S. electrophysiology revenue grew just 3% in the second quarter of 2026 against a market expanding significantly faster, demonstrating that switching costs slowed share loss rather than preventing it.29 The competitive dynamic with Johnson & Johnson offers a useful comparison: VARIPULSE integrates directly into J&J's dominant CARTO mapping platform, creating an institutional switching cost at the lab level. Boston Scientific's proprietary OPAL mapping system represents an effort to build equivalent structural lock-in at the facility level rather than relying solely on physician preference. Whether OPAL succeeds remains an open question rather than an established advantage.
Process power — the strongest and most under-appreciated power here. Precision micro-catheter extrusion with graded stiffness, nitinol braiding, drug-polymer coating chemistry, and reliable high-voltage pulse generation represent manufacturing disciplines refined over decades. These capabilities reside in proprietary tooling, manufacturing facilities, and workforce expertise rather than patents alone. This technical foundation enabled Taxus's deliverability advantage in 2004 and facilitated FARAPULSE's rapid commercial ramp in 2024. Chief Executive Officer Michael Mahoney has repeatedly credited operations and supply chain management with keeping pace with surging demand during the FARAPULSE rollout, a claim supported by manufacturing performance.2712 While process power does not prevent competitive entry—as seen in both stents and pulsed field ablation—it enables Boston Scientific to enter new categories and scale production faster than most peers.
Scale economies — moderate, and largely table stakes. A workforce of roughly 59,000 employees alongside a global regulatory, clinical, and commercial footprint allows the company to amortize clinical trial costs and sales infrastructure across eight operating divisions while bundling products into group purchasing organization contracts.2 However, scale in medical technology is not a unique differentiator; peers such as Medtronic, Abbott, and Johnson & Johnson MedTech maintain comparable or greater scale. Within this industry, scale is a baseline requirement rather than an exclusive competitive moat.
Counter-positioning — historically decisive, currently absent. Catheter-based angioplasty counter-positioned against open-heart surgery, just as pulsed field ablation counter-positioned against thermal ablation. In both instances, established market leaders faced a dilemma: cannibalize existing revenue streams or cede market share to an emerging technology. That structural advantage historically drove Boston Scientific's major growth cycles. By 2026, however, Boston Scientific has become the incumbent in pulsed field ablation, and none of its current product lines counter-position competitors into inaction. Medtronic, Johnson & Johnson, and Abbott all responded rapidly with competing platforms.
Cornered resource, network economies, branding — not material. No meaningful network effects exist in medical catheter sales, where each device operates independently. Brand reputation matters to hospital procurement committees primarily as a proxy for product reliability. Furthermore, the company holds no cornered resource; the core FARAPULSE technology was acquired on the open market rather than developed via an exclusive proprietary discovery.
The overall assessment: Boston Scientific possesses genuine process power, faces decaying switching costs in its primary growth franchise, and currently lacks a counter-positioned growth engine. It remains a robust medical technology enterprise, but not an unassailable fortress.
The venture M&A playbook, restated with its failure rate
The mechanics of Boston Scientific's M&A playbook follow a clear, repeatable framework:
- Take minority equity positions early — Boston Scientific maintained a minority stake in Farapulse for seven years before acquiring the remaining equity outright.25 This early involvement provides operational visibility and technological insight alongside financial optionality.
- Structure transactions with modest upfront cash commitments and substantial contingent milestone payments, transferring clinical and regulatory risk to the sellers.
- Leverage internal clinical trial capabilities to fund and execute pivotal regulatory studies — such as the ADVENT trial for pulsed field ablation and the OPTION and CHAMPION-AF trials for WATCHMAN.2630
- Deploy approved devices through established global sales channels to maximize commercial launch velocity.
Chief Executive Officer Michael Mahoney noted at the 2025 investor day that Boston Scientific executed this model across approximately 50 acquisitions and 45 venture investments during his tenure.12 While the structural template is sound and has produced significant winners, evaluating the model requires considering its historical failure rate alongside its successes. Examples include three separate discontinued TAVR platforms, the Silk Road Medical integration that resulted in closing its Sunnyvale headquarters and eliminating 138 jobs within two months of acquisition, and a urology business that grew less than 1% in the second quarter of 2026 shortly after absorbing the $3.67 billion Axonics acquisition.232921 The strategy generates occasional outsized winners alongside a broader portfolio of modest or negative returns. Investors should evaluate this approach as a venture portfolio strategy rather than a guaranteed engine of category creation.
Management credibility, assessed on behaviour
Evaluating management execution requires separating short-term sentiment shifts from long-term operational performance. The record reflects both significant achievements and notable forecasting failures.
Demonstrated operational execution. Taking leadership in 2012 following years of single-digit stock performance and elevated leverage, Mahoney oversaw more than a decade of operating margin expansion, balance sheet deleveraging, and revenue growth above industry averages. The 2023 investor day target of 8% to 10% organic revenue growth for the 2024–2026 period was exceeded during its first two years, with organic growth reaching mid-to-high teens rates in both 2024 and 2025.323
Forecasting and guidance revisions. At the September 30, 2025 investor day, management established a 10%-plus organic growth target for 2026–2028, presenting the figure as an achievable baseline.12 Subsequent performance diverged sharply from that outlook: full-year 2026 guidance was lowered from 10% to 11% in February, to 7% to 8.5% reported in April, and to 5.5% to 6.5% reported in July.3910 Furthermore, management's February statement that Boston Scientific would be the clear leader in pulsed field ablation by year-end occurred during the same quarter that U.S. electrophysiology growth began decelerating.28 Management attributed the miscalculation to rapid market shifts—specifically, faster-than-expected market conversion to pulsed field ablation and shifting referral patterns following the CHAMPION-AF trial. Nevertheless, the revisions highlighted significant internal forecasting errors across the company's two primary growth platforms within a single year.
Transparency and operational response. In contrast to historical disclosure challenges during the Guidant era, management acknowledged the guidance shortfalls directly, quantified the impact across affected product lines, and stated that headwinds in both WATCHMAN and electrophysiology would persist through 2027, pairing these disclosures with a structured cost-reduction program targeting $500 million in annual run-rate savings by the end of 2029.2910
Insider ownership signals. Mahoney's August 2026 open-market stock purchase—an unplanned, non-10b5-1 transaction of approximately $9 million that expanded his direct holdings past 1.59 million shares—represents a meaningful commitment of personal capital during a period of market repricing.1 While executive stock purchases do not guarantee an equity recovery, discretionary open-market buys provide a clear signal of leadership confidence.
Financial leadership transition. Chief Financial Officer Dan Brennan retired after nearly three decades with the company, succeeded by Jon Monson—a 25-year company veteran and former global controller—effective June 30, 2025.33 While an internal succession maintains operational continuity, it placed a newly appointed financial officer in charge shortly before the company introduced its three-year financial target in September 2025.
The capital allocation audit
Boston Scientific maintained balance sheet discipline throughout the post-Guidant decade, bringing its gross debt leverage ratio down to 1.9 times by the end of 2025, well below its historical peak.31 The key financial question facing the company is whether this balance sheet discipline will persist as it simultaneously funds the $14.5 billion Penumbra acquisition, maintains its $3.0 billion purchase option for MiRus, and navigates a period of slower top-line growth. According to company proxy disclosures, executive incentive compensation remains tied to organic revenue growth, adjusted operating margin expansion, and relative total shareholder return.34 While these performance metrics align leadership incentives with operational targets, large acquisitions structured with initial dilution followed by accretion can temporarily improve operating margin metrics over a multi-year evaluation window, even if the underlying transaction fails to generate returns above the cost of capital.
IX. Analysis & Bear vs. Bull Case
The spine: why this wins from here, and what breaks it
Strip away the narrative, and the investment question in the autumn of 2026 reduces to a single disagreement about duration.
Why Boston Scientific wins from here. The bull case does not depend on FARAPULSE reaccelerating. It depends on three conditions holding simultaneously. First, that the roughly three-quarters of revenue growing around 6% remains stable — second-quarter 2026 performance, with interventional cardiology up 15%, neuromodulation up 12%, endoscopy up 7%, and Asia-Pacific up 11%, indicates that this foundation remains steady.29 Second, that the innovation pipeline management outlined for 2027 and 2028 converts: the SEISMIQ coronary intravascular lithotripsy catheter, FARAWAVE Ultra, entry into the roughly $1 billion intracardiac echocardiography market, the PRECEDENT defibrillator platform to address cardiac rhythm gaps driving a 2% decline, renal denervation, and Penumbra's thrombectomy franchise.29 Third, that the restructuring delivers approximately $500 million in run-rate savings, protecting earnings while top-line growth normalizes.10
If those conditions hold, an investor is buying a diversified medical technology enterprise with genuine process power, growing in the high single digits with expanding margins, at a valuation that no longer embeds a premium growth algorithm.
Why it may not. The bear case is that the market is repricing something structural, not cyclical. Boston Scientific's premium multiple was earned during a five-year period when two franchises grew at rates no large-cap medtech company sustains long term. Both are now decelerating for reasons that execution alone cannot easily fix: pulsed field conversion is largely complete and competitors are integrated into workflows Boston Scientific does not control, while the left atrial appendage referral pattern was disrupted by clinical evidence the company itself generated. Meanwhile, management committed roughly $16 billion of capital across Penumbra and MiRus into a decelerating base, after telling investors the plan was tuck-in acquisitions.82012
The activist version of this argument is pointed: a skeptical investor would argue that management responded to a growth slowdown by buying growth — the precise reflex that produced the Guidant disaster — and that the $2 billion accelerated share repurchase executed in 2026 destroyed value by buying stock before two guidance cuts.29 They would question whether an eight-business-unit portfolio spanning coronary stents, defibrillators, kidney stone baskets, spinal cord stimulators, and now thrombectomy represents a strategic portfolio or a conglomerate. They would also note that combining the chairman and chief executive roles since 2016 concentrates accountability for the targets that were just missed.
The counterargument regarding Penumbra is significant. Guidant was a damaged franchise facing a live Class I recall and criminal exposure. Penumbra is a growing, undamaged business in a validated category. Paying a 19% premium for a $1.4 billion revenue asset growing at 17% is a fundamentally different transaction than paying $27 billion for a defibrillator business whose clinical trust had collapsed.8 Whether it proves to be a sound transaction depends on the returns relative to the price paid, which will not be clear for several years.
Porter's five forces, applied to a catheter company
Rivalry — intense and intensifying. Four large, well-capitalized competitors — Medtronic, Abbott, Johnson & Johnson MedTech, and Edwards Lifesciences in structural heart — possess overlapping portfolios and the resources to fast-follow any new category. The 2026 electrophysiology experience demonstrates this dynamic: a two-year technology lead was substantially eroded within roughly 30 months of FDA approval.[^30]29
Buyer power — rising and under-appreciated. The primary buyer is not the individual physician, but the hospital system's value analysis committee and, increasingly, the group purchasing organization. Consolidation among U.S. health systems has strengthened institutional purchasing power, and dual-vendor qualification in electrophysiology labs is a deliberate strategy to preserve pricing leverage. Capital constraints on ablation generator consoles create a second layer of purchasing friction, as a hospital that purchases one vendor's console has a structural incentive to continue buying that vendor's catheters — a lock-in that benefits Boston Scientific where it placed the console, and works against it where it did not.
Supplier power — low. Polymers, nitinol, and electronic components are not scarce commodities. The company's own manufacturing capacity represents the primary constraint, and operations have generally managed volume well.
Threat of substitutes — the underrated force. Medical technology differs from most industries in that the substitute for a device is frequently a pharmaceutical therapy or a shift in clinical practice, driven by trial results rather than price. The WATCHMAN slowdown in 2026 is a textbook example: volume was not lost to a direct competitor; rather, the referral pattern shifted following new clinical evidence.2930 Any Boston Scientific franchise can be substituted by improved pharmacology or updated clinical guidelines on a timeline outside the company's control.
Threat of new entrants — low at scale, high at the category level. Establishing a direct competitor to Boston Scientific's broader enterprise is prohibitive. However, venture-backed startups regularly establish new device categories, and incumbent medical technology companies typically respond by acquiring them. This is precisely the market in which Boston Scientific competes for acquisitions, driving up entry valuations for assets like Penumbra.
The bull case, stated fairly
Pipeline breadth. Management has highlighted seven major product launches targeting an addressable market exceeding $25 billion across 2027 and 2028, projecting meaningful revenue and earnings expansion beginning in 2028.29 The company's track record of translating acquired technologies into commercial products remains strong where the device matches its core catheter delivery capabilities.
International runway. Electrophysiology grew 23% internationally in the second quarter of 2026 while growing 3% in the U.S., while WATCHMAN expanded 18% internationally against 3% domestically.29 Both franchises remain years behind U.S. adoption levels in Japan, China, and Latin America. While international markets offer a meaningful growth runway, they typically yield lower average selling prices, and Chinese volume-based procurement continues to pressure device margins.
The concomitant procedure. WATCHMAN implants performed during the same clinical session as an ablation grew over 60% and now represent roughly one-third of U.S. volume.29 Boston Scientific remains the only medical device company offering both the leading pulsed field ablation catheter and the leading left atrial appendage occluder, creating a genuine structural portfolio advantage.
MedSurg's resilience. The endoscopy and urology divisions generate high gross margins and operate independently of cardiovascular competitive pressures. The AXIOS stent, in particular, anchors a category that Boston Scientific created and continues to lead.
The bear case, stated fairly
Price and mix compression in electrophysiology. As four vendors offer functionally similar single-use catheters to consolidated hospital purchasing organizations, gross margin premiums inevitably compress. While management has not disclosed FARAPULSE-specific pricing, the trajectory across maturing medical device categories is consistent.
Litigation tail risk. Product liability remains a persistent operational risk. In March 2021, Boston Scientific paid $188.6 million to 47 states and the District of Columbia to resolve claims regarding deceptive marketing of pelvic mesh products, following earlier settlements of thousands of individual claims.3536 Combined with historical Guidant recalls and the LOTUS and ACURATE device withdrawals, the record demonstrates that device liabilities and product discontinuations occur with measurable frequency. This risk is an inherent characteristic of implantable medical technology.
Integration and leverage stacking. Axonics, Silk Road, Relievant, Nalu, and Penumbra represent a heavy concentration of integration work over a short timeframe.212224298 Urology's sub-1% growth in the second quarter of 2026, less than two years after closing the Axonics acquisition, highlights the operational friction associated with multi-asset integration.29
The 2028 promise. Management's growth outlook is explicitly back-end loaded, promising material improvement beginning in 2028.29 This requires investors to hold the stock through an extended transition period based on pipeline execution, echoing the structure of the multi-year targets introduced at the September 2025 investor day.
Myth versus reality
Myth: Boston Scientific abandoned mega-M&A after Guidant. Reality: The company refrained from large-scale acquisitions for nineteen years before announcing the $14.5 billion purchase of Penumbra in January 2026, four months after reiterating a strategy focused on tuck-in acquisitions.812 While Penumbra represents a healthier operating asset than Guidant, the narrative of unbroken small-deal discipline no longer holds.
Myth: FARAPULSE created an $8 billion-plus monopoly. Reality: The platform established a leadership position within a $13 billion market, which four competitors entered within two years, and where U.S. market conversion is largely complete.1229
Myth: WATCHMAN's pivotal trials expanded the market. Reality: While the CHAMPION-AF trial met its primary endpoints, it introduced sufficient clinical ambiguity — including a numerically higher rate of ischemic strokes, potential ablation confounding, and conflicting trial data — to slow physician referral momentum.3029 Positive trial endpoints do not automatically guarantee commercial expansion.
Myth: The 2026 share price decline is a valuation reset on an unchanged business. Reality: Core operational fundamentals altered significantly. Organic growth guidance was lowered from 10–11% to 5–6% within six months, with management confirming that growth headwinds will persist through 2027.31029
The KPIs that matter
Three key metrics will determine the trajectory.
1. U.S. electrophysiology revenue growth, quarterly. This metric provides the clearest measure of whether pulsed field ablation share loss is temporary or structural. U.S. performance is critical because it represents the market where competitive intensity is highest and market conversion is furthest along.
2. Organic net sales growth, consolidated. Boston Scientific's premium valuation multiple depended on organic growth nearly doubling industry averages. Tracking where consolidated growth stabilizes — whether at 6%, 8%, or 10% — will reveal how the market values the restructured enterprise.
3. Adjusted operating margin. Amid decelerating top-line growth and a $700–800 million restructuring program, operating margin represents the primary financial variable within management's direct control.10 Management originally targeted roughly 50 basis points of annual margin expansion toward 30%, but 2026 guidance was revised to 0 to 25 basis points.1229 The magnitude of that reduction measures how much operating leverage was absorbed by the growth slowdown.
X. Epilogue & "If We Were CEOs"
In Marlborough, Massachusetts, in late August 2026, the enterprise that grew from an $800,000 catheter shop employs roughly 59,000 people across eight medical specialties worldwide.2 Chief Executive Officer Michael Mahoney recently purchased $9 million of company stock on the open market following a steep decline that left shares trading at less than half their prior peak.1 The strategic question facing leadership is not whether the core business remains viable, but how management allocates capital and focuses operations over the next three years.
Fix cardiac rhythm management, or exit it. Cardiac rhythm management net sales declined 2% in the second quarter of 2026, with management pointing to the PRECEDENT platform—scheduled to launch in the second half of 2027 and characterized internally as a major generational upgrade—as its primary solution.29 Relying on a future product line to reverse a contracting segment requires an extended holding period for a franchise inherited from Guidant that has struggled to earn its cost of capital. A rigorous strategic assessment would evaluate whether maintaining a third-place position behind Medtronic and Abbott serves as a core portfolio asset or an operational drag.
Resist the temptation to buy the next growth story. Historical precedent shows a consistent corporate pattern: when organic revenue growth decelerates, Boston Scientific resorts to major M&A, as seen in 1994, 2006, and again with the Penumbra announcement in 2026. While the Penumbra acquisition targets a healthy, expanding asset, executing further large transactions using debt financing while organic growth slows would compound financial leverage risks. To rebuild market credibility in 2027, management's primary focus should be closing and integrating Penumbra cleanly while refraining from additional large-scale acquisitions.
Make the MiRus decision on the data, not on the sunk cost. Boston Scientific committed $1.5 billion for a minority stake in MiRus—its fourth entry attempt into transcatheter aortic valve replacement after three previous platform withdrawals—with up to $3.0 billion in optional milestone payments remaining.20 The key test of capital discipline is whether management resists exercising that option if the STAR pivotal trial fails to demonstrate clinical superiority or clear non-inferiority against established platforms like Edwards' Sapien and Medtronic's Evolut. Given that ACURATE was commercialized internationally for years before failing its randomized pivotal trial, proceeding without decisive clinical evidence presents significant operational risk.
Compete on the workflow, not just the catheter. Competitive dynamics in 2026 demonstrated that catheter design alone cannot easily overcome an integrated electrophysiology mapping workflow, such as Johnson & Johnson's CARTO platform. Boston Scientific possesses key ecosystem components—including the OPAL mapping system, FARAVIEW visualization software, emerging intracardiac echocardiography tools, and Preventice remote cardiac monitoring. Combining these technologies into a unified diagnostic and therapeutic workflow creates institutional lock-in at the facility level, offering a more defensible moat than standalone catheter hardware.
Reset the target-setting culture. Management's assertion at the September 2025 investor day that the company had consistently met or beaten its multi-year targets preceded two downward guidance revisions within ten months, lowering 2026 organic growth expectations from 10–11% down to 5.5–6.5%.12310 Rebuilding investor credibility requires introducing realistic guidance ranges rather than rigid floors, providing transparent accounting of what internal forecasting models missed regarding WATCHMAN and electrophysiology adoption, and establishing long-term targets that account for aggressive competitive responses.
From its origins in Watertown, Massachusetts, to a global enterprise built on substituting open surgery with catheter-based interventions, Boston Scientific established a major footprint in modern medical technology. Yet its nearly five-decade history illustrates a recurring strategic lesson: pioneering a novel medical category and maintaining long-term market dominance require distinct operational capabilities—and the company has consistently proven more adept at the former.
XI. Recent News & Transcripts Guide
For investors seeking to verify this analysis against primary sources, key public filings, earnings calls, and transaction announcements document the company's operational transition.
The full-year 2025 results, released February 4, 2026. The company reported $20.074 billion in net sales, GAAP net income of $2.898 billion, Cardiovascular segment net sales of $13.250 billion, MedSurg net sales of $6.824 billion, and initial 2026 organic net sales growth guidance of 10.0% to 11.0% with adjusted earnings of $3.43 to $3.49 per share.3 Examining the release alongside the market reaction highlights the initial divergence: an 18% single-day share price decline driven not by the full-year totals, but by sequential flatness in electrophysiology and WATCHMAN alongside Chief Executive Officer Michael Mahoney's dispute with competitors regarding quarterly market growth.28 The gap between strong full-year financial results and an immediate market selloff marked a pivotal inflection point in public sentiment.
The September 30, 2025 investor day transcript. This transcript serves as a baseline for assessing management credibility, detailing medium-term guidance and corporate strategy: 10%-plus organic revenue growth for 2026 through 2028, approximately 50 basis points of annual adjusted operating margin expansion toward 30%, 70% to 80% free cash flow conversion, a $13 billion electrophysiology market expanding at 15%, a left atrial appendage closure market growing above 20%, an explicit commitment to tuck-in acquisitions, and management's statement that the company had consistently met or exceeded its investor day targets.12 Subsequent corporate communications provide a benchmark against these baseline projections.
The first quarter 2026 call, April 22, 2026. This transcript records the company's initial guidance reduction alongside decelerating momentum across three key operating segments: U.S. electrophysiology share erosion, WATCHMAN volume declines starting in February, and urology growth slowing to roughly 2%.9 Mahoney's acknowledgment that management was not proud of the guidance cut marked a formal departure from the growth algorithm outlined seven months earlier.
The second quarter 2026 call, July 29, 2026. This call provided comprehensive detail on operational adjustments, outlining a second guidance reduction, a $500 million annual run-rate restructuring program, disclosure that pulsed field ablation represented 80% to 85% of the U.S. atrial fibrillation market, and confirmation that growth headwinds in electrophysiology and WATCHMAN would persist through 2027.29 During the question-and-answer session, Chief Medical Officer Dr. Ken Stein detailed referral confusion following the CHAMPION-AF trial, while executive commentary shifted strategic expectations toward 2028 commercial catalysts. Discussions during the call also highlighted concomitant WATCHMAN procedure growth of over 60% as a primary structural driver offsetting standalone volume softness.
The Penumbra transaction materials, January 15, 2026. Documents detailing the $14.5 billion acquisition offer at $374 per share—structured as roughly 73% cash and 27% stock—outline approximately $11 billion in cash consideration funded through cash reserves and new debt issuance to acquire a thrombectomy business generating roughly $1.4 billion in 2025 revenue with 17%-plus organic growth.8 Following transaction close, analytical focus centers on managing combined balance sheet leverage during a period of reduced core organic growth.
The Form 4 filed August 5, 2026. Disclosures detail Mahoney's discretionary open-market purchase of 186,240 shares at a weighted average price of $48.3323 per share—executed outside a 10b5-1 trading plan—alongside an additional 22,119 shares acquired through his 401(k) plan, bringing his direct ownership to 1,590,024 shares.1 Open-market purchases of this magnitude by an active chief executive signal internal leadership confidence, though they do not guarantee immediate equity repricing.
The annual filings. The 2025 and 2024 Form 10-K filings provide detailed operating segment results, litigation disclosures, goodwill and intangible impairment evaluations, and debt maturity schedules.3137 The 2025 proxy statement outlines executive compensation structures and performance metrics tied to corporate targets.34 The complete historical record of public filings is accessible through the Securities and Exchange Commission's EDGAR system.38
References
-
Form 4 — Boston Scientific Corp insider trading activity (Michael F. Mahoney open-market purchase) — StockTitan, 2026-08-05 ↩↩↩↩↩
-
Boston Scientific Corporation — Investor Relations Home (share price, market capitalization and corporate data) ↩↩↩↩↩
-
Boston Scientific announces results for fourth quarter and full year 2025 — Boston Scientific, 2026-02-04 ↩↩↩↩↩↩↩↩↩
-
History of Boston Scientific Corporation — FundingUniverse (International Directory of Company Histories) ↩↩↩↩↩↩↩↩↩↩↩
-
Boston Scientific to Pay Johnson & Johnson $1.725 Billion in Stent Lawsuit Settlement — Reuters, 2010-02-01 ↩↩↩↩
-
Boston Scientific Wins Guidant with $27 Billion Bid — The Wall Street Journal, 2006-01-26 ↩↩↩
-
Johnson & Johnson and Boston Scientific Settle Guidant Merger Lawsuit for $600 Million — Reuters, 2015-02-26 ↩↩
-
Boston Scientific to acquire Penumbra for $14.5B — MedTech Dive, 2026-01-15 ↩↩↩↩↩↩↩↩↩↩
-
Boston Scientific slashes 2026 guidance — MedTech Dive, 2026-04-22 ↩↩↩↩↩↩↩
-
Boston Scientific again cuts 2026 guidance — MedTech Dive, 2026-07-29 ↩↩↩↩↩↩↩↩↩↩↩↩
-
Boston Scientific Corp — Encyclopedia.com (International Directory of Company Histories) ↩↩↩↩↩↩↩
-
Boston Scientific Investor Day 2025 — Transcript, 2025-09-30 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
Drug Eluting Stents and Late Stent Thrombosis: Technical Considerations for Interventional Cardiologists — European Cardiology Review ↩↩
-
Boston Scientific Corporation Announces Agreement To Sell Guidant Corporation's Vascular Intervention And Endovascular Businesses To Abbott Laboratories — BioSpace, 2006-01-08 ↩↩↩↩
-
Boston Scientific Strengthens Structural Heart Product Portfolio by Completing Acquisition of Atritech — Boston Scientific, 2011-03-03 ↩↩
-
Boston Scientific Closes Cameron Health Acquisition — Boston Scientific, 2012-06-08 ↩↩
-
Boston Scientific Closes Symetis Acquisition — Cardiac Interventions Today, 2017-05-16 ↩
-
ACURATE neo2 vs. Approved TAVR Devices in All-Risk Patients With Severe AS (ACURATE IDE) — American College of Cardiology, 2024-10-30 ↩
-
Boston Scientific Discontinues Acurate Neo2 and Acurate Prime TAVR Systems — Cardiac Interventions Today, 2025-05-28 ↩
-
Boston Scientific buys $1.5B stake in TAVR developer MiRus — MedTech Dive, 2026-05-18 ↩↩↩↩
-
Boston Scientific to Acquire Axonics for $3.7 Billion — Reuters, 2024-01-08 ↩↩↩
-
Boston Scientific to Acquire Silk Road Medical for $1.26 Billion — Reuters, 2024-06-18 ↩↩
-
Boston Scientific to close Silk Road Medical headquarters, lay off 138 people — MedTech Dive, 2024-10-28 ↩↩
-
Boston Scientific to buy back pain treatment company Relievant for $850M — MedTech Dive, 2023-09-19 ↩↩
-
Boston Scientific spends $295M to snap up rest of cardiac ablation maker Farapulse — MedTech Dive, 2021-06-24 ↩↩↩
-
Pulsed Field or Conventional Thermal Ablation for Paroxysmal Atrial Fibrillation (ADVENT) — New England Journal of Medicine, 2023-08-27 ↩↩
-
Boston Scientific closes its year of PFA on a high note — MedTech Dive, 2025-02 ↩↩↩
-
Boston Scientific's shares tumble 18% despite strong FY25 growth — Medical Device Network, 2026-02-05 ↩↩↩↩↩
-
Boston Scientific (BSX) Q2 2026 Earnings Call Transcript — The Motley Fool, 2026-07-29 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
CHAMPION-AF: An Uneasy Win For Watchman Device — American College of Cardiology, 2026-04-21 ↩↩↩↩↩
-
Boston Scientific 2025 Form 10-K Annual Report — SEC EDGAR ↩↩↩
-
Boston Scientific sees organic sales growth of 8%-10% over three-year period (2023 Investor Day) — TipRanks/The Fly, 2023-09-20 ↩
-
Boston Scientific Chief Financial Officer Dan Brennan to retire; Jon Monson to succeed Brennan — Boston Scientific, 2025-04-23 ↩
-
Boston Scientific 2025 Notice of Annual Meeting & Proxy Statement (Form DEF 14A) — SEC EDGAR ↩↩
-
California Department of Justice Announces $188.6 Million Multistate Settlement with Boston Scientific Corporation — California Office of the Attorney General, 2021-03-23 ↩
-
Boston Scientific Settles Pelvic Mesh Litigation Claims — Reuters, 2015-10-26 ↩
-
Boston Scientific 2024 Form 10-K Annual Report — SEC EDGAR ↩
-
Boston Scientific Corp — SEC EDGAR Filing Index (CIK 0000885725) ↩
 LinkedIn
 WhatsApp
 Reddit
 Hacker News
 Email
 Kindle
 RSS Feed
 Spotify
 Apple Podcasts
 Amazon Music
 Audible
 YouTube