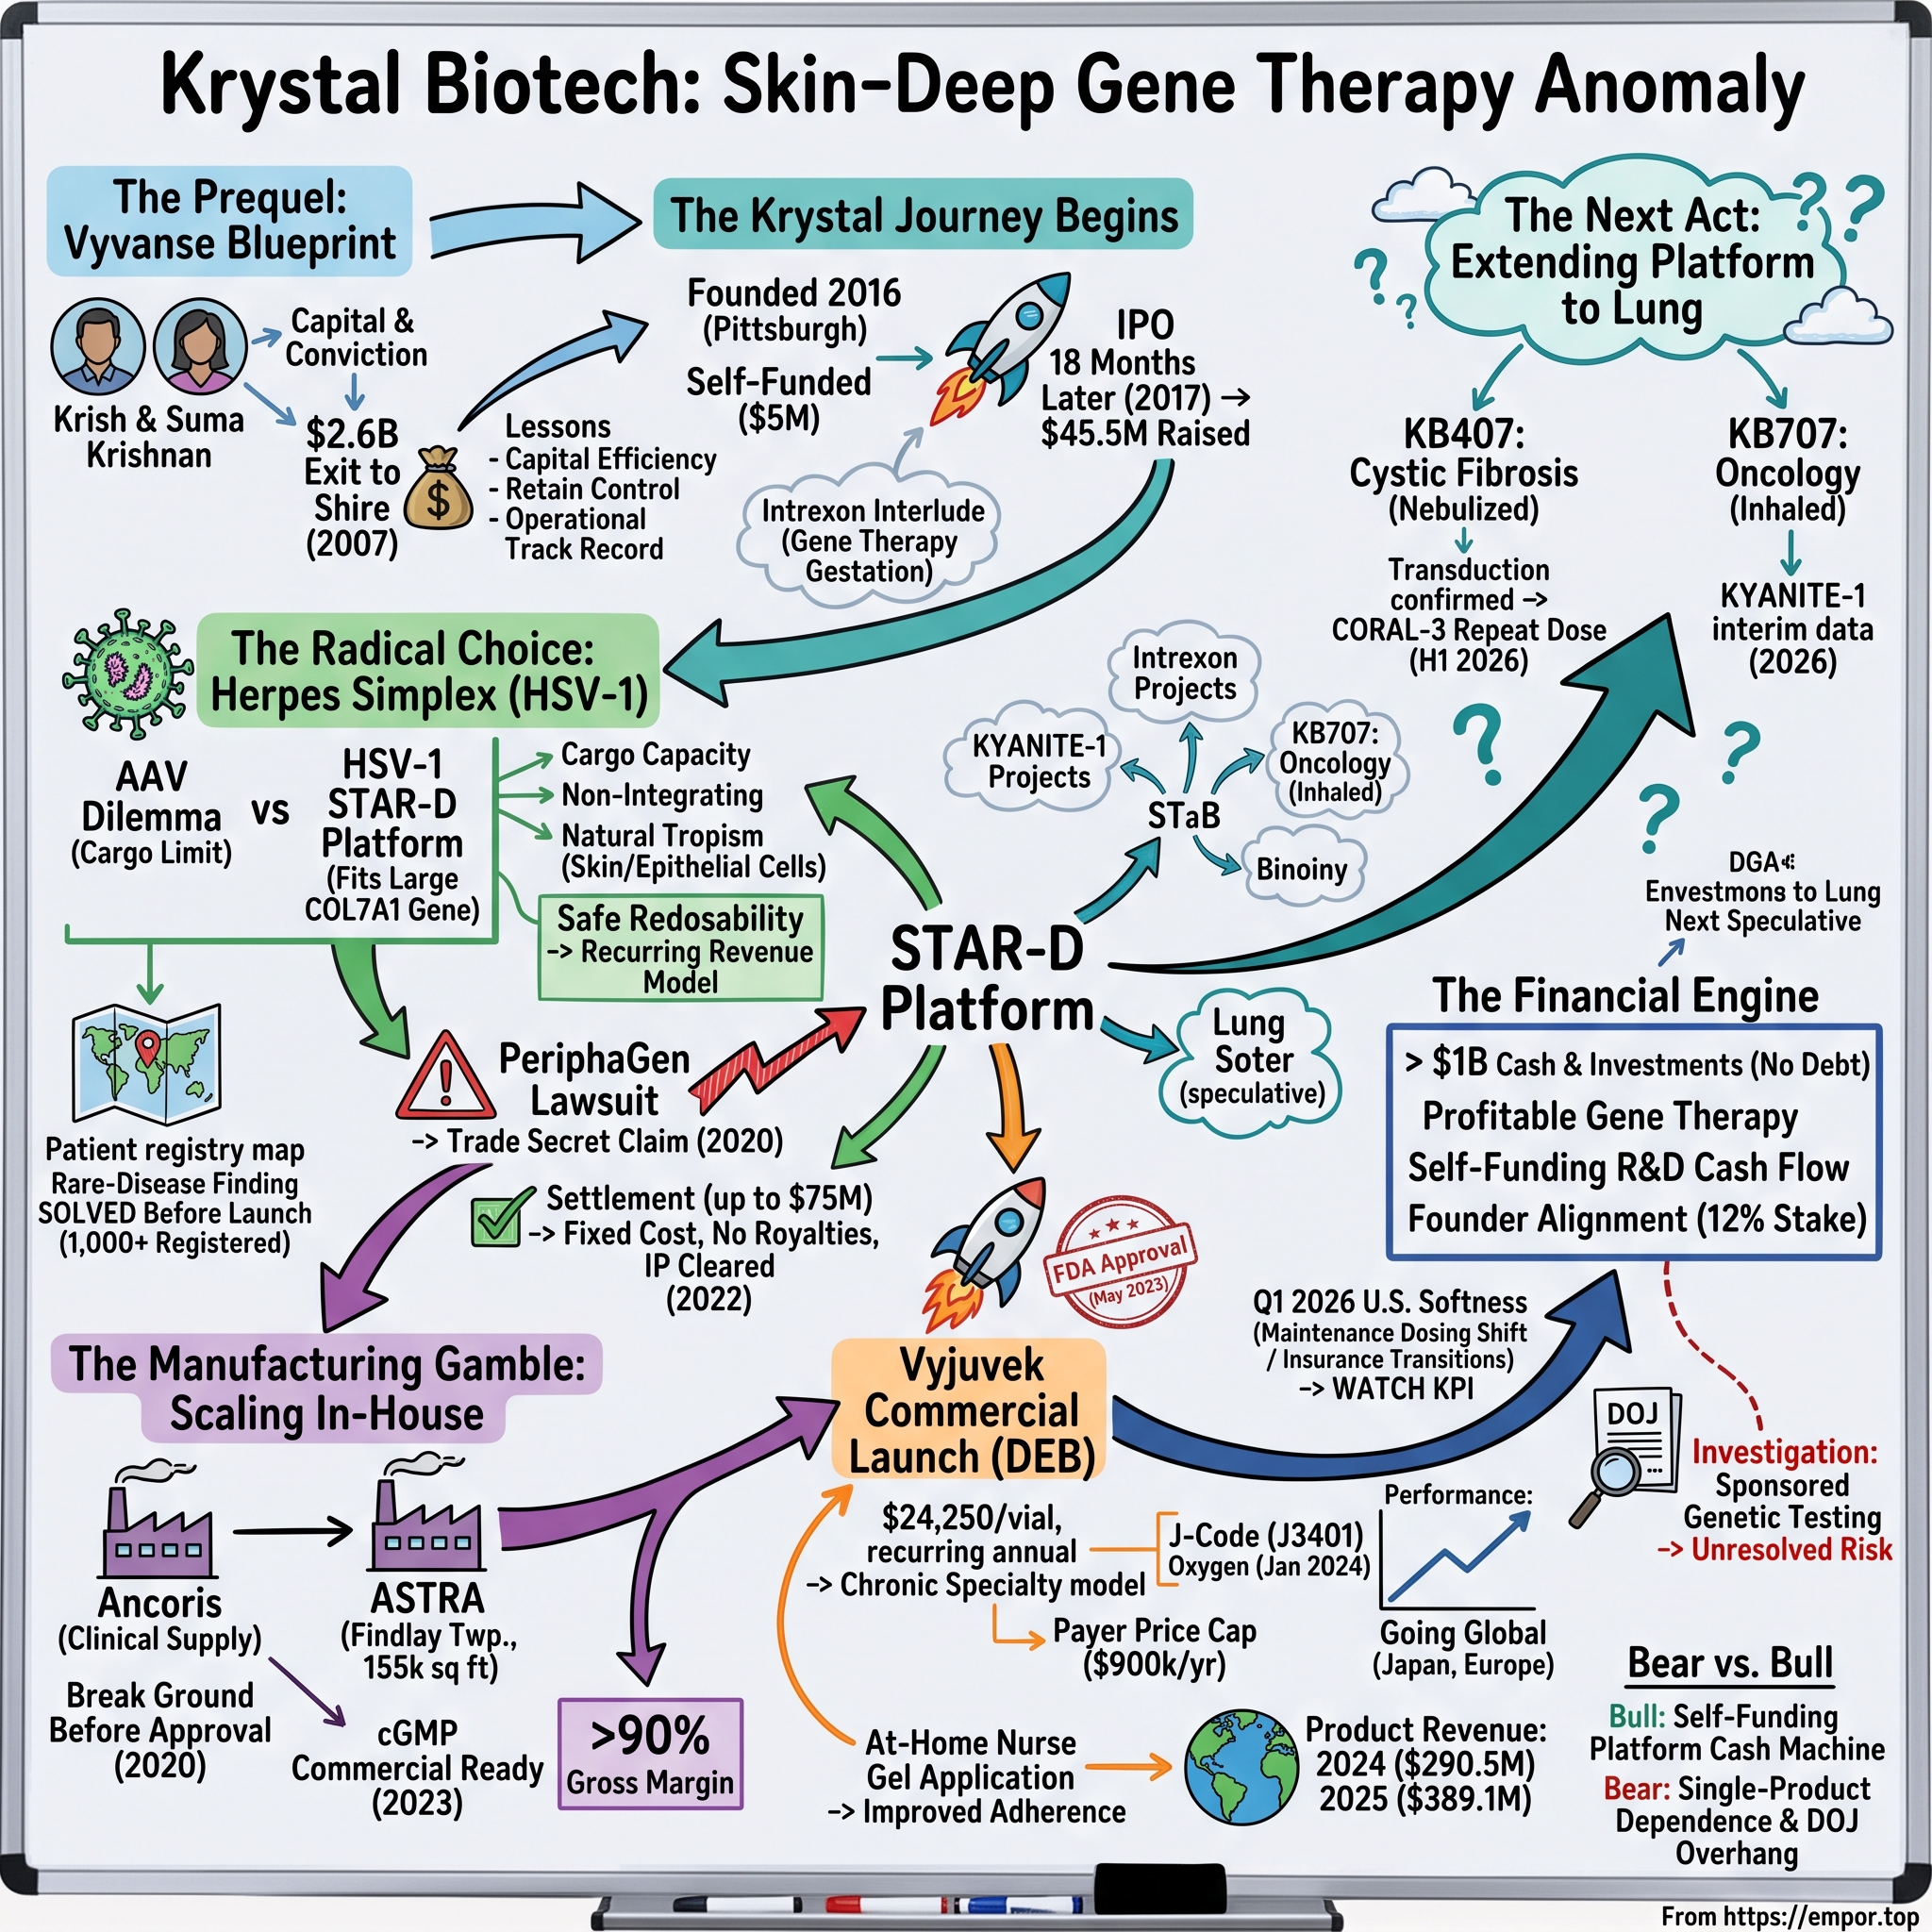
Krystal Biotech, Inc. (NASDAQ: KRYS): The Redosable Gene Therapy Pioneer
I. Introduction & Episode Roadmap
Picture the gene therapy industry circa 2016. The field had just come off a decade of euphoria. Venture money was pouring into companies promising one-time cures for devastating monogenic diseases. The pitch was intoxicating: a single intravenous infusion, one afternoon in a hospital chair, and a lifetime of illness rewritten at the source. Wall Street loved it. Patients' families loved it. And then reality arrived — in the form of manufacturing batches that failed release testing, liver toxicities that showed up in dose-escalation cohorts, neutralizing antibodies that made a second dose impossible, and payers who blanched at seven-figure invoices for therapies whose durability nobody could yet prove.
Into that landscape walked a husband-and-wife team in their fifties, working out of Pittsburgh, with no venture backing, roughly $5 million of their own money, and an idea that most of the field considered either naive or slightly embarrassing.1 They wanted to put gene therapy in a tube. Applied to the skin. By a nurse. Or eventually by the patient. Every week, forever.
Ten years later, that idea is a commercial product on three continents. In the first quarter of 2026, Krystal Biotech reported $116.4 million in global net revenue from VYJUVEK, a 95% gross margin, and $55.9 million of net income — its eleventh consecutive profitable quarter.2 Cumulative revenue since launch had passed $846 million.2 The company ended the quarter with $1.0 billion in cash and investments against total assets of $1.40 billion and stockholders' equity of $1.28 billion, a balance sheet with no meaningful borrowings on it.2
Those numbers deserve context, because in biotech they are genuinely unusual. The overwhelming majority of clinical-stage and even commercial-stage gene therapy companies burn cash continuously and return to the equity market every eighteen to twenty-four months, diluting existing holders to fund the next readout. On the first-quarter 2026 call, CEO Krish Krishnan made the point himself: "We've not accessed the capital market since 2022."3 For a company that has since built out a global commercial organization, launched in the United States, Germany, France and Japan, and is running two registrational trials simultaneously, that is a real fact about capital discipline, not a slogan.
But a compelling origin story is not an investment case, and this article is not a shareholder letter. The interesting questions about Krystal Biotech in mid-2026 are harder than "did the launch work." They are: how much of the gross margin is structural versus a function of a tiny, price-insensitive rare-disease niche? Is the platform genuinely a platform, or is it one spectacular drug plus a pipeline of hypotheses? What happens when the U.S. patient pool saturates — which management has already begun to signal is happening — and revenue growth depends on European price negotiations the company does not control? And what does a company with a billion dollars, no debt, no buyback and no acquisition appetite actually do with its capital?
Here is the roadmap.
We start with the founders — Krish and Suma Krishnan — and the drug that made them, Vyvanse, plus the $2.6 billion exit that funded everything after. Then the science: why Krystal chose herpes simplex virus type 1 as its delivery vehicle when the entire field had standardized on adeno-associated virus, and why that choice is inseparable from the business model. Then the contrarian capital allocation decision that defines the company — building commercial manufacturing before Phase 3 data, at a moment when the textbook said outsource. Then the clinical proof, the competitive field in epidermolysis bullosa, and the commercial rollout with its remarkable cost structure. Then the pipeline — cystic fibrosis, alpha-1 antitrypsin deficiency, oncology, ophthalmology — sized honestly to what has actually been demonstrated. Then a structural analysis using Helmer's 7 Powers and Porter's Five Forces, a playbook of transferable lessons, and finally a genuine bear-versus-bull stress test, including the things a skeptical activist investor would push on hardest.
A word on why this company is worth an investor's time even if they never own a share of it. Krystal is one of the cleanest natural experiments in modern drug development. Two founders made three deliberate, contrarian, expensive choices — an unfashionable viral vector, in-house manufacturing years ahead of proof, and a chronic redosable business model in a field obsessed with one-time cures — and then ran that experiment to a commercial conclusion while a direct competitor made the opposite choice on manufacturing and can be observed in parallel. There are very few places in biotech where you can watch strategy and outcome connect this legibly.
One more framing note before we begin. Krystal's story contains a legal chapter that rarely makes it into the celebratory versions: a trade secret lawsuit filed by a Pittsburgh neighbor that cost the company $75 million to settle and included a claim that outside scientists should have been named as inventors on its core patents.4 We will get there. It matters for how you think about the durability of the moat.
 Subscribe on LinkedIn
II. The Founders' DNA: From Vyvanse to Krystal Biotech
Suma Krishnan grew up in Bombay in a family that struggled financially while raising three children.1 She came to the United States for a master's degree in organic chemistry at Villanova, where she met a graduate student named Krish who was working on an MBA at Wharton.1 That is the whole meet-cute: two immigrants in Philadelphia, one a bench chemist, one a finance person, who would spend the next three decades building drug companies together.
Suma's first serious drug development job was at Janssen.1 Her defining work came later, at New River Pharmaceuticals, a small Virginia company with an unusual thesis. The problem New River set out to solve was not efficacy — amphetamine works perfectly well for attention deficit hyperactivity disorder — but abuse. Stimulant prescriptions were being crushed, snorted and injected. New River's answer was a piece of chemical engineering rather than a new molecule: attach the amino acid lysine to dextroamphetamine, creating a prodrug that is pharmacologically inert until enzymes in the bloodstream cleave the two apart. Snorting it does nothing. Injecting it does nothing. Swallowing it produces a smooth, gradual release. That drug became Vyvanse, and Suma led its discovery, development and approval.1
The commercial arc is the part that shaped everything afterward. New River partnered with Shire to develop and co-promote the compound. In 2007, Shire bought New River outright for $2.6 billion in cash — an extraordinary outcome for a company whose lead asset was, structurally, an old drug with a lysine bolted onto it.5 Krish had run the operational and financial side as COO and CFO.1
Two lessons from that period are visible in everything Krystal has done since.
The first is about control. New River's manufacturing sat with third parties, and the Krishnans came away from that experience convinced that outsourcing the physical production of a complex product is not a cost decision but a risk decision. For a small molecule, that is a manageable annoyance. For a live viral vector, where the product is the process and a shift in bioreactor conditions changes yield, purity and infectivity, it is existential. Hold that thought; Section IV is built on it.
The second is about the capital structure. A $2.6 billion cash exit with a clean cap table produces founders who never have to accept punitive terms again. When the Krishnans started Krystal, they did not raise venture capital. They put in roughly $5 million of their own money and then raised from friends and family, telling those investors explicitly to treat the money as philanthropic given the risk.1 That is not a boast about frugality — it is the reason the founders still held a combined stake of roughly 12% of the company as of mid-2025, and why the company's ownership was never fragmented across successive preferred rounds with liquidation preferences.1
After Shire, both worked at Intrexon, where Suma served as head of therapeutics with a focus on gene therapy.1 That is where she encountered dystrophic epidermolysis bullosa — and where the idea arrived.
The idea was almost aggressively unfashionable. Every serious gene therapy program in 2015 was chasing systemic delivery: get the corrected gene into the liver, the motor neurons, the retina, the bone marrow. Suma's insight ran the other direction. If the diseased tissue is the skin — the most accessible organ in the body, the one you can literally reach out and touch — then why fight the immune system, the liver and the bloodstream at all? Deliver the gene topically. Krish's own recollection of how the idea landed with outsiders is memorable: proposing home-applied gene therapy in a gel was, he said, "like somebody saying today, 'I want to have a house on Mars.'"1
Then there is the choice of Pittsburgh, which the mythology sometimes dresses up as strategic vision. The founders' account is more prosaic: lab space in San Francisco was effectively unavailable during the biotech boom, and Pittsburgh offered the ability to hire graduate students from Carnegie Mellon.1 They commuted from Northern California in the early days.1 What began as a constraint turned into an advantage — cheap industrial real estate in a region with serious academic bioengineering talent is precisely what you need if your plan is to build your own factories, which was not yet the plan but soon would be.
The company went public on Nasdaq in September 2017 in an offering that raised $45.5 million in gross proceeds — 4,554,000 shares at $10.00, with the underwriters exercising their option in full, and Ladenburg Thalmann as sole book-running manager.6 Krish's own description of it is worth quoting because it captures the scale of the enterprise at that moment: "It was a Mickey Mouse IPO."1 A single small-cap bookrunner, a ten-dollar share price, a company with no clinical data and a preclinical asset in a disease most investors had never heard of.
It is worth pausing on what kind of people these are, because it explains a lot of subsequent behavior. Suma holds more than 70 patents across a career that spans Janssen, New River and Intrexon, and she started Krystal at 51 — an age at which most drug developers are managing portfolios rather than founding companies around unproven vectors.1 Her own account of her risk tolerance is unadorned: "I was never afraid of risk-taking. I never felt like I needed a stable job."1 And on what building Krystal required: "You have to be brave and bold to do this."1 Krish, by contrast, is the one who has spent the last three years on earnings calls patiently explaining accrual mechanics for German price negotiations. The division of labor — one founder driving the science and the regulatory strategy, the other running the money and the operations — is the same one that produced Vyvanse, run for a second time.
That continuity has an underappreciated consequence. Most biotech founders are scientists who hire commercial executives late, after approval, when the company's habits are already formed. Krystal has had a commercially trained chairman since inception, which is a plausible part of why the manufacturing and home-administration decisions — both of which are commercial decisions dressed up as technical ones — were made years before there was a product to commercialize.
The relevant analytical point for an investor looking backward is this: Krystal's later capital discipline is not purely a matter of managerial virtue. It is partly a consequence of the founders having been rich and experienced before they started. They could afford to fund the risky early years themselves, which meant they never had to sell equity cheaply, which meant they retained enough ownership to behave like owners. That is a genuine structural advantage — and also a reason to be careful about generalizing the "playbook." Most founders do not get to start with a $2.6 billion exit behind them.
What they did with that freedom was pick a virus nobody wanted.
III. The HSV-1 Platform: Why Krystal Succeeded Where AAV and Lentivirus Failed
To understand the technical choice, you first have to understand the disease, and dystrophic epidermolysis bullosa is one of the cruelest in medicine.
Think of skin as a two-layer laminate. The epidermis sits on top; the dermis sits underneath. Holding them together is a set of molecular rivets called anchoring fibrils, and those fibrils are made of a protein called type VII collagen, encoded by the COL7A1 gene. In DEB, mutations in that gene mean the rivets never form. The top layer of skin is essentially unglued from the layer beneath it. Friction that would be trivial for anyone else — a waistband, a hug, a bedsheet — separates the layers and creates a blister, then an open wound. Children with severe forms are called "butterfly children" because their skin is as fragile as a butterfly's wing. Wounds recur for a lifetime, scarring fuses fingers together, and chronically wounded skin carries a high risk of aggressive squamous cell carcinoma. Before 2023, there was nothing to offer but bandages and pain management.
So why hadn't gene therapy solved it? The answer is a packaging problem, and it is beautifully concrete.
Viral vectors are delivery trucks. You strip out the virus's own genetic cargo and load in the therapeutic gene instead. The dominant truck in gene therapy is adeno-associated virus, or AAV — the vector behind approved products like Zolgensma for spinal muscular atrophy. AAV is small, well-characterized, and relatively well-tolerated. But it has a hard cargo limit of roughly 4.7 kilobases of DNA. The COL7A1 coding sequence is about 8.9 kilobases. It is not that AAV delivers collagen VII poorly; it is that the gene physically does not fit in the truck. Twice over.
The alternative was lentivirus or retrovirus, which can carry larger payloads. But those vectors integrate into the host cell's genome — they splice themselves permanently into the patient's DNA. That confers durability, and it also carries the risk of insertional mutagenesis: the vector lands next to an oncogene, switches it on, and causes cancer. Gene therapy's history includes exactly that outcome in early trials. And because integrating vectors are typically used ex vivo — you harvest a patient's cells, modify them in a laboratory, and put them back — the whole approach requires surgery, cell culture and specialized facilities. We will meet a competitor who took exactly that route.
There is a useful way to hold the whole problem in your head. Imagine you need to deliver a piano to an apartment. AAV is a compact car — reliable, easy to park, welcomed everywhere, and physically incapable of carrying a piano. Lentivirus is a flatbed truck that can carry the piano but insists on bolting it permanently to the floor of the apartment, sometimes through a load-bearing wall. What the field needed was a large vehicle that could carry the piano, drive itself to the right building without a map, and then leave the instrument sitting in the room without drilling into anything.
Krystal's answer was to pick a truck nobody wanted to drive: herpes simplex virus type 1.
The engineering logic is straightforward once you see it. HSV-1 carries a double-stranded DNA genome of roughly 152 kilobases — more than thirty times AAV's capacity. Loading in an 8.9-kilobase gene is not a squeeze; it is a rounding error, with room left over for regulatory elements and, in principle, multiple genes at once. Second, HSV-1 has spent millions of years of evolution optimizing exactly one job: infecting epithelial cells in skin and mucosa. Krystal did not have to engineer tropism; the virus already had it. Third, HSV-1 does not integrate into the host genome. It persists as an episome — a separate circular piece of DNA floating inside the nucleus — which structurally removes the insertional mutagenesis risk.
Krystal's engineering work, which the company calls the STAR-D platform, consists of deleting the genes HSV-1 needs to replicate, rendering it unable to reproduce or cause disease, while leaving the cellular-entry machinery intact. The result is a delivery vehicle that gets into skin cells efficiently and then does nothing except express the gene you loaded.
Now the part that turns a technical choice into a business model.
Because the corrected gene sits as an episome rather than integrating, and because skin cells continually divide and shed, the genetic correction is inherently temporary. Skin turns over; the effect fades; wounds can reopen. In academic terms, that sounds like a weakness — this is not a "cure." In commercial terms, it means the therapy must be redosed, and this is where Krystal's contrarianism paid off in a way that was not obvious in 2016.
The reason systemic AAV therapies are one-and-done is not that a single dose is scientifically ideal. It is that a single intravenous infusion provokes high titers of neutralizing antibodies, and a second dose is therefore useless. The immune system has seen the truck and destroyed it. That biological constraint forced an entire commercial model: a single seven-figure invoice, presented once, with durability that must be argued rather than observed. Payers hated it. Patients whose response waned had no recourse.
Applied topically to skin, Krystal's vector does not appear to provoke a systemic neutralizing response sufficient to block re-administration. Patients can be dosed weekly for years. That converts a one-time, high-stakes, all-or-nothing transaction into something the healthcare system already knows how to pay for: a chronic therapy, billed as it is used, that stops if it stops working.
Two caveats deserve stating plainly, because the enthusiastic version of this story tends to skip them. First, redosability is a double-edged commercial sword. It is a durable revenue stream when patients stay on therapy, and it is a source of quarter-to-quarter volatility when they do not — a dynamic that has already begun to show up in Krystal's reported results and which we will examine in Section VI. Second, the long-term safety record of applying a replication-deficient virus weekly to chronically open wounds for decades simply does not exist yet, because the product has only been on the market since 2023. The observed safety profile is clean. "Clean over three years" and "clean over thirty years" are different claims.
The skin, though, was only the first tissue. The platform's real test would be whether the same logic — accessible epithelial surface, large gene, redosable topical delivery — extends to the eye and the lung. Before Krystal could find out, it had to solve a much more mundane problem: how to actually make the stuff.
IV. The Great Manufacturing Gamble: Why Vertical Integration De-Risked the Launch
In March 2019, Krystal Biotech held an inauguration for a facility called Ancoris. It was a 4,500-square-foot current Good Manufacturing Practice plant near the company's Pittsburgh headquarters, staffed by more than 25 people, built to make clinical and initial commercial supply of what was then called KB103.7
At that moment, Krystal had no approved product, no Phase 3 data, and a market capitalization that would have made most of the industry's manufacturing consultants laugh. It was building a factory for a drug that might never exist.
To appreciate how far outside the playbook that was, consider the standard advice. Early-stage biotech is a cash-preservation exercise. Every dollar spent on bricks and stainless steel is a dollar not spent on clinical trials. Commercial-scale biologics facilities cost tens to hundreds of millions of dollars and take two to three years to build and validate. If the pivotal trial fails, that facility becomes an illiquid, specialized, largely unsellable liability. So you outsource: contract development and manufacturing organizations exist precisely to absorb that risk, and every venture board in the industry pushes toward them.
The Krishnans' counter-argument was rooted in the New River experience and in the physics of viral manufacturing. For a small molecule, the recipe is the product — hand it to a contract manufacturer and you get back what you specified. For a live viral vector, the process is the product. Bioreactor conditions, cell line handling, purification steps and analytical release assays all determine what actually ends up in the vial. A CDMO optimizing across a dozen clients' programs cannot give any one of them the obsessive process control that a novel vector requires. And regulators do not grade on a curve: a Biologics License Application can be rejected purely on chemistry, manufacturing and controls grounds, with the clinical data untouched.
In January 2020, before any Phase 3 readout, Krystal doubled down. It announced a second facility, Astra, a 100,000-square-foot cGMP plant in Findlay Township, Pennsylvania, near the Pittsburgh airport corridor, projected to take twelve to fifteen months to build out and validate, with roughly 75 initial jobs and the potential for more than 200 at full capacity.8 Astra was designed to expand production capacity, serve as a redundant backup site for the lead product, and support the broader pipeline.9 Krish's framing at the time was direct: "Biologics manufacturing is a complex science and is a competitive advantage for Krystal Biotech."8 The specific capital cost of the Astra build was not disclosed in the company's announcement.
Whether that was strategic genius or expensive luck is a fair question — and the answer arrived, unusually, in the form of a natural experiment. A direct competitor took the opposite approach, and we can compare outcomes.
Abeona Therapeutics was developing prademagene zamikeracel, or pz-cel, an autologous cell-based gene therapy for recessive DEB. In April 2024, the FDA issued Abeona a Complete Response Letter. The reason was not efficacy and not safety. Abeona disclosed that the agency required additional information to satisfy chemistry, manufacturing and controls requirements — specifically, validation requirements for certain manufacturing and release testing methods, including items captured as observations during the FDA's pre-license inspection. The company was explicit that the CRL identified no deficiencies in clinical efficacy or safety data, and that no new clinical studies were requested.10 Abeona resubmitted its application in October 2024.11 Approval finally came on April 28, 2025, when the FDA cleared the product as ZEVASKYN.12
Read that timeline carefully. A therapy whose clinical data the FDA did not dispute lost roughly a year to manufacturing paperwork and process validation. In a rare disease with a small, well-identified patient population and a competitor already in the market building physician relationships and payer authorizations, a year is not a rounding error. It is the difference between being the first therapy a family hears about and being the second.
There is a second, quieter payoff from vertical integration, and it shows up in the income statement. Because Krystal designs, manufactures, tests and distributes in-house, it captures the margin a CDMO would otherwise take, and — more importantly — it controls batch quality directly rather than negotiating over it. Cost of goods sold for the full year 2025 was $23.0 million against $389.1 million of net product revenue.13 We will unpack what that ratio does and does not prove in Section VI.
Myth versus reality: what the manufacturing bet actually bought
The consensus retelling of this chapter tends to collapse into a single claim — that building factories early gave Krystal an unassailable cost advantage. That is only partly right, and the imprecision matters.
Myth: the facilities are why the gross margin is extraordinary. Reality: vertical integration removes a CDMO's markup and gives Krystal control over yield, but the dominant driver of a 94% gross margin on a rare disease product is the price, not the plant. Strip the price down to a European negotiated level and the same facility produces a materially different margin. The plant explains reliability far better than it explains profitability.
Myth: owning manufacturing eliminates supply risk. Reality: it relocates the risk. Krystal no longer depends on a third party's priorities, and it now has no external fallback. There is no qualified contract manufacturer standing by. Astra provides internal redundancy for the lead product, which is meaningful, but both plants sit in the same region.9
Myth: the bet was obviously correct at the time. Reality: it was correct conditional on the science working, and the founders knew it. Building a commercial-scale viral vector facility ahead of pivotal data converts scientific risk into balance-sheet risk; it does not remove risk. Had GEM-3 failed, two purpose-built plants in western Pennsylvania would today be an object lesson in capital destruction rather than a case study in foresight.
What the bet genuinely bought was schedule certainty at the regulatory gate — the ability to file a BLA whose manufacturing section had been rehearsed in the company's own building, by the company's own staff, on the company's own timeline. That is worth more in gene therapy than in almost any other category of medicine, because gene therapy is where CMC failures are most common and most expensive. It is a narrower claim than "unassailable moat," and it is better supported.
The Phase 3 data arrived at the end of 2022, and it was not close.
V. Clinical Proof & The Epidermolysis Bullosa Landscape
Picture the practical problem facing a clinical trial designer in dystrophic epidermolysis bullosa around 2020. The entire diagnosed U.S. population is measured in the low thousands. The severity range within that population is enormous — one enrolled patient might have a handful of wounds, another might be almost entirely covered in them. Wounds open and close on their own timetable. And every family you approach has been waiting their whole life for something to work, which makes the ethics of assigning half of them to placebo genuinely uncomfortable.
Krystal's solution to all four problems at once was a single design choice, and it is the sort of thing that makes clinical statisticians sit up.
The conventional way to run a placebo-controlled trial is to randomize patients: half get drug, half get placebo, and you compare groups. In a rare disease with a few dozen enrollable patients and enormous variation in disease severity between individuals, that design is statistically fragile. One unusually severe patient landing in the wrong arm can distort the result.
Krystal randomized wounds instead. Within each patient, investigators identified matched pairs of similar wounds. One wound in each pair received B-VEC; the other received an identical placebo gel. Neither patient nor investigator knew which was which. Every patient served as their own control, eliminating between-patient variability entirely — and, incidentally, ensuring that no participant was denied active treatment across their whole body.
The results, published in the New England Journal of Medicine on December 15, 2022, covered 31 patients over 26 weeks of once-weekly application.14 At six months, complete wound healing occurred in 67% of B-VEC-treated wounds versus 22% of placebo-treated wounds.15 At three months, the figures were 71% versus 20%.15 Serious drug-related adverse events were not observed; the notable side effects were mild — pruritus and local reactions.15
The magnitude matters as much as the statistical significance. A tripling of complete healing rates against an internal control, in wounds that had in many cases been open for years, is not a marginal effect that needs careful statistical framing. It is the kind of result that changes what physicians believe is possible.
It also mattered for a reason that has nothing to do with statistics. Because every participant received active treatment somewhere on their body, the trial sidestepped the ethical objection that dogs placebo-controlled studies in devastating rare diseases — and it generated, inside a single patient, the visual comparison that would later drive physician adoption faster than any published odds ratio. A dermatologist looking at two adjacent wounds on the same child, one closed and one not, does not need a forest plot.
The FDA approved VYJUVEK on May 19, 2023, for the treatment of wounds in patients six months of age and older with DEB carrying mutations in COL7A1.16 It was the first topical gene therapy approved in the United States and the first redosable gene therapy anywhere.16 Crucially, the label permitted administration outside a hospital — in a clinic or at the patient's home. That regulatory detail, easy to overlook, is arguably worth as much commercially as the efficacy data: it removed the infusion suite, the specialized center, and the travel burden from the delivery model entirely.
Two and a half years later, in September 2025, the FDA approved a label expansion that removed the lower age limit — extending eligibility to patients from birth — and allowed patients and caregivers to apply the therapy themselves, with greater flexibility in managing wound dressings.17 Both changes attack friction rather than efficacy, which tells you where management believes the remaining commercial constraint lives.
From skin to eye
DEB does not stop at the skin. The same missing anchoring fibrils affect the mucous membranes and the surface of the eye, producing recurrent corneal abrasions, scarring, and in severe cases functional blindness. In February 2024, the New England Journal of Medicine published a case report describing a patient with cicatrizing conjunctivitis in both eyes caused by DEB who received B-VEC reformulated as an ophthalmic drop, administered under a compassionate-use protocol by a team including Alfonso Sabater at the Bascom Palmer Eye Institute.18 The treatment was associated with improved visual acuity following surgery, and the case was described as the first use of topical gene therapy in the eye.19
A single patient is a single patient, and no serious investor should underwrite a program on a case report. But the scientific signal was meaningful: the same vector, the same gene, a different accessible epithelial surface, and a biological response. Krystal moved that program — KB803 — into a registrational study, and as of mid-2026 enrollment is complete with 16 patients in the IOLITE trial, a randomized, intrapatient, double-blind, decentralized, placebo-controlled crossover design with a readout expected in the fourth quarter of 2026.2 The trial is powered to detect at least a 25% reduction in symptom days.2
The competitive field
Three products now address DEB in the United States, and they are not close substitutes.
FILSUVEZ, from Chiesi Global Rare Diseases, was approved on December 19, 2023 — a topical gel derived from birch bark triterpenes, indicated for wounds in dystrophic and junctional epidermolysis bullosa in patients six months and older.20 In its pivotal trial, 41.3% of patients achieved first complete target wound closure within 45 days versus 28.9% on control gel.20 It is a wound-healing accelerator. It does not deliver COL7A1, does not restore type VII collagen, and does nothing to prevent the next blister from forming. It is worth noting that FILSUVEZ carries a broader label in one respect — it covers junctional EB, which Krystal's product does not.
ZEVASKYN, from Abeona, is a fundamentally different proposition. It is an autologous cell-based therapy: clinicians harvest the patient's own skin cells, ship them to a specialized facility for genetic modification, grow them into sheets of skin graft, and surgically transplant those grafts onto wounds. It is priced at $3.1 million as a one-time treatment.21 The clinical rationale is durability — a successful graft is permanent tissue. The practical constraint is scale. A surgical session addresses a limited number of large chronic wounds; it cannot address the dozens of small, unpredictable blisters that erupt across a patient's body between procedures. And it requires a qualified treatment center, a surgical suite and general anesthesia.
So the competitive landscape is less a head-to-head war than a segmentation. FILSUVEZ competes on cost and breadth of label. ZEVASKYN competes on permanence for specific large wounds and may well be complementary rather than substitutive. VYJUVEK competes on the thing that actually governs a DEB patient's daily life: hundreds of small wounds, everywhere, treated at home, every week.
The investor conclusion here is narrower than the marketing version. Krystal's clinical differentiation is real and well-evidenced. What it does not do is confer permanent protection: a competitor with a redosable topical vector of any construction would attack the same mechanism, and the barrier to that is manufacturing and regulatory experience rather than biology alone.
Which brings us to the part of the story where the science becomes an income statement.
VI. The Vyjuvek Commercial Rollout: Software Gross Margins in a Biotech World
In the summer of 2023, Krystal's commercial team faced a question that has broken better-funded companies. They had an approved therapy for a disease with no alternatives, a patient population small enough to fit in a mid-sized concert hall, and a cost structure that would let them price almost anywhere. What number do you put on a tube of gel that closes wounds a child has had since birth?
Rare disease pricing is a negotiation conducted in public with no good options. Price too low and you cannot fund the next program. Price too high and payers erect prior-authorization barriers that keep the drug from patients while preserving the appearance of coverage. And unlike a one-time infusion, where the payer writes a single cheque and the argument ends, a chronic weekly therapy means arguing with the same insurer about the same patient every year for the rest of that patient's life.
Krystal launched VYJUVEK at a wholesale acquisition cost of $24,250 per vial, with an average patient expected to use roughly 26 vials per year — implying an annual cost of about $630,500.22 Because DEB wound burden varies enormously between patients, and because a patient with extensive wounds could consume far more than the average, the company offered commercial payers an annual price cap of $900,000 per patient.22 That cap is the interesting design choice: it converts an open-ended, actuarially frightening exposure into a bounded liability that an insurer can budget for. The net realized price after government rebates and gross-to-net adjustments is not separately disclosed.
The commercial trajectory since then reads as follows. The 2023 partial launch year produced roughly $51 million in net product revenue. In 2024, revenue reached $290.5 million — a 473% increase — with cost of goods sold of $20.1 million, net income of $89.2 million, and $749.6 million of cash and investments at year end.23 In 2025, revenue reached $389.1 million, up approximately 34%, with net income of $204.8 million and $955.9 million of cash and investments.13
That 2025 net income figure needs a caveat that management supplied and investors should hold onto. On the fourth-quarter call, Chief Accounting Officer Kate Romano noted that the company released a majority of the valuation allowance previously recorded against its deferred tax assets, and separately benefited from the reversal of Section 174 R&D capitalization requirements under new legislation — producing a one-time, non-cash tax benefit that inflated reported EPS for the year.24 Reported 2025 earnings per share of $7.08 basic is therefore not a clean run-rate. Operating performance is better assessed from revenue, gross margin and operating expenses than from the bottom line in that particular year.
The gross margin question
Cost of goods sold was $23.0 million on $389.1 million of 2025 revenue — a 94% gross margin for the year, ticking to 95% in the first quarter of 2026 on $6.3 million of COGS.132 Management has guided to gross margins in the 90% to 95% range for the foreseeable future.24
Why is this possible on a live biologic when traditional biologics manufacturers work with margins twenty to thirty points lower? Two reasons, one structural and one situational.
The structural reason is the production biology. Krystal's replication-deficient HSV-1 is grown in suspension bioreactors at high titer. Once a run is set up, the marginal cost of additional virus is low relative to the fixed cost of the run — the economics of the facility resemble a plant with high fixed costs and very low variable costs, which is exactly why fixed-cost absorption improves as volume grows. Vertical integration removes the CDMO margin layer on top of that.
The situational reason is less flattering and equally important: the denominator. A 94% gross margin on a product priced at hundreds of thousands of dollars per patient per year, sold to a few hundred patients, is substantially a function of price, not manufacturing brilliance. Any therapy with that price point and that unit volume would show a striking margin. The genuinely impressive claim — that Krystal makes a complex viral vector cheaply and reliably at commercial scale — is supported, but it is not the same claim as "software-like economics." If European price negotiations settle materially below U.S. levels, the margin compresses regardless of how efficient the factory is. Management has already flagged the mechanism: fourth-quarter 2025 gross margin dipped to 94% from 96% in the third quarter in part because ex-U.S. volumes carry a higher cost per unit ahead of planned process optimizations for those markets.24
What the demand data actually shows
Krystal's disclosed operating metrics are unusually granular for a rare disease launch, and they tell a more nuanced story than the revenue line.
By the end of 2025, the company had secured over 660 U.S. reimbursement approvals since launch and reached over 500 unique prescribers, adding more than 50 new prescribers in the fourth quarter alone.13 By the first quarter of 2026, those figures had moved to over 695 reimbursement approvals and over 570 unique prescribers, with more than 60 new prescribers added in the quarter.2 On the first-quarter call, Krish put a denominator on it: roughly 1,200 identified U.S. patients, with the company at approximately 60% market share and expecting to reach 720 approvals by the following quarter.3
That is a genuinely strong access record. But look at what happened to U.S. revenue. Of the $116.4 million in first-quarter 2026 global revenue, the United States contributed $87.5 million, with Europe and Japan together contributing $28.9 million.3 U.S. revenue was affected by two things: an unusually high volume of insurance switchovers in the first quarter, and — more structurally — what management calls the "start-stop" dynamic.3
This is the most analytically important disclosure in the recent Krystal story, and it deserves plain English. VYJUVEK works. Wounds close. When a patient's wounds close, that patient may pause therapy and resume when new wounds open. Christine Wilson, who runs U.S. commercial, described patients "achieving durable wound closure, which, in many cases, is allowing them to transition to as-needed utilization of VYJUVEK over time."24 Krish framed it on the first-quarter call as the intended outcome: "We've seen many instances of patients stopping and coming back on drug, which is what we had always wanted this to be — that's the tail on the drug."3
He also said the quiet part: "On a Q-by-Q basis, it's really tough to predict the ups and downs."3
An investor should hold both halves of that. Clinical success producing intermittent utilization is genuinely good news about the product and genuinely complicating news about the revenue model. A chronic weekly therapy with 100% persistence and a chronic weekly therapy used intermittently at 50% of theoretical volume are very different businesses at the same patient count. Nearly three years into the U.S. launch, revenue per patient is no longer a stable multiplier — and management has not disclosed an average annualized revenue per active patient, which is precisely the metric that would resolve the question. Analyst Ritu Baral of TD Cowen pushed on a related risk on the first-quarter call, asking whether insurers were adding friction around drug holidays and reauthorization; Krish's answer was that the company had seen no issues with access or reauthorization to date.3 That is a clean, specific answer to a specific question, and it is also a claim that will be tested as the installed base ages.
Meanwhile the growth engine has shifted geography. The European Commission approved VYJUVEK on April 23, 2025, making it the first corrective gene therapy for DEB in Europe, with flexible home or healthcare-setting administration.25 Japan's Ministry of Health, Labour and Welfare granted marketing authorization on July 24, 2025, with pricing negotiated in October.26 The UK's MHRA approved it on May 15, 2026, adding it to the orphan register with up to twelve years of market exclusivity.27 Germany launched in late August 2025; France operates under an early access program pending price negotiation.24 Management expects a German pricing decision in the second half of 2026 and a French decision in 2027, with Italy and Spain targeted for launch in the second half of 2026.23 Distributor agreements covered more than 20 countries at the end of 2025, with a stated goal of 40-plus during 2026.24
Krish stated the strategic reality bluntly on the fourth-quarter call: "There are more DEB patients outside the United States than within it," and overseas expansion is expected to be the predominant driver of revenue growth in 2026.24 He also warned that revenue "may not track linearly with patient counts this year due to accruals, timing effects and ongoing pricing negotiations," noting the company tends to be conservative when accruing for a future negotiated price.24
Translated: the near-term revenue line is now substantially a function of price negotiations with European governments — a party with more bargaining power than a U.S. commercial insurer, and one whose decisions Krystal cannot control. That is a materially different growth profile from the 2023–2025 U.S. ramp, and the company has been reasonably candid about it.
The obvious question follows: what else is in the pipeline?
VII. The Pipeline and Real Optionality: Cystic Fibrosis, AATD, and Beyond
On January 8, 2026, Krystal published an interim update from the highest dose cohort of CORAL-1, its Phase 1 study of inhaled KB407 in cystic fibrosis. The headline was not a clinical endpoint. It was a set of biopsies.
In all six patients with successful bronchoscopies, the vector had transduced conducting airway cells, with transduction rates ranging from 29.4% to 42.1% regardless of the patient's modulator status. Wild-type CFTR protein delivery and expression was confirmed in the conducting airway cells of patients carrying class I mutations, with durability of expression out to at least 96 hours.28
To see why that mattered, you need the competitive context. Cystic fibrosis is caused by mutations in the CFTR gene, producing thick mucus and chronic lung infection. Vertex Pharmaceuticals transformed the disease with small-molecule modulators — Trikafta and its predecessors — which work by helping a defective CFTR protein fold and function correctly. But modulators require a protein to fix. Patients with class I nonsense mutations produce essentially no CFTR protein at all; there is nothing for a modulator to correct. Those patients, along with those who cannot tolerate modulators, have been left behind by the single greatest therapeutic advance in their disease.
KB407 is mutation-agnostic. It delivers full-length wild-type CFTR directly to lung epithelium via a nebulizer — the same platform logic as the skin, applied to a different accessible epithelial surface. Suma Krishnan's framing on the fourth-quarter call was that the results "give us high conviction in the potential of KB407 to fill the treatment gap that exists today for modulator-ineligible patients," and that they showcase "the versatility of HSV-1-based gene delivery to epithelial tissues beyond the skin."24
The appropriate investor posture is interested skepticism. Molecular confirmation of delivery and expression in human lungs is a real and non-trivial de-risking event — the lung is a hostile environment with thick mucus, alveolar macrophages and mechanical clearance that skin does not have, and many inhaled gene therapy attempts have failed at precisely this step. But protein expression in a biopsy is not the same as improved lung function in a patient. No clinical efficacy has been demonstrated. The FDA's own feedback, as Suma described it on the first-quarter 2026 call, was that the agency was persuaded by the expression data but that repeat-dose safety had not been established.3 Krystal is running an open-label, single-arm, 24-week repeat-dose safety study in five modulator-ineligible or intolerant CF patients, with the Cystic Fibrosis Foundation's backing, and is negotiating an innovative registrational design that may use prospectively collected CFF natural history data to supplement placebo-controlled data.3 Alignment with the FDA is expected in the second half of 2026, with a registrational study targeted to start in the first half of 2027.3
Also in 2026, the FDA granted platform technology designation to KB407 and to KB111, adding to the designation previously granted for KB801.2 Krish argued on the call that these designations "bring a compounding advantage" — each program's development data strengthens the collective regulatory dataset, reducing cost and time for the next candidate.3 That is a plausible mechanism and a genuinely differentiated regulatory position, but it is a claim about future efficiency that has not yet been demonstrated across multiple approvals.
The rest of the pipeline, sized to what has actually been shown:
KB801 (neurotrophic keratitis) is the second registrational program and arguably the nearest-term real option beyond DEB. EMERALD-1 was upsized to approximately 60 patients with a once-daily dosing regimen and flexible administration by healthcare professional, caregiver or patient, targeting roughly 30 activated sites and a data readout before the end of 2026.242 Neurotrophic keratitis is a substantially larger indication than ocular DEB.
KB408 (alpha-1 antitrypsin deficiency) delivers the SERPINA1 gene to lung tissue via inhalation, addressing genetic emphysema. The SERPENTINE-1 repeat-dosing study includes bronchoscopies at baseline and after four doses, measuring lung AAT and bound neutrophil elastase levels — data points management has said will support accelerated approval discussions with the FDA, with an update expected before year-end 2026.24
KB707 (oncology) is an HSV-1 vector engineered to express IL-2 and IL-12 in the tumor microenvironment, prioritized in an inhaled formulation for non-small cell lung cancer through the KYANITE-1 study. Data presented at ASCO in 2025 showed an overall response rate of 27% in eleven efficacy-evaluable NSCLC patients at the abstract cutoff, rising to 36% with extended follow-up.29 The FDA granted RMAT designation in February 2026, and interim efficacy data plus potential registrational plans are expected later in 2026.24 Small-n response rates in heavily pretreated patients are hypothesis-generating, not conclusive; oncology is also the one arena where Krystal would face genuinely well-capitalized competition.
KB111 (Hailey-Hailey disease) received Fast Track designation in January 2026. The program is unusual in that Krystal had to build the measuring instrument before it could run the trial — developing and validating a disease-specific severity scale, which had the side effect of assembling a genetically tested patient repository that management expects to feed enrollment.243 A small open-label safety study was set to begin in 2026 with a registrational start targeted for 2027.3
Jeune Aesthetics (KB301, KB304) remains a wholly owned subsidiary pursuing collagen delivery for dynamic wrinkles and décolleté aging, with a KB304 Phase 2 initiation targeted for 2027.2 This is the most speculative item on the list and is sized accordingly — it consumes little cash and should carry little weight in any valuation.
Platform or product?
It is worth naming the question the pipeline is really asking, because it determines how the whole company should be valued.
A product company earns a multiple on the cash flows of the thing it sells. A platform company earns a multiple on the expectation that the underlying technology produces several more things to sell, each cheaper and faster than the last because the hard problems — vector design, manufacturing, regulatory precedent, delivery format — are already solved.
Krystal is priced closer to the second. The evidence for the platform interpretation is genuine: the same vector backbone now carries four different genes into three different tissues; FDA platform technology designations have been granted across multiple programs; the manufacturing lines are shared; and the company has repeatedly won approval for home administration, which is the delivery format that makes all of it commercially viable.23
The evidence against is equally simple: outside DEB, not one program has demonstrated clinical benefit in a controlled trial. Delivery is not efficacy. Expression is not outcome. Every pipeline program to date has cleared the biology gate and none has yet cleared the medicine gate. Two attempts to do so land before the end of 2026.
The pipeline verdict, then: Krystal has one approved product generating all of its revenue, two registrational readouts due before the end of 2026 that would materially change the story, and a set of Phase 1 programs where biological delivery has been demonstrated but clinical benefit has not. Management's own framing on the fourth-quarter call — that the company believes it has "the capabilities to self-launch these four indications" if approved — is a statement of intent, not of achievement.24 The single most consequential fact about the next twelve months is that two of those readouts arrive within them.
VIII. Hamilton Helmer's 7 Powers & Porter's 5 Forces Analysis
Frameworks are only useful if they are applied adversarially, so let us grade honestly rather than generously. The temptation with a company like Krystal is to run through Helmer's list and award full marks on every line, because the business is profitable, the technology is differentiated and the competition is visibly struggling. That exercise produces a flattering picture and no information. The useful version asks a harder question about each power: if a well-capitalized competitor decided tomorrow to attack this position, which of these advantages would actually slow them down, and for how long?
Helmer's 7 Powers
Counter-positioning — strongest claim. This is the power Krystal actually has, and it is textbook Helmer. The incumbent gene therapy field committed itself to one-time systemic cures. Krystal adopted a chronic, redosable, topically applied model that the field's purists could dismiss as "not really gene therapy." Incumbents could not easily copy it, not because they lacked the ability, but because doing so would have contradicted the entire narrative on which they had raised capital and built their vector platforms. That gave Krystal years of unmolested runway. The caveat is that counter-positioning decays once the counter-position is proven — and VYJUVEK's commercial success has now proven it to everyone.
Proprietary technology — strong but qualified. The STAR-D platform's cargo capacity advantage over AAV is a matter of physics, not of skill, and physics does not expire. But intellectual property is where this power lives, and Krystal's IP position was directly challenged. In May 2020, PeriphaGen filed suit in the Western District of Pennsylvania alleging breach of contract and misappropriation of trade secrets relating to Krystal's product candidates and the STAR-D platform, and separately sought to add two of its employees as inventors on several Krystal U.S. patents covering the treatment of skin disorders using replication-defective HSV-1 vectors.4 Krystal settled: a binding term sheet in March 2022, a final agreement in April 2022, $25 million upfront plus four contingent milestone payments of $12.5 million each — totaling $75 million, which the company has now fully paid.304 The settlement included acquisition of certain PeriphaGen assets and a license for dermatological applications.30 That resolves the overhang, and it also tells you the foundational IP was contestable enough to be worth $75 million to make go away.
Cornered resource — moderate. The team's accumulated know-how in purifying and manufacturing replication-defective HSV-1 at commercial scale is real and hard to replicate quickly. But "the founders are very good" is the weakest form of this power, because it walks out the door. Suma Krishnan is central to R&D and both founders are in their sixties; succession is an unaddressed question in public disclosure.
Scale economies — moderate, and improving. The Pittsburgh facilities are built and their fixed costs absorbed. Each additional program routed through the same lines improves incremental margin, while a would-be competitor must either build from scratch or accept CDMO economics and CDMO process risk. This power strengthens if — and only if — the pipeline delivers additional approved products.
Switching costs — moderate, and weaker than the bull case assumes. A patient established on VYJUVEK has an insurance authorization, a supply chain, a nursing or self-administration routine, and healed wounds. Switching to a surgical graft or a non-disease-modifying gel is unattractive. But the start-stop dynamic reveals the limit: patients already stop and restart routinely, which means the behavioral lock-in is with the disease management pattern, not with the specific product. A future redosable topical competitor would face a lower switching barrier than the framework suggests.
Branding and network economies — essentially absent. Rare disease physician awareness is real but is not brand power in Helmer's sense, and there is no network effect. The framework should not be stretched to award powers that do not exist.
Porter's Five Forces
Threat of new entrants — low, but not "very low." The barriers are the capital and regulatory expertise required to manufacture and validate replication-defective viral vectors at scale — which the Abeona timeline demonstrates are real. But Krystal has now published the roadmap: HSV-1 works, topical redosing works, home administration is approvable. A well-capitalized entrant with patience faces a known path rather than an unknown one.
Bargaining power of buyers — moderate in the U.S., high in Europe. In the U.S., the absence of disease-modifying alternatives and the substantial cost of supportive wound care give Krystal a defensible value argument, evidenced by the access record. In Europe and Japan, the buyer is a national government with a rare disease budget, and the negotiation is asymmetric. Krish acknowledged as much: beyond the clinical merits, "there are also political factors that come into negotiations in these countries."3 Since ex-U.S. markets are now the primary growth driver, this force is becoming more important, not less.
Bargaining power of suppliers — low. Vertical integration is precisely designed to eliminate this, and it does. The residual exposure is raw materials and single-site concentration, addressed in Section X.
Threat of substitutes — low for the core use case. Neither a wound-healing accelerator nor a surgical graft addresses hundreds of recurring small lesions at home. But "low" is not "none": FILSUVEZ is dramatically cheaper and holds a broader label covering junctional EB, and cost-conscious payers in constrained systems may use it as a first-line step.
Rivalry — currently low, structurally fragile. Three products, three different mechanisms, one small patient pool. Rivalry stays low as long as the segmentation holds. It would intensify immediately if any competitor demonstrated a redosable topical alternative.
Net assessment: Krystal's competitive position is genuinely strong today and rests on a combination of counter-positioning, manufacturing know-how and first-mover access relationships. What it does not have is a self-reinforcing moat that widens with time. The most durable elements — the physics of vector capacity and the accumulated manufacturing expertise — are real; the most celebrated element, being first with a redosable topical gene therapy, is precisely the kind of advantage that erodes once someone else decides to build one.
IX. Playbook: Key Strategic and Investing Lessons
Four transferable lessons come out of this story, and each carries a limit worth stating.
1. Judge technology by its physical properties, not its narrative. Herpes simplex virus type 1 arrives with unhelpful associations. Investors and executives spent years steering around it. Krystal ignored the connotation and read the specification sheet: a 152-kilobase double-stranded DNA genome, native epithelial tropism, non-integrating persistence. Those properties made it the only sensible vehicle for an 8.9-kilobase gene delivered to skin. The limit: stigma is not always irrational, and reading a spec sheet correctly requires deep domain expertise. This lesson is easy to state and hard to apply — for every mispriced "ugly" technology there are several that are unloved for good reason.
2. Controlling the means of production is a commercial decision, not a capital expenditure. The industry treats manufacturing as a cost center to be outsourced and the clinic as the value driver. Krystal inverted that, building Ancoris before pivotal data and breaking ground on Astra before knowing whether the drug worked. The payoff was not primarily margin; it was the absence of a CMC-driven Complete Response Letter of the kind that cost a direct competitor roughly a year. The limit: this only worked because the science worked. Building a factory ahead of Phase 3 is a leveraged bet on your own conviction, and it converts scientific risk into balance sheet risk. It is advice for founders with unusual confidence and unusual resources, not general guidance.
3. Design the business model around how the payer actually pays. The gene therapy sector fell in love with the one-and-done cure because it is scientifically elegant. Elegant is not the same as reimbursable. A single seven-figure invoice with unproven durability is the hardest possible sale to an insurer, and it leaves no recourse if the effect wanes. A chronic weekly therapy billed as used slots into infrastructure the healthcare system already operates. The limit — and this is the honest twist: the same model that eased reimbursement produced the start-stop revenue volatility now visible in Krystal's quarterly results. Redosability is not free; it trades one form of commercial risk for another.
4. A clean cap table compounds like a financial asset. No venture rounds. No structured debt. Founder self-funding at the outset, a small IPO, and equity raises concentrated in the pre-commercial years. The result is a company whose founders retain roughly 12% and whose management can credibly tell investors it has not tapped the market in years.13 The limit: this was made possible by a prior $2.6 billion exit. Founders without that history face a genuine tradeoff between dilution and speed, and pretending otherwise is survivorship bias.
The meta-lesson is about sequencing. Krystal did the expensive, unglamorous, de-risking work — manufacturing, process control, regulatory groundwork on home administration — before it had the luxury of doing so. Companies that defer that work until after positive data discover that the queue for CDMO capacity and FDA inspection slots does not care about their urgency.
Which sets up the harder question: does the case still hold from here, at a valuation that already reflects most of what has gone right?
X. Skeptical Stress Test: The Bull vs. Bear Case and Risk Radar
By late July 2026, Krystal shares traded around the mid-$350s, giving the company a market capitalization above $10 billion, against a 52-week range running roughly from the low $130s to the low $380s.31 That is a remarkably wide band for a company with a stable, approved, profitable product — the low end and the high end differ by nearly a factor of three within twelve months. It tells you the market has been repricing this business aggressively, and that what it is repricing is not the drug but the story about what comes after the drug.
So the useful exercise is not to ask whether Krystal is a good company. It plainly is. The useful exercise is to ask what a sceptical investor would attack, what management has done when challenged, and which specific mechanisms could break the case.
Management credibility
Assessing management by behavior rather than rhetoric, the record is largely favorable with specific things to watch.
On the positive side: the founders' incentives are aligned through a combined stake of roughly 12%, not through option grants alone.1 The execution record on the core asset is strong — pivotal trial delivered, BLA approved without a CMC setback, manufacturing built ahead of need, label subsequently expanded twice in ways that reduced patient friction. Narrative consistency across calls is high: the same operating principle — "invest behind measurable execution milestones, compound value without relying on dilution" — appears in substantially the same form quarter over quarter.24
More tellingly, management has been willing to volunteer bad or complicating news before analysts extract it. The start-stop utilization dynamic was disclosed by the company rather than discovered by the market. The gross margin dip in the fourth quarter of 2025 was explained specifically — ex-U.S. units carrying higher cost per unit ahead of process optimization — rather than waved away.24 The one-time tax benefits inflating 2025 EPS were flagged by the chief accounting officer on the call rather than buried in a footnote.24 Krish's warning that revenue "may not track linearly with patient counts" ahead of European pricing outcomes is the kind of expectation-setting that costs credibility in the short run and earns it over time.24
Where a skeptic would push: the company declines to disclose the metrics that would let outsiders independently assess the start-stop dynamic. Patient counts outside the U.S. are described by management as approximations derived from vials shipped, and Krish explicitly declined to break them down by country, arguing further segmentation "just makes it that much more irrelevant."24 That is a defensible position on data quality and also a convenient one. Revenue per active patient — the single number that would clarify whether intermittent utilization is stabilizing or deteriorating — has not been provided.
The activist lens on capital allocation
This is the sharpest available critique, and it has been raised repeatedly on calls by analysts at William Blair and Clear Street.243
The facts: Krystal holds over $1 billion in cash and investments, generates substantial operating cash flow, carries no meaningful debt, and has no share repurchase program.2 Guided 2026 non-GAAP R&D and SG&A of $175–195 million represents an increase over 2025's actual $150.3 million, but the company is not remotely spending its cash generation.24
Management's answer has been consistent across at least two consecutive calls, which is itself informative. Krish has stated plainly that the company does not presently intend to use cash for in-licensing or acquiring third-party technology or companies.24 On timing a buyback, his framing has been that with several registrational programs approaching launch and three larger indications — oncology, alpha-1, aesthetics — whose development and commercialization paths remain undefined, it is "difficult to be very definitive on a timeline," and that once there is visibility into the next drug's launch, "that would be a great timing to think about share buyback."243
An activist would find that answer unsatisfying in a specific way. It is a reason to wait, not a policy. There is no stated hurdle rate, no framework for what would trigger a return of capital, and no articulated view of what the optimal cash balance is for a company with this cost structure. The counter-argument — that a company about to self-launch multiple indications simultaneously needs a fortress balance sheet, and that biotech companies which return capital and then need it back destroy value through dilution — is legitimate. But "we will decide later" is a governance posture, not a capital allocation strategy, and the cash pile grows every quarter. The commitment to avoid M&A is, notably, the more valuable half of the answer: the graveyard of profitable rare disease companies that diversified into overpriced oncology assets is well populated, and management has repeatedly and specifically declined to walk into it.
The bull case, stated fairly
Krystal has demonstrated something the gene therapy field had not: that a genetic medicine can be manufactured at high margin, sold into existing reimbursement infrastructure, and generate real profits without dilution. The U.S. launch has achieved roughly 60% share of identified patients with access approvals still accelerating.3 International markets contain more DEB patients than the U.S. does and are in the earliest innings, with four major European markets and Japan either launched or launching.24 Two registrational readouts arrive before the end of 2026 in indications — ocular DEB and neurotrophic keratitis — where the company already knows the patients, the supply chain and the reimbursement pathway. The KB407 biopsy data established that HSV-1 delivery works in human lungs, opening a genuinely large addressable population of modulator-ineligible CF patients. And platform technology designations across three programs suggest a regulatory efficiency advantage that compounds.
The bear case, stated fairly
Substantially all revenue comes from one product in one indication in a patient pool of roughly 1,200 identified U.S. patients, where the company already holds about 60% share.3 U.S. growth from here depends less on new patients than on utilization intensity — and utilization intensity is falling as patients heal and shift to as-needed dosing, a dynamic management concedes is hard to predict quarter to quarter.3 Growth has therefore shifted to markets where price is set by government negotiation, with German and French outcomes still unresolved and revenue being conservatively accrued in the interim.24 Gross margin, the most celebrated metric, is partly a function of U.S. price levels that may not survive international benchmarking. The pipeline has produced excellent biology and no clinical efficacy outside DEB. And the valuation embeds a platform, not a single drug.
Risk radar: the mechanisms that actually matter
Pipeline translation risk. Skin is uniquely forgiving: accessible, immunologically tolerant to topical application, and self-renewing. The lung has mucus, macrophages and mucociliary clearance. The eye has tear turnover and a tightly regulated immune environment. Krystal has demonstrated delivery in the lung and a compelling single-patient result in the eye; neither is clinical efficacy. If KB801 and KB803 miss in the fourth quarter of 2026, the investment case reverts to a single-product rare disease business — a fine business, valued very differently.
Reimbursement and utilization risk. Two distinct mechanisms. First, European and Japanese price points may set international reference benchmarks that eventually pressure U.S. pricing. Second, as more patients settle into intermittent use, payers may impose documentation requirements around reauthorization after treatment pauses. Management reports no such friction to date.3 This is a risk to monitor, not one currently manifesting.
Manufacturing concentration. The vertical integration that de-risked the launch also concentrates risk geographically. Both facilities are in western Pennsylvania. Astra was explicitly designed as a redundant site for the lead product, which mitigates single-facility failure.9 But there is no qualified CDMO backup, and a regional event — contamination, natural disaster, a regulatory action affecting the site — would have no external fallback. This is the clearest example of a strength and a risk being the same decision.
Long-term safety. Weekly application of a replication-deficient virus to chronically open wounds over decades has no precedent. The observed profile through three years of commercial use is clean, and the episomal, non-integrating design removes the mechanistic basis for the field's most feared complication. But an absence of long-term data is not the same as evidence of long-term safety, and a safety signal emerging in year eight would be far more damaging to a chronic therapy than to a one-time treatment.
Key personnel. The scientific vision and the operational discipline are concentrated in two people who are also the largest shareholders. Public disclosure on succession planning is limited.
Accounting and disclosure. No going-concern issues, no restatements, no auditor signals of concern. The valuation allowance release and Section 174 reversal that boosted 2025 EPS were disclosed and explained on the call.24 The PeriphaGen settlement obligations have been fully paid.4 Investors should nonetheless normalize 2025 earnings for the one-time tax items before drawing multi-year trend conclusions.
XI. Epilogue & Episode Outro
Step back and the shape of the story is clear. Krystal Biotech proved that a genetic medicine can be an ordinary — even excellent — commercial business: manufactured in-house at high margin, sold into infrastructure payers already understand, generating profit rather than consuming it, funded without perpetual dilution. That is a meaningful contribution to a field that spent a decade proving the opposite. Ten years after two people started it with their own money in a city nobody associated with biotech, the company reported eleven consecutive quarters of positive EPS and a billion dollars in the bank.32
What remains unproven is the sentence Krystal's valuation depends on. Not "the drug works" — the drug demonstrably works. The unproven sentence is that the platform generalizes: that the same virus, the same episomal logic, the same redosable topical delivery works in the lung and the eye with the reliability it works on skin, and that Krystal can repeat the manufacturing-and-launch trick three or four more times without the fortress balance sheet becoming a substitute for discipline.
The next twelve months provide unusually clean evidence on that question. Two registrational readouts land before the end of 2026. Germany's price is decided. Italy and Spain launch or they don't. CF repeat-dose safety data arrives. Rarely does a company face so many falsifiable tests in so short a window.
Three things are worth tracking above everything else.
First, revenue per active patient rather than headline revenue. The U.S. patient pool is largely identified and largely penetrated. What determines the trajectory of the core business now is not how many patients start therapy but how much therapy each patient consumes as wounds heal and utilization becomes intermittent. Total revenue conflates new patients, price and intensity; separating them is the whole game.
Second, the ex-U.S. price outcomes — Germany first, then France and Italy. These set the international reference benchmarks for every subsequent market, they determine whether the ex-U.S. business carries the margin structure of the U.S. business, and they are the primary growth driver management has identified for 2026.
Third, the two registrational ophthalmology readouts. KB803 in ocular DEB and KB801 in neurotrophic keratitis are the first real tests of whether the platform thesis is a thesis or a fact. A clean win in either would transform Krystal from a one-drug company with promising biology into a genuinely multi-indication business — and would say more about the next decade than any quarter of revenue.
There is a version of the next few years in which Krystal becomes what its valuation implies: a multi-indication genetic medicines company with four or five approved redosable products flowing through two Pittsburgh plants, funding its own development from operating cash, never returning to the equity market. There is another version in which VYJUVEK settles into a durable but slow-growing rare disease annuity of a few hundred million dollars, the ophthalmology readouts disappoint, and the billion dollars of cash starts looking less like a fortress and more like a problem management has deferred solving. Both versions are consistent with everything known today. That is precisely why the readouts matter more than the quarters.
The scoreboard on the manufacturing bet is not final either. It looks, from here, like one of the better capital allocation decisions in recent biotech history. It is also a decision that depended on the science working, made by founders who could afford to be wrong, and it deserves to be studied as much for its preconditions as for its outcome.
References
-
How A 60-Year-Old Drug Developer Built $4.4 Billion Krystal Biotech To Treat 'Butterfly Skin Disease' — Forbes, 2025-07-31 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
Krystal Biotech Announces First Quarter 2026 Financial and Operating Results — GlobeNewswire, 2026-05-04 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
Earnings call transcript: Krystal Biotech Q1 2026 beats earnings expectations — Investing.com, 2026-05-04 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
Krystal Biotech, Inc. Form 10-K for the Fiscal Year Ended December 31, 2024 — SEC EDGAR ↩↩↩↩
-
Shire buys New River Pharmaceuticals for $2.6 billion — PharmaTimes, 2007 ↩
-
Krystal Biotech Announces Closing of Initial Public Offering and Full Exercise of Underwriters' Option to Purchase Additional Shares — GlobeNewswire, 2017-09-22 ↩
-
Krystal Biotech Continues Vertical Integration with Official Inauguration of Ancoris Gene Therapy Manufacturing Facility at its Pittsburgh Headquarters — Krystal Biotech, 2019 ↩
-
Krystal Biotech Builds Second Gene Therapy Facility in Findlay Township, Pennsylvania — Area Development, 2020-01-28 ↩↩
-
For DEB, Astra Facility Opens to Support B-VEC Gene Therapy Production — Epidermolysis Bullosa News ↩↩↩
-
Abeona Therapeutics Provides Regulatory Update on Pz-cel — GlobeNewswire, 2024-04-22 ↩
-
Abeona Therapeutics Completes Pz-cel Biologics License Application Resubmission to U.S. Food and Drug Administration — GlobeNewswire, 2024-10-29 ↩
-
U.S. FDA Approves ZEVASKYN (prademagene zamikeracel), the First and Only Cell-Based Gene Therapy for Patients with Recessive Dystrophic Epidermolysis Bullosa — Abeona Therapeutics, 2025-04-28 ↩
-
Krystal Biotech Announces Fourth Quarter and Full Year 2025 Financial and Operating Results — BioSpace, 2026-02-17 ↩↩↩↩
-
Trial of Beremagene Geperpavec (B-VEC) for Dystrophic Epidermolysis Bullosa — New England Journal of Medicine, 2022-12-15 ↩
-
New England Journal of Medicine Publishes Phase 3 Data on B-VEC in Patients with Dystrophic Epidermolysis Bullosa — GlobeNewswire, 2022-12-14 ↩↩↩
-
FDA Approves First Gene Therapy for Dystrophic Epidermolysis Bullosa (DEB) — American Society of Gene & Cell Therapy, 2023-05 ↩↩
-
Krystal Biotech Announces FDA Approval of Updated VYJUVEK Label — GlobeNewswire, 2025-09-15 ↩
-
Ocular Gene Therapy in a Patient with Dystrophic Epidermolysis Bullosa — New England Journal of Medicine, 2024-02-08 ↩
-
Krystal Biotech Announces Publication in the New England Journal of Medicine on the Application of B-VEC to Treat Ocular Complications in Patient with Dystrophic Epidermolysis Bullosa — GlobeNewswire, 2024-02-08 ↩
-
Chiesi Global Rare Diseases Receives FDA Approval for FILSUVEZ (birch triterpenes) topical gel for the Treatment of Epidermolysis Bullosa — GlobeNewswire, 2023-12-19 ↩↩
-
FDA approves Abeona's $3.1m cell therapy for rare skin disease — Pharmaceutical Technology, 2025-04 ↩
-
For A Change, There's Optimism About A Gene Therapy's Commercialization: Vyjuvek For Wound Care — Forbes, 2023-11-06 ↩↩
-
Krystal Biotech Announces Fourth Quarter and Full Year 2024 Financial and Operating Results — GlobeNewswire, 2025-02-19 ↩
-
Earnings call transcript: Krystal Biotech Q4 2025 surpasses expectations with strong revenue growth — Investing.com, 2026-02-17 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
Krystal Biotech Announces European Commission Approval of VYJUVEK for the Treatment of Dystrophic Epidermolysis Bullosa — Krystal Biotech, 2025-04-23 ↩
-
Krystal Biotech Announces Approval of VYJUVEK by Japan's Ministry of Health, Labour and Welfare for the Treatment of Dystrophic Epidermolysis Bullosa — GlobeNewswire, 2025-07-25 ↩
-
Krystal Biotech Announces United Kingdom MHRA Approval of VYJUVEK for the Treatment of Dystrophic Epidermolysis Bullosa — GlobeNewswire, 2026-05-18 ↩
-
Krystal Biotech Announces Positive Interim Clinical Update from KB407 Phase 1 CORAL-1 Study with Confirmation of Wild-Type CFTR Delivery to the Lungs of Patients with Cystic Fibrosis — GlobeNewswire, 2026-01-08 ↩
-
Development Program for KB707 Will Prioritize Inhaled Formulation for NSCLC — OncLive ↩
-
Krystal Biotech Announces Settlement with PeriphaGen, Inc. — Krystal Biotech, 2022 ↩↩
-
Krystal Biotech (KRYS) Stock Price & Overview — StockAnalysis.com ↩
 LinkedIn
 WhatsApp
 Reddit
 Hacker News
 Email
 Kindle
 RSS Feed
 Spotify
 Apple Podcasts
 Amazon Music
 Audible
 YouTube