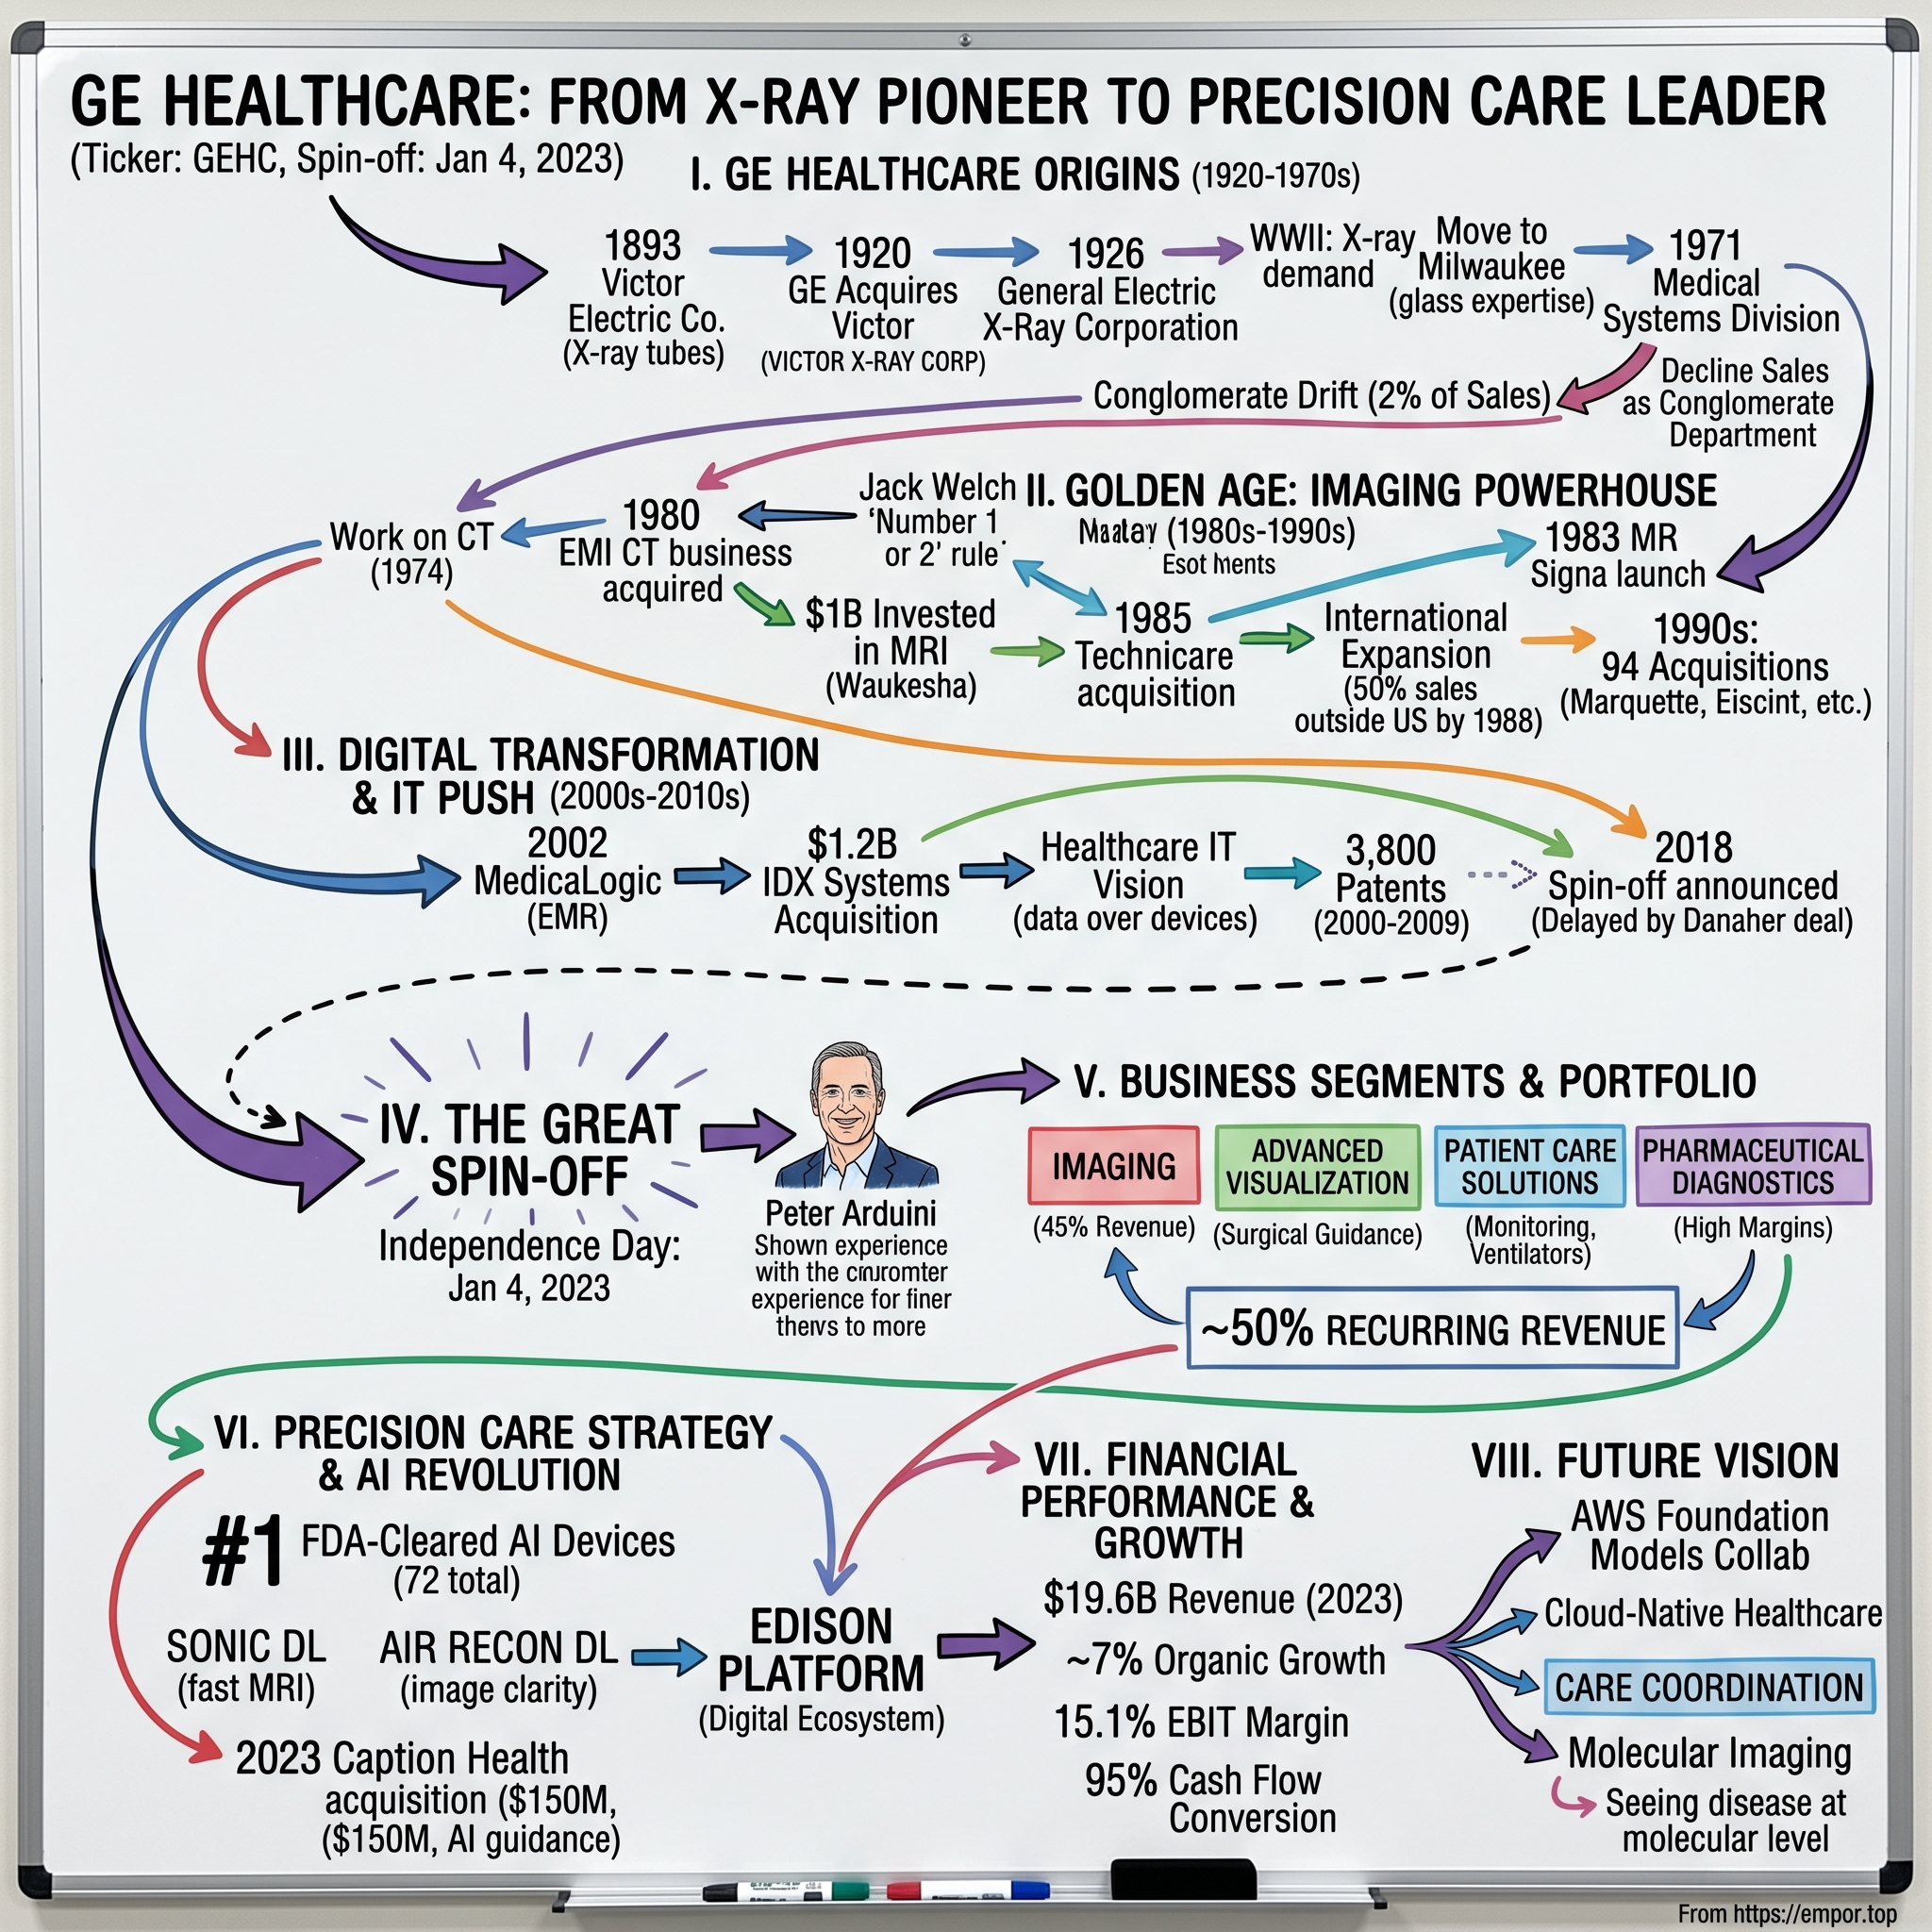
GE HealthCare Technologies: The Industrial Giant's Pure-Play Rebirth
I. Introduction & Episode Roadmap
The Morning the Monogram Walked Out the Door
On the morning of January 4, 2023, an enterprise with more than a century of operating history marked its first official day as an independent company. GE HealthCare Technologies began regular-way trading on the Nasdaq under the ticker GEHC. The previous day, General Electric had distributed one GEHC share for every three GE shares held by investors, retaining a 19.9% stake for itself.12 Larry Culp, who had spent four years stabilizing GE's overextended balance sheet, framed the spin-off as the first step in a three-way corporate breakup. It was also the most straightforward to articulate: aviation would remain within GE Aerospace, the energy businesses would spin off as GE Vernova, and healthcare would lead the sequence.3
The business that departed Thomas Edison's conglomerate that week bore little resemblance to a standard corporate spin-off. Far from an orphaned division, it was an established industrial heavyweight generating nearly $20 billion in annual revenue.4 Today, the company employs approximately 54,000 people and serves healthcare institutions across more than 160 countries.5 Management reports an active installed base exceeding five million imaging, ultrasound, and patient monitoring systems, which collectively interact with more than one billion patients each year.6 Across the developed world, equipment in almost any hospital CT suite, ultrasound room, or intensive care bay is likely to bear the familiar GE script. Yet even that emblem is now leased back from the former parent company under a trademark licensing agreement structured in renewable ten-year periods.2
The Core Question
The central strategic question facing the business is whether a century-old, capital-intensive medical hardware manufacturer can escape the traditional "conglomerate tax." Can it successfully pivot from capital-equipment manufacturing—traditionally known as selling "iron"—into high-margin software and what leadership terms "precision care"? And can it defend its share in a mature global imaging oligopoly against disciplined European competitors on one side and an aggressive, state-backed Chinese national champion on the other?
Nearly four years into independence, the operational reality has proved considerably more demanding than the initial spin-off narrative suggested. GEHC has navigated significant milestones: it established standalone investment-grade financing, managed through post-pandemic supply chain bottlenecks, secured the first FDA clearance for its proprietary photon-counting CT architecture, and reported a record order intake in mid-2026.78 At the same time, the company has fallen short of its initial margin expansion targets, absorbed a prolonged slump in Chinese capital spending that executives originally dismissed as temporary, and recorded three consecutive years of declining free cash flow. In July 2026, management placed its Patient Care Solutions segment under strategic review—an announcement that coincided with the resignation of its chief financial officer.9810
The Road Ahead
This analysis proceeds in nine parts. It begins with a nineteenth-century Chicago X-ray shop and traces the Jack Welch era that built GE Medical Systems into a global imaging powerhouse. It examines the lucrative service contracts that became the division's core cash engine, the costly missteps in healthcare IT, and the distressed 2019 sale of its biopharma business to Danaher. Next, it details the mechanics of the 2023 separation before examining each operating segment: advanced imaging, the struggling patient monitoring unit, and the high-margin contrast media and radiopharmaceuticals franchise. Finally, it evaluates the company's artificial intelligence initiatives, benchmarks its competitive moat against global rivals, stress-tests its exposure to China, and examines the three operational metrics that will determine whether GE HealthCare emerges as a compounding compounder or remains a cyclical medical manufacturer.
Understanding GEHC's modern competitive and reimbursement challenges requires returning to where the industrial giant first learned to see beneath the skin.
 Subscribe on LinkedIn
II. The Deep Roots: From Coolidge Tubes to Jack Welch’s "GEMS" (1893–1980s)
A Chicago Workshop and a Strange New Light
In 1893, two Chicago craftsmen, Charles F. Samms and Julius B. Wantz, founded the Victor Electric Company to manufacture specialized electrical apparatus for physicians and dentists.11 Two years later, in a laboratory in Würzburg, Wilhelm Röntgen discovered X-rays after observing an unexpected fluorescence from a cathode-ray tube. Within months, experimenters worldwide were assembling crude radiographic apparatus, but Victor Electric was among the few commercial enterprises that committed to developing clinical equipment systematically.
X-ray technology in that era remained hazardous and erratic. Early tubes were gas-filled glass bulbs whose output fluctuated wildly from day to day, forcing operators to gauge exposure almost entirely by intuition. The decisive breakthrough came from General Electric’s Research Laboratory in Schenectady, New York. In 1913, physicist William Coolidge developed a high-vacuum tube featuring a heated tungsten filament, creating an X-ray beam that was stable, controllable, and reproducible. The Coolidge tube, patented in 1916, established the operating architecture for medical X-ray generation for decades to come.12
The shift was analogous to moving from an open campfire to a gas burner: where early practitioners effectively tended an unpredictable flame, Coolidge gave operators a calibrated dial. For General Electric, the invention established a foundational engineering competence that became central to its corporate identity: the ability to govern the physics of radiation with industrial precision.
GE Absorbs Victor
The commercial enterprise and the research laboratory converged on October 1, 1920, when Victor combined its operations with GE’s X-ray business. By 1926, GE had fully acquired the company, reorganizing it as the General Electric X-Ray Corporation. By 1930, the Victor brand had been largely phased out.11 The division transferred its primary manufacturing operations to Milwaukee in 1947.11 That southeastern Wisconsin hub, later expanded into neighboring Waukesha, remains the industrial epicenter of GE HealthCare’s global imaging footprint today.
For decades following the Second World War, medical equipment remained a secondary division within an industrial conglomerate whose capital allocation was dominated by power generation turbines, locomotives, jet engines, and consumer appliances. While the medical unit maintained high engineering standards, its capital requirements and commercial priorities were consistently overshadowed by GE’s heavier industrial businesses—an internal tension between hardware manufacturing and conglomerate resource allocation that would reemerge throughout its corporate history.
The CT Shock and the MRI Bet
That institutional inertia was shattered in the early 1970s from an unexpected quarter. Godfrey Hounsfield, an engineer at the British conglomerate EMI—best known as a recorded-music empire—introduced computed tomography. CT bypassed the limitations of conventional radiography by capturing cross-sectional X-ray projections from multiple angles and employing mathematical algorithms to reconstruct cross-sectional slices of internal anatomy. Overnight, conventional flat-film X-ray imaging appeared technologically obsolete.
Walter Robb, who led GE Medical Systems from 1973 to 1986, spearheaded the conglomerate's response. Robb accelerated GE’s internal CT development, converting a late start into commercial leadership, before committing capital to the emerging field of magnetic resonance imaging.13 Rather than relying on ionizing radiation, MRI utilizes powerful magnetic fields and radiofrequency pulses to align and perturb hydrogen protons in tissue water. Commercializing the technology required constructing massive superconducting electromagnets, cooled by liquid helium to near absolute zero, capable of maintaining field homogeneity precise enough to resolve soft-tissue contrast. At the 1983 meeting of the Radiological Society of North America, GE unveiled the Signa system, which the company marketed as the world's first high-field MRI scanner.14 Robb was later awarded the National Medal of Technology for championing the program.13
Welch's Laboratory
When Jack Welch assumed leadership of General Electric as chief executive in 1981, he instituted his signature operating mandate: every business unit had to achieve a first- or second-place market share in its global industry, or face restructuring, sale, or closure. GE Medical Systems met that standard, and Welch quickly transformed the division into an operational laboratory. Between 1986 and 1996, his protégé John Trani oversaw aggressive international expansion, cross-border joint ventures, and rigorous manufacturing discipline at GEMS, before departing to run the toolmaker Stanley Works.15
This postwar transformation established two foundational elements of GE HealthCare's investment profile. Strategically, it generated the proprietary hardware franchises in CT and MRI that still anchor the company's global hospital relationships. Culturally, it forged an operations-first, scale-driven organization that treated global market share as its primary defense against cyclical capital spending. The next strategic phase would focus on transforming that growing installed base of heavy machinery into an annuity-like services business.
III. The Scanner Wars & Building the Service Fortress (1980s–2000s)
A Consumer Electronics Swap That Bought Europe
In July 1987, General Electric executed one of the most unconventional asset swaps in modern corporate history. The conglomerate traded its consumer electronics business—most of which it had recently absorbed through its acquisition of RCA—to France's Thomson-CSF in exchange for Thomson's medical equipment operations and between $500 million and $1 billion in cash.16 With a single transaction, GE exited a fiercely contested television manufacturing market dominated by Japanese rivals while acquiring an established European diagnostic imaging footprint that would have required a decade to build organically. Jack Welch's mandate—requiring each business to achieve a first- or second-place market share—had been applied in reverse: shed a commoditized consumer franchise to consolidate global leadership in medical capital goods.
In Asia, expansion proceeded through strategic partnership. In 1982, GE partnered with Japan's Yokogawa Electric to form Yokogawa Medical Systems. By 1994, the venture was reorganized as GE Yokogawa Medical Systems, with GE holding a 75% majority stake.17 The alliance provided GE with a vital commercial beachhead in Japan as well as a cost-effective engineering and manufacturing base for the broader Asian market. It established an early operational template for the "in-country, for-country" manufacturing strategy that GE HealthCare continues to deploy across China today.
The late 1990s brought a series of targeted acquisitions designed to expand the division beyond radiology suites. In 1998, GE acquired Norway’s Vingmed Sound, establishing the technological foundation for its cardiovascular ultrasound franchise.18 That same year, GE Medical Systems completed an all-stock acquisition of Marquette Medical Systems, valued at $45 per Marquette share at signing, integrating patient monitoring and diagnostic cardiology into the portfolio.19 Those monitoring assets formed the structural nucleus of what is today the Patient Care Solutions segment—the operating division placed under strategic review in mid-2026.
The Real Profit Pool: Keeping Machines Alive
Diagnostic scanners are typically sold through competitive, cyclical capital procurement cycles. Healthcare systems replace a CT or MRI system roughly once a decade, negotiating aggressively through group purchasing organizations. Consequently, the durable profit pool lies not in the initial hardware transaction, but in maintenance. A hospital that suffers an unplanned MRI outage forfeits scheduled procedure revenue, strains clinical workflows, and damages physician relationships. To safeguard uptime, hospital administrators commit to lucrative multi-year service contracts encompassing 24-hour remote diagnostic monitoring, expedited spare parts delivery, and specialized field engineering support.
GE constructed that operational infrastructure systematically. The company paired proprietary diagnostic software—designed to identify hardware faults and system degradation—with an expansive global field engineering workforce. Together, these capabilities converted one-off capital sales into decades-long recurring revenue streams. While GE HealthCare does not break out pure standalone service margins as an isolated line item in its reporting, the segment economics offer clear indirect confirmation: operating units characterized by high installed-base density and recurring consumable demand have consistently generated the company's highest segment operating margins.
Myth vs. Reality: Was the Service Moat Impregnable?
The conventional investment bull case has long portrayed GE's proprietary diagnostic software and dedicated field engineering corps as an unassailable competitive moat, shielding its installed base from third-party encroachment. The historical record, however, reveals a more vulnerable architecture—one challenged directly by federal antitrust regulators.
In 1996, the U.S. Department of Justice filed an antitrust suit against General Electric, alleging that the conglomerate licensed its advanced diagnostic software to hospital systems only on the condition that they refrain from competing with GE to service medical equipment at other healthcare facilities. Under the terms of a 1998 consent decree, the government voided those restrictive licensing provisions across more than 500 hospital networks. The settlement simultaneously permitted GE to acquire InnoServ, an independent multi-vendor maintenance provider, but required GE to divest InnoServ’s proprietary diagnostic servicing software.20
Two strategic insights emerge from that legal confrontation. First, regulatory oversight established an enduring constraint on equipment manufacturers attempting to monopolize service tools, enabling hospital biomedical engineering teams to service their own equipment more freely. Second, rather than resisting third-party multi-vendor maintenance, GE opted to internalize it, expanding its commercial mandate to service competitor machinery.
This precedent reframes the strength of the installed-base moat. While customer lock-in remains powerful, it is governed not by airtight legal exclusivity, but by operational scale, parts availability, and engineering response times. The definitive operational metrics that would signal any structural degradation in this moat—namely, service contract renewal rates and pricing realization—are not broken out in the company's financial disclosures, leaving public market investors to infer service retention from broader margin trends.
Having established its industrial imaging and servicing engine, GE spent the ensuing two decades attempting to extend that scale into clinical software and life sciences. That expansion would yield one remarkably lucrative franchise, an expensive strategic detour, and an emergency divestiture whose financial consequences linger over the standalone enterprise today.
IV. The Conglomerate Tax & The Sacrificial Lamb (2000s–2021)
The £5.7 Billion Handshake
On October 10, 2003, Jack Welch's successor, Jeff Immelt, announced General Electric's most ambitious bet on healthcare: an all-stock acquisition of Amersham plc, the British life sciences and diagnostic imaging agents group. Valued at 800 pence per share, the transaction totaled roughly £5.7 billion, or $9.5 billion.21 When the transaction closed on April 8, 2004,22 Amersham chief executive Sir William Castell joined GE as a vice chairman and took the helm of the combined healthcare business.21
For Immelt, Amersham represented the operational centerpiece of a strategic thesis he termed "early health." By diagnosing pathology at the molecular level, GE aimed to shift up the clinical value chain from selling capital hardware to influencing frontline therapy decisions. The conceptual parallels to modern GE HealthCare strategy are striking: two decades apart, leadership arrived at essentially the same conclusion—that imaging hardware delivers superior economic value when paired with proprietary chemistry and diagnostic data. The distinction lies in balance-sheet capacity: Immelt pursued that integration using a sprawling conglomerate balance sheet, whereas modern chief executive Peter Arduini must fund that expansion from GEHC's standalone cash generation.
The Amersham acquisition brought two fundamentally distinct operating divisions. The first was a bioprocessing and life sciences business that supplied filtration equipment, chromatography columns, and single-use consumables used to manufacture biologic therapies. The second was a diagnostic pharmaceuticals portfolio consisting of contrast media injected prior to CT and X-ray angiograms, alongside radioactive molecular tracers for nuclear medicine. Two decades later, that diagnostic chemistry franchise would endure to become the highest-margin operating segment within standalone GE HealthCare.
The Software Detour
GE's subsequent expansion targeted clinical information technology. In September 2005, the company agreed to acquire IDX Systems for $44 per share in cash, representing approximately $1.2 billion net of acquired cash.23 The strategic thesis appeared logical: by controlling both diagnostic scanners and medical image archives, GE could theoretically capture the underlying clinical and administrative software workflows governing hospital operations.
In execution, however, healthcare enterprise software followed a very different trajectory. The U.S. electronic health record boom of the late 2000s and 2010s was dominated by dedicated software vendors, most notably Epic Systems. GE's Centricity suite never achieved platform dominance across hospital networks. In April 2018, GE agreed to sell its value-based care software unit—encompassing revenue cycle, ambulatory care, and workforce management applications—to private equity firm Veritas Capital for $1.05 billion in cash.24 After more than a decade of capital investment and system integration, GE divested the assets for less than the headline purchase price of IDX alone.
The underlying failure reflected a classic mismatch between industrial hardware culture and enterprise software development. Hardware engineering organizations excel at deploying fixed physical assets and supporting them through multi-year service contracts. Enterprise software, by contrast, demands continuous delivery cycles driven by day-to-day clinician workflow feedback. GE's corporate operating rhythms—governed by Six Sigma manufacturing discipline, annual capital budgeting, and sales forces conditioned to market multi-million-dollar imaging suites—proved ill-suited to enterprise software procurement, where hospital chief information officers rather than radiology department heads controlled purse strings. When the 2009 Health Information Technology for Economic and Clinical Health (HITECH) Act unleashed billions in federal incentives for electronic records adoption, hospital systems consolidated around integrated enterprise software platforms rather than specialized suites from equipment manufacturers.
This historical record provides critical context for standalone GE HealthCare. As current management presents artificial intelligence and proprietary clinical software as the primary catalysts for margin expansion, investors evaluate those commitments against an established precedent: the organization previously attempted a software pivot of comparable ambition, only to exit at a capital loss. While that past does not predetermine the outcome of modern AI initiatives, it underscores why market skeptics place the burden of proof squarely on execution.
The Meltdown and the Crown Jewel
By 2018, General Electric faced an acute balance-sheet crisis. On June 26, 2018, then-chief executive John Flannery—himself the former head of GE Healthcare—announced plans to separate the medical division entirely, proposing to monetize approximately 20% of the unit and distribute the remaining 80% to shareholders within 12 to 18 months under GE Healthcare chief executive Kieran Murphy.25 Just three months later, on October 1, 2018, GE’s board ousted Flannery after barely a year in office, appointing former Danaher chief executive Larry Culp as chairman and CEO.26
Culp took charge of a parent enterprise burdened by unsustainable leverage, severe cash burn in its power division, and legacy long-term care insurance liabilities. Deleveraging the balance sheet required rapid liquidity, and the most readily monetizable asset within the portfolio was the biopharma operation his former firm had long evaluated.
On February 25, 2019, Danaher agreed to acquire GE’s biopharma business for $21.4 billion, yielding approximately $20 billion in net cash proceeds after tax benefits.27 The transaction closed on March 31, 2020, just as global lockdowns took hold, with Danaher rebranding the division as Cytiva.28 The divestiture proved poorly timed for the healthcare business: bioprocessing tools and consumables were on the cusp of an unprecedented demand boom driven by global vaccine manufacturing and monoclonal antibody production. The initial 2018 separation blueprint was shelved, and GE Healthcare was stripped of its fastest-growing, highest-margin consumables franchise. The remaining portfolio—centered on diagnostic imaging, ultrasound, patient monitoring, and pharmaceutical diagnostics—was left with higher capital intensity and greater exposure to cyclical hospital capital spending.
While Culp’s decision effectively stabilized the parent conglomerate by generating crucial debt-reduction liquidity, it illustrated the classic conglomerate tax in stark terms: a thriving, defensive life sciences business was dismantled to absorb financial distress generated by industrial divisions entirely unrelated to healthcare.
One Last Purchase on the Parent's Balance Sheet
Before executing the final corporate spin-off, General Electric completed one final medical technology transaction on the parent balance sheet. On September 23, 2021, GE agreed to acquire BK Medical, an advanced surgical ultrasound specialist, from private equity sponsor Altaris for $1.45 billion in cash.29 The acquisition was intended to extend GE's traditional diagnostic ultrasound footprint directly into surgical suites, enabling real-time intraoperative visualization and providing imaging infrastructure for robotics-assisted surgical procedures.30
Valuation multiples beyond the headline purchase price were not disclosed in public filings, nor does management report standalone financial performance for BK Medical, which remains embedded within the broader Ultrasound segment. For public market investors evaluating post-acquisition capital returns, the absence of segmented operational disclosures leaves little visibility into whether the asset has delivered on its surgical integration thesis.
Two decades of transformative acquisitions, ill-fated software bets, and defensive divestitures ultimately reshuffled GE's medical operations into a narrower, hardware-centric enterprise. Having relinquished its life sciences crown jewel to preserve its parent, GE HealthCare was prepared for independent life as a standalone industrial pure-play.
V. The Great Carve-Out: Engineering Standalone GEHC (2021–2023)
The Announcement
On November 9, 2021, Larry Culp announced that General Electric would break itself apart into three independent public companies, confirming that healthcare would be spun off in early 2023 with GE retaining a 19.9% stake, followed by energy in 2024 and aviation remaining as the parent entity.3 The structural shift marked an institutional acknowledgment that the conglomerate model had become a net hindrance rather than a financial shield. Healthcare did not require an emergency fire sale; it needed the autonomy to allocate its own capital, direct its own research priorities, and trade on its standalone operational merits.
The Man Who Came Back
Months earlier, on June 24, 2021, GE had named Peter Arduini chief executive of GE Healthcare, effective January 2022, to succeed Kieran Murphy.31 The appointment represented a deliberate balance of institutional familiarity and standalone medtech leadership. Arduini had spent 15 years within GE Healthcare early in his career, subsequently led Baxter's medication delivery division, and from 2012 served as president and chief executive of Integra LifeSciences, a publicly traded mid-cap medtech manufacturer.31
In public presentations and quarterly earnings calls, Arduini has presented an operations-driven demeanor rather than executive showmanship, prioritizing product launch cadence, commercial order funnels, lean manufacturing, and "in-country, for-country" localization over sweeping corporate rhetoric. His decade leading Integra provided direct exposure to the public-market discipline that a conglomerate division rarely encounters: meeting quarterly market expectations, executing programmatic tuck-in acquisitions without a parent corporate apparatus, and systematically pruning underperforming product lines. Those operating disciplines mirror the exact challenges confronting standalone GEHC as it integrates software assets like Intelerad and evaluates the future of Patient Care Solutions. The enduring strategic question for investors is whether an operational playbook refined at a mid-cap enterprise can scale effectively across a global organization more than ten times Integra's size.
The Plumbing of a Spin-Off
Corporate spin-offs often appear seamless in press releases, but their financial architecture is dictated by capital-structure engineering. GE HealthCare’s capital structure was shaped by the parent company's imperative to transfer leverage to its newly minted subsidiary.
In November 2022, GEHC issued $8.25 billion in senior unsecured notes across six tranches, with maturities extending from 2024 to 2052.32 Approximately $4.25 billion constituted "new money," with the net proceeds distributed directly to GE. The remaining $4.0 billion of notes was transferred to GE, which used the paper to extinguish its own outstanding commercial borrowings through debt exchanges.32 On the spin-off distribution date, GEHC drew down an additional $2.0 billion under a three-year term loan facility. The separation information statement detailed approximately $10.2 billion in total debt and an aggregate cash distribution to General Electric of approximately $4.9 billion.332 In practical terms, the medical business commenced independent life by absorbing a substantial share of its former parent’s deleveraging burden.
Capital structure was not the only point of friction. General Electric retained an initial 19.9% equity stake, monetizing the position across the subsequent two years primarily through structured debt-for-equity exchanges handled by Morgan Stanley. The parent company completed the disposal of its remaining shares in November 2024.34 For its first twenty-three months of regular-way trading, GEHC’s share register was constrained by a known, large-scale seller—a technical supply overhang that frequently depresses a spin-off's valuation multiple until fully absorbed.
Intellectual property rights introduced another operational nuance. The historic "GE" monogram and corporate brand—the core visual assets hospital procurement committees recognize worldwide—remain the property of General Electric. Standalone GEHC operates under a fee-bearing trademark licensing agreement structured in ten-year renewable terms, subject to termination under specific triggers such as a corporate change of control.2 The branding that underpins customer trust is an asset the company leases rather than owns.
Building a Company Around a Division
Governance for the standalone entity was designed to establish boardroom independence while preserving continuity with the parent company. In September 2022, General Electric appointed Larry Culp as non-executive chair of the incoming GEHC board.35 As of the company's 2026 proxy statement, Culp continues to serve as chair, categorized under governance standards as an independent director.36 In May 2026, Rodney Hochman was appointed independent lead director.37 On September 22, 2026, the company announced that AT&T’s retiring chief financial officer, Pascal Desroches, would join the board effective January 4, 2027.38
Executive leadership in the finance seat has experienced greater volatility. Helmut Zodl served as the company's initial chief financial officer through the separation. In May 2023, GEHC appointed Jay Saccaro—who had served as CFO at Baxter since 2015 and previously at Hill-Rom—as chief financial officer, effective June 1, 2023.39 Three years later, in July 2026, Saccaro announced his resignation, and corporate controller George Newcomb was named interim CFO effective August 14, 2026.4010 While an executive departure mid-transformation does not inherently signal fundamental operational distress, an unexpected transition in the finance office—occurring simultaneously with a strategic review of Patient Care Solutions and following a downward revision to full-year margin guidance—introduces acute execution risk and elevates scrutiny on a permanent successor.
What Separation Actually Changed
The most demanding operational carve-out work unfolded far from public view. As an integrated division, the healthcare business had relied on General Electric’s corporate center for treasury operations, tax structuring, enterprise IT architecture, pension asset management, corporate risk insurance, and enterprise-wide procurement. Transitional service agreements with the former parent provided operational continuity during the initial separation. Over time, however, each shared service had to be built organically or outsourced, establishing standalone administrative expense lines that flowed through the income statement as recurring corporate overhead alongside multi-year restructuring expenses. This dynamic is central to evaluating the company's financial trajectory: because initial margin gains in 2023 and 2024 were driven substantially by internal restructuring and productivity programs, market participants must distinguish between temporary cost-out benefits and sustainable operating leverage. The margin compression that surfaced in 2025 and 2026 indicates that structural dis-synergies were more substantial than early spin-off projections implied.
Yet the operational dividend of independence is equally concrete. Standalone status grants GE HealthCare direct authority over its research and development allocation, capital expenditure budgets, and portfolio acquisitions. Management incentives are tied directly to GEHC’s standalone performance and equity valuation rather than diluted across conglomerate divisions. Strategic capital deployment—such as the clinical software acquisition of Intelerad—can proceed without competing against the capital requirements of jet engine manufacturing or power turbine servicing. Independence does not ensure flawless capital allocation, but it eliminates conglomerate mediation: the operational successes and strategic miscalculations belong entirely to GE HealthCare’s leadership and board.
With the corporate apparatus established and standalone financing in place, the strategic focus shifts to the operating machinery itself—and the four distinct divisions that generate its cash flow.
VI. Anatomy of a $20B Healthcare Giant: Segment Realities & Unit Economics
Three Businesses, Three Different Economies
Consider the diagnostic workflow across a typical major hospital. In the radiology suite, a patient enters a CT scanner after receiving an intravenous dose of iodinated contrast to illuminate vascular structures. Down the corridor, a sonographer maneuvers an ultrasound transducer across an expectant mother's abdomen. In the intensive care unit, bedside monitors track cardiac rhythms and arterial oxygen saturation. GE HealthCare can furnish every one of those tools. Yet the underlying unit economics of these categories diverge sharply, and that divergence defines the enterprise.
In mid-2026, GEHC consolidated its financial reporting into three operating segments. Management merged the standalone Imaging and Advanced Visualization Solutions divisions into Advanced Imaging Solutions (AIS), which now reports alongside Patient Care Solutions (PCS) and Pharmaceutical Diagnostics (PDx).418 The realignment marked the company's second structural reshuffle in two years. In 2024, the former Ultrasound unit was expanded into Advanced Visualization Solutions (AVS), a transfer that caused reported Imaging revenue to contract from roughly $10.6 billion in 2023 to $8.9 billion in 2024 as product lines shifted.442 While frequent organizational revisions are common following a corporate carve-out, they obscure multi-year performance trends, requiring investors to evaluate recast segment histories with caution.
Advanced Imaging Solutions: The Engine
AIS forms the commercial core of the business. On a recast basis, the division generated approximately $14.6 billion in 2025 revenue—representing roughly 70% of consolidated sales—and an operating segment margin of about 14.2%.41 The portfolio encompasses CT, MRI, molecular imaging, X-ray, mammography, and image-guided therapy systems, alongside the complete ultrasound portfolio: the Voluson women's health franchise, Vivid cardiovascular scanners, and the BK Medical intraoperative surgical systems.
That aggregate margin masks a stark operational divide within the newly merged unit. In 2024, prior to the consolidation, the standalone Imaging segment generated an operating margin of 12.3% on $8.9 billion in sales, while AVS—anchored by ultrasound—delivered a 25.6% margin on $5.1 billion.42 Ultrasound functions as a higher-volume, lower-ticket, more repeatable capital purchase, where GE's clinical brand equity and installed footprint yield pricing power. Heavy diagnostic hardware presents far tougher operating dynamics: large-bore CT and MRI scanners contend with protracted procurement cycles, aggressive hospital tender discounting, and substantial research burdens. First-quarter 2026 results underscored that divergence, as the legacy Imaging margin deteriorated to 7.8% while AVS maintained a 22.3% margin.43 Blending both franchises into AIS creates a smoother composite financial profile, but it effectively obscures the margin volatility of the heavy equipment business.
Within AIS, capital allocation centers on distinct technological bets. In magnetic resonance, the company received FDA clearance in May 2020 for its proprietary deep-learning reconstruction algorithm, AIR Recon DL.44 The software reduces image noise to accelerate image capture, with management claiming it can reduce patient scan durations by up to 50%.45 A subsequent cardiac application, Sonic DL, secured clearance in 2023, accompanied by claims of scan speeds up to twelve times faster than conventional acquisitions.46 In hardware engineering, GEHC introduced its sealed "Freelium" magnet architecture in February 2025. Requiring less than 1% of the liquid helium consumed by conventional superconducting systems, the 1.5T platform secured FDA clearance in February 2026.4748 The engineering shift addresses a critical operational vulnerability: liquid helium remains a finite, costly commodity subject to acute geopolitical supply disruption.
The economic mechanics of large-scale diagnostic hardware dictate this dynamic. Procurement typically initiates through competitive institutional tenders. Equipment manufacturers submit bids against rigid technical specifications, where final pricing negotiations frequently turn on marginal concessions. While upfront hardware margins can be razor-thin, winning a procurement tender secures a captive decadal revenue stream encompassing maintenance contracts, software licensing, replacement components, and preferential positioning for future replacement cycles. The company's total order backlog—encompassing both capital equipment orders and multi-year service obligations—stood at $23.9 billion at the close of the second quarter of 2026, representing more than a full year of enterprise sales.8 Compressed hardware margins indicate that competitive pricing pressures, compounded by component and logistics inflation, outpaced the company's ability to push through contractual price realization.
In computed tomography, competitive differentiation hinges on photon-counting detection. Conventional scintillation detectors function like a rain gauge, measuring aggregate absorbed radiation energy across an exposure. Photon-counting detectors, by contrast, record each individual X-ray photon and evaluate its specific energy level, delivering superior spatial resolution and multi-energy tissue characterization at significantly reduced radiation doses. GEHC built its photon-counting capability through its 2020–2021 acquisition of Prismatic Sensors, a Swedish developer of deep-silicon detector technology. In March 2026, the FDA granted clearance for the company's Photonova Spectra system.7 While the regulatory clearance marks an essential technical milestone, it arrived more than four years behind rival Siemens Healthineers—a competitive deficit evaluated later in this analysis.
Patient Care Solutions: The Problem Child
Patient Care Solutions manufactures the bedside physiological monitors, anesthesia delivery workstations, diagnostic ECG carts, and neonatal incubators utilized across critical care and acute hospital settings. The division delivered stable revenue of roughly $3.1 billion in both 2024 and 2025, recording a 12.6% segment operating margin in 2024.429 Operational performance subsequently deteriorated. In the first quarter of 2026, organic revenue contracted 8.1% year over year as segment margins collapsed to 1.4%.43 By the second quarter of 2026, organic revenue dropped 13.5%, plunging the segment into operating losses with a negative margin of 3.8%.8
Concurrently with its second-quarter earnings release on July 29, 2026, GEHC announced a formal review of strategic alternatives for PCS to maximize shareholder value. During the investor call, management confirmed that potential outcomes encompass retained ownership, an outright divestiture, or alternative transaction structures.8 While no definitive transaction has materialized, the financial calculus is straightforward: carving out a $3 billion division operating below breakeven would immediately lift consolidated operating margins. However, an outright sale relinquishes top-line scale, while negotiating leverage resides largely with prospective strategic acquirers—such as Philips or Shenzhen Mindray Bio-Medical Electronics—who already possess commanding market positions. The strategic review represents an institutional admission that an asset portfolio assembled in the late 1990s has evolved into an operational drag, with the net financial realization of any corporate exit remaining unresolved.
Pharmaceutical Diagnostics: The Hidden Razor-Blade
Pharmaceutical Diagnostics operates as the organization's most consistently profitable franchise. The unit supplies iodinated contrast media, including Omnipaque and Visipaque, alongside specialized radiopharmaceuticals and molecular imaging tracers such as DaTscan for Parkinsonian syndromes, Vizamyl for amyloid beta PET imaging, and Cerianna for estrogen-receptor-positive metastatic breast cancer.49 Every contrast-enhanced CT requires an individual vial; every molecular scan demands a dedicated tracer dose. Diagnostic scanners serve as the installed capital base, while PDx captures an annuity-like consumables stream—supplying contrast agents not only for GE equipment, but across third-party imaging systems globally.
The segment's reported financials reflect that structural advantage. In 2024, PDx generated an operating margin of 32.2% on $2.5 billion in revenue, posting 9% organic growth—the strongest performance across the enterprise.42 Division revenue expanded to $2.9 billion in 2025.9 That momentum carried into 2026, with second-quarter organic revenue rising 14.6% alongside a 29.6% segment margin.8 Strategic capital deployment contributed to that expansion: in March 2025, GEHC completed the acquisition of the remaining equity stake in Japanese radiopharmaceutical manufacturer Nihon Medi-Physics.5 Product pipeline execution provided additional support; in September 2024, the FDA approved Flyrcado (flurpiridaz F-18), a novel myocardial perfusion PET imaging tracer whose 110-minute radioactive half-life allows centralized commercial cyclotron manufacturing and unit-dose regional distribution rather than requiring on-site cyclotron synthesis.50
Myth vs. Reality: Is PDx Recession-Proof?
The prevailing investment thesis asserts that PDx offers insulated, non-cyclical cash flows that protect GEHC against fluctuations in hospital capital expenditure budgets. While clinical procedure volumes support the demand thesis, supply-chain history reveals material operational concentration.
In the spring of 2022, municipal COVID-19 lockdowns in Shanghai forced the temporary closure of GE's primary global Omnipaque manufacturing facility. The company alerted hospital systems to anticipate an 80% curtailment in order fulfillment spanning six to eight weeks.51 Because GE controlled approximately one-third of the global contrast media market,52 the stoppage triggered acute clinical rationing worldwide. Health systems with limited inventories—such as Vanderbilt University Medical Center, which held seven to ten days of supply—reduced institutional contrast consumption by roughly 50% within a single week, conserving doses and redirecting diagnostic protocols toward ultrasound or non-contrast magnetic resonance.51 Production returned to roughly 60% of capacity by late May and was fully restored by June 8, after municipal restrictions eased and GE surged production at its Cork, Ireland facility while air-freighting global shipments.52
Management responded with dedicated capital expenditure. In November 2022, the company committed $80 million to expand active pharmaceutical ingredient capacity at its chemical manufacturing plant in Lindesnes, Norway, by 30%, concurrently investing in a new fill-and-finish line in Cork, Ireland, and securing multi-year raw iodine supply agreements.53 In February 2025, GEHC committed an additional $138 million to expand the Cork facility. Leadership estimates the total addressable contrast media market at approximately $7 billion, expanding at an annual rate of 5% to 7%.54
The evidence refines the investment premise: while clinical demand for contrast media is durable and generates the company's highest operating margins, the 2022 supply disruption demonstrated that manufacturing concentration represents a significant operational vulnerability. Subsequent capital investments mitigate that exposure without eliminating it entirely. For institutional investors, PDx remains the operating division most capable of commanding a premium valuation multiple. The decisive operational metric is whether the segment can sustain high-single-digit organic revenue growth as Flyrcado commercializes and amyloid-targeting diagnostic tracers for Alzheimer's disease scale.
If Pharmaceutical Diagnostics serves as the company's quiet cash engine, artificial intelligence represents its loudest strategic commitment. The operational question is whether software generates standalone economic value or merely functions to protect hardware margins.
VII. Precision Care & The AI Frontier: Algorithmic Moat or Hardware Feature?
A Nurse, a Probe, and an Algorithm
Consider a rural clinic lacking a specialized cardiac sonographer. A nurse places an ultrasound transducer against a patient's chest while onboard software guides every adjustment in real time—angle left, slide down, hold steady—before automatically capturing a diagnostic-quality echocardiogram. That clinical workflow formed the core premise behind Caption Health, which GE HealthCare acquired in February 2023 for $127 million in upfront cash, a $10 million holdback, and up to $13 million in contingent earn-outs.55
The transaction exemplified what Peter Arduini terms "precision care": embedding algorithmic intelligence into physical capital goods to simplify clinical operation and link diagnostic imaging directly to therapy selection. Under this strategic vision, GEHC seeks to evolve from a traditional capital-equipment manufacturer selling industrial hardware into an essential digital infrastructure layer governing clinical care decisions.
The Digital Buying Spree
The company's initial post-separation software transactions were measured in scale. On April 1, 2024, GEHC completed the acquisition of Cleveland-based MIM Software, which develops clinical imaging analysis and automated contouring applications for radiation oncology and nuclear medicine, for approximately $259 million net of acquired cash,56 plus up to $36 million in contingent milestone payments.[^57] In 2025, the company acquired icometrix, a Belgian developer of artificial intelligence software that analyzes brain MRI scans to track neurological conditions and support emerging Alzheimer's therapies, for an undisclosed sum.5
That disciplined posture changed significantly in early 2026. On March 18, 2026, GEHC completed the $2.3 billion acquisition of Intelerad, a provider of enterprise medical imaging software and cloud-based picture archiving and communication systems.43 Intelerad represents the largest acquisition of the company's standalone era—surpassing the combined scale of Caption Health and MIM Software several times over. Funded while the corporate balance sheet remained leveraged from the 2023 spin-off, the transaction demonstrated that post-separation capital allocation is no longer confined to modest tuck-in deals.
The Clearance Scoreboard
In public communications, GE HealthCare routinely highlights the U.S. Food and Drug Administration's database of artificial intelligence- and machine learning-enabled medical devices as evidence of its technological lead.57 In May 2024, GE led the industry with 72 clearances, ahead of Siemens Healthineers at 64, Canon Medical Systems at 28, and Philips at 27.58 By July 2025, management announced that the company had reached 100 clearances, maintaining the top ranking on the FDA list for the fourth consecutive year.45 The company's 2025 annual report cited 115 AI-enabled FDA authorizations across its global portfolio.5
Myth vs. Reality: Is GEHC Becoming a Software Company?
The primary investment bull case contends that aggressive digital acquisitions and algorithm clearances will transform GE HealthCare into an enterprise with a substantial, high-margin stream of recurring software revenue commanding premium valuation multiples. Evaluating that thesis requires examining two practical operational tests: how much standalone revenue these clearances generate, and who ultimately pays for them.
On revenue generation, GEHC does not report standalone AI or software revenue as an isolated line item in its financial disclosures. The company's premier commercial algorithms, including AIR Recon DL in magnetic resonance and Sonic DL in cardiac imaging, are commercialized predominantly as integrated features of its scanning equipment. Their economic value materializes through faster scan speeds, expanded daily patient throughput, and a stronger technical argument in competitive hospital tenders, rather than as decoupled software-as-a-service subscriptions. While higher throughput protects equipment pricing power and increases customer switching costs, it functions fundamentally as an enhancement to hardware sales rather than as a standalone recurring software business.
On purchasing dynamics, historical precedent warrants institutional caution. Two decades ago, the medical division pursued a similar software thesis through its acquisition of IDX Systems, only to sell the core value-based care assets to Veritas Capital at a capital loss after failing to dominate hospital-wide enterprise workflows.2324 The acquisition of Intelerad represents a deliberate attempt to capture dedicated, recurring enterprise software revenue. Whether the asset successfully accelerates recurring software growth or struggles against specialized health-tech competitors will depend on whether management begins disclosing standalone software revenue and margin trends to public markets.
Furthermore, the competitive landscape presents external technological challenges. Foundational computer vision and multimodal artificial intelligence models developed by large technology platforms and academic consortia are advancing rapidly in medical image interpretation. Simultaneously, hospital networks are increasingly adopting vendor-neutral software platforms capable of running AI algorithms across multi-vendor fleets. If basic image reconstruction and feature detection become commoditized utilities, an accumulated lead in regulatory clearances will offer diminishing commercial differentiation during institutional tenders. GEHC's primary strategic defense is to integrate its proprietary algorithms directly into scanner acquisition pipelines and raw signal workflows where external models cannot easily operate. That architecture represents an effective defensive barrier, but it serves to safeguard physical equipment margins rather than open an independent software profit pool.
The operational record suggests that market claims portraying GEHC as an emerging software company overstate the current reality. Artificial intelligence functions as an effective competitive instrument that reinforces hardware pricing power and deepens field service retention, but it has not yet evolved into an autonomous profit engine. Regulatory clearance tallies reflect engineering productivity rather than commercial monetization. The confirming milestone for investors will be sustained, transparently disclosed software revenue growth from Intelerad and the digital portfolio at accretive operating margins. The disconfirming signal would be margin dilution and another quiet asset write-down.
With that software premise evaluated, the analysis turns next to the durable competitive moats that protect the industrial core.
VIII. Strategic Architecture: 7 Powers & Porter’s Five Forces
A Chess Board With Three Big Players
For decades, the global diagnostic imaging market has operated as a disciplined triopoly dominated by GE HealthCare, Siemens Healthineers, and Philips. Each competitor understands the others' installed base, pricing strategies, and product cycles through thousands of institutional hospital tenders. More recently, however, an aggressive fourth competitor—Shanghai-based 上海联影医疗 (United Imaging Healthcare)—has entered the arena. Applying classical strategic frameworks clarifies a central question: which of GE HealthCare's operational advantages are truly proprietary and defensible, and which are structural characteristics shared across the entire imaging oligopoly?
Hamilton Helmer's 7 Powers
Switching costs: strong, but bounded. Hospital systems running large fleets of GE scanners invest heavily in clinical training on proprietary user interfaces, integrate imaging protocols into institutional picture archiving and communication systems, and commit to multi-year maintenance agreements. Transitioning to an alternative vendor requires costly technician retraining, clinical workflow re-engineering, and new servicing relationships, providing substantial incumbency protection. However, as demonstrated by the 1998 Department of Justice antitrust settlement, legal and regulatory constraints prevent equipment manufacturers from fully monopolizing servicing tools. Furthermore, sophisticated hospital procurement committees deliberately maintain multi-vendor equipment fleets to preserve commercial bargaining leverage and resist single-vendor lock-in.
Scale economies: strong. Developing next-generation computed tomography or magnetic resonance imaging platforms demands hundreds of millions of dollars in capital expenditure and protracted clinical development cycles. Management reports that GEHC has invested more than $5.1 billion in research, development, and product capital expenditures since the corporate separation.5 An incumbent possessing a vast global installed base can amortize those fixed research investments—alongside the substantial overhead of a worldwide field service network—across a vastly higher unit volume than any regional contender. Yet because Siemens Healthineers commands comparable operating scale, this dynamic operates primarily as a formidable barrier to new entrants rather than a decisive source of differentiation against top-tier peers.
Process power: moderate. Decades of specialized engineering in fabricating superconducting magnets, high-vacuum X-ray tubes, and precision radiation detectors generate proprietary manufacturing know-how that competitors cannot easily duplicate. The company's sealed-magnet Freelium architecture and deep-silicon photon-counting detectors represent notable examples of this industrial craftsmanship.477 Nevertheless, the fact that Siemens Healthineers secured commercial clearance for photon-counting CT more than four years ahead of GEHC illustrates that specialized process know-how does not inherently guarantee sustained technological primacy.
Cornered resource: moderate, concentrated in PDx. GEHC's proprietary contrast media and radiopharmaceutical manufacturing and distribution network—encompassing its specialized chemical plants, multi-year raw iodine supply contracts, and regional radiopharmacy infrastructure such as Nihon Medi-Physics—constitutes an operational asset that is difficult for pure-play hardware competitors to replicate. At the same time, the 2022 Shanghai manufacturing halt demonstrated that high geographic concentration can transform a strategic asset into an acute operational vulnerability.
Brand: moderate. The century-old "GE" monogram commands deep clinical trust and institutional credibility among hospital administrators and department chairs. Yet standalone GEHC leases rather than owns that brand identity under a licensing arrangement structured in renewable ten-year terms.2
Network effects: weak. Diagnostic imaging hardware exhibits negligible direct network effects: an individual CT or MRI scanner does not become inherently more valuable simply because neighboring healthcare systems install the same platform. While aggregated, multi-site scan data could theoretically generate algorithmic learning advantages for diagnostic software, there is little empirical evidence that data-driven feedback loops have established an unassailable competitive moat.
Counter-positioning: absent. GE HealthCare operates as a traditional industrial incumbent, competing across the same commercial vectors, tender cycles, and service models as its historical peers. Conversely, domestic challenger 上海联影医疗 (United Imaging Healthcare) has deployed counter-positioning against GEHC in China, utilizing state industrial backing and aggressive tender pricing to capture domestic market share without having to defend the high gross margins and legacy cost structures required by Western multinational incumbents.
Porter's Five Forces
Threat of new entrants: low in Western markets, high in China. Stringent regulatory clearances, lengthy clinical validation cycles, substantial capital requirements, and the necessity of deploying a round-the-clock global field engineering workforce effectively shield premium Western imaging markets from de novo entrants. China, however, represents a notable exception. Subsidized by state industrial policy and favored by national procurement mandates, domestic champions have successfully overcome these entry barriers to challenge established multinationals on their home ground.
Buyer power: high and rising. In the United States, hospital consolidation and the growing clout of group purchasing organizations have concentrated commercial procurement power into fewer, more sophisticated hands. Across Europe and Asia-Pacific, equipment purchases are predominantly governed by centralized national health services or public procurement tenders. These institutional buyers routinely split fleet awards across multiple vendors, negotiate aggressive volume discounts, and leverage competitive bidding to compress upfront hardware margins. China's centralized volume-based procurement represents the most aggressive manifestation of this dynamic.
Supplier power: moderate. Equipment and consumables manufacturing depends on critical raw materials and components, including liquid helium, raw iodine, specialized semiconductor chips, and memory components. When supply constraints emerge, input inflation directly pressures operating margins. In April 2026, GEHC lowered its full-year margin guidance, citing significant cost increases across memory chips, oil, and global freight—a direct demonstration of supplier power compressing operating results.43
Threat of substitutes: low. Cross-sectional diagnostic imaging remains indispensable to clinical practice; no non-imaging diagnostic modality can replace the anatomical visualization required prior to complex surgical interventions, oncology therapy staging, or acute stroke management. Substitution occurs almost entirely across imaging modalities—such as substituting diagnostic ultrasound for computed tomography to avoid ionizing radiation—and GEHC maintains commanding market positions across all primary diagnostic categories.
Rivalry: intense but historically rational. Competition among the primary imaging manufacturers—GE HealthCare, Siemens Healthineers, and Philips—is fierce in technical specifications and commercial bids, yet pricing behavior has historically remained rational. Rather than engaging in destructive price wars that would permanently erode hardware gross margins, the oligopoly has competed on technological differentiation, workflow productivity, and total cost of ownership. The growing penetration of Chinese state-backed competitors in emerging markets represents the primary threat to that historical pricing discipline.
What the Frameworks Say Together
Synthesizing Helmer's 7 Powers and Porter's Five Forces reveals an underlying strategic paradox. GE HealthCare operates within an inherently attractive industry characterized by high barriers to entry, virtually zero threat of external substitution, and historically disciplined oligopolistic rivalry. Yet the durable competitive advantages that protect this industry belong largely to the collective oligopoly rather than to GEHC uniquely. Scale economies, switching costs, and precision manufacturing processes shield the incumbent triumvirate from outside disruption, but they do little to guarantee that GEHC can systematically capture market share from Siemens Healthineers or permanently insulate its margins against United Imaging.
The defining structural exception is Pharmaceutical Diagnostics. Neither Siemens nor Philips possesses an in-house contrast media and radiopharmaceuticals business. PDx equips GEHC with an annuity-like consumables stream that monetizes global procedure volumes across the entire industry, generating revenue every time a patient receives contrast media regardless of whether the scan occurs on a GE, Siemens, or Philips system. In Helmer's taxonomy, this captive diagnostic chemistry franchise represents the closest asset GEHC holds to an asymmetrical competitive power that its direct hardware rivals cannot easily match—even if its manufacturing concentration introduces acute operational risk.
The strategic implication is clear: GE HealthCare's long-term returns on capital depend less on attempting to dislodge Siemens from its hardware strongholds than on preserving oligopolistic pricing discipline in capital tenders while accelerating the high-margin consumables and precision software that ride atop the global installed base. That delicate balance sets the stage for an examination of the competitive battlefield itself.
IX. Competitive Landscape: The Big Three vs. The Chinese Giant
Siemens Healthineers: First Across the Line
On September 30, 2021, Siemens Healthineers announced FDA clearance for the Naeotom Alpha, marketing the platform as the world's first photon-counting CT scanner, powered by cadmium telluride semiconductor detectors.59 That regulatory milestone arrived more than four years before GE HealthCare secured clearance for its silicon-based Photonova Spectra in March 2026. By January 2026, Siemens reported roughly €1 billion in cumulative photon-counting orders and approximately €700 million in commercial revenue from the technology.7 Wall Street analysts anticipate that GEHC's photon-counting orders will build gradually through late 2026, with material revenue contribution unlikely before 2027.7
Siemens Healthineers completed its initial public offering in Frankfurt in March 2018 at €28 per share, with former parent Siemens AG retaining a majority equity stake.60 In April 2021, the German group closed its $16.4 billion acquisition of radiation oncology leader Varian Medical Systems,61 establishing a comprehensive presence in cancer therapy that GEHC cannot match through its diagnostic portfolio alone. For its fiscal year 2025, Siemens Healthineers reported approximately €23.4 billion in revenue, reflecting comparable revenue growth of 5.9%.62 The German peer operates not only as a larger and faster-growing enterprise, but as the incumbent that secured commercial first-mover advantage in photon-counting detection.
For GEHC, the primary strategic question is not merely whether its proprietary deep-silicon detectors can match cadmium telluride in physical resolution or energy discrimination. Rather, it is whether Siemens's four-year lead in academic medical center installations, peer-reviewed clinical literature, and radiologist familiarity has established institutional switching costs that GEHC cannot easily overcome in premium tenders. The decisive evidence to track will be photon-counting order intake and revenue disclosures across late 2026 and 2027.
Philips: The Wounded Rival
Royal Philips has spent five years managing the fallout from an acute product quality crisis within its Respironics division. In June 2021, the Dutch group initiated a massive global recall of sleep apnea machines and mechanical ventilators over concerns that sound-abatement foam could degrade into toxic particulates. In April 2024, Philips entered into a consent decree with the U.S. Department of Justice and the Food and Drug Administration, halting new U.S. sales of sleep and respiratory care devices until strict operational remediation standards are met.63 That same month, Philips agreed to pay $1.1 billion to resolve U.S. personal injury and medical monitoring claims, recording a €982 million litigation provision against its earnings.64
The multi-year crisis absorbed executive attention and impaired Philips's institutional standing across hospital procurement offices, creating a plausible commercial opening for GEHC to capture market share in diagnostic imaging and patient monitoring tenders. Yet GEHC's operational results illustrate the limits of competitor distress: despite Philips's vulnerabilities, Patient Care Solutions contracted organically and descended into operating losses in mid-2026. If Philips's institutional challenges created a commercial opportunity, it proved insufficient to counterbalance GEHC's internal execution and product headwinds in patient monitoring.
United Imaging: The Home-Field Champion
Founded in 2011, 上海联影医疗 (United Imaging Healthcare) completed an initial public offering on Shanghai's STAR Market on August 22, 2022, with its shares surging approximately 73% on its trading debut.65 The company manufactures a full diagnostic imaging portfolio encompassing magnetic resonance, computed tomography, positron emission tomography (PET/CT), diagnostic X-ray, and radiation therapy equipment.
United Imaging's recent financial results reflect both the policy volatility and underlying momentum of the Chinese healthcare equipment market. In 2024, annual revenue contracted roughly 10% to RMB 10.3 billion as centralized hospital equipment upgrade subsidies experienced bureaucratic disbursement delays.66 In 2025, revenue rebounded sharply, expanding approximately 34% to RMB 13.8 billion, aided by a 51% surge in international sales to RMB 3.4 billion—accounting for nearly a quarter of its consolidated business.67 Domestically, United Imaging reported holding the leading market share in China for magnetic resonance systems, ranking first in new CT unit installations for three consecutive years, and maintaining the top position in PET/CT systems for a decade.68 While these rankings reflect the manufacturer's own operational claims, they signal a clear shift in commercial momentum.
The underlying catalyst is domestic substitution—known in Chinese industrial policy as guochandaitai (国产替代). In centralized public procurement tenders, government guidelines favor qualified domestic manufacturers. Once a local diagnostic platform is judged clinically comparable to multinational alternatives, the premium pricing historically commanded by foreign incumbents becomes difficult to defend. Furthermore, United Imaging's international growth suggests that domestic champions are beginning to export price-competitive hardware into emerging markets across Southeast Asia, the Middle East, and Latin America.
The competitive landscape divides into two distinct operational fronts. In mature Western healthcare systems, GE HealthCare faces an entrenched technological race against Siemens Healthineers, which holds a four-year head start in photon-counting CT commercialization. In China, GEHC must defend its position within a structurally tilted procurement environment where a well-capitalized domestic rival is gaining share. Neither competitor is retreating, and neither battle has been decided—making a rigorous stress test of GEHC's direct exposure to China the logical next inquiry.
X. The China Stress Test: Anti-Corruption, VBP, & Equipment Stimulus
The Summer the Tenders Stopped
In the summer of 2023, hospital administrators across China abruptly froze capital commitments. Beijing had initiated a sweeping healthcare anti-corruption campaign (医疗反腐) scrutinizing institutional kickbacks and capital procurement practices. Equipment tenders ground to a halt, procurement reviews lengthened, and signed contracts sat unexecuted as hospital leadership navigated regulatory audits. By September 2023, multinational peers including Siemens Healthineers, Philips, Elekta, and Intuitive Surgical had all flagged delayed hospital orders in China.69 GE HealthCare soon encountered the same commercial freeze.
The sudden paralysis struck at a vital growth pillar. On its second-quarter 2024 earnings call, management disclosed that China had represented approximately 14% of consolidated revenue the prior year.70 For more than a decade, the country had served as one of the global imaging industry's most dependable engines of volume expansion, propelled by hospital construction and regional diagnostic upgrades.
The Stimulus That Froze Demand
The policy environment shifted again in the spring of 2024, introducing an unexpected counter-incentive. On March 7, 2024, China's State Council issued an action plan promoting large-scale equipment renewal (大规模设备更新). The policy aimed to substantially increase equipment investment across key economic sectors, including healthcare, through 2027, and explicitly directed support for medical institutions to upgrade clinical apparatus.71[^73]
On paper, a state-directed equipment refresh promised a multi-year tailwind for scanner manufacturers. In practice, the announcement froze near-term purchasing. Rather than committing institutional funds, hospital administrators paused procurement tenders to wait for subsidized government funding allocations. The resulting freeze affected the entire sector; even domestic champion United Imaging attributed its 2024 revenue contraction to bureaucratic delays in the disbursement of these equipment renewal funds.66
Myth vs. Reality: Management's China Forecasts
The prevailing investment assumption held that GE HealthCare's geographic diversification, established domestic manufacturing footprint, and premium product tiers would insulate the business from localized Chinese policy disruptions. The operating record throughout 2024 and 2025 demonstrated the limits of that defense.
In February 2024, GEHC guided to approximately 4% consolidated organic revenue growth for the year.4 By the first-quarter earnings call, management acknowledged that sales in China had contracted by roughly 11% year over year, attributing the decline to a demanding comparison against a stimulus-aided first quarter in 2023 alongside anti-corruption scrutiny. Despite that drag, leadership reaffirmed its full-year organic growth outlook.
That posture proved unsustainable. On July 31, 2024, management lowered full-year organic revenue growth guidance to a range of 1% to 2%.70 On the call, leadership quantified the revision as a roughly $500 million top-line headwind in China, citing the "prolonged timing of the rollout of the new stimulus" and guiding investors to anticipate a high-teens decline in regional sales during the second half of the year. In October, executives cautioned that consolidated growth was trending toward the lower bound of that reduced range.72 On that call, management reported that sales in China had fallen 17% year to date and would finish the full year down by high teens, while setting expectations that tangible stimulus funding would remain limited through the first half of 2025. Full-year 2024 organic revenue growth ultimately arrived at 1%.42
When questioned regarding intensifying domestic competition, management acknowledged "a lot of local competition" while emphasizing that GE had manufactured and sourced in China for more than thirty-five years. Yet across the 2024 earnings transcripts reviewed, executives did not identify United Imaging by name or attribute regional contractions to competitive share loss. That framing offers a plausible account of policy timing, but it remains analytically incomplete. While administrative delays explain an industry-wide freeze, they do not explain why the leading domestic rival rebounded to 34% revenue growth in 2025 while GEHC budgeted for another regional contraction in 2026.6773
The premise that GEHC's global reach and premium portfolio insulate it from Chinese policy shocks is contradicted by the 2023–2025 operational record. The company absorbed a deep, sustained retrenchment across a market that had generated roughly a seventh of consolidated sales, and initial management forecasts proved consistently optimistic. The narrower, defensible conclusion is that GEHC can absorb sharp regional contractions without impairing enterprise solvency, as consolidated organic revenue growth recovered to 3.5% in 2025.9 For investors, China must be evaluated not as a compounding growth engine, but as an increasingly volatile, policy-governed replacement market.
That structural shift is accelerating. On the second-quarter 2026 call, management noted that China's centralized volume-based procurement (集中带量采购) framework is expanding into medical equipment tendering. That development signals enduring pricing pressure rather than a cyclical recovery to historical segment margins.
Volume-based procurement alters the commercial landscape in fundamental ways. Rather than individual hospitals negotiating bilateral equipment purchases, a provincial government or hospital consortium aggregates purchasing demand into a single consolidated tender. Manufacturers bid for guaranteed procurement volumes, and the lowest qualifying price typically captures the primary allocation. In pharmaceuticals and medical consumables, VBP rounds have produced steep pricing concessions. For complex diagnostic imaging systems, the tendering process is less standardized, but the direction is evident: fewer, larger, and more price-driven tenders where domestic manufacturers benefit from lower cost structures and state industrial alignment. The forward test for GE HealthCare is whether regional equipment orders can stabilize at acceptable operating margins as volume-based procurement expands, or whether Chinese tenders will permanently dilute equipment profitability.
Every operational factor evaluated thus far—from tender discounting and segment margin divergence to Chinese procurement headwinds—ultimately flows directly into the income statement and cash generation of the standalone enterprise.
XI. Financial Architecture & Capital Allocation Scorecard
A Report Card With Mixed Grades
The standard corporate spin-off playbook follows an established narrative: redundant corporate overhead is eliminated, operational focus unlocks margin expansion, and public markets re-rate the focused pure-play at a premium multiple. GE HealthCare’s initial three years of independence reveal a considerably more complicated trajectory.
In 2023, GEHC delivered 8% organic revenue growth, generating approximately $19.6 billion in sales with an adjusted EBIT margin of 15.1% and free cash flow of roughly $1.7 billion.4 In 2024, organic top-line growth decelerated to 1% as revenue reached $19.7 billion, but standalone productivity initiatives pushed the adjusted EBIT margin up to 16.3%, even as free cash flow drifted down to $1.6 billion.42 In 2025, organic revenue growth recovered to 3.5%, lifting revenue to $20.6 billion. Yet operating profitability reversed: the adjusted EBIT margin contracted by 100 basis points to 15.3%, and free cash flow fell for a second consecutive year to approximately $1.5 billion.9 While organic order intake expanded 5.2% and the book-to-bill ratio reached 1.07—signaling that new bookings outpaced product deliveries—cash generation continued to compress.9
That 2025 margin erosion was exacerbated by external trade policy shocks. Following the escalation of U.S.–China tariffs in April 2025, management lowered adjusted earnings-per-share guidance to a range of $3.90 to $4.10 from its original outlook of $4.61 to $4.75, factoring in an estimated $0.85 per share in tariff-related costs.74 Ultimately, the direct tariff headwind totaled approximately $245 million at the EBIT line and $0.43 per share, enabling adjusted EPS to reach $4.59.973 Just as executives had underestimated the duration of China's procurement freeze in 2024, the April 2025 tariff forecast proved excessively pessimistic. In both instances, the operational takeaway is that GEHC's forecasting mechanisms remain vulnerable to geopolitical and macroeconomic policy shifts beyond corporate control.
The Investor Day Promise
At its Investor Day on November 21, 2024, leadership established medium-term financial targets spanning 2026 through 2028. The framework promised mid-single-digit organic revenue growth of 4% to 6%, an adjusted EBIT margin reaching "high-teens to 20%+", high-single-digit to low-double-digit EPS growth, and free cash flow conversion exceeding 90%.75
Measuring those medium-term commitments against immediate operational guidance reveals an emerging gap. In February 2026, management issued initial full-year guidance forecasting 3% to 4% organic revenue growth and an adjusted EBIT margin of 15.8% to 16.1%.9 Two months later, in April 2026, the company lowered its margin outlook to a range of 15.4% to 15.7% and projected free cash flow of approximately $1.6 billion, pointing to acute cost inflation across memory semiconductors, oil, and global logistics.43 Consequently, entering the first year of its targeted three-year window, GEHC is guiding organic growth below its medium-term corridor and operating margins between two and four percentage points short of the high-teens threshold.
To be sure, those targets were structured across a multi-year horizon rather than an isolated annual reporting period. Commercial order momentum showed notable strength in the second quarter of 2026, posting record organic order growth of 11.1%, a book-to-bill ratio of 1.15, and an order backlog expanding to $23.9 billion.8 That commercial backlog provides tangible support for an operational acceleration in the second half of 2026 and into 2027. Nevertheless, the post-spin financial pattern has been characterized by episodic margin gains followed by subsequent retrenchment, rather than the steady, compounding margin progression contemplated in the Investor Day targets.
Capital Allocation
Capital return to shareholders has expanded incrementally. GEHC initially paid a quarterly dividend of $0.03 per share, raised the payout to $0.035 in early 2025, and on September 23, 2026, announced a further increase to $0.04 per share.7576 Share repurchases commenced in 2025, totaling roughly $200 million for the year, followed by $100 million in repurchases during the first quarter of 2026 and $200 million in the second quarter, leaving $500 million under the existing board authorization.9438
The far more consequential capital allocation decision was the acquisition of Intelerad. Committing $2.3 billion to enterprise software at a time when operating margins were compressing and the corporate balance sheet remained leveraged from the initial separation represents an assertive bet on the company's precision care thesis. While strategic expansion into enterprise software is not inherently unsound, it fundamentally alters the risk profile of management's capital allocation track record: institutional investors will evaluate capital discipline not on modest programmatic tuck-ins like Caption Health or MIM Software, but on whether Intelerad delivers accretive returns on invested capital.
The Balance Sheet After the Spin
GE HealthCare commenced independent trading with approximately $10.2 billion in total debt, an obligation incurred primarily to fund cash and debt-exchange distributions to General Electric.33 Across 2023 and 2024, the enterprise directed free cash flow toward steady deleveraging. However, the $2.3 billion outlay for Intelerad, combined with newly initiated share repurchases, absorbed liquidity that could have accelerated debt paydown. Sustained deleveraging now hinges directly on a recovery in free cash flow, tying balance-sheet flexibility back to operating margin expansion.
Cash conversion represents a quieter, yet more structural, financial indicator. Management's Investor Day framework targeted a free cash flow conversion rate exceeding 90% of adjusted net income.75 Generating approximately $1.5 billion in free cash flow in 2025 against adjusted EPS of $4.59 left cash conversion well below that threshold.9 While tariff expenses and ongoing carve-out restructuring explain a portion of the variance, the shortfall also reflects the intrinsic working capital and capital expenditure requirements of an industrial hardware manufacturer. Until cash conversion approaches the targeted 90% benchmark, describing GEHC as a high-return compounding compounder represents an aspirational target rather than an established operating reality.
The Activist's Memo
Were an activist investor to evaluate GE HealthCare's standalone architecture, the resulting brief would focus on four immediate governance and portfolio questions. First, accelerate the resolution of Patient Care Solutions: with the segment generating operating losses in mid-2026, a separation or structured exit offers the most immediate lever to lift consolidated margins, a path management is already exploring under its strategic review. Second, examine whether Pharmaceutical Diagnostics—delivering operating margins near 30% and organic growth that consistently outpaces the core equipment divisions—is fundamentally mispriced inside a capital-intensive hardware manufacturer, and whether a dedicated carve-out would command a higher valuation multiple. Third, align executive compensation directly with the 2026–2028 Investor Day margin targets, reinforcing accountability after initial annual guidance trailed medium-term commitments. Fourth, mandate transparent financial segmentation for recurring software revenue, Intelerad’s post-acquisition returns, and underlying service contract economics. While no activist has publicly surfaced these demands in disclosures to date, these strategic questions represent the exact operational tensions confronting the board.
With the financial architecture and capital allocation profile established, the final assessment turns to the central investment debate governing the equity.
XII. The Bear vs. Bull Debate & Material Risk Radar
The Bull Case
Demographic expansion provides structural tailwinds for diagnostic volume. An aging global population requires increased imaging surveillance for cardiovascular disease, oncology, stroke, and neurodegenerative disorders. As both a major capital equipment manufacturer and a primary supplier of specialized contrast media, GE HealthCare is positioned to capture recurring economic value across both initial scanner installations and long-term procedure volumes.
Emerging Alzheimer's therapies offer tangible clinical optionality. In July 2023, Leqembi received traditional FDA approval with a prescribing label requiring baseline and periodic magnetic resonance imaging to monitor for amyloid-related imaging abnormalities (ARIA), including brain edema and microhemorrhages.77 Eli Lilly’s Kisunla secured FDA approval in July 2024 for patients with confirmed amyloid pathology, carrying a comparable ARIA monitoring protocol.78 That regulatory expansion followed an October 2023 decision by the Centers for Medicare & Medicaid Services to eliminate its lifetime national coverage restriction on amyloid PET scans, deferring coverage determinations to regional Medicare Administrative Contractors.[^81] Because each candidate requires molecular amyloid confirmation—frequently via PET—followed by serial MRI surveillance, commercial adoption creates compounding demand across GEHC’s scanner fleet, its Vizamyl diagnostic tracer, and icometrix's brain-MRI analysis software. However, because real-world uptake of anti-amyloid therapies has unfolded gradually and blood-based biomarker diagnostics may eventually bypass PET scans for initial screening, this pipeline represents strategic optionality rather than guaranteed near-term revenue.
A growing backlog reinforces commercial revenue visibility. An equipment order backlog reaching $23.9 billion alongside a second-quarter 2026 book-to-bill ratio of 1.15 confirms sustained customer demand, providing tangible operational visibility into product deliveries through late 2026 and into 2027.8
Portfolio rationalization offers an immediate mix benefit. Resolving the strategic review of the loss-making Patient Care Solutions segment while accelerating the high-margin Pharmaceutical Diagnostics franchise systematically tilts enterprise revenue toward higher-margin, recurring cash flows.
The Bear Case
Medium-term operating margin targets appear out of reach. Entering the 2026–2028 Investor Day planning window, adjusted EBIT margins hover near 15% rather than approaching the targeted high-teens threshold. Management's downward revision to full-year 2026 margin guidance underscored structural vulnerability to external input inflation across memory semiconductors, oil, and freight that contractual pricing realization has yet to offset.43
Chinese market headwinds may prove structural rather than cyclical. The combination of domestic procurement preferences (guochandaitai), aggressive tender competition from United Imaging Healthcare, and the expansion of centralized volume-based procurement suggests that regional demand may not return to historical profitability, threatening permanent market share loss and margin compression.
A multi-year commercial deficit in photon-counting CT persists. Siemens Healthineers established a four-year head start with the Naeotom Alpha, accumulating roughly €1 billion in customer orders and entrenching its platform across leading academic medical centers before GEHC secured FDA clearance for its silicon-based Photonova Spectra in early 2026.7
Artificial intelligence capabilities risk rapid commoditization. If foundational computer vision models and vendor-neutral PACS software commoditize basic image reconstruction and feature recognition, GEHC's industry-leading regulatory clearance tally will provide diminishing commercial pricing power in competitive hospital procurement tenders.
Free cash flow conversion continues to weaken. Annual free cash flow drifted down from $1.7 billion in 2023 to $1.5 billion in 2025, with management guiding to approximately $1.6 billion for 2026 despite cumulative top-line revenue expansion—diverging sharply from its targeted 90% conversion benchmark.443
Material Risk Radar
Supply chain and manufacturing concentration. The spring 2022 shutdown in Shanghai demonstrated the acute operational vulnerability of the company's highest-margin franchise. Despite subsequent capital investments in Ireland and Norway, global contrast media and molecular tracer production remains concentrated across a limited number of specialized synthesis and fill-and-finish facilities.
Geopolitical trade volatility and tariff exposure. Direct trade barriers imposed a roughly $245 million headwind on adjusted EBIT in 2025.9 While GEHC recorded $129 million of International Emergency Economic Powers Act (IEEPA) tariff refunds in second-quarter 2026 net income, leadership excluded the item from adjusted operational guidance, underscoring that global trade policy remains an unpredictable earnings variable.8
Executive turnover during an operational transition. The search for a permanent chief financial officer follows Jay Saccaro’s departure in July 2026, leaving interim leadership in the finance office precisely as the board conducts a strategic review of Patient Care Solutions and attempts to restore full-year margin momentum.10
Weighing the Two Cases
Which side does the weight of evidence favor? The bull thesis rests primarily on commercial demand—and clinical demand remains demonstrably robust. Second-quarter 2026 order acceleration, an expanding $23.9 billion backlog, and steady volume growth in Pharmaceutical Diagnostics confirm that healthcare systems continue to acquire advanced imaging hardware and run high daily procedure volumes.
The bear thesis, however, rests on conversion: whether GE HealthCare can translate durable clinical demand into expanding operating margins and superior free cash flow. On that fundamental test, the post-spin operating record remains challenged. Operating margins trail 2024 levels, annual cash generation has drifted downward for three consecutive years, and initial 2026 financial guidance was reduced within months of issuance.
This divergence reveals that the central investment debate is not about the underlying health of the global diagnostic imaging market. Global procedural volumes and machine utilization will expand. The pivotal question is whether GEHC possesses the pricing discipline, operational productivity, and software monetization required to capture that growth at accretive margins—or whether input inflation, tender discounting, tariff volatility, and structural margin degradation in China will continue to dilute earnings.
The debate ultimately centers on operational execution. The history and structural frameworks point to a few durable lessons.
XIII. Playbook: Business & Investing Lessons
1. The Conglomerate Discount Is Real, But Separation Isn't Free
GE HealthCare's standalone trajectory makes a compelling case for corporate focus. For decades, the division's strategic priorities were subordinated to its parent conglomerate's capital requirements—culminating in the distressed sale of its high-margin biopharma franchise to shore up balance-sheet liabilities elsewhere. Yet independence brought its own structural friction: an inherited debt burden, standalone corporate overhead dis-synergies, recurring segment reorganizations, and unrelenting public-market scrutiny. The broader investing lesson is that corporate carve-outs should be evaluated not by the initial autonomy they achieve, but by how capital is deployed once conglomerate support is gone. The opening quarters of an industrial spin-off often flatter operating results as stranded costs are eliminated and standalone productivity programs take effect. The decisive test arrives when programmatic cost cuts run their course and baseline operational leverage must sustain operating margins. For GEHC, that transition is underway.
2. The Installed Base Is the Asset, But Hospitals Keep the Keys
An expansive installed base paired with a dedicated field engineering workforce creates a high-margin recurring cash engine, but customer captivity is never absolute. The 1998 Department of Justice antitrust settlement demonstrated that regulatory authorities can dismantle restrictive diagnostic servicing agreements when manufacturer lock-in overreaches.20 For capital goods manufacturers, durable economic rents stem from field responsiveness, parts availability, and proprietary consumables rather than contractual coercion. Incumbency endures only as long as an equipment manufacturer lowers a hospital's total operational friction; when vendor maintenance becomes an administrative bottleneck, healthcare networks mobilize internal biomedical engineering teams or split fleet procurement tenders across rival suppliers.
3. Clearances Are Not Revenue
Accumulating regulatory authorizations does not equate to commercial software monetization. While GE HealthCare regularly highlights its industry-leading tally of AI-enabled clearances from the Food and Drug Administration, that algorithmic value is predominantly embedded into physical hardware to defend equipment margins rather than commercialized as high-margin, decoupled recurring subscriptions. Furthermore, corporate history offers a cautionary precedent: the division's prior major healthcare IT bet, built around the acquisition of IDX Systems, was ultimately divested at a capital loss.24 The investing takeaway is to measure realized commercial revenue rather than regulatory certificates. A parallel principle applies to hardware innovation: Siemens Healthineers secured commercial clearance for photon-counting CT more than four years ahead of GEHC, converting that technical head start into approximately €700 million in commercial revenue before GEHC's platform even reached the market.7 In capital-intensive medtech, engineering milestones matter only to the extent that they convert into durable customer orders and commercial pricing power.
4. Sovereign Buyers Rewrite the Rules
The sharp retrenchment across China demonstrates how rapidly sovereign purchasing mandates can transform a dependable regional growth engine into a prolonged commercial headwind. When national healthcare policy pivots toward anti-corruption enforcement, centralized volume-based procurement, and explicit domestic substitution (guochandaitai), multinational incumbents lose pricing leverage. Once qualified domestic alternatives achieve clinical parity, institutional tenders tilt toward local manufacturers. Incumbency in state-funded healthcare systems is only as durable as the host government's regulatory framework. Crucially, the competitive dynamic cuts both ways: as Shanghai-based United Imaging Healthcare expanded international sales by 51% in 2025,67 it established that domestic champions will leverage state-backed domestic scale to export price-competitive imaging suites across global emerging markets. Western medical technology incumbents that historically viewed China as a regional end market must now confront it as the home base of a formidable global competitor.
XIV. Epilogue & The Forward Watchlist
The Unfinished Transformation
On September 23, 2026, GEHC raised its quarterly dividend to $0.04 per share.76 It was an incremental gesture, but one that fit the operational moment: a business returning capital modestly while navigating an active strategic review of its patient monitoring division, an interim chief financial officer, a multi-billion-dollar enterprise software integration, and a compressed margin outlook. Standalone GE HealthCare has demonstrated that it can operate independently without conglomerate support. What remains unproven is whether it can achieve the compounding organic growth and premium valuation multiples of an elite medtech pure-play rather than trading like a cyclical capital goods manufacturer.
The Three Numbers That Matter
1. Adjusted EBIT margin. At its 2024 Investor Day, management established a target for adjusted EBIT margins reaching "high-teens to 20%+" by 2028.75 With full-year 2026 guidance lowered to approximately 15.5%,43 operating profitability sits several percentage points below that medium-term corridor. Whether resolving the Patient Care Solutions strategic review, sustaining Pharmaceutical Diagnostics momentum, and extracting returns from Intelerad can bridge that structural gap represents the clearest test of management's operating credibility.
2. Orders and book-to-bill. While second-quarter 2026 commercial bookings demonstrated sharp acceleration, the enterprise requires a sustained book-to-bill ratio comfortably above 1.0 to prove it is systematically defending market share against Siemens Healthineers and United Imaging Healthcare, rather than merely capturing pent-up demand following Chinese procurement freezes and tariff adjustments.
3. PDx organic growth. As the organization's highest-margin and least cyclical operating division, Pharmaceutical Diagnostics functions as the primary catalyst for portfolio mix expansion. If commercial execution across Flyrcado, amyloid-targeting Alzheimer's diagnostic tracers, and the Nihon Medi-Physics platform sustains high-single-digit organic revenue growth, that expansion will carry much of the operational load required to reach consolidated margin targets.
More than a century after William Coolidge calibrated the medical X-ray tube in Schenectady, the enterprise built around his invention confronts an entirely modern control problem: transforming an entrenched, capital-intensive installed base into durable, high-margin growth. The subsequent two years of standalone execution will determine whether GE HealthCare's separation marked a genuine corporate rebirth or merely an exchange of tickers.
References
-
GE Completes Separation of GE HealthCare — General Electric, 2023-01-04 ↩
-
GE HealthCare Technologies Form 8-K on Completion of Separation and Distribution — U.S. SEC EDGAR, 2023-01-04 ↩↩↩↩↩
-
GE Plans to Form Three Public Companies Focused on Growth Sectors of Aviation, Healthcare, and Energy — General Electric, 2021-11-09 ↩↩
-
GE HealthCare Reports Fourth Quarter and Full Year 2023 Financial Results (Form 8-K Exhibit 99) — U.S. SEC EDGAR, 2024-02-06 ↩↩↩↩↩
-
GE HealthCare Technologies 2025 Annual Report on Form 10-K — U.S. SEC EDGAR, 2026-02 ↩↩↩↩↩
-
GE HealthCare Wins FDA Nod for Photon-Counting CT Technology — MedTech Dive, 2026-03 ↩↩↩↩↩↩↩
-
GE HealthCare Reports Second Quarter 2026 Financial Results — GE HealthCare via BioSpace, 2026-07-29 ↩↩↩↩↩↩↩↩↩↩↩
-
GE HealthCare Reports Fourth Quarter and Full Year 2025 Financial Results (Form 8-K Exhibit 99) — U.S. SEC EDGAR, 2026-02-04 ↩↩↩↩↩↩↩↩↩↩↩
-
GE HealthCare CFO Jay Saccaro Steps Down — MedTech Dive, 2026-07-24 ↩↩↩
-
Victor X-Ray Corporation, est. 1893 — Made-in-Chicago Museum ↩↩↩
-
Walter Robb, Former Head of GE Medical Systems, Dies — DOTmed, 2020-03-25 ↩↩
-
SIGNA Returns: SIGNA Creator and SIGNA Explorer Designed for Improved Patient Comfort and Productivity — GE Healthcare via PR Newswire, 2014-12-02 ↩
-
Thomson SA Acquiring General Electric Co.'s Consumer Electronics Business — UPI, 1987-07-23 ↩
-
GE Yokogawa Medical Systems Case Study — Japan Institute for Labour Policy and Training ↩
-
From Startup to Global Brand: A Medical Ultrasound Success — Business Norway ↩
-
GE Medical Systems Completes Merger with Marquette Medical Systems — Med Device Online, 1998-11-24 ↩
-
Justice Department Settles Antitrust Suit Against General Electric Over Medical Equipment Servicing — U.S. Department of Justice, 1998-07-14 ↩↩
-
GE Acquires Amersham for $9.5 Billion in 800p per Share All-Stock Transaction — General Electric, 2003-10-10 ↩↩
-
Amersham plc Form 6-K: Completion of Acquisition by General Electric — U.S. SEC EDGAR, 2004-04-08 ↩
-
IDX Systems Corporation Form 8-K Exhibit 99.1: GE to Acquire IDX — U.S. SEC EDGAR, 2005-09-29 ↩↩
-
Veritas Capital to Acquire Revenue Cycle, Ambulatory Care and Workforce Management Software Unit from GE Healthcare for $1.05 Billion — Veritas Capital, 2018-04-02 ↩↩↩
-
GE Focuses Portfolio for Growth and Shareholder Value Creation — General Electric, 2018-06-26 ↩
-
Flannery Ousted at GE After Less Than 2 Years — WBUR / Associated Press, 2018-10-01 ↩
-
Danaher to Acquire the Biopharma Business of General Electric Life Sciences for $21.4 Billion — Danaher Corporation, 2019-02-25 ↩
-
Danaher Completes Acquisition of the Biopharma Business of General Electric Life Sciences; Business Will Be Called Cytiva — Danaher Corporation, 2020-03-31 ↩
-
GE to Acquire BK Medical, Expanding Ultrasound Portfolio into Surgical Visualization — General Electric via SEC EDGAR, 2021-09-23 ↩
-
GE Healthcare to Buy BK Medical, Eyeing Robotics — MedTech Dive, 2021-09-23 ↩
-
Peter Arduini Named CEO of GE Healthcare — GE Healthcare, 2021-06-24 ↩↩
-
GE Announces Closing of Offering of $8.25 Billion Senior Notes Issued by GE HealthCare — General Electric, 2022-11-22 ↩↩
-
GE HealthCare Information Statement (Form 10, Exhibit 99.1) — U.S. SEC EDGAR, 2022-11 ↩↩
-
GE Completes Sale of Its Remaining Stake of Common Stock of GE HealthCare Technologies — Simpson Thacher & Bartlett, 2024-11-12 ↩
-
GE Announces Board of Directors for Future Independent GE HealthCare — General Electric, 2022-09-12 ↩
-
GE HealthCare Technologies 2026 Proxy Statement (Form DEF 14A) — U.S. SEC EDGAR, 2026-03-18 ↩
-
GE HealthCare Form 8-K: Board Leadership Update — U.S. SEC EDGAR, 2026-05-07 ↩
-
GE HealthCare Appoints Veteran Finance Executive Pascal Desroches to Board of Directors — GE HealthCare via SEC EDGAR, 2026-09-22 ↩
-
GE HealthCare Names James Saccaro Chief Financial Officer (Form 8-K Exhibit 99) — U.S. SEC EDGAR, 2023-05-09 ↩
-
GE HealthCare Form 8-K Exhibit 99: CFO Transition — U.S. SEC EDGAR, 2026-07-23 ↩
-
GE HealthCare Form 8-K: Segment Recast to Advanced Imaging Solutions — StockTitan (SEC filing summary), 2026-07-29 ↩↩
-
GE HealthCare Reports Fourth Quarter and Full Year 2024 Financial Results (Form 8-K Exhibit 99) — U.S. SEC EDGAR, 2025-02-13 ↩↩↩↩↩↩
-
GE HealthCare Reports First Quarter 2026 Financial Results (Form 8-K Exhibit 99) — U.S. SEC EDGAR, 2026-04-29 ↩↩↩↩↩↩↩↩↩
-
FDA Clears AIR Recon DL Deep Learning-Based MR Image Reconstruction Technology from GE Healthcare — Axis Imaging News, 2020-05 ↩
-
GE HealthCare Tops FDA List of AI Authorizations — Imaging Technology News, 2025-07-22 ↩↩
-
GE Healthcare Introduces Sonic DL, FDA-Cleared AI Deep Learning Technology — Imaging Technology News, 2023-06-07 ↩
-
GE HealthCare Unveils Sealed Magnet Platform at ECR — AuntMinnie, 2025-02-26 ↩↩
-
GE HealthCare Secures FDA Clearances for SIGNA MRI Tech — AuntMinnie, 2026-02 ↩
-
GE HealthCare Focuses on Expanding Access to Nuclear Medicine Through AI, Radiopharmaceutical and Imaging Innovations — GE HealthCare, 2026-06-01 ↩
-
FDA Approves GE HealthCare's Flyrcado for Diagnosing Coronary Artery Disease — Pharmaceutical Executive, 2024-09 ↩
-
Rapid Response to the Acute Iodinated Contrast Shortage — Journal of the American College of Radiology (PMC), 2022-05-19 ↩↩
-
GE Healthcare Says Contrast Media Production Back to Full Capacity — MedTech Dive, 2022-06-03 ↩↩
-
GE HealthCare Announces $80 Million Investment to Expand Contrast Media Production Capacity — GE HealthCare, 2022-11-17 ↩
-
GE HealthCare to Invest $138M in Irish Contrast Media Production — MedTech Dive, 2025-02-04 ↩
-
GE HealthCare Prospectus (Form 424B3), Caption Health Acquisition Disclosure — U.S. SEC EDGAR, 2023-04-25 ↩
-
GE HealthCare Quarterly Report (Form 10-Q) for Q2 2024 — U.S. SEC EDGAR, 2024-07 ↩
-
Artificial Intelligence and Machine Learning (AI/ML)-Enabled Medical Devices — U.S. FDA CDRH, 2024-05-13 ↩
-
GE HealthCare Leads FDA's AI-Enabled Device List — DOTmed, 2024-05-24 ↩
-
Siemens Healthineers Receives FDA Clearance for NAEOTOM Alpha, the World's First Photon-Counting CT — Siemens Healthineers, 2021-09-30 ↩
-
Siemens Healthineers IPO Priced at EUR 28.00 per Share — Siemens Healthineers, 2018-03-16 ↩
-
Siemens Healthineers Completes Acquisition of Varian — Imaging Technology News, 2021-04 ↩
-
Siemens Healthineers Q4 and Fiscal Year 2025 Results — Siemens Healthineers, 2025-11-05 ↩
-
Philips Respironics Reaches Agreement with U.S. Government on a Consent Decree — Royal Philips, 2024-04-09 ↩
-
Philips First Quarter Results 2024 — Royal Philips, 2024-04-29 ↩
-
United Imaging Healthcare Announces Listing of Initial Public Offering — PR Newswire, 2022-08-22 ↩
-
联影医疗2024年年报解读 (United Imaging Healthcare 2024 Annual Results) — Sina Finance, 2025-04-29 ↩↩
-
联影医疗2025年业绩 (United Imaging Healthcare 2025 Results) — China Securities Journal, 2026-04-29 ↩↩↩
-
联影医疗市场份额 (United Imaging Healthcare Market Position) — Cailian Press (CLS) ↩
-
Hospital, Lab Equipment Makers Brace for China Demand Slowdown — MedTech Dive, 2023-09-15 ↩
-
GE HealthCare Reports Second Quarter 2024 Financial Results — GE HealthCare, 2024-07-31 ↩↩
-
China Unveils Action Plan for Large-Scale Equipment Renewal and Consumer Goods Trade-Ins — The State Council of the PRC, 2024-03-13 ↩
-
GE HealthCare Reports Third Quarter 2024 Financial Results (Form 8-K Exhibit 99) — U.S. SEC EDGAR, 2024-10-30 ↩
-
GE HealthCare Technologies Q4 2025 Earnings Call Highlights — Yahoo Finance, 2026-02 ↩↩
-
GE HealthCare Reports First Quarter 2025 Financial Results (Form 8-K Exhibit 99) — U.S. SEC EDGAR, 2025-04-30 ↩
-
GE HealthCare Hosts 2024 Investor Day (Form 8-K Exhibit 99) — U.S. SEC EDGAR, 2024-11-21 ↩↩↩↩
-
GE HealthCare Announces Cash Dividend Increase for Third Quarter of 2026 — GE HealthCare via BioSpace, 2026-09-23 ↩↩
-
FDA Grants Traditional Approval for LEQEMBI (lecanemab-irmb) for the Treatment of Alzheimer's Disease — Eisai via PR Newswire, 2023-07-06 ↩
-
FDA Approves Treatment for Adults with Alzheimer's Disease (Kisunla) — U.S. Food and Drug Administration, 2024-07-02 ↩
 LinkedIn
 WhatsApp
 Reddit
 Hacker News
 Email
 Kindle
 RSS Feed
 Spotify
 Apple Podcasts
 Amazon Music
 Audible
 YouTube