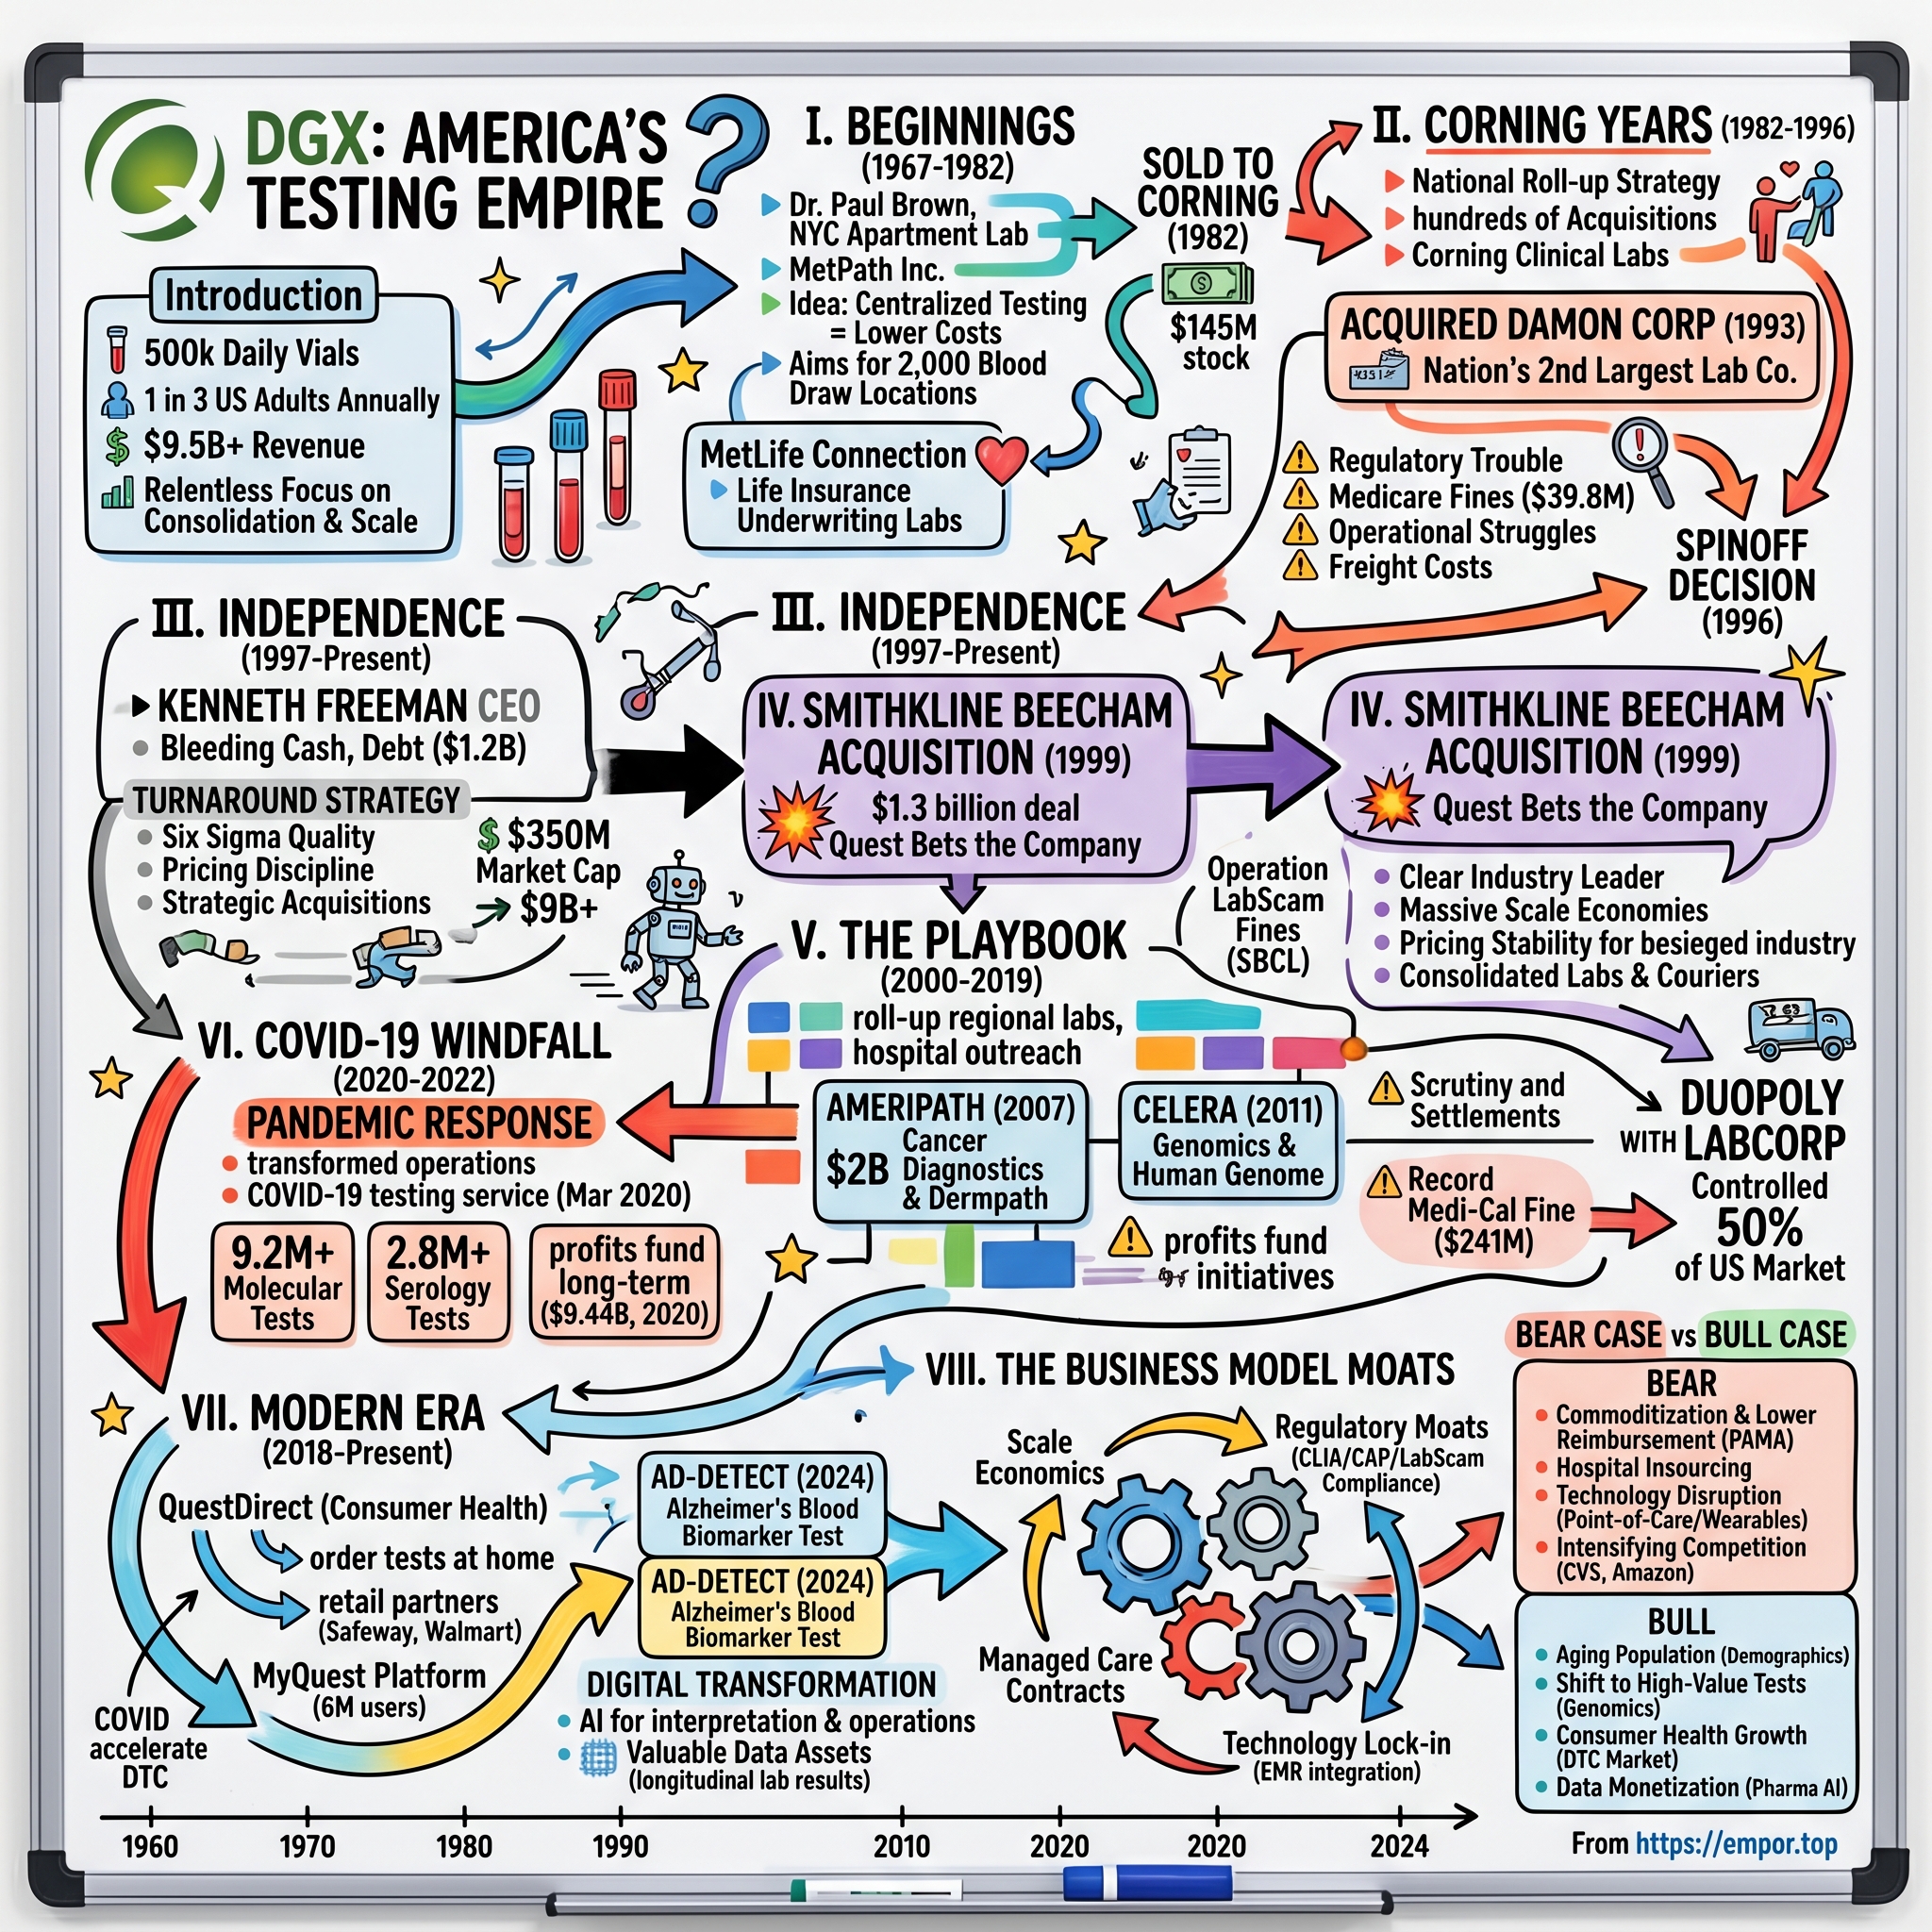
Quest Diagnostics: The Testing Machine That Outlasted the Pandemic
I. Cold Open & Roadmap (8-10 min)
Somewhere in America, right now, a phlebotomist is tying a tourniquet around an arm. It is an utterly forgettable moment — the small talk, the alcohol swab, the pinch, the vial rocking gently in a gloved hand. Multiply that moment by the population of a mid-sized country and you have the business of Quest Diagnostics.
The company's own description of its reach is worth sitting with. In its 2025 annual report, Quest states that it serves approximately one-third of the adult population of the United States each year, and roughly half over any three-year span, through a network of about 2,400 patient service centers staffed by some 25,000 phlebotomists and other clinical personnel.1 That is not a marketing metric. It is a description of infrastructure — a physical logistics network of couriers, drop boxes, refrigerated vans and automated laboratories that moves biological material from arms to answers, at scale, every day, in a country that has never quite decided whether healthcare is a market or a utility.
Quest and Labcorp Holdings between them form the closest thing American diagnostics has to a duopoly. Labcorp's full-year 2025 revenue was $13.95 billion, of which its Diagnostics Laboratories segment — the part that competes directly with Quest — represented a bit over three-quarters, putting the two companies within shouting distance of each other on core lab revenue.2 Quest's own 2025 revenue was $11.04 billion.3 In a $100 billion-plus U.S. clinical lab market where roughly half of all testing still happens inside hospitals, these two independents dominate the outsourced pool and command an outsized share of the higher-value esoteric work that hospital labs cannot economically run themselves.
Here is the hook. Quest began in April 1967 as Metropolitan Pathology Laboratory — MetPath — founded by a pathologist named Paul Brown in a two-bedroom Manhattan apartment, where Pap smear slides were reportedly stained in the bathtub.4 Fifty-nine years later, the company just posted its largest revenue year in history. And it did so three full years after the pandemic windfall that once made it look like a growth stock had completely evaporated.
That round-trip is the tension this story exists to resolve. In 2021, COVID-19 testing pushed Quest's revenue to $10.79 billion and reported diluted EPS to $15.55 — numbers that looked, at the time, like a step-change.5 Two years later, revenue had fallen to $9.25 billion and reported diluted EPS to $7.49 — a better-than-50% collapse in reported earnings from a peak the company itself had warned was temporary.6 By 2025, revenue had not only recovered but exceeded the COVID peak; by mid-2026, management was guiding to $11.95–$12.05 billion for the full year after raising its outlook twice.7
So the question is not whether Quest recovered. It plainly did. The question is what the recovery is made of. Because the growth engine that got Quest back above its pandemic high is not the same engine that produced the pandemic high. It is built from health-system joint ventures, a dialysis-testing asset purchase, a Canadian acquisition, a fast-growing but still-small consumer channel, and a portfolio of advanced diagnostics — Alzheimer's blood biomarkers, cardiometabolic panels, a minimal-residual-disease liquid biopsy — that ranges from genuinely material to genuinely unproven. Some of that growth is high quality. Some of it, by management's own arithmetic, comes in at margins below the company average and dilutes the mix while it ramps.
This piece works through that stack in order: how the duopoly was built, what Quest's capital allocation record actually shows when you check the deals rather than the narrative, what the COVID years did and did not prove, where the moat is real and where management itself says it is thin, and which one or two numbers actually matter for tracking whether the current story holds.
Start with how a bathtub in Manhattan became half of a national duopoly.
 Subscribe on LinkedIn
II. Origins, Compressed: MetPath to Independent Company (1967-1999) (12-15 min, deliberately brief)
Paul Brown's insight in 1967 was mundane and correct: hospitals in the New York area needed better pathology than they could produce themselves, and someone willing to specialize could do it more accurately and more cheaply.4 That is, in one sentence, the entire economic logic of the reference laboratory industry, and it has not changed in six decades. Everything that follows is a story about scale — who could aggregate the most specimens onto the most automated instruments across the densest courier routes.
MetPath grew inside the orbit of large institutional capital rather than as a scrappy independent. Corning Glass Works acquired the business in 1982 and then did the thing that industrial conglomerates did in that era: it rolled up hundreds of local and regional laboratories to assemble a national reference network.4 For fourteen years, the lab business sat inside a company better known for Pyrex and optical fiber, funded through cycles that had nothing to do with healthcare. Then, on the last day of 1996, Corning spun it out as an independent public company under a new name: Quest Diagnostics.4
Independence arrived at an awkward moment. The clinical laboratory industry of the early-to-mid 1990s had a fraud problem that was not incidental but structural. The billing model — labs bundling extra tests into panels that physicians ordered without understanding the reimbursement consequences — invited abuse, and the Justice Department went after it systematically under an initiative known as Operation LabScam. Corning's own laboratory arm was directly implicated: in October 1996, Damon Clinical Laboratories, a wholly owned Corning subsidiary, pleaded guilty to conspiracy to defraud the government and paid $119 million — a $35.3 million criminal fine plus $83.7 million in civil settlement — for billing Medicare and other federal programs for tests that were neither ordered nor medically necessary between 1988 and 1993. Damon was permanently barred from federal health programs.8
This is the origin of the modern compliance function at Quest, and it is worth stating plainly rather than skipping: the company was spun out of a corporate parent whose lab subsidiary had just pleaded guilty to healthcare fraud, weeks before the spin-off completed. Kenneth Freeman, who took the helm at separation, inherited a business that needed operational integration, a cleaned-up billing culture, and a way to grow in an industry where the regulator had just demonstrated it would criminally prosecute the incumbents.
Then came the deal that made the modern industry. In February 1999, Quest agreed to acquire SmithKline Beecham Clinical Laboratories, one of the three largest independent labs in the country, with 1998 revenues of $1.6 billion — more than Quest itself. The transaction closed on August 16, 1999 for approximately $1.3 billion, paid with $1.025 billion of cash and roughly 12.6 million Quest shares, leaving SmithKline Beecham holding about 29.5% of the combined company.9
It is hard to overstate how much of today's industry structure traces to that single transaction. Before it, Quest was a strong regional operator; after it, the U.S. independent laboratory market had two national players of comparable scale, and the third tier never caught up. Everything downstream — the ability to sit across the table from national health plans as an in-network necessity rather than a supplicant, the leverage in payer contracting, the political weight to fight Medicare rate-setting for two decades — flows from being one of two rather than one of five.
There is a delicious irony in the deal that deserves a footnote in the compliance story. SBCL itself had, two years before the acquisition, entered what Attorney General Janet Reno described on February 24, 1997 as the second-largest healthcare fraud settlement in history: $325 million, also arising from LabScam-era billing practices.10 Quest bought scale, and it bought a business that had just written the government a nine-figure check for the same category of conduct that had already cost its own parent $119 million. The compliance apparatus that Quest built in the years after 1999 was not corporate virtue-signalling; it was the price of assembling a national network out of two organizations that had both been caught.
The investor takeaway from this compressed history is narrow but load-bearing. Quest's advantage was never invented in a lab. It was assembled through acquisition, and the durable part of it — density of collection points, courier routes, and payer contracts — is physical and contractual rather than technological. That distinction matters enormously when you get to the 2020s and start asking whether a genomics platform or an oncology assay can be bolted onto the same machine and produce the same returns.
Which brings us to the era when Quest tried exactly that.
III. The Consolidation Playbook and Its First Big Miss: AmeriPath (2000-2019) (30-35 min)
If you want to understand why a lab company is worth more than the sum of its instruments, follow a courier van.
A phlebotomist draws blood in a strip-mall patient service center in suburban Phoenix. A driver on a fixed route collects specimens from that center and eleven others, plus forty physician offices, and delivers them to a rapid-response lab by evening. The esoteric work goes onward, overnight, to a regional or national facility with mass spectrometers and sequencers that cost more than the entire strip-mall operation. The marginal cost of adding the forty-first physician office to that route is close to nothing. The marginal cost of a new entrant building the route from scratch is enormous.
That is route density, and it is the least glamorous and most real competitive advantage in this industry. It is also why Quest's playbook for two decades was arithmetic rather than invention: buy the specimens, put them on the existing van, run them on the existing instrument, and let the fixed-cost absorption do the work.
The clean example was Unilab. In April 2002, Quest agreed to acquire Unilab Corporation — the largest independent clinical lab in California, with 2001 revenues of $390 million, three full-service labs, 39 rapid-response labs and 386 patient service centers — in a transaction valued at $1.1 billion including roughly $200 million of Unilab debt, paid mostly in Quest stock.11 California was the one large state where Quest lacked depth. Buying the leading independent there was not a technology bet or a diversification; it was the purchase of density in a geography, at a price of a bit under three times revenue, into a cost structure that could absorb it. Alongside Unilab, Quest tucked in dozens of smaller regional labs and hospital outreach books over the decade — each one a few more stops on an existing route.
Then came the deal that tests whether the playbook travels.
The AmeriPath problem
On April 16, 2007, Quest announced it would acquire AmeriPath Group Holdings in an all-cash transaction valued at approximately $2 billion, including about $770 million of debt assumed at closing. AmeriPath carried annualized revenues exceeding $800 million and consisted of a large anatomic pathology practice, a dermatopathology franchise (Dermpath Diagnostics, with 80-plus dermatopathologists reading some 2.4 million biopsies a year), and Specialty Laboratories, an esoteric testing business. Quest's leadership framed it as establishing "our leading position in cancer diagnostics," in what management described as two of the fastest-growing segments in diagnostic testing.1213
The seller was Welsh, Carson, Anderson & Stowe. The private equity firm had taken AmeriPath private in 2003 in a deal whose equity value was $627 million and whose enterprise value was roughly $839 million including debt.14 Four years later it exited at $2 billion. Trade press at the time characterized it, accurately, as Welsh Carson doubling its money.14
Set aside the emotional reaction to a sponsor flip for a moment and look at what Quest was actually buying: professional-services revenue. Anatomic pathology is not a high-throughput automated assay. It is a pathologist, a microscope, and a professional judgment, billed under Medicare's physician fee schedule and its technical-component rules. That is a fundamentally different economic animal from a chemistry panel running on an automated analyzer. It has limited operating leverage — you cannot double the biopsies read without roughly doubling the pathologists — and its reimbursement was set by a payer that spent the following decade methodically reducing what it paid for pathology and dermatopathology services.
The timing compounds the problem. Quest closed a $2 billion, largely debt-funded acquisition in mid-2007, on the eve of a financial crisis, into a category whose price curve was about to bend the wrong way for a decade.
Now the honest part, because this is where a lazy version of the story would overreach. The claim that Quest "overpaid" for AmeriPath is well supported on price: the same asset traded at roughly a third of the value four years earlier, in a business with structurally weaker operating leverage than Quest's core, immediately before a Medicare reimbursement environment that ground pathology economics lower. But price criticism is not the same as demonstrated loss. A review of Quest's annual filings in the years that followed does not surface an AmeriPath-specific goodwill impairment charge; the acquired business was folded into the broader Diagnostic Information Services reporting unit, where it stopped being separately visible. Absence of a write-down in a reporting unit that large is weak evidence either way — a shrinking sub-business inside a growing unit will not trigger an impairment test on its own.
The calibrated conclusion: the record supports "Quest paid a full private-equity exit price for a business with worse operating leverage than its core, entering a decade of adverse reimbursement." The record does not support "Quest formally wrote the deal down." Treat the overpayment claim as plausible on price and unproven on realized loss — and note the more useful forward-looking lesson, which is that Quest's core cost advantage does not automatically transfer to acquired businesses that are professional-services-shaped rather than throughput-shaped.
Celera, and the conversion problem
Four years later, Quest tried the other kind of deal. On May 17, 2011, it completed the acquisition of Celera Corporation — the company descended from the genome-race era — for $671 million, or roughly $344 million net of Celera's cash and short-term investments, at $8.00 per share.15 The stated logic was a pipeline: genetic tests and biomarkers in cardiovascular disease and cancer.
The interesting thing about Celera in 2026 is how little there is to say about it. It never became a named, sized growth line in Quest's subsequent disclosure. Its assets were absorbed; some products persisted; the "platform" framing did not produce a business the company chose to quantify for investors. That is not a scandal — plenty of acquisitions get absorbed — but it is a data point about a specific capability, and it is the most relevant historical evidence available when assessing Quest's newer platform bets. When a company tells you it has acquired a technology platform that will become a growth driver, the honest question is: what happened the last time?
For Quest, the answer across the 2007-2011 window is: the density deals worked and stayed visible; the platform deals were absorbed and stopped being discussed. That is not a base rate of zero, but it is not a base rate that justifies paying up for optionality either.
The quiet 2018 seed
One more thing happened in this era that mattered far more later than it did at the time. On November 7, 2018, Quest launched QuestDirect, a consumer-initiated testing service that let people order lab tests for themselves — more than 35 tests and panels at launch, available in 48 states, accessible through the MyQuest patient app that already had six million users.16
In 2018, this was a curiosity. It was two years before COVID normalized ordering your own test, and roughly seven years before the business became large enough for management to size publicly. Flag it here; it pays off in Section VII, and the length of that gestation is itself the most useful thing about it.
The pattern across this entire era is consistent enough to be predictive. Quest is very good at buying specimen volume and running it cheaper than the seller could. It is unproven at buying technology and turning it into disclosed revenue. Hold that distinction, because the pandemic was about to hand the company more cash than it had ever generated, and the question of what it would do with that cash was about to become the whole story.
IV. The COVID Round-Trip: Windfall, Denominator Effect, and the Base-Business Question (2020-2023) (35-40 min)
In March 2020, the least glamorous corner of American healthcare became, briefly, the most important one. Governors held press conferences about swab supply. Cable news chyrons carried testing capacity numbers. The nasopharyngeal PCR test — a molecular assay of the sort Quest had been running quietly for years — became a national political object.
Quest scaled into it hard. And for two years, the financial results looked like a different company.
Revenue reached $9.44 billion in 2020 and then $10.79 billion in 2021, a 14% increase on top of a year that had itself been extraordinary.5 Reported diluted EPS went from $10.47 in 2020 to $15.55 in 2021.5 In 2021 alone, COVID-19 testing generated $2.77 billion of revenue.17 Return on equity in 2021 approached 31%, more than double the level the business would settle back to. It was, on paper, one of the great operating windfalls in large-cap healthcare.
Then the denominator came for it.
COVID testing revenue fell to $1.45 billion in 2022, a 47.5% decline, and total revenue slipped to $9.88 billion with reported diluted EPS of $7.97 — down 48.7% year over year.17 Management's own 2023 guidance called for COVID testing revenue of $175 million to $275 million, an 81-88% further decline, and warned that total revenue would drop again.17 It did: full-year 2023 revenue was $9.25 billion and reported diluted EPS was $7.49.6 The daily testing volumes told the same story in physical terms — from roughly 60,000 COVID tests a day at the peak down toward the high teens of thousands within about a year, a collapse that forced repeated guidance resets through 2022 and 2023.18
From peak to trough, reported diluted EPS fell from $15.55 to $7.49 in two years. That is a more than 50% decline in reported earnings, and it happened not because the company failed but because the thing that produced the earnings stopped existing.
Testing the "COVID proved out the platform" claim
The bullish framing of this period, which Quest and its peers both used, is that the pandemic proved the strategic value of a national laboratory network capable of pandemic-scale response. Test that claim against the company's own numbers.
As a capability statement, it holds up and deserves credit. Quest built molecular testing capacity from a standing start to tens of thousands of tests a day, managed a global reagent and swab supply chain under conditions where every buyer in the world was competing for the same inputs, and stood up serology alongside PCR. The cash that capability generated funded real, durable things: laboratory automation, front-end specimen-processing systems, and digital infrastructure that still shows up in the productivity commentary five years later.
As a revenue statement, it fails almost completely. The COVID revenue was non-recurring in nearly its entirety. The testing market was not structurally repriced; it did not become permanently larger; Quest did not emerge with a higher-priced base business. The peak-to-trough EPS round-trip is the disconfirming evidence, and it is dispositive. Anyone modelling Quest today should treat 2020-2021 as an exogenous volume event that funded capex, not as a demonstration that the addressable market permanently expanded.
The narrower, surviving version of the claim is worth keeping: surge capability is real, it was paid for by the surge itself, and it is an asset in the next public-health event. That is a strategic option, not an earnings line.
A CEO change at the bottom, not the top
Leadership turned over in the middle of the unwind, and the timing matters for how you judge the current management team.
On February 3, 2022, Quest announced a succession plan: Steve Rusckowski, chief executive for more than a decade, would hand the CEO role to James E. Davis, an internal executive who had run the bulk of the company's general diagnostics revenue.19 Davis became CEO on November 1, 2022, and the board elected him Chairman effective April 1, 2023.20
Note where in the cycle that happened. Davis did not take over at the 2021 peak and preside over a decline. He took over at the trough — into a year in which the company had just told investors that COVID revenue would fall another 80%-plus and total revenue would decline for the second consecutive year. Whatever one concludes about the Davis era, the fair baseline for measuring it starts in late 2022, not 2021. That cuts both ways: it removes the unfair charge that he destroyed the COVID earnings, and it removes the flattering optical benefit of comparing 2026 revenue to a 2023 trough that he inherited rather than created.
The AMCA breach: the vendor-risk precedent nobody should skip
One event from just before this window deserves space here, because it is the company's live precedent on the exact risk category its current strategy leans into hardest.
Between August 1, 2018 and March 30, 2019, the web payment page of American Medical Collection Agency — a third-party billing collections vendor used by Quest's revenue cycle partner — was compromised. Quest disclosed in June 2019 that information on approximately 11.9 million of its patients had been present on the affected AMCA system, including personal data, certain financial data, Social Security numbers and medical information, though not laboratory test results.2122 The resulting class actions were consolidated into multidistrict litigation in the District of New Jersey.21 AMCA itself, the vendor at the center of it, later reached a settlement with a coalition of state attorneys general that included a $21 million payment — largely suspended based on the company's financial condition — and mandatory security remediation obligations.23
Two things follow. First, the breach happened at a vendor, not inside Quest's own systems, which is precisely the failure mode that scales badly as a company adds partners: every wellness platform, wearable integration, EHR connector and billing intermediary is another edge on the attack surface. Second, Quest's forward strategy — consumer-initiated testing, biological-age scoring with third parties, AI tools trained on lab data, an order-to-cash systems rebuild — multiplies exactly that class of dependency. This is not a reason to dismiss the strategy. It is a reason to treat "Quest is a trusted custodian of health data" as a claim with a documented nine-figure-patient counterexample in its recent past, rather than an assumption.
With the pandemic accounting settled and a new CEO in place at the bottom of the cycle, the relevant question becomes structural: what is this business, actually, and where does its advantage come from?
V. Core Business Deep Dive: Industry Structure, the Duopoly, and How Quest Actually Wins (45-55 min — the deepest section, sized to ~95%+ of revenue and profit)
Here is the most important slide Quest does not need to make: there isn't a segment breakdown to argue about.
Quest reports essentially one business — Diagnostic Information Services — and it is approximately the entire company. Of $11.04 billion in 2025 revenue, DIS accounted for effectively all of it, spanning routine clinical testing, gene-based and esoteric testing, anatomic pathology, and risk-assessment services for life insurers.13 In the second quarter of 2026, DIS revenue grew 10.3% against consolidated growth of 10.2% — the two numbers are the same number.24
This is not a conglomerate. There is no other engine, no financial arm, no software subsidiary quietly carrying the multiple. Nearly the entire investment case rides on the economics of running clinical tests in the United States and, since 2024, Canada. That concentration is a feature for analytical clarity and a risk for everything else.
What the industry actually looks like
Picture the market as a barbell. At one end sit the hospitals: roughly half of U.S. clinical laboratory testing is performed inside hospital-affiliated or single-ownership labs, largely for their own inpatients and outpatients. These labs are not run to maximize lab profit; they are run because a hospital needs stat results at 3 a.m. and because a lab is part of what a hospital is. At the other end sit the independents, where Quest and Labcorp are dominant, and where the specimens that hospitals choose not to run — the low-volume esoteric assays, the send-outs, the outreach book serving community physicians — accumulate.
In between is a long tail of regional independents, physician-office labs and specialty niche players, some of which get acquired every year by the two majors.
The strategically interesting part is the flow between the two ends of the barbell. Hospitals under financial pressure increasingly decide that running a full-service laboratory is a use of capital and workforce they would rather redeploy. When they do, they either sell their outreach book, outsource reference testing, or hand over lab management entirely. Every one of those transactions moves volume from the hospital end of the barbell to the independent end. Quest's hospital channel grew at a double-digit rate in the second quarter of 2026, and on the earnings call Davis described three distinct routes into hospitals — reference testing, collaborative lab management arrangements, and outright outreach acquisitions — with reference testing and same-store collaborative volumes each growing at mid-single digits.24 That is the pipeline, and it is genuinely more attractive when hospitals are financially strained.
Porter's Five Forces, applied honestly
Buyer power: high, and structurally rising. Quest sells to two kinds of buyer with real leverage. Commercial health plans decide network inclusion for tens of millions of covered lives; being out-of-network with a national payer is close to an existential event for a lab. And Medicare simply sets its own price administratively through the Clinical Laboratory Fee Schedule. There is no version of this industry where the seller dictates terms.
Supplier power: low. Reagents, analyzers and consumables are multi-sourced across Roche, Abbott, Siemens Healthineers, Beckman and others. Quest is a large enough buyer to run competitive processes. The one place supplier power creeps in is at the technology frontier: when a single vendor holds an FDA clearance that no one else has, Quest becomes a distributor of someone else's assay rather than the owner of its own — a dynamic visible in its Alzheimer's portfolio, discussed in Section VII.
Rivalry: a stable duopoly, not a price war. Quest and Labcorp compete hard for hospital reference contracts and payer network positions but have not engaged in the kind of destructive price competition that would wreck both. Evidence from the Q2 2026 call: CFO Sam Samad described hospital reference-lab pricing as "slightly negative" in what he called "a competitive sector," while health plan renewals ran "flat to slightly positive," netting to roughly flat overall unit pricing.24 That is the signature of disciplined rivalry — pressure at the contested edges, stability in aggregate.
New entrants: genuinely hard. Replicating a national courier network, 2,400 collection sites, CLIA-certified high-complexity labs, and in-network status with every major payer is a multi-billion-dollar, multi-year, heavily regulated undertaking with no obvious way to earn a return during the build. This is the one force that clearly favors the incumbents.
Substitutes: the real threat. Not a new Quest — a different way of getting the answer. Hospital systems insourcing rather than outsourcing. Payers building or buying their own lab capacity. Point-of-care analyzers in physician offices. At-home collection kits. None of these takes the whole market; each of them takes a slice at the margin, and margins are where this business lives.
7 Powers: where the moat is, and where management says it isn't
Run Hamilton Helmer's framework across Quest and two powers survive contact with the evidence.
Scale economies are the foundation. Fixed costs — instruments, laboratory real estate, courier routes, IT, the compliance apparatus — are spread across an enormous specimen base. This is why the incremental specimen is so profitable and why acquiring volume works. It is also why Quest can run a productivity program like Invigorate targeting 3% in annual cost savings year after year and actually deliver it.24
Process power / switching costs are the subtler one, and they are real in the core. When a physician practice orders through Quest, it is not just choosing a vendor. Quest's ordering system is integrated into the practice's electronic health record; the courier arrives at a known time; the staff know the requisition workflow; results flow back into the chart in a known format. Quest has been layering on top of that — an IntelliDraw tool that walks physician office staff through specimen collection, an AI Companion built on Google Gemini that translates biomarker results into plain language for patients and which had been engaged roughly 350,000 times through the MyQuest app within a quarter of launch.25 Each of these raises the cost of switching a little, not because the test is different but because the workflow is.
Now the disconfirming evidence, and it comes from the CEO himself. Asked on the July 2026 call about ramping Haystack MRD volumes after New York State approval, Davis said Quest is "pacing our commercial investments, and we're pacing the growth of tests that we're doing commensurate with reimbursement. We don't want to get too far out in front of ourselves. We don't need to get too far out in front of ourselves because the switching costs are next to nothing, a clinician can switch."24
That is as clean a bound on the moat as an investor could ask for, delivered by the person with the most incentive to overstate it. In the integrated core — routine testing ordered through embedded workflows — switching costs are meaningful. In newer, standalone, specialist-ordered test categories, they are approximately zero, and competitive position depends on assay performance, clinical evidence and reimbursement rather than on incumbency. Any thesis that extends the core moat to the growth categories is extending it further than management itself does.
There is no branding power here worth naming, no network economy in the technical sense, and no cornered resource. The advantage is scale plus workflow friction, applied to a physical logistics problem. That is a real advantage. It is not an expanding one.
PAMA: the pricing risk with a date on it
The single most consequential external variable for Quest has a name, a mechanism, and a calendar.
The Protecting Access to Medicare Act of 2014 was designed to replace administratively set Medicare lab rates with market-based ones. The mechanism: labs report the prices private payers actually pay them, CMS computes a weighted median, and Medicare pays that. The design flaw: the reporting obligation, as originally implemented, effectively captured only a narrow slice of the market. On the Q2 2026 call Davis noted that in the previous cycle only about 1% of roughly 10,000 labs submitted data, producing what he called "a very, very biased statistical sample of actual laboratory market-based pricing."24
The consequences were not theoretical. The first three rounds of cuts, executed in 2018, 2019 and 2020, saved the government roughly $4 billion over three years against an original ten-year savings estimate of about $2.5 billion — a cut that overshot its own design target by a wide margin, in Davis's telling.24 Congress has delayed further cuts six times.
Where it stands now: a fresh CMS data collection cycle closed July 31, 2026, and Quest submitted. Management expects CMS to report out in "late September, early October" 2026 — which is to say, essentially now.24 Davis laid out three scenarios on the call with unusual specificity. One: CMS proceeds and new rates take effect January 1, 2027. Two: Congress passes the RESULTS Act, which Quest and its trade association have been lobbying for since its introduction in September 2025; it had over 115 cosponsors and had cleared a House Energy and Commerce hearing but still required markup, a CBO score and a CMS technical assessment. Under that bill, rates stay flat for 2027 and 2028, a 2027 data collection feeds new rates in 2029, and future cuts are capped at 5% per year, with a third party collecting adjudicated claims to build a genuinely representative sample. Three: neither happens and the industry pushes for a seventh delay.24
This deserves to be understood as a near-term, binary-ish catalyst rather than a generic risk-factor bullet. Quest's 2025 annual report describes the 2018-2020 PAMA reductions and the pending RESULTS Act legislation as live items.1 An investor watching this company between now and January 2027 should treat the CMS announcement and the fate of the RESULTS Act as the highest-information events on the calendar.
The LDT rule: an overhang that lifted, and could come back
The other regulatory thread ran the opposite direction, and it is genuinely good news for Quest that deserves to be named as such — and then qualified.
In 2024, the FDA finalized a rule asserting authority to regulate laboratory-developed tests as medical devices. LDTs are assays a lab designs, validates and runs itself rather than buying as a kitted product; roughly 80,000 were estimated to be in use, and they are the backbone of esoteric and advanced diagnostics — including, at Quest, its own multi-biomarker Alzheimer's panel and the Haystack MRD assay. Bringing them all through device-style premarket review would have been an existential cost and timing shock to the category.
On March 31, 2025, a federal judge in the Eastern District of Texas vacated the rule in its entirety, holding that the FDA lacked statutory authority because laboratory-developed testing services are professional medical services rather than tangible devices — an outcome shaped by the Supreme Court's Loper Bright decision curtailing deference to agency interpretation.26 The FDA declined to appeal, and in September 2025 issued a rule formally restoring the pre-2024 definition, ending a decades-long effort to extend oversight.27
The consequence for Quest is concrete: the regulatory path for its advanced-diagnostics pipeline runs through CLIA and state programs such as New York's, not through FDA premarket review. That materially de-risks the Haystack and AD-Detect roadmaps.
The qualification matters just as much. This was a judicial vacatur and an agency retreat, not a statute. Congress has repeatedly considered LDT legislation and could pass it. A different administration could attempt a differently constructed rule. Framing the LDT outcome as a permanent settlement would be exactly the kind of absolute verdict the evidence does not support. It is a reversible political and legal outcome that currently favors Quest.
The competitive scoreboard
The duopoly framing survives inspection. As of early September 2026, Quest and Labcorp carry broadly comparable market capitalizations in the mid-$20 billions, and on the core lab business their revenue bases are within roughly a billion dollars of one another.23 Labcorp is the more diversified of the two, carrying a substantial biopharma laboratory services business alongside diagnostics; Quest is the purer-play clinical testing asset. Neither is a laggard. Neither has the other on the ropes.
For multiple and margin context, investors often reach for adjacent names — ICON and Medpace on the contract-research side, Illumina as the sequencing-technology supplier whose cost curve determines what genomic testing costs everyone. Illumina is the more interesting comparison, because it is simultaneously an input supplier and a potential disruptor: falling sequencing costs enlarge the addressable market for genomic assays, but they also lower the barrier for a specialist competitor to enter a specific test category — precisely the category where Davis says switching costs are next to nothing.
The picture that emerges is a business with a real, physical, hard-to-replicate advantage in the routine core; roughly flat pricing that is defended rather than expanded; a stable competitive structure; and its most important variable set by a federal agency on a calendar the company does not control. Which raises the natural next question: given that, what has management been doing with the money?
VI. Capital Deployment Since the COVID Trough: Building the Next Growth Layer (2023-2026) (35-40 min)
Every capital allocator eventually faces the same fork, and Quest hit it in 2023. Revenue was falling for the second consecutive year. The COVID cash was in the bank. The core business was growing but not fast. A new CEO, four months into the job, had to decide what the next decade would be built out of.
The answer, in retrospect, was: buy volume, buy geography, and take one option on technology. Then lever up to do it.
The technology option: Haystack Oncology
In April 2023, Quest agreed to acquire Haystack Oncology, an early-stage company with a tumor-informed minimal residual disease test, for approximately $300 million in cash at closing plus up to $150 million contingent on performance milestones.28 The deal closed on June 20-21, 2023; Quest's filings record it as a $392 million all-cash transaction net of cash acquired — $304 million of cash consideration plus contingent consideration initially valued at $88 million.29
Worth explaining what MRD testing actually is, because the term obscures a genuinely elegant idea. When a tumor is removed, the clinical question is whether any cancer cells remain. Imaging cannot see a handful of cells. A tumor-informed MRD test sequences the patient's own tumor first, builds a personalized fingerprint of its mutations, and then goes hunting for those exact mutations in the bloodstream — circulating tumor DNA shed by any residual disease. Because it knows precisely what to look for, it can detect at concentrations measured in parts per million. In plain terms: instead of scanning the whole haystack for anything needle-shaped, you photograph your specific needle first and then look only for that.
The clinical promise is real. The commercial reality, three years in, is that Quest has not disclosed Haystack revenue.
What it has disclosed is milestones. In the second quarter of 2026, New York State approved the tumor-informed assay — a rigorous review process that, per Davis, only one other company had cleared for a tumor-informed solid-tumor ctDNA MRD test — which opened commercial access across all fifty states.24 Quest also became the largest reference laboratory to offer cancer tests through Flatiron Health's Onco EMR molecular profiling integration, starting with a pilot at American Oncology Network and a planned rollout to Flatiron's roughly 4,700 clinicians later in 2026.24 Earlier in the year, Quest announced a research collaboration with City of Hope to study Haystack MRD in recurrence monitoring across 14 U.S. sites.25 Reimbursement is the gating item: Quest sits in the Novitas Medicare Administrative Contractor jurisdiction and has submitted to MolDx, with coverage hoped for in the back half of 2026.24
Hold the certification-is-not-commercialization line here. A state approval, an EHR integration and a research collaboration are three things a company does before it has revenue, not evidence that it has revenue. And Quest's own management has said as much: it is deliberately pacing commercial investment to reimbursement and explicitly does not want to run ahead of it.24 That is disciplined behavior and should be credited as such. It is also, unambiguously, a statement that this is still a technical-milestone story.
Set that against Celera. Quest has bought a technology platform before, framed it as a growth driver, and then absorbed it without it ever becoming a named revenue line. That history does not condemn Haystack — the assay is demonstrably differentiated in a way Celera's asset arguably was not, the regulatory path just got materially easier with the LDT vacatur, and management's caution about switching costs suggests clear-eyed internal assessment. But it does set the burden of proof. The revised, defensible version of the Haystack claim is: a credible technical asset in a large category, with the commercialization step — the step Quest has historically been weakest at — still entirely ahead of it. The falsifier is specific: disclosed, sized Haystack revenue within roughly 12-18 months of the New York approval. If Quest is still describing milestones and not dollars in mid-2028, the Celera pattern will have repeated.
The geography and scale play: LifeLabs
On August 23, 2024, Quest completed its largest acquisition since AmeriPath: LifeLabs, Canada's largest community laboratory operator, purchased from the Ontario Municipal Employees Retirement System for approximately C$1.35 billion — roughly US$1 billion including net debt. LifeLabs and its more than 6,500 employees continued operating under their own brand, management team and headquarters.30
Note the seller again: a financial sponsor. That is now the second time Quest has bought a major asset from an institutional owner that had held it for years and optimized it for sale. The AmeriPath precedent argues for scrutiny of price rather than of logic — and here the logic is much cleaner. LifeLabs is a specimen-volume business in a defined geography with a public-payer reimbursement structure, not a professional-services roll-up. It is the Unilab template applied to a country rather than a state.
The financing is where it gets interesting. Quest's leverage moved materially. Net debt to EBITDA had been about 1.2x at the end of 2021, flush with COVID cash; it rose to roughly 2.4x in 2022, 2.8x in 2023, and then spiked to about 3.5x at the end of 2024 in the wake of LifeLabs, before working back to roughly 3.0x at the end of 2025.1 At December 31, 2025, Quest carried $6.92 billion of total debt against $7.17 billion of stockholders' equity — and goodwill plus other intangibles of $10.58 billion against $16.23 billion of total assets.1 Roughly two-thirds of the balance sheet is acquisition accounting, and tangible book value is negative.
That last fact is not a scandal for a serial acquirer of asset-light service businesses, but it is the thing a skeptical investor should hold onto: Quest's balance sheet is a record of prices paid, and its equity cushion depends on those acquired businesses continuing to earn.
In April 2026, Quest priced a $500 million offering of 5.000% senior notes due 2036, closing May 6, with proceeds earmarked for general corporate purposes including repayment of the $500 million of 3.45% notes maturing that June.31 Read plainly: that particular issuance was a refinancing, not incremental leverage, but it repriced a tranche of debt upward by more than 150 basis points — a small, concrete illustration of what a higher-rate world costs a levered acquirer over time.
The volume engine: Fresenius and Corewell
The two deals actually driving the 2025-2026 reacceleration are neither technological nor international.
On August 5, 2025, Quest completed the acquisition of select clinical testing assets — and dialysis-related water testing assets — from Fresenius Medical Care's Spectra Laboratories.32 This put Quest into end-stage renal disease testing, serving dialysis clinics nationwide, in a country where roughly 36 million people have chronic kidney disease.24 By the second quarter of 2026, Davis characterized the Fresenius book as contributing close to $100 million of incremental revenue year over year, with a margin profile improving sequentially through the year.24
On August 26, 2025, Quest and Corewell Health announced a joint venture — Diagnostic Lab of Michigan, LLC, 51% Quest and 49% Corewell — under which Quest would provide collaborative lab solutions across Corewell's 21 hospital laboratories in Michigan and build a 100,000-square-foot facility in Southfield with automated microbiology and high-throughput molecular testing. Supply chain and reference agreements began in late 2025, transaction completion was expected in the first quarter of 2026, and the new laboratory is slated to be operational in the first quarter of 2027.33 Financial terms were not disclosed beyond a statement that the deal met Quest's growth, profitability and return criteria.
Then management quantified it, which is more than most companies do. Corewell was sized at approximately $250 million of positive revenue impact for 2026, at a margin rate guided to low single digits improving to mid-single digits.24 Together, Corewell and Fresenius contributed 9 percentage points of Quest's 13.1% requisition volume growth in the second quarter of 2026 — meaning organic volume excluding the two relationships grew 4.1%.24 And they mechanically dragged reported revenue per requisition down 2.8%; adjusted for that mix, revenue per requisition was up 2.9%.24
Here is the analytical conclusion, and it should be stated without euphemism. Quest's headline growth is currently outrunning its margin quality. The two relationships driving the reacceleration carry margins far below the company average — low-to-mid single digits versus a consolidated adjusted operating margin of 16.5% — and they accounted for roughly 30 basis points of the 40-basis-point year-over-year decline in adjusted operating margin in the quarter, alongside 20 basis points from Project Nova investment and 20 basis points from mark-to-market on deferred compensation.24 Management projects full-year operating margin still expands, on the argument that Corewell and Fresenius lap in the fourth quarter and volume strength offsets higher fuel costs and a heavier second-half Nova spend.24
That is a checkable claim with a deadline. If 2026 operating margin does not expand as guided, the volume-led growth strategy will have failed its first honest test.
Returns to shareholders, and what the split reveals
Quest raised its quarterly dividend 7.5% to $0.86 per share in February 2026 — its fifteenth increase since the beginning of 2012 — and has returned roughly $8.1 billion through share repurchases since 2012.1 During 2025 it repurchased 2.5 million shares for $452 million, leaving about $0.4 billion of authorization, which the board topped up in February 2026.3
The proportions tell the story. Against a stretch that included roughly $1 billion for LifeLabs, $392 million for Haystack, the Fresenius assets, and a Michigan joint venture requiring a new lab build, buybacks of well under half a billion a year are a rounding item. Capital allocation priority sits with M&A, and management has said explicitly that its revenue guidance includes no contribution from prospective acquisitions — meaning the M&A pipeline is upside to guidance, and also a standing claim on the balance sheet.24
Step back and the shape of the strategy is clear, and it is a genuine shift worth naming rather than treating as background. In 2021, Quest was deleveraging and pruning: it sold its 40% stake in the Q² Solutions clinical trials laboratory joint venture to IQVIA for $760 million on April 1, 2021, recording a pre-tax gain of roughly $310 million and exiting the biopharma lab business while retaining a preferred-provider relationship.34 By 2024-2026, it was re-levering to buy volume. Both are defensible. But an investor should recognize that the company running today is not the disciplined-pruning company of 2021; it is a re-leveraging acquirer, and it is doing that into an unresolved Medicare pricing decision.
That is the core. Now the part of the story that gets far more attention than its size warrants — and deserves to be sized honestly.
VII. Sized to Its Weight: Consumer, Wellness, and Advanced Diagnostics (18-22 min — proportional to ~2-4% of revenue today, framed as real optionality)
There is a version of the Quest story circulating that goes: legacy lab company discovers the longevity boom, partners with wearables companies, sells biological-age scores to biohackers, becomes a consumer health platform. It is a fun story. It is also, at present, about 2% of the company.
Management sized the entire consumer-initiated testing business — questhealth.com plus indirect channels where Quest powers third-party wellness and functional-health companies — at approximately $250 million in 2025, and guided it to grow 20-30% in the following year. On the July 2026 call, Davis said it was tracking "on the high side of that estimate."24 Against $11.04 billion of 2025 revenue, $250 million is roughly 2.3%.3
Take the growth seriously and the size seriously at the same time. A business growing 30% off $250 million adds $75 million; the same percentage growth in the physician channel would add an order of magnitude more. Consumer testing is not yet a pillar. It is a fast-compounding option with an unusually attractive characteristic: on the Q1 2026 call, Samad said the margin profile on these deals — wearables collaborations, wellness partnerships, and questhealth.com itself — is on par with or slightly better than the enterprise average, because the tests are paid out of pocket or client-billed rather than adjudicated through health plans.25 The offsetting cost is slower cash collection: Quest attributed part of a rise in days sales outstanding to exactly this mix shift.24
The partner list has grown quickly. WHOOP built in-app lab testing on Quest's collection network and mobile phlebotomy, with a third-party provider handling test ordering and results delivery.35 On August 25, 2026, Humanity Health launched its Biological Age analysis in the United States through questhealth.com — a $29 add-on to several existing health profiles, requiring no additional blood draw, scoring how a person's cardiovascular, metabolic, liver, kidney, immune and hormonal systems are functioning relative to chronological age.36
Now, the more financially relevant story, which gets less airtime.
Quest's advanced diagnostics portfolio spans five clinical areas — advanced cardiometabolic and endocrine, autoimmune, brain health, oncology, and women's and reproductive health — and generated over $1 billion in revenue in 2025 on double-digit growth.1 That is roughly nine percent of the company, four times the consumer business, and it is the primary driver of the mix shift that actually moves the P&L.
The mechanism is tests per requisition. Every time a patient shows up for a blood draw, Quest gets a fixed amount of collection cost and courier cost. Whether the sample generates four tests or five, the arm is only stuck once. Samad quantified the shift on the Q2 2026 call: before COVID, Quest ran somewhere between 3.5 and 4.0 tests per requisition; today it is "almost north of 4.5."24 Roughly one additional test per patient visit, spread across hundreds of millions of requisitions, drops through at high incremental margin. That is what produced 2.9% mix-adjusted revenue-per-requisition growth in a quarter when unit pricing was flat.24
This is a genuine structural gain, and it deserves to be called that. It is also worth noting what it is not: it is not pricing power. Quest is selling more per visit, not charging more per test.
The specific categories doing the work: advanced cardiometabolic tests including ApoB and Lp(a) — both newly recommended by American Heart Association guidelines, which is the sort of external validation that converts a niche assay into a standing order25 — plus liver fibrosis testing, autoimmune panels, and brain health, which Davis said grows at "high double-digit rates."24
Brain health is the most interesting and the most instructive. Quest's AD-Detect franchise uses blood biomarkers to assess the likelihood of Alzheimer's pathology — amyloid beta 42/40 ratios, phosphorylated tau, and the APOE genetic risk marker — as a far less invasive alternative to PET imaging or spinal fluid analysis. On August 24, 2026, Quest announced it would offer a laboratory test service based on Roche's Elecsys pTau217 assay, which the FDA had just cleared as the first single-biomarker blood test supporting both rule-in and rule-out assessment of amyloid pathology, with a nationwide launch planned for the fourth quarter and incorporation into future AD-Detect panels in 2027.37 At the end of August, Quest also launched its own multi-biomarker laboratory-developed test combining pTau217 with amyloid beta 42/40 and APOE, with an algorithmic interpretation.37
On reimbursement, Davis was precise in a way that should be read carefully. Elevance Health now reimburses the pTau217 biomarker — but not, he noted, the amyloid AB 42/40 marker that Quest considers equally important and that is part of its own combined panel.24 He added that there is broad Medicare Advantage reimbursement for these panels, and declined to size the Alzheimer's book.24
Two observations follow. First, the FDA-cleared assay at the center of this is Roche's, not Quest's — Quest is the distribution channel, which is a good place to be for volume and a weaker one for durable differentiation. Second, a payer covering half the panel is a partial win being reported as a coverage milestone. The falsifiable version of the brain-health claim is that reimbursement broadens to the full multi-biomarker panel across major commercial payers, not just the single biomarker.
Finally, the timeline lesson, which is the most useful thing in this section. QuestDirect launched in November 2018.16 It took roughly seven years to become a $250 million, double-digit-growth, named business. Seven years is the observed conversion time for a Quest consumer optionality bet that worked. Anyone assuming Haystack MRD or brain-health panels monetize meaningfully faster than that is assuming something Quest's own history does not support.
VIII. Current Management: Davis Era Scorecard (20-25 min)
The tell in any earnings call is what happens when an analyst asks a hard question. Not the prepared remarks — those are written by committee. The Q&A, where a CFO either produces a number or produces a paragraph.
James E. Davis is not a diagnostics lifer, and that shapes how he runs the company. His background is industrial and operational: General Electric, spanning aviation and healthcare, followed by a stint as chief executive of InSightec, a medical device company. He joined Quest in 2013 and spent nearly a decade running the operating core — the general diagnostics business that generated the large majority of the company's revenue — before the board elevated him to CEO effective November 1, 2022 and then to Chairman on April 1, 2023.1920
That biography argues against reading the current strategy as a reinvention. Davis was the internal continuity choice, promoted from the P&L he already ran, in a company whose board explicitly values his long tenure across multiple roles. The strategy he has executed — buy volume, integrate it into the network, drive a standing 3% productivity program, place selective bets at the edges — is recognizably the same playbook Quest has run since Unilab, executed with more explicit quantification. Anyone framing the Davis era as a bold new direction is over-reading it. What has genuinely changed is the willingness to lever up to fund it, and the granularity of the disclosure around it.
Alignment and governance, stated plainly
The 2026 proxy shows Davis beneficially owning 489,497 shares as of March 6, 2026, of which 107,050 were held directly and 382,447 were shares subject to exercisable options, plus 35,374 underlying restricted stock units — less than 1% of shares outstanding.38 Quest's ownership guidelines require directors and executive officers to hold stock worth a multiple of the board cash retainer, with a 75% net-share retention requirement until the threshold is met.38 This is standard professional-manager alignment: meaningful personal wealth tied to the stock, nothing approaching founder-scale ownership, and compensation weighted toward equity.
At the annual meeting on May 20, 2026, shareholders elected the full board slate, ratified PricewaterhouseCoopers as auditor by a wide margin, and approved the advisory vote on executive compensation.39 A shareholder proposal asking for an independent board chair failed, with roughly 24.0 million shares in favor against 69.8 million opposed — a bit over a quarter of votes cast supported it.39 The board had recommended against, arguing Davis's long tenure and industry experience suited the combined role.38
Two things to say about that, in the right proportion. There is no activist campaign against Quest on the public record, and no governance fight underway; saying so is more useful than implying tension that does not exist. But a quarter of votes cast for splitting the chair and CEO roles is not nothing — it is the routine institutional-investor objection to a combined role at a company that has just re-levered its balance sheet to pursue acquisitions. It belongs in the file as a mild, unresolved governance flag rather than a crisis.
Guidance discipline: the checkable record
The strongest available evidence on management credibility is the shortest: how they have set and revised numbers over the last three reporting periods.
In February 2026, alongside full-year 2025 results of $11.04 billion in revenue, reported diluted EPS of $8.75 and adjusted diluted EPS of $9.85, Quest set initial 2026 guidance of $11.70-$11.82 billion in revenue and $10.50-$10.70 in adjusted EPS.3 In April, after a first quarter with revenue of $2.90 billion (up 9.2%, with 9.0% organic) and adjusted EPS of $2.50, it raised the range to $11.78-$11.90 billion and $10.63-$10.83.40 In July, after a second quarter with revenue of $3.04 billion and adjusted EPS of $3.12, it raised again to $11.95-$12.05 billion and $11.05-$11.25.7
Two raises off a base built from named, quantified drivers rather than atmospherics. That is a positive, checkable data point on communication discipline — with the honest caveat that it covers two quarters. A team that raises twice in a good year has demonstrated that it did not set an aggressive initial number; it has not yet demonstrated how it behaves when it misses.
There is also a caution embedded in the second-quarter beat that management itself flagged: of the 19.1% adjusted EPS growth, roughly four points came from the favorable resolution of tax contingencies worth $0.10 per share. Samad said so unprompted, giving the ex-item figure of 15.3% growth in the same breath.24 Volunteering the lower number is a small thing that says something.
Under pressure
The July call produced two exchanges worth reading as evidence of how this team handles difficulty.
Michael Cherny's team at Leerink pressed on the second-half margin bridge: if margins were down 40 basis points in the quarter, what gets them up for the full year? Samad decomposed the quarter into its three named causes — 20 basis points of Project Nova spending, 30 from the Corewell and Fresenius mix, 20 from mark-to-market on deferred compensation plans — then named the second-half headwinds specifically, including fuel costs at the high end of the prior range and worth close to $10 million, and a Nova spend now expected at 70% of the annual total in the back half versus about 60% previously. Then the offsets: continued volume strength, and lapping Corewell and Fresenius in the fourth quarter.24 That is an answer with arithmetic in it, including two numbers that got worse.
Ann Hynes at Mizuho asked whether hospital bad-debt deterioration, which a large hospital operator had just pre-announced, would flow downstream to the labs. Rather than deflecting, Samad gave the collection mechanics and named the metric — patient concessions running around 5% of revenues, slightly improved year over year — and Davis followed with the actual policies: a sliding scale for patients near the poverty line, referral to collections after a period, and a requirement that patients with significant outstanding balances settle before receiving the next service.24
The PAMA answer, laid out in three explicit scenarios with specific dates and legislative mechanics rather than a wave at "reimbursement uncertainty," is the third data point.24
The pattern is consistent across both 2026 calls reviewed: specific, numerate answers to hard questions, including when the number is unflattering. That is genuine evidence for a credibility read. It is not proof of good judgment about capital allocation — a management team can be admirably transparent about a strategy that turns out to be wrong. The transparency makes the strategy checkable, which is exactly what the next two years will do.
IX. Bear vs. Bull, and What Would Change the Story (25-30 min)
Two intelligent investors can look at the same Quest and see different companies. Here is the strongest version of each, with the disconfirming evidence attached to each claim rather than quarantined.
The bull case
Duopoly economics with real, if bounded, pricing stability. Two players dominate the independent lab market, entry is capital-intensive and slow, and rivalry is disciplined. The bound is management's own pricing commentary — flat overall, slightly negative in hospital reference, flat-to-slightly-positive with health plans.24 The correct bull formulation is stability, not expansion.
A demographic tailwind that is not speculative. An aging population with rising chronic disease burden generates more testing per person per year, essentially mechanically. Davis pointed to chronic conditions plus a genuine consumer shift toward preventive testing as the twin drivers of a utilization environment he described as showing no slowdown.24
Mix shift that is measured, not asserted. The move from 3.5-4.0 to north of 4.5 tests per requisition is the single most credible structural gain in the story, because it shows up directly in mix-adjusted revenue per requisition and because the incremental test carries almost no incremental collection cost.24
An M&A runway created by other people's problems. Hospitals under workforce and financial pressure keep deciding they would rather not run laboratories. Davis described a healthy funnel across all three routes — reference, collaborative lab management, and outreach acquisition — including a new collaborative agreement with a nonprofit California health system signed in the second quarter, and was explicit that Quest prefers to partner with systems that are growing rather than shedding hospitals.24
A regulatory overhang that just lifted. The vacatur and rescission of the LDT rule removed a multi-year threat to the entire advanced-diagnostics pipeline.2627
Small things compounding fast. Consumer testing growing above 30% at enterprise-or-better margins, and a billion-dollar advanced diagnostics portfolio growing at double digits, off a real base with real customers.124
The bear case
PAMA is undecided, and the decision is imminent. A CMS rate announcement expected around now, with new rates potentially effective January 1, 2027, and a legislative alternative that has cosponsors but has not been marked up, scored or assessed.24 The first three rounds of PAMA cuts overshot their own savings target substantially.24 Medicare is a large share of a business whose overall unit pricing is already flat.
Leverage rose to fund growth, and the timing is uncomfortable. Net debt to EBITDA moved from roughly 1.2x at the end of 2021 to about 3.5x after LifeLabs, settling near 3.0x at the end of 2025, with two-thirds of the balance sheet in goodwill and intangibles and negative tangible book value.1 Re-levering into an unresolved federal pricing decision, alongside an ACA-subsidy-driven mix headwind management still sizes at 30 basis points of full-year revenue, stacks two risks in the same window.24
Growth is currently outrunning margin quality, by management's own math. Nine of 13.1 points of volume growth in the second quarter came from two low-margin relationships that mechanically pushed reported revenue per requisition down 2.8% and cost 30 basis points of operating margin.24 Excluding them, volume grew 4.1% — a perfectly respectable number, and a much less dramatic one.
The new bets are unsized, and the base rate is not encouraging. Haystack has state approval, an EHR integration and a research collaboration; it does not have disclosed revenue, and management is deliberately pacing investment to reimbursement while acknowledging near-zero switching costs in the category.24 Brain health has a payer covering one of two biomarkers Quest considers essential, on an assay cleared for Roche rather than for Quest.2437 Against that stands Celera: a $671 million platform acquisition that never became a named growth line.15 And AmeriPath: a $2 billion purchase at roughly three times the price a sponsor had paid four years earlier, into a decade of adverse pathology reimbursement.1214
An activist's angle, if one showed up. The pitch would write itself: a combined chair-CEO role that a quarter of voting shareholders wanted split; a balance sheet where tangible book value is negative and goodwill exceeds equity; a serial-acquirer record with at least one deal that looks expensive against its own comparable and one that quietly disappeared; buybacks at well under half a billion a year while $1.4 billion goes into a Canadian acquisition; and a growth algorithm currently dependent on relationships that dilute margin during ramp. None of that is a scandal. All of it is available material.
Bounded negative findings, stated as such. Across Quest's annual and quarterly filings and the news record covering 2022 through mid-2026, no accounting restatement or material weakness disclosure surfaced, and no activist campaign is on the public record. PricewaterhouseCoopers was ratified as auditor with over 94% of votes cast in favor.39 These are results of a bounded search over named records for a defined period. They are not a general assurance that nothing exists.
Weighing it
Take the claims one at a time and say where they land.
The moat claim. History does not reject it, but it narrows it considerably. Scale economies and workflow-embedded switching costs are real in routine testing, and forty years of failed challengers support that. But the moat does not extend to the growth categories, and the CEO said so. Revised claim: a durable cost-and-workflow advantage in the routine core that produces price stability, not price expansion, and that does not travel to standalone specialist assays. Falsifier: sustained negative unit pricing across both hospital reference and health plan books, or share loss in the core physician channel.
The capital allocation claim. The record is genuinely mixed and should be described that way. Volume-and-density deals — Unilab, LifeLabs, Fresenius, Corewell — fit the cost structure and have historically worked. Technology-platform deals have not converted. The Davis era looks more numerate than its predecessors, because the Corewell and Fresenius contributions were sized, guided and tracked in public rather than folded into a narrative. But the sample is three years long and includes no completed cycle from acquisition to demonstrated return. Falsifier: whether Corewell's margin rate actually climbs from low to mid single digits on the stated schedule, and whether net debt to EBITDA resumes declining after the 2026 notes issuance.
The optionality claim. Leave it intact but unproven, and discount the timeline. QuestDirect took seven years to reach $250 million.1624 Celera took forever and arrived nowhere. Haystack's technical case is stronger than Celera's ever was and its regulatory path is now clearer, but conversion is the step Quest has historically been worst at. Falsifier: disclosed, sized Haystack revenue within 12-18 months of the New York approval.
The management-quality claim. Intact on communication, unproven on judgment. Two guidance raises, decomposed answers under analyst pressure, unprompted disclosure of a one-time tax benefit, and a structured rather than evasive PAMA answer are real evidence.24 None of it tests how the team behaves in a bad year, which is when management quality is actually measured.
The KPIs that matter
Three numbers carry most of the information about whether this story is working. Track them; do not calculate them from scratch, because Quest reports them directly.
One: mix-adjusted revenue per requisition, and the tests-per-requisition figure behind it. This is the cleanest measure of whether the advanced-diagnostics mix shift is real and continuing. It strips out the Corewell and Fresenius distortion, and it is the single metric that captures both pricing and mix in a business where unit pricing is flat by design.
Two: organic requisition volume excluding the named collaborations. In the second quarter of 2026 that was 4.1% against a headline 13.1%.24 The gap between those two numbers is the difference between a company growing its base and a company growing through structurally lower-margin partnerships. Both are legitimate; they are not the same thing.
Three: adjusted operating margin. This is where PAMA, the Corewell and Fresenius ramp, Project Nova spending, fuel and wage inflation all land. Management has committed to full-year 2026 expansion despite a second-half headwind stack.24 It is the most falsifiable promise currently outstanding.
Around those, watch the events: the CMS PAMA rate announcement expected in late September or early October 2026, and whether the RESULTS Act advances; whether Haystack revenue gets disclosed; and the leverage trajectory.
X. Durable Lessons and What to Watch (10-15 min)
Three things generalize from this story, and they are not the ones a promotional version would pick.
Physical scale is a real moat, and it caps out. Route density, collection-point coverage, instrument utilization and payer network position are genuine, hard-to-replicate advantages in a regulated logistics business. Six decades of consolidation produced two national players and no third. But the payoff from that structure is stability, not escalating pricing power — and the proof is that in a quarter where volume grew 13.1% and the company raised guidance twice in a year, unit pricing was flat, hospital reference pricing was slightly negative, and health plan renewals were flat to slightly positive.24 A duopoly in a business where one buyer sets prices by regulation and the others control network access is a good place to sit. It is not a place from which you extract more each year.
Capital allocation quality is not a company trait; it is a deal-type trait. Quest's record separates cleanly. When it bought specimens and routes — Unilab in California, LifeLabs in Canada, dialysis testing from Fresenius, hospital laboratory management in Michigan — it bought something its cost structure could digest, and the results have generally been visible in the numbers. When it bought technology platforms and professional-services roll-ups — Celera, AmeriPath — the outcomes were absorption and, at minimum, a full price. The current era is more numerate than its predecessors: Corewell was sized at $250 million with a stated margin trajectory, and management reports against it quarterly.24 That is a real improvement in disclosure discipline. It is not yet a completed cycle, and calling it proven capital allocation would be exactly the sort of unearned verdict this record cautions against.
Regulatory dependency is not a risk factor here; it is close to the center of the investment case. A CMS methodology decision can move the price of a large share of Quest's volume without a competitor doing anything. A federal court ruling in Texas, and an agency's decision not to appeal it, determined whether Quest's entire advanced-diagnostics pipeline needed premarket review.2627 Neither of those outcomes was in management's control, and the second one is reversible. Any model of this company that weights competitive dynamics heavily and treats Washington as background noise has the weights backwards.
The bathtub in the Manhattan apartment is a good story, and the arc from there to a third of American adults is genuinely remarkable. But the thing that determines what Quest is worth from here is not the arc. It is whether a company that just re-levered to buy volume can hold its margins while a federal agency decides what it gets paid — and whether the technology bets on the edges convert this time, given that the last comparable one did not.
References
-
Quest Diagnostics Incorporated Form 10-K, fiscal year 2025 — U.S. Securities and Exchange Commission, filed 2026-02-26 ↩↩↩↩↩↩↩↩↩
-
Labcorp Announces 2025 Fourth Quarter and Full Year Results — Labcorp Investor Relations, 2026-02-17 ↩↩
-
Quest Diagnostics Reports Fourth Quarter and Full Year 2025 Financial Results; Provides Guidance for Full Year 2026; Increases Quarterly Dividend 7.5% to $0.86 Per Share — Quest Diagnostics Newsroom, 2026-02-10 ↩↩↩↩↩↩
-
Quest Diagnostics 50th Anniversary: Celebrating a Half Century of Life-Changing Results — Quest Diagnostics Newsroom, 2017-04-24 ↩↩↩↩
-
Quest Diagnostics Announces Preliminary Fourth Quarter and Full Year 2021 Financial Results — Quest Diagnostics Newsroom, 2022-01-12 ↩↩↩
-
Quest Diagnostics Reports Fourth Quarter and Full Year 2023 Financial Results; Provides Guidance for Full Year 2024 — PR Newswire, 2024-02-01 ↩↩
-
Quest Diagnostics Reports Second Quarter 2026 Financial Results; Raises Revenue and EPS Guidance for Full Year 2026 — PR Newswire, 2026-07-23 ↩↩
-
Corning subsidiary pays $119 million, barred from Medicare program to settle fraud cases — Phillips & Cohen LLP, 1996-10-09 ↩
-
Quest Diagnostics Completes Acquisition of SmithKline Beecham Clinical Laboratories — Quest Diagnostics Investor Relations, 1999-08-16 ↩
-
Attorney General Janet Reno announces SmithKline Beecham Clinical Laboratories settlement — U.S. Department of Justice, 1997-02-24 ↩
-
Quest Diagnostics to Acquire Unilab Corporation In Transaction Valued at $1.1 Billion — Quest Diagnostics Investor Relations, 2002-04-02 ↩
-
Quest Diagnostics to Acquire AmeriPath in a Transaction Valued at $2 Billion — Quest Diagnostics Newsroom, 2007-04-16 ↩↩
-
Quest Diagnostics Form 8-K, Exhibit 99.1 (AmeriPath acquisition announcement) — U.S. Securities and Exchange Commission, 2007-04-16 ↩
-
Welsh Carson doubles money on exit — Private Equity International, 2007 ↩↩↩
-
Quest Diagnostics, a Pioneer in Consumer Health, Expands Offering with Launch of QuestDirect — Quest Diagnostics Newsroom, 2018-11-07 ↩↩↩
-
Quest Diagnostics Reports Fourth Quarter and Full Year 2022 Financial Results; Provides Guidance for Full Year 2023 — PR Newswire, 2023-02-02 ↩↩↩
-
Quest cuts 2023 COVID tests forecast amid continued slump; Q4 profit plunges — MedTech Dive, 2023 ↩
-
Quest Diagnostics Announces Leadership Succession Plan — Quest Diagnostics Investor Relations, 2022-02-03 ↩↩
-
Quest Diagnostics Board of Directors Elects James E. Davis Chairman of the Board — Quest Diagnostics Newsroom, 2023-03-03 ↩↩
-
Quest Diagnostics says 11.9 million patients' financial and medical information may have been exposed in data breach — CNBC, 2019-06-03 ↩↩
-
Quest Diagnostics Statement on the AMCA Data Security Incident — Quest Diagnostics Newsroom, 2019 ↩
-
AMCA Settles 2019 Healthcare Data Breach with 41 State Attorneys General — Compliancy Group ↩
-
Quest Diagnostics Incorporated (DGX) Q2 2026 Earnings Call Transcript — Seeking Alpha, 2026-07-23 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
Quest Diagnostics Incorporated (DGX) Q1 2026 Earnings Call Transcript — Seeking Alpha, 2026-04-21 ↩↩↩↩
-
Federal Court Vacates FDA Rule on Laboratory Developed Testing Services, Siding with ACLA — American Clinical Laboratory Association, 2025-03-31 ↩↩↩
-
Quest Diagnostics to Acquire Haystack Oncology — Quest Diagnostics Newsroom, 2023-04-27 ↩
-
Quest Diagnostics Completes Acquisition of Haystack Oncology — Quest Diagnostics Newsroom, 2023-06-21 ↩
-
Quest Diagnostics Completes Acquisition of LifeLabs, Enhancing Access to Diagnostic Innovation — Quest Diagnostics Newsroom, 2024-08-26 ↩
-
Quest Diagnostics Prices $500 Million of Senior Notes — Quest Diagnostics Newsroom, 2026-04-27 ↩
-
Quest Diagnostics Completes Acquisition of Clinical Testing Assets from Fresenius Medical Care — Quest Diagnostics Newsroom, 2025-08-05 ↩
-
Corewell Health and Quest Diagnostics to Enter into Joint Venture Providing Enhanced Laboratory Services in Michigan — Quest Diagnostics Newsroom, 2025-08-26 ↩
-
Quest Diagnostics Sells Ownership Interest in Q² Solutions to IQVIA — Quest Diagnostics Newsroom, 2021-04-01 ↩
-
WHOOP Partners with Quest Diagnostics for In-App Lab Testing — Clinical Lab Products ↩
-
Humanity Brings Biological Age Analysis to the U.S. Through questhealth.com — Quest Diagnostics Newsroom, 2026-08-25 ↩
-
Quest Diagnostics to Offer FDA-Cleared Roche pTau217 Blood Test to Assess Alzheimer's Disease Pathology — Quest Diagnostics Newsroom, 2026-08-24 ↩↩↩
-
Quest Diagnostics Incorporated Definitive Proxy Statement (DEF 14A), 2026 Annual Meeting — U.S. Securities and Exchange Commission ↩↩↩
-
Quest Diagnostics Incorporated Form 8-K, annual meeting voting results — U.S. Securities and Exchange Commission, filed 2026-05-21 ↩↩↩
-
Quest Diagnostics Reports First Quarter 2026 Financial Results; Raises Revenue and EPS Guidance for Full Year 2026 — Quest Diagnostics Newsroom, 2026-04-21 ↩
 LinkedIn
 WhatsApp
 Reddit
 Hacker News
 Email
 Kindle
 RSS Feed
 Spotify
 Apple Podcasts
 Amazon Music
 Audible
 YouTube