Fortis Healthcare: The Rise, Fall, and Rebirth of India's Healthcare Giant
I. Introduction & Episode Roadmap
There is a particular kind of silence that falls over a hospital lobby when vendors stop delivering.
In the spring of 2018, across several Fortis Healthcare facilities in North India, that silence was becoming audible. Suppliers of stents, sutures, reagents, and contrast dye — the unglamorous consumables that keep a tertiary hospital running — had begun slow-walking deliveries. Consultants who had spent a decade building cardiac and oncology practices under the Fortis brand were taking calls from rivals like Max, Medanta, and Apollo. The company's auditors refused to sign off on its financial statements. Its two founders — brothers who a decade earlier ranked among India's wealthiest individuals — had just resigned from the board of the company funded by their grandfather's pharmaceutical empire.
Yet the operating theatres kept running. Surgeries continued, and patients kept coming.
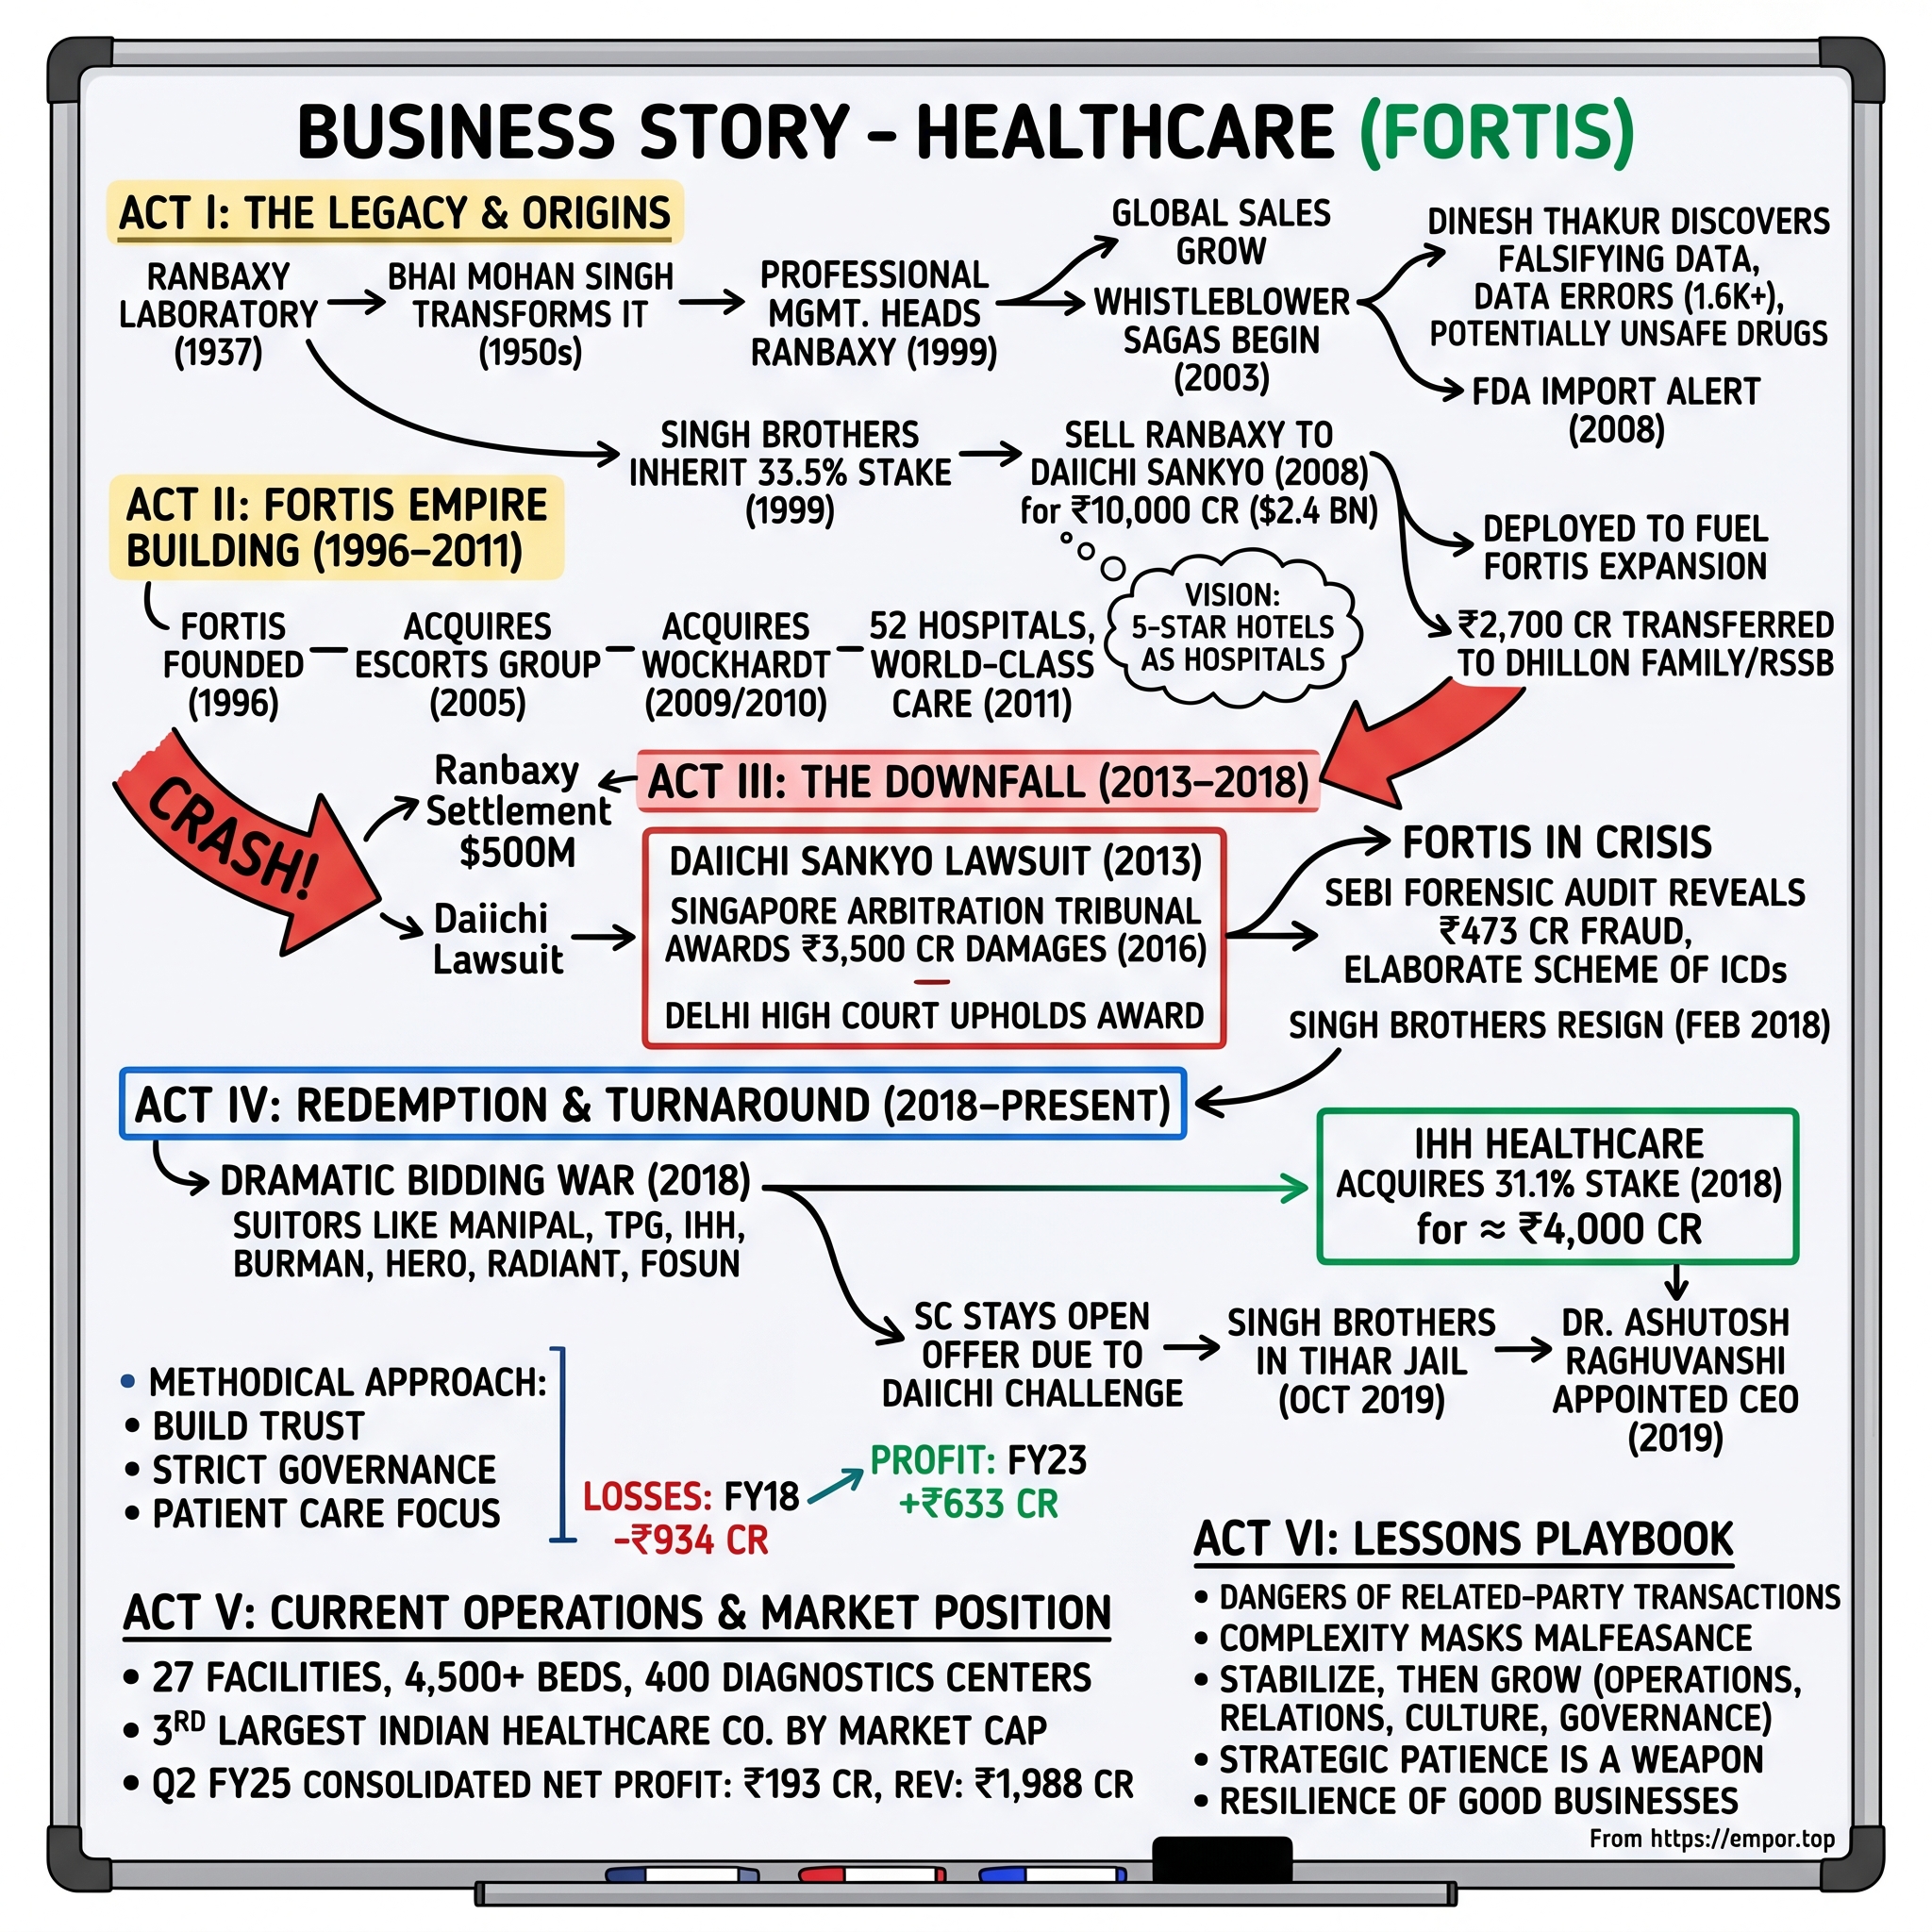
That gap between a collapsing corporate structure and a functioning clinical asset is the central story of Fortis Healthcare, making it one of the most instructive case studies in modern Indian business. Promoters siphoned over ₹473 crore out of the listed company and its subsidiaries through promoter-controlled entities.[^9] A separate non-banking financial company in the same promoter orbit, Religare Finvest, was drained of thousands of crores. The founders, Malvinder Mohan Singh and Shivinder Mohan Singh, were arrested in October 2019 and sentenced for contempt of a Supreme Court order in the Daiichi Sankyo dispute.5 A four-way international bidding war broke out over the company in mid-2018. Malaysia's IHH Healthcare won the contest, paying ₹4,000 crore for a 31.1% stake in November 2018[^12] — only to find itself legally frozen at that exact ownership percentage by a Supreme Court stay that remains in effect as of September 2026.[^6]
The resulting paradox is striking. IHH has spent nearly eight years unable to complete the mandatory open offer that would give it majority control. It cannot squeeze out minority shareholders or fully integrate treasury operations. It has been dragged through contempt proceedings, forensic audit orders, and, as recently as August and September 2026, a fresh Delhi High Court forensic audit direction that Fortis is now appealing in the Supreme Court.[^7] By almost every measure of corporate control, IHH's investment in India has been a legal nightmare.
Yet over that same period, under chief executive officer Dr. Ashutosh Raghuvanshi — a cardiac surgeon turned hospital operator — the underlying operations roughly doubled revenue while expanding operating EBITDA margins from single digits into the low twenties.
The broader lesson is that healthcare in emerging markets is a long-duration, asset-heavy infrastructure business where clinical trust, rather than brand advertising or abstract scale, serves as the compounding asset. Fortis demonstrates an uncomfortable reality for corporate governance purists: severe governance failure can vaporize shareholder value without destroying the physical and human assets that generate clinical revenue. A hospital in Gurugram with a heart transplant program and a loyal physician referral network remains a high-value clinical asset, even when its former promoter is serving time in Tihar Jail.
However, the inverse caution is equally vital: an asset that survived a corporate fraud does not automatically become a sound investment. The legal overhang is far from cosmetic, the margin gap against best-in-class peers is closing slowly, and the diagnostics business once viewed as high-margin optionality has been repriced by competitive market forces.
The narrative unfolds across several key phases: the Ranbaxy inheritance and the $2.4 billion Daiichi Sankyo transaction that funded initial expansion; the founding of Fortis and its aggressive domestic acquisitions; the international expansion that consumed over $1 billion with minimal return; the promoter siphoning scandal and Religare contagion; the 2018 bidding battle and IHH's constrained victory; the legal web still binding the business; the operational turnaround; the unit economics of Indian hospital beds compared across Apollo, Max, Medanta, and Narayana; the strategic positioning of Agilus Diagnostics; and an evaluation of the core metrics that will dictate future returns.
The story begins, as so many Indian corporate sagas do, with a family empire and a pharmaceutical company.
 Subscribe on LinkedIn
II. The Ranbaxy Legacy & The Singh Family Saga
Ranbaxy did not begin as a Singh family business. It began in 1937 as a Delhi distributorship named for its two founding cousins — Ranjit Singh and Gurbax Singh — the corporate equivalent of a portmanteau licence plate. When the cousins could not repay money lent to them by a relative, that relative, Bhai Mohan Singh, took the company over. What had been a small distribution outfit became, over the following four decades, the vehicle through which India taught itself to make medicine.
The intellectual architect of that transformation was Bhai Mohan Singh's son, Dr. Parvinder Singh — a University of Michigan-trained pharmacist with a conviction that an Indian company could compete with Western pharmaceutical majors on their own soil. India's 1970 Patents Act, which recognized process patents but not product patents, gave domestic firms a legal runway to reverse-engineer molecules that were still under patent elsewhere. Parvinder Singh understood that this was not a permanent gift. He built Ranbaxy for the world that would exist after India rejoined the global patent regime: international filings, US FDA-registered plants, and a genuine research budget. By the 1990s, Ranbaxy was India's largest pharmaceutical company and its most credible global exporter.
Parvinder Singh died of cancer in 1999 at age 56. His sons Malvinder and Shivinder — then in their mid-twenties, with Duke MBA and business-school credentials — inherited a promoter holding of roughly a third of India's flagship drug company. They inherited something else too, which would matter more: a corporate culture in which the promoter family's word was final and the distinction between the family's balance sheet and the company's was, at best, fluid.
The $2.4 Billion Exit
On June 11, 2008, the brothers agreed to sell their roughly 34% promoter stake in Ranbaxy Laboratories to Japan's Daiichi Sankyo for about $2.4 billion, in a transaction that valued Ranbaxy at roughly $4.6 billion in total. The timing looked, for a few months, like genius. Lehman Brothers collapsed three months later, and Indian equity markets lost more than half their value. The Singh brothers had converted an illiquid family holding into cash at what turned out to be very near the market top.
The legend of the Singh brothers as visionary capital allocators — executives who sold pharma at the peak to fund a nation-building hospital empire — was born in that window. Yet that narrative collapses under closer scrutiny.
The claim: the Daiichi sale was strategic foresight, a deliberate rotation from a commoditizing generics business into the structurally superior economics of Indian healthcare delivery.
The disconfirming record. Start with what Daiichi Sankyo did not know. In 2003, a Ranbaxy employee named Dinesh Thakur, recruited from Bristol-Myers Squibb, had begun documenting systematic falsification of drug testing data in dossiers Ranbaxy was submitting to the US FDA and other regulators. Thakur took his findings up the chain, was pushed out, and eventually became a whistleblower to US authorities. The outcome, five years after the Daiichi transaction closed: in May 2013, Ranbaxy's US subsidiary pleaded guilty to felony charges and agreed to pay $500 million to resolve criminal and civil liability — at the time the largest settlement ever with a generic drug manufacturer, covering adulterated drugs and false statements to the FDA.[^13]
Daiichi Sankyo, having bought control of a company whose US manufacturing credibility was about to be publicly incinerated, went to arbitration in Singapore. In April 2016, the tribunal ruled against the Singh brothers, finding that the sellers had concealed material information about regulatory investigations, and awarded damages of roughly ₹3,500 crore including interest.5 The award has been the subject of enforcement litigation in Indian courts ever since — litigation that became the single largest constraint on Fortis Healthcare's ownership structure.
So the sale was not a call on the pharma cycle. It was the monetization of an asset whose largest hidden liability was known to the sellers and not to the buyer — a conclusion established by an international arbitral tribunal rather than editorial interpretation.
And the proceeds? This is the pattern that should have warned Fortis shareholders years before 2018. The $2.4 billion did not go into a disciplined healthcare compounding program. It was deployed across an expanding, opaque web: financial services under Religare, the Fortis hospital chain, international healthcare ventures, unhedged foreign currency convertible bonds, real estate, and a growing tangle of inter-corporate deposits and circular loans between promoter entities. By the time the siphoning came to light, the brothers were not wealthy investors navigating bad bets. They were leveraged operators using one entity's cash to service another's debt.
Verdict: the founder-genius thesis is rejected outright. No version of "disciplined capital allocator" survives an arbitral finding of concealment alongside a documented pattern of related-party cash extraction. Why this matters analytically is not for moral bookkeeping about two men now in their fifties; it is because the institutional deficiencies that allowed it — a pliant board, related-party approvals without arm's-length testing, and auditors who caught it late — are precisely the structural flaws a current investor must confirm have been remediated, not merely re-staffed.
That history frames the healthcare entity built with those proceeds.
III. Empire Building: The Birth of Fortis & M&A Binge (1996–2012)
The first Fortis hospital opened in Mohali, Punjab, in 2001 — a cardiac-focused facility in a Tier-2 North Indian city, an unconventional springboard for a national health system. Dr. Parvinder Singh had conceived it partly as a memorial project; the company was incorporated in 1996 as an offshoot of Ranbaxy Laboratories, long before anyone anticipated it would outlive the pharmaceutical business itself.
What Fortis introduced to Indian healthcare in its first decade was, in essence, an aesthetic repositioning. Indian private hospitals in the 1990s — even prominent ones — were largely utilitarian: clinical green walls, congested corridors, and administrative friction inherited from state-run facilities. Fortis proposed that a hospital could be operated with hospitality-grade standards: sunlit lobbies, tiered room options, and staff trained in customer experience alongside clinical protocols. Apollo Hospitals pioneered this high-end private model in Chennai in 1983, but Fortis systematically scaled it across North India.
That strategy offered more than cosmetic appeal; it carried direct economic consequences. Hospitality-grade amenities do not improve clinical outcomes on their own, but they do expand the addressable pool of private-pay patients and tilt the payor mix toward higher-margin cash and private insurance customers — the single most potent profitability lever in hospital economics. It was a revenue-mix strategy executed as a service brand, and it proved immediately effective.
Buying the North
Fortis, however, chose rapid acquisition over organic expansion. Between 2005 and 2012, the company embarked on an aggressive inorganic expansion campaign.
Escorts, 2005. The Escorts Heart Institute and Research Centre on Okhla Road in Delhi was then the premier cardiac institution in North India — a flagship hospital that commanded unmatched clinical reputation and performed a dominant share of the region's complex cardiovascular procedures. Fortis acquired the healthcare assets of the Escorts Group for approximately ₹585 crore. In a single transaction, Fortis transformed from a regional operator in Punjab into the owner of Delhi's leading cardiac facility.
Despite the corporate turmoil that followed in later years, this acquisition proved durable. Two decades later, the Okhla Road facility remains a core operational and financial anchor. It illustrates a fundamental rule of healthcare economics: a hospital possessing a deeply entrenched specialty reputation in a supply-constrained metropolitan market functions more like an irreplaceable infrastructure asset than a standard operating business.
Wockhardt, 2009–10. The second major transaction was an expansive territory capture. Fortis acquired ten facilities from Wockhardt Hospitals — which was divesting assets under corporate debt pressure — for roughly ₹909 crore. The deal added more than 1,000 operational beds and established immediate footprints in major urban markets, including Mumbai, Bengaluru, and Kolkata, highlighted by the Mulund facility in Mumbai.
At approximately ₹90 lakh per bed, the headline valuation appeared competitive relative to greenfield build costs. On a forward enterprise value to EBITDA basis, however, the transaction was expensive. The acquired facilities suffered from low occupancy and thin operating margins, meaning Fortis paid an enterprise multiple in the mid-teens for earnings that were largely projections. That valuation might have been manageable under conservative financing, but Fortis funded the purchase heavily with short-term debt.
This established the structural risk pattern that governed the subsequent decade: Fortis repeatedly prioritized speed of expansion over capital discipline. In an industry where new hospital beds require four to six years to reach steady-state occupancy and profitability, accelerating growth with short-term debt is a perilous strategy. It functions only if asset ramp-ups meet ideal timelines; it becomes dangerous if operational delays coincide with broader corporate stress.
The International Detour
The strategic focus fractured further over the next three years. Between 2010 and 2012, operating under the entity Fortis Global Healthcare, the company deployed over $1 billion outside India. The international shopping spree included an Australian dental clinic roll-up (Dental Corporation), a primary-care network in Hong Kong (Quality HealthCare), a hospital chain in Vietnam (Hoan My), and a contested bid for Singapore's Parkway Holdings, where Fortis engaged in a high-stakes bidding war against Khazanah Nasional — the Malaysian sovereign wealth fund vehicle that would later form IHH Healthcare.
Fortis ultimately lost the takeover contest for Parkway, selling its stake after being outbid by Khazanah. The overarching industrial logic of the overseas expansion was weak. Fortis positioned itself as a pan-Asian healthcare platform, even as its core Indian hospitals — its primary driver of clinical authority and high-return domestic growth — lacked sufficient capital and its balance sheet took on heavy debt. Australian dental practices shared virtually no operational synergies with tertiary cardiac care in New Delhi: there was no meaningful procurement scale, no transferable clinical protocol, and no cross-border patient referral pipeline.
Between 2011 and 2014, Fortis systematically divested the international portfolio — liquidating holdings in Parkway, Quality HealthCare, and Dental Corporation. The rapid exits represented forced deleveraging under financial strain rather than strategic asset rotation.
The RHT Structure — and the Falsification It Deserves
Parallel to its overseas expansion, Fortis executed the most consequential financial engineering in its corporate history: the creation of Religare Health Trust (RHT), a business trust listed in Singapore in 2012.
The transaction mechanism was a sale-and-leaseback structure packaged inside a listed yield vehicle. Fortis transferred the physical real estate and hospital infrastructure of key Indian facilities to RHT, which was funded by yield-seeking public investors in Singapore. RHT held the physical property, while Fortis operated the clinical facilities and paid RHT a mandatory, recurring business trust service fee for using the assets.
The claim made at the time: separating property from operations would reduce the overall cost of capital. Promoters argued that hospital real estate represented a stable, bond-like asset that income investors would finance at low yields, whereas hospital clinical operations represented a higher-return growth business suitable for equity investors. Monopolizing operational assets while offloading real estate was billed as an asset-light framework designed to accelerate expansion.
What actually happened. The service fee obligations to RHT were fixed and mandatory, whereas hospital occupancy and operating revenues remained variable. When international investments underperformed, domestic acquisitions ramped up slower than projected, and promoter-level debt created cash demands across the group, Fortis found itself burdened by heavy fixed lease payments on top of an already leveraged balance sheet. Hospital-level operating margins were structurally depressed by recurring fees decoupled from operational performance. In financial terms, Fortis transformed variable operational risk into a rigid contractual liability in an industry where facility-level demand fluctuates.
Verdict: the asset-light model failed when applied to capital-intensive tertiary healthcare delivery. The ultimate confirmation of that failure came in 2019, when Fortis spent approximately ₹4,650 crore to buy back RHT's Indian assets specifically to eliminate the ongoing service fee burden. A corporation does not deploy substantial capital to dismantle an effective corporate structure. The underlying lesson is not that asset-light models are inherently flawed, but that offloading real estate only lowers a firm's cost of capital if underlying operational cash flows are resilient enough to service fixed liabilities through industry downcycles. Facility-level hospital cash flows do not possess that stability.
By 2013, Fortis possessed premier clinical assets bound to an over-leveraged balance sheet, an onerous fixed lease burden, a contracting international footprint, and controlling shareholders facing severe liquidity demands. The eventual restructuring became a matter of basic arithmetic.
IV. Financial Alchemy & The $78M Siphoning Scandal (2013–2018)
The instrument at the centre of the fraud was almost boringly mundane: the inter-corporate deposit.
An ICD is simply a short-term loan from one company to another, outside the banking system. It is legal, common, and in a well-governed group, unremarkable — surplus cash parked with a sister entity at a market rate, properly disclosed, and properly approved. What made it lethal at Fortis was the combination of three features: the borrowers were promoter-controlled entities, the loans were unsecured and unrated, and they were rolled over continuously so that no single quarter ever showed a default.
Between 2016 and 2018, more than ₹473 crore — roughly $78 million at the exchange rates of the period — moved out of Fortis Healthcare Limited and Fortis Hospitals Limited through this mechanism, routed via a set of entities that had no discernible healthcare business.[^9] Names that surfaced in the subsequent regulatory record included Best Healthcare, Fern Healthcare, and Modland Wears — companies whose formal shareholding was structured to obscure the promoters' connection but which SEBI later found to be connected to them.[^9] The money went toward promoter obligations: servicing the mounting Daiichi liability and legal defence, funding investments in real estate ventures linked to the Radha Soami Satsang Beas ecosystem with which the family had deep ties, and plugging holes elsewhere in an increasingly illiquid personal balance sheet.
This sequence underscores a direct causality. The Singapore arbitration award created a multi-thousand-crore personal liability for the promoters. The promoters controlled a listed hospital company with real operating cash flow. Cash moved from the operating entity to the personal balance sheet. The Ranbaxy fraud of 2003 and the Fortis fraud of 2017 were not two separate stories; the first produced the liability that motivated the second.
The Religare Contagion
Running in parallel was the larger financial-services version of the same scheme. Religare Enterprises — the financial services group the brothers had also built with Ranbaxy proceeds — housed a non-banking financial company, Religare Finvest. NBFCs exist to make loans. Religare Finvest made them to promoter-affiliated entities, in amounts eventually alleged to exceed ₹2,400 crore, on terms no independent credit committee would have approved. When those loans went bad, they took a regulated lender down with them, with consequences for depositors and corporate creditors entirely outside the healthcare business.
This structural spillover separates Fortis from an ordinary governance lapse. This was not aggressive accounting or a self-dealing property lease. It was the systematic use of two separate public vehicles — a hospital chain and a lending institution — as funding sources for the controlling family's personal obligations.
The Auditors Finally Say No
The mechanism that broke the cycle was, as is so often the case, an auditor's signature.
For financial year 2018, Deloitte Haskins & Sells declined to issue a clean opinion on Fortis Healthcare's accounts. The qualification was specific: the auditors stated they were unable to comment on the recoverability of the ICD advances and on the completeness of related-party disclosures, warning that the matters under investigation could have further effects that were not determinable. In audit language, this is close to the loudest available alarm short of a disclaimer.
A qualified opinion on a listed company of Fortis's size is not a technicality. It severs access to cheap credit, triggers covenant reviews across lenders, freezes institutional equity participation, and — in the specific case of a hospital — prompts vendors to demand cash on delivery. The clinical supply chain problem that opened this story was a direct downstream consequence of an accounting qualification.
SEBI initiated a forensic examination, and in its eventual order in the matter of Fortis Healthcare Limited, directed recovery of the diverted funds together with interest from the entities and individuals involved, alongside penalties.[^9] The regulator's finding was unambiguous: the transactions represented a deliberate scheme to divert funds from the listed company.
The Board That Wasn't
The claim under test here is a general one: that independent directors on a listed Indian company protect minority shareholders from promoter overreach.
The record at Fortis: through 2016 and 2017, the board repeatedly approved or permitted the renewal of unsecured, unrated short-term advances to entities that would later be found to be promoter-connected, without independent valuation or documented arm's-length testing. Institutional shareholders raised concerns; proxy advisory dissent existed in the voting record. Nothing changed until two forcing events occurred simultaneously — the auditors refused to sign, and lenders began invoking pledged promoter shares. The board reconstituted itself only after external agents with contractual leverage acted.
Verdict: the thesis fails as stated. Independent boards in promoter-dominated structures are a lagging indicator of governance, not a leading one; the binding constraints in this case were the auditor, the lenders, and the regulator. For an investor, the practical translation is that board composition is close to worthless as a standalone diligence signal in a company with a concentrated controlling shareholder. What has actual predictive value is whether a controlling shareholder's personal balance sheet is under stress — the single best-correlated warning sign in the entire Fortis timeline.
In February 2018, with lenders invoking pledges and auditors refusing to sign, Malvinder and Shivinder Singh resigned from the Fortis board. In October 2019, the Economic Offences Wing of Delhi Police arrested them in connection with the Religare Finvest matter; in November 2019 the Supreme Court sentenced them in the Daiichi contempt proceedings, and they went to Tihar Jail.5
By February 2018, Fortis Healthcare had already become something unusual in Indian capital markets: a large, high-quality, clinically respected asset base with no promoter at all. It was, effectively, ownerless.
The phone lines to the investment banks lit up immediately.
V. The 2018 Bidding War & IHH's Entangled Takeover
For roughly four months in 2018, Fortis Healthcare became the most contested corporate asset in India. Unusually for an Indian corporate takeover, the battle played out entirely in public before institutional shareholders who suddenly found themselves holding the deciding vote.
The sequence began when Manipal Hospitals, backed by TPG Capital, made the first move — an early lead that quickly became a disadvantage. Public shareholders, led by foreign institutional investors including Jupiter India and East Bridge, immediately attacked Manipal's initial proposal as opportunistic for under-valuing the core hospital operations. The deal structure was also complex, pairing the hospital acquisition with a demerger of the diagnostics business on terms minority investors resisted. Manipal revised its terms repeatedly, but shareholders continued to object. In a standard promoter-led takeover, controlling owners would have executed the deal regardless of minority complaints. With the Singh brothers ousted, however, institutional investors possessed genuine leverage and exercised it.
Hero Enterprise (led by the Munjal family) and the Burman family office submitted an unsolicited proposal to infuse capital without acquiring operational control — a structure offering domestic ownership optics, but failing to address who would actually manage the troubled chain. Radiant Life Care, partnered with KKR, put forward an alternative recapitalization plan. Finally, IHH Healthcare Berhad — the Malaysian operator of Parkway Pantai and Acibadem that had outbid Fortis for Parkway eight years earlier — proposed a straightforward cash injection.
By July 2018, the reconstituted board faced an operational imperative that the bidding noise had obscured. Fortis did not primarily need a high valuation headline; it required immediate liquidity to pay vendors, reassure clinical practice leads, and refinance short-term debt. Crucially, it needed a credible operator capable of stemming physician departures.
IHH's proposal provided both capital and operational credibility. On November 13, 2018, IHH completed a ₹4,000 crore (roughly $570 million) preferential allotment, acquiring a 31.1% stake at ₹170 per share and assuming controlling board oversight.[^12] The capital injection immediately stabilized vendor supply chains, reassured creditors, and funded the buyout of RHT's Indian assets to eliminate the onerous fixed lease obligations.
The Trap Closes
Under Indian takeover regulations, an acquirer crossing the 25% ownership threshold must launch a mandatory open offer to public shareholders for an additional 26% stake. IHH initiated the offer. Had it closed, IHH would have secured roughly 57% equity ownership — giving it outright majority control to consolidate financial statements, integrate corporate operations, and restructure the balance sheet.
The transaction hit a legal wall. Daiichi Sankyo, seeking to enforce its arbitration award against the Singh brothers, petitioned the Supreme Court of India, contending that the Fortis-IHH transaction violated existing status quo orders regarding promoter asset disposal. In December 2018, the Supreme Court stayed the open offer.[^6]
As of September 2026, that judicial stay remains active. Consequently, IHH has spent nearly eight years locked into a 31.1% controlling stake without the legal ability to reach majority ownership.
Was It Cheap?
Evaluating the acquisition reveals two distinct perspectives. The bullish case highlights asset value: at ₹170 per share, IHH acquired control of a top-tier Indian hospital platform at approximately ₹85 lakh per bed. This implied an enterprise value multiple in the low teens — a substantial discount relative to listed peers trading at nearly double that multiple, and well below the replacement cost of building equivalent greenfield tertiary hospitals. On asset pricing alone, IHH secured a favorable entry.
The bearish argument, which has proven accurate over the subsequent eight years, views that discount not as a market mispricing but as the cost of legal entrapment. Without majority control, IHH cannot fully consolidate Fortis's cash flows onto its balance sheet, execute a corporate merger, or squeeze out minority holders. Furthermore, injecting parent equity for capital expansion risks self-dilution within a constrained ownership framework. As a result, every expansion project at Fortis has had to rely strictly on internal cash generation or debt financing.
The reality sits squarely between these views. IHH paid a control price for limited operational governance without full financial ownership. While it has successfully implemented operational enhancements — standardizing clinical protocols, improving procurement, and installing professional management — the broader financial benefits of full ownership remain frozen behind a court order. Ultimately, whether the 2018 acquisition creates long-term value depends on an unpredictable legal outcome: the eventual resolution of the Supreme Court stay. Until then, the investment functions less as a conventional controlling acquisition and more as a long-dated legal option.
Which requires understanding the litigation properly.
VI. Legal Ghosts & Auditor Falsification: Daiichi, SEBI, and Court Stays
The legal history of Fortis Healthcare is not a single case. It is a matrix of overlapping proceedings across multiple jurisdictions, and it has proven durable because various claimants are pursuing different assets through distinct legal doctrines with only partial overlap.
Daiichi Sankyo's enforcement track is the primary driver of this legal web. Holding an arbitral award of roughly ₹3,500 crore against the Singh brothers, Daiichi has spent a decade attempting to locate and attach recoverable assets. The complication is that most of the brothers' visible wealth consisted of pledged Fortis shares. When lenders invoked those pledges during the 2018 collapse, the shares transferred to financial institutions that sold them into the public market. Daiichi's litigation subsequently pushed toward more complex legal theories: alleging that certain asset disposals violated court orders, demanding that the corporate veil be pierced, and seeking to unwind downstream transactions. The contempt proceedings that resulted in the brothers' imprisonment in 2019 stemmed directly from this enforcement track.5
The litigation also carries an international dimension. In September 2026, the Tokyo District Court dismissed claims brought by an IHH subsidiary against Daiichi Sankyo arising out of the Fortis acquisition — a reminder that the two corporate entities have been litigating against each other rather than focusing solely on the former promoters, making a negotiated resolution unlikely in the near term.2
SEBI's track addressed the securities-law violation: the systematic diversion of capital from a listed enterprise. The regulator's order directed the recovery of siphoned funds alongside interest and financial penalties.[^9] Enforcing recovery orders against individuals whose remaining assets are simultaneously claimed by a Japanese pharmaceutical company and creditors of a distressed lender, however, amounts to standing in a long legal queue rather than accessing liquid capital.
The 2026 forensic audit front remains the active battleground. In August 2026, the Delhi High Court ordered a fresh forensic audit of historic transactions involving Fortis, the Singh brothers, and IHH. In September 2026, Fortis Healthcare filed a Special Leave Petition in the Supreme Court challenging that order, arguing in substance that a listed company operating under a completely reconstituted board should not be subjected to a broad investigation into conduct it neither committed nor benefited from.[^7]
While that argument carries logical weight, it also reflects the defensive posture of a corporation seeking to regain control of its narrative in the courts. That such litigation remains necessary eight years after the initial fallout highlights the persistent nature of the company's legal baggage.
Reading the Auditors' Language
A useful exercise in analyzing Fortis's balance sheet involves examining its audit opinions in sequence, as the shifting tone of audit qualifications tracks operational recovery far more reliably than executive presentations.
In financial year 2018, auditors issued an inability-to-comment disclaimer, stating they could not verify the recoverability of inter-corporate deposit balances or ensure the completeness of related-party disclosures. That language reflected fundamental uncertainty about the reliability of the underlying accounts. In subsequent years, as bad debts were written off, regulatory investigations concluded, and related-party exposures were quarantined, audit opinions shifted toward emphasis-of-matter notes focused on ongoing litigation and the pending Supreme Court stay.6
An emphasis of matter is not an accounting qualification; it confirms that the financial statements are presented fairly while directing attention to material contingencies. This transition — moving from an inability to express an opinion to issuing a clean opinion with explicit contingencies — provides clear evidence that internal financial reporting was systematically restructured rather than cosmetically masked. It also signals that investors must monitor footnote disclosures annually, as legal contingencies remain active.
Falsifying "The Legal Overhang Doesn't Matter"
The claim, frequently advanced by bullish market observers: the litigation targets the former promoters personally, Fortis's clinical assets remain insulated, and the surrounding legal complex is mere background noise.
Testing the claim requires evaluating the mechanism that directly affects operations — not the probability of a direct financial judgment against the hospital network, which remains low, but the impact on cost of capital and corporate integration:
The judicial stay on the open offer prevents IHH from increasing its equity stake. Consequently, Fortis is unable to access low-cost parent capital from an international strategic sponsor committed to Indian expansion. Every new hospital bed added to the network must be funded through internal cash flows or higher-cost domestic debt. This constraint imposes a measurable drag on expansion velocity while preventing treasury integration between parent and subsidiary. Furthermore, as the August 2026 Delhi High Court order demonstrates, the company remains exposed to periodic court-ordered inquiries that consume executive time and generate recurring headline volatility.[^7]
Verdict: the bull thesis holds only in a narrow sense. Direct balance-sheet exposure to an adverse legal judgment appears well contained, confirming the basic premise of operational insulation. Contained balance-sheet risk, however, is not equivalent to strategic immunity. The legal overhang functions as a continuous tax on capital structure efficiency. The single event that would invalidate the cautious view is clear and observable: a Supreme Court ruling that vacates the stay and allows the open offer to proceed. Until that occurs, Fortis must be evaluated as a standalone business funding growth entirely from its own operating cash flows.
To its operational credit, the company has managed to expand effectively under those exact constraints.
VII. The Turnaround Under Dr. Raghuvanshi & IHH (2019–Present)
When Dr. Ashutosh Raghuvanshi took over as Managing Director and CEO of Fortis Healthcare in March 2019, the role was less of a conventional corporate leadership position and closer to a clinical receivership.
Raghuvanshi brought a distinct perspective to the post: he was a cardiac surgeon turned hospital administrator. Trained in cardiothoracic surgery with more than three decades of experience, he had spent roughly eighteen years helping build Narayana Health alongside Dr. Devi Shetty. That Bengaluru-based health system became internationally recognized for lowering the cost of cardiac surgery through high surgical volumes, standardized clinical protocols, disciplined asset utilization, and strict control over consumable expenses.
That background proved vital for Fortis. While Narayana monetized volume and operational efficiency, Fortis relied on clinical acuity and premium pricing. The underlying operational discipline, however, transferred directly. A surgeon accustomed to evaluating operating theatre turnaround times and procedure package costs brought a granular clinical focus to a hospital chain that had been managed for a decade primarily as a speculative financial vehicle.
His mandate from the reconstituted board and IHH aligned with those operational priorities. His executive compensation — approximately ₹10 crore annually — and incentive structure were tied to operating EBITDA growth, revenue per occupied bed, clinical governance metrics, and debt reduction.3 In July 2026, the board reappointed him as MD and CEO for a term extending to March 2029, signaling institutional confidence in the operational trajectory.3 Meanwhile, IHH exercised oversight through non-executive board representation, led by figures such as Dr. Prem Kumar Nair, and by introducing group-wide clinical governance standards.
The Playbook
First, rebuild critical relationships. The most urgent task in 2019 was reputational repair across three core groups whose trust had eroded: senior clinicians deciding whether to remain, medical equipment and consumable vendors determining credit terms, and lenders deciding whether to roll over debt. In hospital operations, these commercial relationships are vital. Losing a top interventional cardiologist does not merely eliminate a salary expense; it permanently severs patient referral networks and high-margin surgical volumes.
Second, undo the financial engineering. In 2019, Fortis completed the buyout of RHT Health Trust's Indian assets for approximately ₹4,650 crore, using capital from IHH alongside new debt facilities. Though it represented a substantial cash outlay during a period of corporate recovery, it proved to be a decisive operational move. The transaction eliminated annual business trust service fees exceeding ₹270 crore and restored direct ownership of physical hospital real estate to the balance sheet, expanding borrowing capacity. While the immediate margin improvement was largely structural, the restored leverage capacity provided the financial foundation for subsequent expansion.
Crucially, repurchasing real estate at market value years after a sale-and-leaseback transaction remains value-destructive compared to retaining ownership from the start. The RHT buyout repaired structural damage rather than generating fresh equity value, with the financial burden historically borne by original shareholders.
Third, focus the portfolio. Fortis divested or closed the remaining overseas assets and underperforming peripheral facilities, concentrating resources on regional hospital clusters where the chain held strong market density.
What the Numbers Say
The financial recovery reflects this operational pivot. In FY2018, at the trough of the corporate crisis, Fortis recorded a consolidated net loss of approximately ₹934 crore on revenue of roughly ₹4,561 crore, with operating margins compressed into mid-single digits and net leverage exceeding 4.5 times EBITDA.
By FY2026, the company reported consolidated revenue of approximately ₹9,128 crore — up roughly 17% year on year — with operating EBITDA reaching about ₹2,085 crore and a consolidated operating EBITDA margin of 22.8%, led by the hospital segment at 22.2%.1 Over the same period, net debt to EBITDA declined below 0.6 times.
Translating these figures into operational terms reveals the drivers of performance. Consolidated revenue roughly doubled over eight years — a solid expansion, though broadly in line with Indian private healthcare growth driven by rising medical insurance adoption and post-pandemic demand normalization. The primary accomplishment lies in margin expansion, which stemmed from three distinct factors: the one-time structural elimination of RHT lease fees; the operational ramp-up of previously underutilized beds toward steady-state occupancy; and an ongoing increase in revenue per occupied bed driven by a strategic shift toward complex, high-acuity medical procedures.
This distinction is central to evaluating future earnings growth. The first two margin drivers — real estate restructuring and occupancy normalization — are largely complete. Consequently, future margin expansion over the coming five years depends almost entirely on sustaining the shift toward higher-acuity treatment mix.
Meanwhile, the balance sheet has transitioned from an operational vulnerability into a growth enabler. With net leverage at 0.6 times EBITDA in a capital-intensive industry where bed expansion drives top-line growth, Fortis can fund new capacity through internal cash flow. Given the Supreme Court stay restricting capital transactions with its majority sponsor, self-funded expansion remains the primary path forward.
VIII. Core Hospital Economics & Competitive Landscape (7 Powers & 5 Forces)
Strip away the branding and a private hospital is a machine controlled by a small number of operational dials. Understanding Fortis — or Apollo, or Max — requires focusing on four primary metrics.
ARPOB is average revenue per occupied bed per day. It represents the pricing dial and is driven overwhelmingly by clinical specialty mix. A patient admitted for an uncomplicated procedure generates a fraction of the daily revenue of a patient undergoing robotic oncological surgery or a liver transplant. Fortis has driven ARPOB from roughly ₹41,000 per day around FY2019 to above ₹62,000 per day in FY2026 — mid-single-digit compound annual growth, of which only part reflects inflation.1 The remainder stems from case-mix migration toward high-acuity specialties such as oncology, neurosciences, organ transplants, and robotic surgery.
Occupancy is the utilization dial, where higher rates are not inherently superior. Fortis operates in the 65% to 70% range. Pushing significantly beyond that threshold limits a facility's capacity to admit emergency and high-acuity cases that generate the strongest economics. A hospital running at 90% occupancy on low-acuity care yields lower returns than one operating at 68% occupancy with an active transplant program.
ALOS — average length of stay — is the throughput dial, moving inversely to intuition. Fortis has compressed ALOS from around 3.6 days toward roughly 3.1 days, primarily by expanding minimally invasive and laparoscopic procedures. Shorter stays allow each bed to serve more patients annually, raising revenue per bed even under flat pricing. It functions as the healthcare equivalent of inventory turnover.
Payor mix serves as the margin dial and carries the highest regulatory sensitivity. Government scheme patients — under Ayushman Bharat or the ECHS for armed forces personnel — are treated at fixed tariffs that sit 15% to 20% below private commercial rates. Cash-paying patients and those covered by private health insurance yield substantially higher realizations. Every private hospital chain in India continuously optimizes this balance, though over-indexing on private payors introduces reputational and regulatory exposure.
Brownfield Versus Greenfield
Fortis currently operates roughly 4,500 beds across 27 facilities. Its stated plan is to add approximately 1,800 beds between FY2027 and FY2030 at a cadence of 400 to 500 beds per year, expanding its total bed capacity with backing from IHH.1
Crucially, the majority of these additions are brownfield expansions — new towers and additional floors built at existing operational hospitals. The economic contrast between brownfield and greenfield expansion is stark. Brownfield capacity historically costs between ₹70 lakh and ₹90 lakh per bed, compared to ₹1.5 crore to ₹2 crore per bed for greenfield projects. Furthermore, brownfield beds achieve financial payback in two to three years, whereas greenfield facilities require five to seven years.
This capital efficiency is driven not by lower construction costs, but by shared infrastructure. An additional bed at an existing hospital immediately leverages centralized assets: intensive care units, operating theatres, imaging suites, pathology laboratories, administrative oversight, hospital accreditations, operating licenses, and established clinical referral networks. A greenfield hospital must construct these capabilities from scratch and spend several years building doctor and patient volume. Consequently, incremental returns on invested capital for brownfield beds far exceed those of greenfield builds, leading major Indian hospital operators to adopt the same expansion model.
For the same reason, brownfield expansion does not constitute an exclusive competitive moat. Max Healthcare, Apollo Hospitals, and Medanta are executing identical brownfield strategies, frequently within the same metropolitan markets.
Cluster Density
Fortis's operational footprint is geographically concentrated across key regional hubs: the National Capital Region (including FMRI in Gurugram, Noida, Shalimar Bagh, and Faridabad), Punjab (Mohali and Ludhiana), Bengaluru, Kolkata, and Mumbai's Mulund facility. The NCR market alone generates over 45% of total hospital revenues.
High cluster density offers clear operational advantages: it facilitates internal patient referral flows across facilities, allows clinical specialists to cover multiple sites, and concentrates regional marketing spend. However, it also creates significant geographic concentration risk. A local pricing intervention, regulatory mandate, or aggressive competitive expansion in Delhi-NCR directly impacts nearly half of Fortis's revenue base. Delhi-NCR is simultaneously the primary expansion target for Max Healthcare, Medanta, Apollo, and Manipal.
The 7 Powers, Honestly Applied
Process Power — valid, but narrowly scoped. High-acuity quaternary programs, such as organ transplantation at FMRI Gurugram, represent organizational capabilities built over years: coordinated teams of surgeons, intensivists, anesthetists, transplant coordinators, and standardized clinical protocols operating at sufficient case volume to maintain proficiency. Competitors cannot replicate this system simply by hiring an individual clinician, as the broader institutional infrastructure remains at the facility. This clinical depth is the primary driver of Fortis's ARPOB expansion.
Scale Economies — moderate and secondary. Centralized procurement for medical consumables, diagnostic imaging equipment, and pharmaceutical distribution yields modest cost savings. However, at roughly 4,500 beds, Fortis is smaller than Apollo's network of over 10,000 beds, meaning pure scale benefits accrue more strongly to larger peers.
Cornered Resource — significant, but market-constrained. Fully permitted real estate suitable for major multi-specialty hospitals in Tier-1 locations like Gurugram, Noida, and Mohali is difficult to acquire at viable valuations. Fortis's existing metropolitan land parcels represent non-replicable assets that make brownfield expansion economically compelling.
Switching Costs — asymmetric across doctors and patients. Patient switching costs remain low, as patients typically follow individual physicians or insurance network coverage rather than hospital brands. Switching costs are higher for senior physicians. A consultant who has built a mature practice supported by a specialized clinical team, familiar equipment, and an established referral network faces friction when moving to a competing facility. Hospitals defend against clinician departures through competitive revenue-sharing arrangements and investments in advanced medical technology, such as surgical robotics and radiotherapy systems, which smaller facilities cannot fund.
Counter-Positioning — non-existent. Fortis operates under the same structural model as Apollo and Max. Every major Indian hospital chain is pursuing the same strategy: metro cluster density, high-acuity case mix, brownfield bed additions, and ARPOB expansion. The business model features no unique operational choices that incumbents are unable or unwilling to copy. Fortis relies on established asset quality rather than a differentiated business model.
Porter, Compressed
Supplier power is high, driven primarily by specialized physicians. Star clinicians in high-acuity specialties command revenue shares that can reach a fifth or more of professional fees, establishing a structural ceiling on operating margins across the Indian hospital sector.
Buyer power is moderate to high and expanding. Institutional payors and private insurers negotiating package rates gain leverage as commercial insurance penetration increases. Additionally, price controls imposed by the National Pharmaceutical Pricing Authority on high-margin medical devices, such as cardiac stents and orthopedic implants, demonstrate ongoing regulatory pricing intervention.
Threat of new entrants remains low in Tier-1 metropolitan markets due to real estate costs and capital requirements, but is higher in Tier-2 cities where land is available and Fortis has a limited operational presence.
Threat of substitutes for complex tertiary and quaternary inpatient care is negligible, as high-acuity surgical procedures cannot be replaced by outpatient or digital alternatives.
Industry rivalry remains intense and is concentrated in the metropolitan markets where Fortis operates its core facilities.
Where Fortis Sits
Based on FY2026 estimates across listed peers: Apollo Hospitals leads in total scale with over 10,000 beds, operating EBITDA margins in the 23% to 24% range, and ARPOB near ₹58,000, complemented by an extensive pharmacy network and digital health operations. Max Healthcare delivers industry-leading margins and realizations, operating roughly 4,300 beds with EBITDA margins in the 26% to 27% range and ARPOB near ₹75,000, driven by its concentrated footprint in premium NCR locations. Medanta operates approximately 2,800 beds at 24% to 25% margins, focused on high-acuity quaternary procedures. Narayana Health operates a volume-focused model with roughly 6,000 beds, 21% to 22% margins, and ARPOB near ₹38,000, demonstrating the viability of high-throughput operational models.
Fortis ranks third in total bed scale and sits in the middle of the peer group on operating margins. The most direct operating comparison is Max Healthcare, which maintains a similar bed count in overlapping geographic markets while generating roughly 400 basis points higher EBITDA margins and 20% higher revenue per bed. That performance gap highlights remaining operational upside for Fortis, while confirming that its facility network, though financially sound, continues to lag best-in-class peer execution.
IX. Hidden Business: Agilus Diagnostics & Private Equity Optionality
In May 2023, a diagnostics business operating more than 400 laboratories and thousands of collection points across India rebranded.4
SRL Diagnostics — long one of India's most prominent pathology brands alongside Dr Lal PathLabs and Metropolis Healthcare — was renamed Agilus Diagnostics. While management cited standard corporate repositioning, the move addressed a deeper vulnerability: SRL originally stood for Super Religare Laboratories. The brand carried in its initials the name of the financial services group at the center of the Singh family siphoning scandal. In healthcare diagnostics, where product value rests entirely on trust in a laboratory report, association with corporate fraud represents an operational liability rather than a simple public-relations issue.
Agilus remains central to Fortis's financial and operational model. In FY2026, the unit generated gross revenue of approximately ₹1,527 crore — representing roughly one-sixth of consolidated revenue — while delivering operating EBITDA margins of 23.6%, slightly exceeding the hospital division's profitability.1 The business generates cash flow with significantly lower capital intensity than hospital beds, provides operational synergy by managing pathology across Fortis facilities, and houses an expanding specialized genomics and esoteric-testing portfolio where pricing power remains defensible.
The PE Knot
For years, private equity investors — including the International Finance Corporation, NYCA Partners, and Resurgence Fund — held a combined 31% minority stake in Agilus dating back to the Religare era. The investors sought an exit starting around 2021 through an initial public offering or a trade sale. Neither materialized on schedule: public market valuations for Indian diagnostics firms compressed post-pandemic, while a trade sale risked transferring a major stake in Fortis's primary pathology partner to a competitor.
Fortis resolved the deadlock by buying out the investors, agreeing to acquire the 31% stake for approximately ₹1,780 crore and restoring Agilus as a fully consolidated, majority-controlled subsidiary.
The operational logic was clear: a hospital operator benefits from maintaining corporate control over the entity managing its clinical pathology. Yet the transaction also represented another major capital allocation required to resolve legacy ownership structures. Combined with the earlier repurchase of Religare Health Trust's real estate assets, Fortis has committed thousands of crores under post-2018 management simply to dismantle structural arrangements established by its former promoters. While the balance-sheet cleanup was necessary, it consumed capital that would otherwise have funded core expansion.
Falsifying the Optionality Thesis
The claim: Agilus provides high-margin, capital-light growth optionality on top of an asset-heavy hospital platform, and an eventual standalone listing represents substantial unpriced equity value.
The disconfirming evidence. Following post-COVID normalization, the Indian diagnostics sector faced margin pressure from three concurrent forces: online aggregators such as Tata 1mg and PharmEasy offering discounted test bundles for customer acquisition; digital-first diagnostic entrants operating at loss-leading price points; and persistent competition from unorganized local laboratories. Industry operating EBITDA margins across listed peers compressed from historical highs near 30% into the low 20% range before stabilizing.
More fundamentally, the economic comparison between diagnostics and tertiary hospitals breaks down on structural grounds. Pathology testing lacks the competitive moats inherent in hospital operations: it features no bed-capacity constraints, no prime metropolitan land holdings, and minimal switching costs, as accredited laboratory tests are highly standardized and driven primarily by physician referral. While diagnostics requires less capital to build, it commands weaker pricing power. On an incremental return-on-capital basis, adding a brownfield hospital bed in Gurugram for ₹80 lakh with a sub-three-year payback offers superior risk-adjusted economics compared to standalone laboratory expansion.
Verdict: the thesis is narrowed rather than rejected outright. Agilus is a viable operational division — cash-generative, clinically integrated with the hospital network, and positioned in specialized testing. It does not, however, represent high-growth software-like optionality or warrant valuation as a structurally insulated franchise. The relevant test going forward is specific and observable: whether Agilus can maintain operating EBITDA margins above 22% while expanding revenue at or above the organized diagnostics industry growth rate over the coming years. Sustaining those thresholds validates the integrated operational model; resuming margin compression would relegate the business to a mature cash generator within a broader hospital enterprise.
X. Playbook: Business & Capital Allocation Lessons
1. Governance failure destroys equity value faster than it destroys asset value — but only if the assets are genuinely irreplaceable. Fortis lost the overwhelming majority of its market capitalization, its founders, its clean audit opinion, and its access to credit. It did not lose the Escorts cardiac franchise on Okhla Road or the transplant program at FMRI Gurugram, because those were built on clinical talent, procedure volume, and accumulated reputation that corporate fraud could not erode. The critical qualifier is irreplaceable. A commoditized business facing the same crisis simply collapses. The lesson is not to acquire fraud-distressed companies; it is to separate asset quality from corporate governance quality, recognizing that a turnaround option exists only when the underlying assets cannot be easily duplicated by a competitor.
2. Brownfield expansion is the highest-return capital deployment available in Indian healthcare, and it is available to everyone. Adding a tower to an existing hospital generates incremental returns far above greenfield developments because the primary infrastructure investments are already capitalized. This represents both an economic reality and a strategic constraint: because every disciplined operator executes the same playbook, brownfield expansion is table stakes rather than a proprietary competitive moat. The ultimate advantage belongs to operators possessing expandable real estate in supply-constrained metropolitan markets.
3. Asset-light financial engineering in a capital-intensive, cyclically utilized business converts flexible operational risk into rigid contractual obligations. The Religare Health Trust (RHT) structure appeared defensible on paper but proved destructive in practice. The test for any asset-light vehicle — whether a sale-and-leaseback, yield co, infrastructure investment trust, or opco-propco structure — is straightforward: stress-test fixed service charges against trough operating cash flows during a facility's weakest operational year, rather than relying on average projections. Fortis failed that test, ultimately deploying roughly ₹4,650 crore to dismantle the structure and buy back its real estate.
4. The operator-versus-owner distinction is real and measurable. The Fortis turnaround was led by an executive whose background was built on optimizing surgical throughput, operating under an incentive structure tied to margin expansion, revenue per occupied bed, and debt reduction rather than top-line revenue growth or aggressive deal-making. That behavioral shift is evidenced by what did not occur after 2019: no speculative international ventures, no complex financial engineering, and no large diversifying acquisitions. Management focused strictly on deleveraging, repurchasing alienated assets, and executing brownfield bed additions. Disciplined execution across seven years of financial filings provides the most reliable management signal available to investors.
5. Strategic patience by a foreign parent is not equivalent to a successful investment outcome. IHH has navigated eight years of court stays, contempt proceedings, forensic audits, and cross-border litigation without exiting, extracting operational improvements along the way. Yet whether that long-term posture yields a full financial return remains subject to judicial rulings rather than operational execution. Investors should avoid mistaking an unresolved legal impasse for a validated strategic triumph.
XI. Investor Analysis: The Investment Spine & Bull vs. Bear Case
Why Win
The affirmative case for Fortis Healthcare rests on four distinct pillars, each supported by varying degrees of operational evidence.
The strongest pillar is the company's asset position: premier tertiary hospitals situated on prime real estate across New Delhi-NCR, Mumbai, Bengaluru, Kolkata, and Punjab. These metropolitan footprints cannot be replicated under current land costs and municipal permitting timelines. This advantage is demonstrated rather than merely asserted, as competing chains are similarly prioritizing brownfield expansions over building new flagship urban facilities.
The second is the brownfield growth runway: a plan to add approximately 1,800 beds through FY2030 at existing facilities, funded entirely through internal accruals while maintaining net leverage below 0.6 times EBITDA. The capital is available and the underlying unit economics are favorable. However, an execution gap remains: the strategy requires commissioning 400 to 500 beds annually, an operational cadence Fortis has yet to sustain over multiple consecutive years.
The third is ARPOB expansion through acuity migration, which represents the primary remaining structural driver of margin expansion and is backed by a multi-year operational track record.
The fourth, and least persuasive from an investment perspective, is IHH sponsorship — an asset that enhances clinical protocols and governance standards, but remains financially constrained by ongoing litigation.
Why Not
The bear case relies on observable operational and legal realities rather than market speculation.
The legal entrapment is indefinite. The Supreme Court stay has held for nearly eight years with no resolution date, and the September 2026 Special Leave Petition challenging the Delhi High Court's forensic audit order demonstrates that new legal proceedings continue to originate.[^7] Holding Fortis shares means owning an enterprise whose underlying governance structure remains tied to external judicial timelines.
Clinician cost inflation caps margin expansion. With star specialists commanding revenue shares of up to 20% or more of professional fees in competitive specialties, and with Max, Medanta, and Apollo actively recruiting across the same New Delhi-NCR talent pool, bridging the gap from operating margins of roughly 23% toward Max Healthcare's 26% to 27% level is not simply a function of executive resolve. It depends on labor market dynamics in which Fortis does not set prevailing compensation rates.
Bed rollout execution risk remains concrete. Commissioning new hospital towers in Faridabad, Noida, and Gurugram involves construction delays, municipal approvals, and an initial ramp period during which new capacity dilutes occupancy and margins before reaching profitability. Major hospital operators routinely encounter scheduling slippages during multi-year expansion cycles.
Regulatory pricing intervention represents an ongoing exposure. The National Pharmaceutical Pricing Authority has previously imposed price ceilings on cardiac stents and orthopedic implants. Extending price caps to additional categories of medical consumables or implantable devices would directly impact high-margin operational lines.
Easy turnaround gains are exhausted. Eliminating RHT lease fees provided a one-time structural reset, and post-pandemic bed occupancy normalization is largely complete. Future earnings growth depends on incremental case-mix optimization and cost management against rising operational expenses.
The Activist's Questions
A skeptical institutional investor analyzing Fortis today would focus on three primary issues.
First, the complexity discount: a hospital network housing a sizeable diagnostics subsidiary, an unresolved parent ownership structure, and lingering litigation warrants a valuation haircut. Furthermore, buying out minority private equity holders in Agilus consolidated corporate control while eliminating the near-term prospect of a separate, value-crystallizing public listing.
Second, the reinvestment discipline question: management has deployed substantial capital twice — repurchasing RHT real estate assets and acquiring Agilus minority stakes — to unwind legacy promoter structures rather than add clinical bed capacity. Skeptical investors will expect future cash flows committed strictly to bed expansion, supported by disclosed project-level return targets and commissioning dates.
Third, disclosure granularity: current financial reporting lacks cluster-level breakdowns for occupancy, revenue per occupied bed, and operating margins, preventing outside investors from evaluating how heavily New Delhi-NCR facilities support consolidated earnings.
Against these critiques, management has established credibility by delivering on its public commitments regarding balance-sheet deleveraging, margin expansion, and non-core asset divestments across seven years of financial disclosures. Maintaining narrative transparency while operating under structural legal constraints provides a reliable indicator of institutional discipline.
The Three KPIs
One — ARPOB growth and underlying specialty mix. Investors must monitor the proportion of total revenue derived from high-acuity fields, including oncology, organ transplants, neurosciences, and robotic surgery. This shift represents the primary driver of structural margin expansion and serves as the benchmark for clinical execution.
Two — annual bed commissioning rate and time to 60% occupancy. The long-term growth thesis relies on operational delivery. Announced capacity additions carry little weight until beds are commissioned and ramped on schedule. Commissioning over 400 beds annually while achieving target occupancy within 18 months validates the expansion plan; repeated timeline extensions invalidate it.
Three — the hospital EBITDA margin gap relative to Max Healthcare. This metric currently sits at roughly 400 basis points. The spread reflects execution efficiency, payor-mix management, clinician cost control, and case-mix acuity against the company's most direct peer in overlapping geographic markets. Narrowing the gap confirms operational progress; widening it indicates that strong clinical assets are being constrained by suboptimal execution.
XII. Epilogue & Strategic Outlook
The trajectory of Fortis Healthcare spans nearly nine decades — from a Delhi pharmaceutical distributorship named after two cousins, to the generic drug pioneer that brought Indian medicine to global markets, through an international arbitral award that exposed hidden liabilities, to a hospital chain built on transaction proceeds and drained by promoter obligations, and finally to a Malaysian operator holding a 31.1% controlling stake under an ongoing judicial stay.
What survived that corporate collapse was the underlying clinical asset base: premier tertiary hospitals operating high-acuity medical programs, supported by established physician networks, and anchored on real estate in supply-constrained metropolitan markets.
That evolution mirrors a broader structural shift across Indian healthcare. The sector continues to consolidate from a fragmented network of promoter-driven nursing homes into institutional multi-specialty chains backed by professional management, institutional capital, and standardized clinical governance. Fortis represents the most extreme case of this transition — executing the shift not through a gradual corporate restructuring, but through balance-sheet failure, executive arrests, and court-supervised stabilization.
The strategic outlook for Fortis hinges on four operational and legal variables: whether judicial rulings eventually allow IHH Healthcare to execute its open offer and secure majority control; whether the planned 1,800 brownfield beds are commissioned and monetized on schedule; whether the operating margin gap against top-tier regional competitors narrows; and whether high-acuity case-mix growth can continue to lift average revenue per occupied bed faster than clinician compensation costs rise.
Ultimately, the resolution of these challenges will not be determined by the narrative of corporate recovery. It will be decided quarter by quarter by underlying operating metrics — the definitive measure of performance for one of modern Indian business's most complex corporate sagas.
References
-
Fortis Healthcare Investor Relations Portal — Fortis Healthcare Limited ↩↩↩↩
-
Tokyo District Court Dismisses IHH Subsidiary Claims Against Daiichi Sankyo — Business Standard, 2026-09-10 ↩
-
Dr. Ashutosh Raghuvanshi Reappointed MD & CEO of Fortis Healthcare — Business Standard, 2026-07-24 ↩↩
-
SRL Diagnostics Rebrands to Agilus Diagnostics — Agilus Diagnostics ↩
-
Singh Brothers Sentenced for Contempt of Supreme Court Order in Daiichi Case — India Today, 2019-11-15 ↩↩↩↩
-
Fortis Healthcare Financial Results & Annual Reports — BSE India ↩
 LinkedIn
 WhatsApp
 Reddit
 Hacker News
 Email
 Kindle
 RSS Feed
 Spotify
 Apple Podcasts
 Amazon Music
 Audible
 YouTube