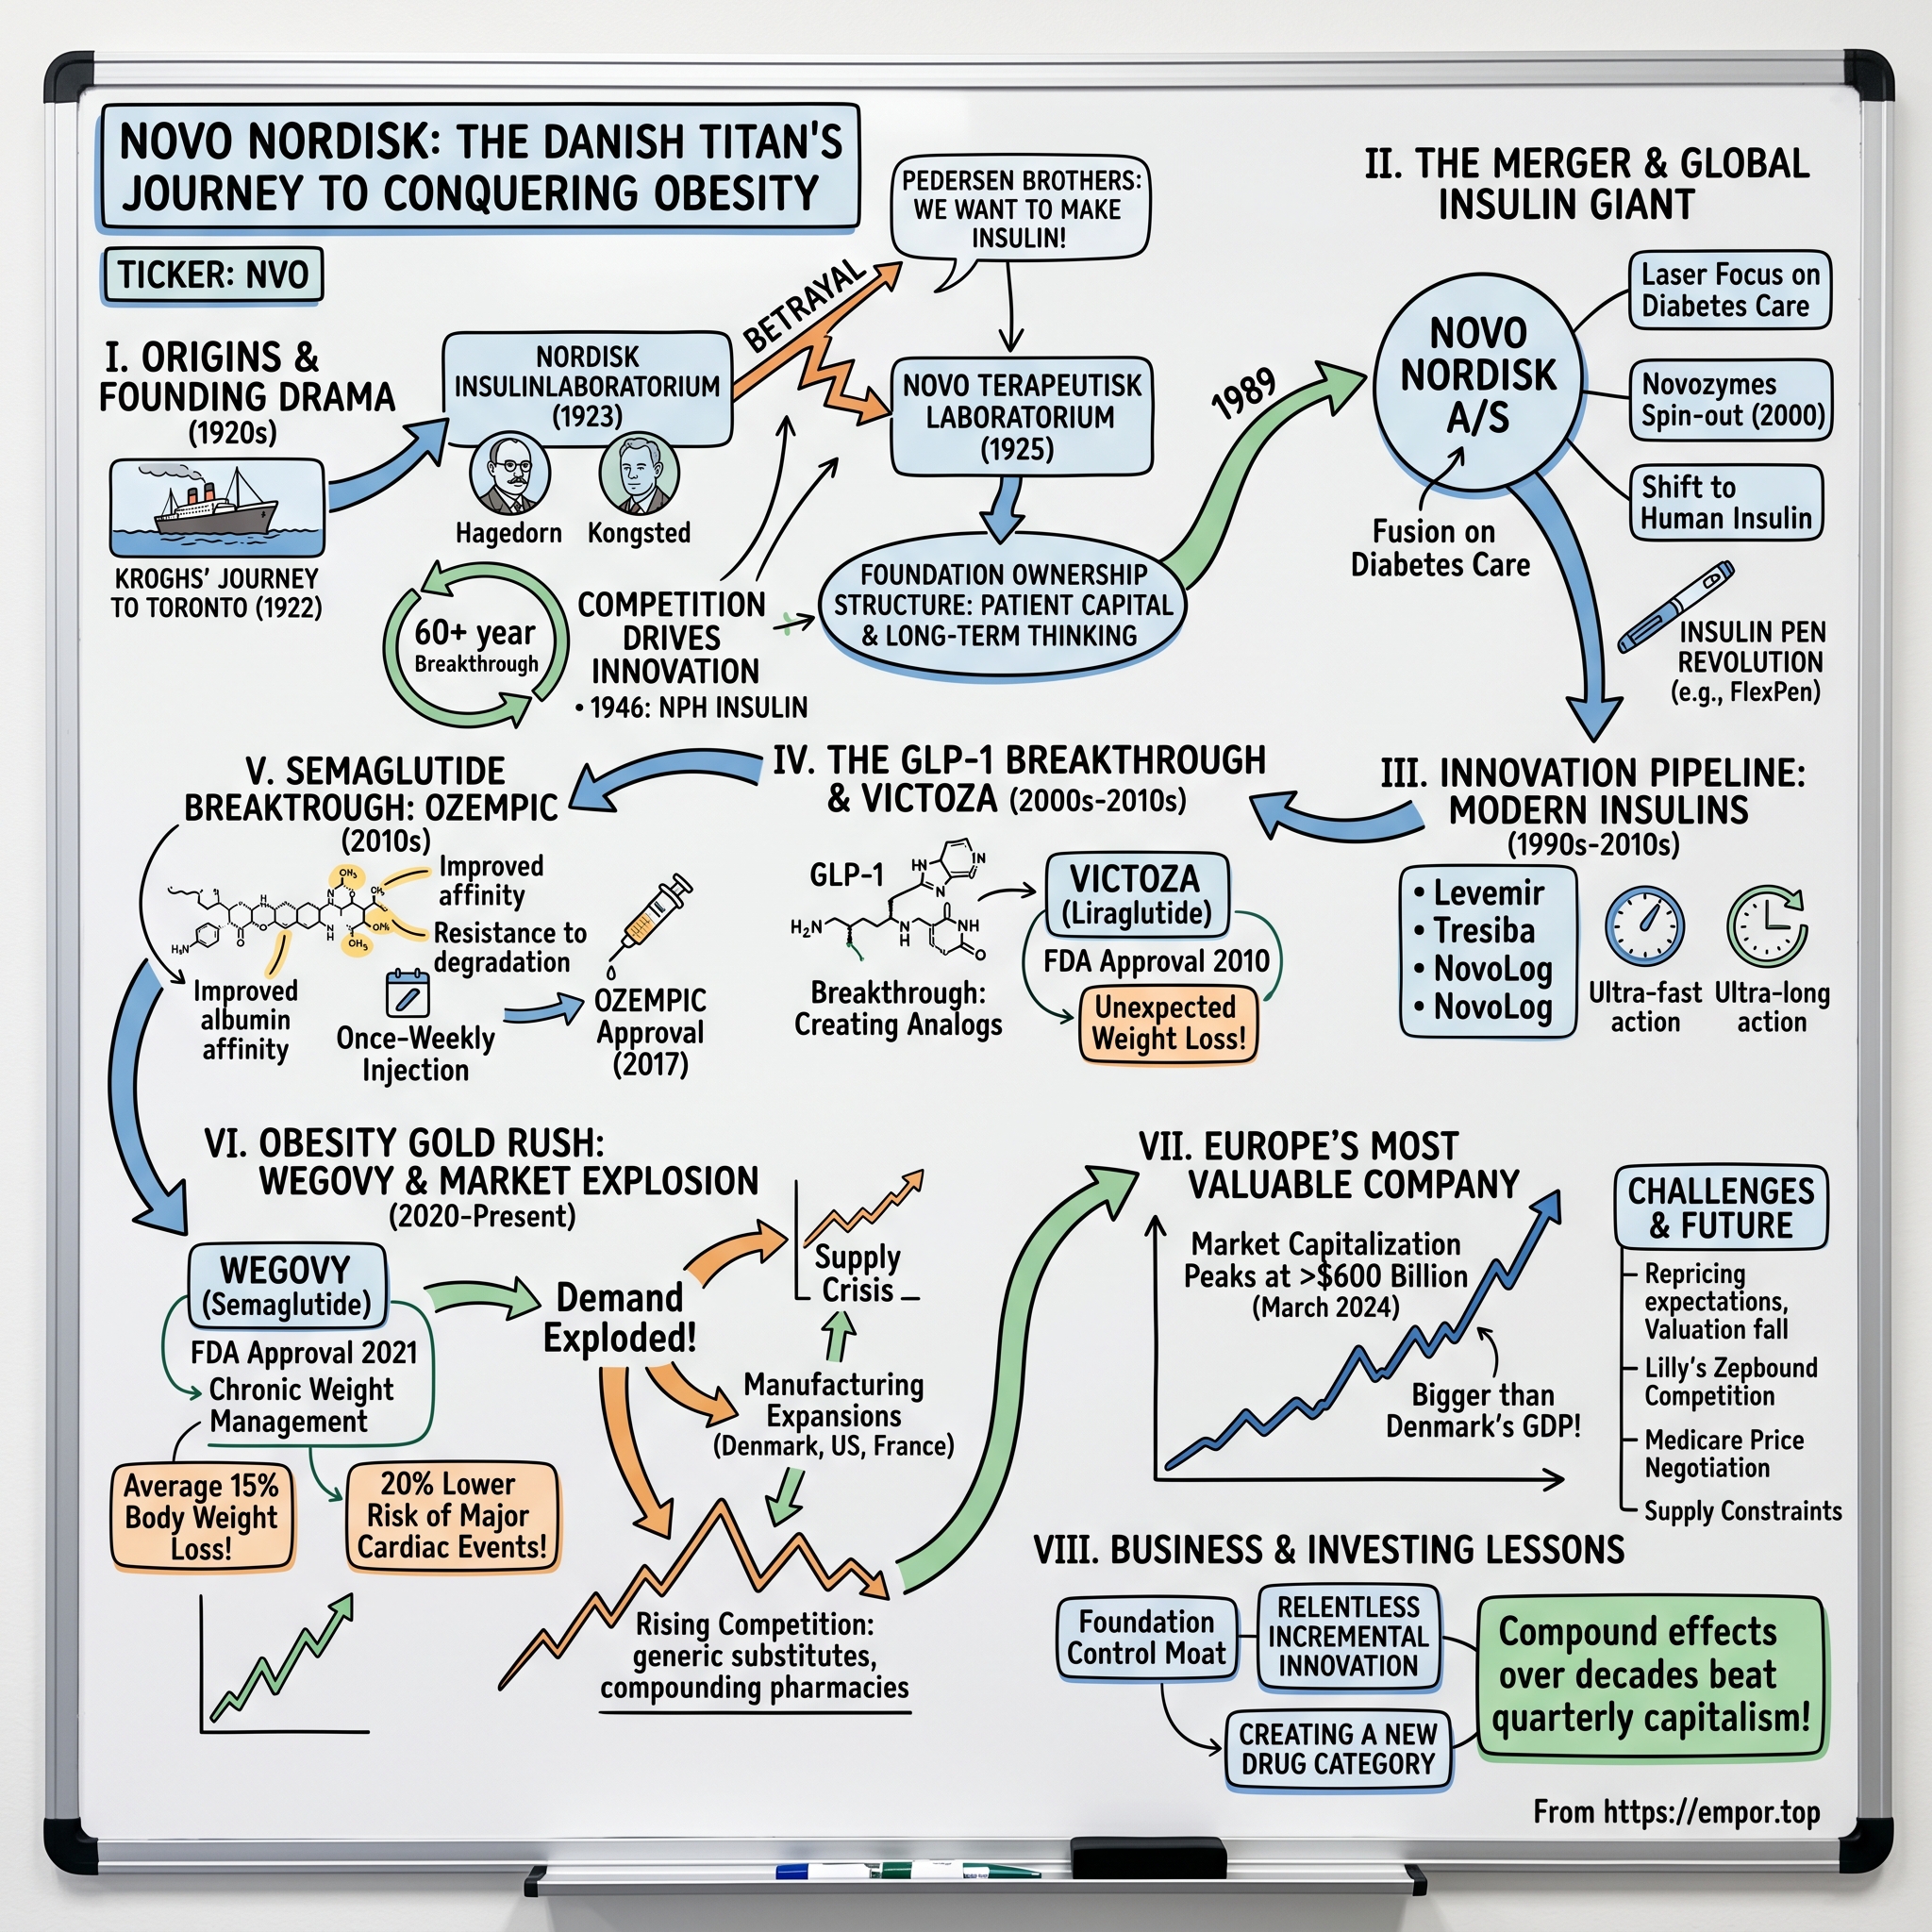
Novo Nordisk: How the Company That Invented Obesity Drugs Lost Control of the Story
I. Introduction & Episode Roadmap
In June 2024, a share of Novo Nordisk traded just under €140 in Frankfurt. The Danish company that makes semaglutide had become the most valuable listed business in Europe, a single molecule had rewritten the economics of an entire industry, and the joke in Copenhagen was that Denmark's national accounts now had a pharmaceutical sector attached to them rather than the other way around.
On the morning of February 4, 2026, that same share traded around €40.1
Nothing had blown up. There was no fraud, no recall, no plant fire, no patent invalidated by a court. Novo Nordisk sold DKK 309 billion of medicine in 2025 — roughly $45 billion — grew sales 10% at constant exchange rates, and earned an operating profit of DKK 128 billion.2 Those are the financials of a company most managements would trade places for. And yet the market took roughly 70% off the equity, the chief executive was gone, the chairman and six independent directors were gone, and a company whose entire brand was patient, century-long Danish discipline had cut nine thousand jobs in a single announcement.3
This is a story about what happens when a business gets everything right for a decade and then discovers that the thing it built was not as defensible as everyone — including its own management, its own board, and its own controlling foundation — had assumed.
The mechanics are worth stating plainly up front, because the narrative around Novo Nordisk in 2026 tends to collapse into "obesity drug company falls to earth," which is both true and useless. Four things happened, roughly at once. The next-generation drug that was supposed to succeed semaglutide, CagriSema, produced trial data that disappointed the market and later lost a head-to-head trial against Eli Lilly's product outright.45 The company's guidance — historically conservative, historically beatable — was cut three times in 2025 on the sales line and once more on profit, destroying a reputation it had spent two decades building.63 The controlling shareholder, the Novo Nordisk Foundation, forced out a chief executive and then a majority of the board, over the sitting board's objections, in a governance sequence that minority investors could observe but not influence.78 And the United States government, Novo's largest and most profitable market, negotiated a structural repricing of the entire GLP-1 category that the company has now guided will cut Wegovy's list price roughly in half from the start of 2027.910
Then, on September 4, 2026 — four days before this was written — an independent data monitoring committee told Novo Nordisk to stop two more Phase 3 trials of ziltivekimab, the anti-inflammatory antibody that was the company's single largest bet on building a third therapeutic franchise beyond diabetes and obesity.1112
The roadmap from here: a century of Danish insulin rivalry and the foundation structure that still holds 77% of the votes; the accidental discovery inside a diabetes drug that appetite could be engineered; the supercycle and the $16.5 billion manufacturing deal made at the top of it; the CagriSema readout that broke the story; the boardroom reckoning; the competitive war with Eli Lilly that Novo is currently losing on value and winning on volume; and an honest reckoning with whether foundation control is the long-term advantage it has always been marketed as.
Start where the whole thing started: with a Danish physiologist, his physician wife, and a plane ticket to Toronto.
 Subscribe on LinkedIn
II. Origins: The Danish Insulin Wars and the Foundation Structure That Still Runs the Company
In 1922, August Krogh was a Nobel laureate physiologist and his wife Marie was a physician with type 2 diabetes. When they travelled to North America and learned that researchers in Toronto had isolated insulin, the professional interest was not abstract. Marie Krogh's own condition was, at the time, a slow death sentence. The Kroghs secured permission to produce insulin in Scandinavia, and in 1923 — with Hans Christian Hagedorn, whom Marie personally recruited — they founded Nordisk Insulinlaboratorium.13
Two years later, two brothers who had worked at Nordisk, Harald and Thorvald Pedersen, left to start a competitor called Novo Terapeutisk Laboratorium.13 Danish corporate history is full of polite institutions; this was not one of them. For six decades the two firms sat within a few kilometres of each other in the Copenhagen suburbs, competing on the same molecule for the same patients, each convinced the other was doing it wrong.
That rivalry produced something more durable than either company. Insulin is not a pill. It is a protein that must be fermented, purified, formulated into a suspension with predictable release characteristics, filled into a sterile container without contamination, and delivered into a patient's body by that patient, at home, several times a day, for the rest of their life. Every one of those steps is a manufacturing problem rather than a chemistry problem. Nordisk's NPH insulin in 1946 — a formulation that slowed insulin's absorption so it lasted longer — was a formulation-science achievement, not a discovery.13 The insulin pen, which Novo commercialised in 1985, was a device engineering achievement.13
This matters because it explains what Novo Nordisk actually is. It is not, and has never been, primarily a molecule-discovery company in the mould of a Merck or a Pfizer. It is a protein manufacturing and delivery-device company that happens to own extraordinary molecules. Almost everything good and bad that has happened to it since 2021 flows from that identity.
The two companies merged in 1989 to form Novo Nordisk A/S. What merged alongside them was more consequential than the operating businesses: Nordisk's foundation, established in the 1920s, and Novo's, established in 1951.13 Today the combined Novo Nordisk Foundation controls the company through a holding vehicle, Novo Holdings A/S, which at the end of 2025 held roughly 28.1% of Novo Nordisk's share capital and 77.3% of its voting rights.14 The mechanism is a dual-class structure: unlisted A shares carry ten votes each, listed B shares carry one, and the Foundation's own articles require it to keep a voting majority in A shares and at least a quarter of the share capital.14
For thirty years this structure has been marketed — by the company, by Danish business commentators, and by a fair number of investors who should have read the articles of association more carefully — as the source of Novo Nordisk's long horizon. The argument is intuitive. A controlling owner whose purpose is philanthropic rather than financial cannot be raided, cannot be pressured into a bad merger, and can fund a twenty-year research programme without a quarterly earnings call punishing it. The Foundation distributed roughly DKK 10 billion for scientific, humanitarian and social purposes in 2024 alone.14 The Steno Diabetes Center — formed when the two rivals merged their diabetes hospitals in 1992 — and the spin-out of the enzymes business as Novozymes in 2000 are both cited as evidence of an owner willing to reshape assets on a decadal clock rather than an annual one.13
Hold that claim in mind. It is the single most-repeated structural argument for owning this stock, and Section VIII tests it against what the Foundation actually did in the autumn of 2025 — which was to demonstrate, in public, that the same voting power that insulates management from the market also insulates the controlling shareholder from everyone else.
For now, the relevant inheritance is narrower: a century of protein manufacturing discipline, a rivalry-hardened formulation culture, and an owner with the balance sheet to fund whatever the scientists asked for. That combination was about to meet a molecule nobody had planned for.
III. Building the Global Insulin and GLP-1 Giant (1989–2017)
The merged company spent the 1990s and 2000s doing something unglamorous extremely well: converting insulin from a commodity extracted from pig pancreases into a portfolio of engineered analogs, each with a different absorption curve, each delivered through a proprietary pen.
The strategic logic was switching costs, built patient by patient. A person with type 1 diabetes who has learned to dose NovoLog before meals and Levemir at night, using a device whose click-feel and dial they know in the dark, does not casually switch. Their endocrinologist does not casually switch them either. Payers negotiated hard on price, but the installed base was sticky in a way that few pharmaceutical franchises are, because the product was a daily behavioural routine rather than a prescription refilled quarterly.
Then came the gut hormones.
Here is the mechanism in plain terms. When you eat, your small intestine releases a hormone called glucagon-like peptide-1 — GLP-1 — which does three useful things at once. It tells the pancreas to release insulin, but only when blood sugar is actually elevated. It slows the rate at which the stomach empties. And it signals the brain that you are full. Evolution built a single molecule that handles both blood-sugar control and appetite. The problem is that natural GLP-1 is destroyed in the bloodstream within a couple of minutes, which makes it useless as a drug.
The entire GLP-1 industry is therefore an engineering exercise: take the natural peptide, modify it enough to survive in the body for hours or days, but not so much that it stops working. Novo Nordisk's first serious answer was liraglutide, marketed as Victoza and approved in 2010 — a once-daily injection that competed against early entrants from Amylin and Eli Lilly.
Victoza also produced the first genuinely uncomfortable episode in Novo Nordisk's modern record, and it belongs here rather than buried in a risk footnote. Because rodent studies had shown a signal for a rare thyroid cancer, the FDA required a Risk Evaluation and Mitigation Strategy: Novo had to make sure prescribing physicians knew about the risk. In September 2017 the company agreed to pay $58.65 million to resolve US Department of Justice allegations that its sales representatives had done close to the opposite — giving doctors information that created "the false or misleading impression that the Victoza REMS-required message was erroneous, irrelevant, or unimportant."1516 The settlement split into $12.15 million in disgorgement for alleged food-and-drug violations between 2010 and 2012 and $46.5 million for alleged False Claims Act violations through 2014.16 Novo denied wrongdoing.16
The reason to flag a nine-year-old settlement is not moral bookkeeping. It is that the behaviour described — a commercial organisation running ahead of what the label and the science strictly supported, in service of volume — is a recognisable pattern, and it recurs in a different form in Section VI, where the question becomes what investors were and were not told about a trial protocol. One settlement is an incident. A pattern of the commercial and communication function outrunning the clinical facts is a management-quality observation, and it is fair to hold both readings open.
There is a commercial lesson inside the insulin decades that the obesity era later obscured. Novo Nordisk never won on molecule novelty; several rivals had comparable analogs. It won on the boring compounding of small advantages — a pen that a partially sighted elderly patient could dose reliably, a cold-chain that worked in markets with unreliable electricity, a sales organisation that talked to endocrinologists in eighty countries. Those advantages were slow to build and slow to erode, which is exactly the profile of a durable franchise. The obesity franchise that followed had the opposite profile: enormous, fast, and built on a molecular advantage that a competitor could out-engineer. Investors who assumed the second business would behave like the first were extrapolating from the wrong half of the company's history.
By 2017, Novo Nordisk was the world's largest insulin producer with a credible and growing GLP-1 franchise, a strong but unspectacular growth profile, and a share price that had gone essentially nowhere for two years. The company was, in the language of the time, a quality compounder. What happened next was not in anyone's model.
IV. The Semaglutide Supercycle: Ozempic, Wegovy, and the Run to Europe's Most Valuable Company (2012–2024)
The chemistry story is almost boring. Semaglutide is a modified version of natural GLP-1 that retains 94% of its structure — close enough that the body's receptors recognise it, different enough that the enzymes that would normally destroy it cannot. A fatty-acid chain attached to the peptide lets it bind to albumin in the blood, effectively hiding it from clearance. The result was a molecule that could be injected once a week instead of once a day.
Once-weekly versus once-daily sounds like a marketing detail. It is not. For a chronic medication a patient must self-administer forever, cutting injections from 365 a year to 52 changes adherence, which changes outcomes, which changes what payers will pay. Ozempic was approved for type 2 diabetes in December 2017. Two years later Novo did something genuinely difficult: it put the same peptide in a pill. Peptides are digested in the stomach like any other protein, which is why insulin has never been oral. Novo's answer was an absorption enhancer called SNAC, which temporarily raises the local pH in the stomach lining and shepherds a small fraction of the drug across into the bloodstream. Rybelsus, launched in 2019, was the first oral GLP-1 anywhere. It was inefficient — most of the dose is wasted — but it worked, and it required a manufacturing scale that no competitor could casually replicate.
Rybelsus is worth pausing on, because it illustrates the strange economics of this company better than any strategy deck. Because only a small fraction of an oral peptide dose survives the stomach, an oral tablet consumes many times more active ingredient than an injection delivering the same clinical effect. In other words, Novo chose to solve a patient-convenience problem by burning through the scarcest input it had. That was a defensible trade when the constraint was patient willingness to inject. It became a much harder trade once the binding constraint became manufacturing capacity — and it is the single clearest reason why an oral small molecule, which can be made in a conventional chemical plant rather than a fermentation-and-purification facility, is a genuine structural threat to the peptide incumbents rather than merely another competing product.
The part nobody planned for was the weight loss.
Diabetes trials measure HbA1c, a marker of average blood sugar. Weight is a secondary endpoint. In the SUSTAIN and STEP programmes, the secondary endpoint kept walking away from the primary one: patients were losing not two or three percent of body weight but low double digits. Novo Nordisk's institutional instinct — a century of talking to endocrinologists about glycemic control — was to treat this as a helpful side benefit. The culture had no vocabulary for selling appetite suppression, and the industry's history of obesity drugs was a graveyard of withdrawn products and reputational damage.
What forced the pivot was not a strategy offsite. It was patients, prescribers writing off-label, and eventually social media, turning "Ozempic" into a common noun before Novo had a branded obesity product to sell. Wegovy — the same molecule at a higher dose, with an obesity label — was approved in 2021, into a market that the company's own customers had already created for it.
The event that converted obesity from a cosmetic category into a reimbursable one arrived on August 8, 2023. The SELECT trial had followed 17,604 adults over 45 with overweight or obesity and established cardiovascular disease, but crucially without diabetes, for up to five years. Semaglutide 2.4mg cut major adverse cardiovascular events — cardiovascular death, non-fatal heart attack, non-fatal stroke — by 20% versus placebo, with all three components moving in the right direction.17 Novo's development head, Martin Holst Lange, called it a trial that could "change how obesity is regarded and treated."17
He was, on this occasion, right, and the reason is economic rather than clinical. A payer can decline to fund weight loss. A payer cannot easily decline to fund a 20% reduction in heart attacks and strokes in a population it is already paying to treat. SELECT is why obesity drugs got onto formularies, and it is why the 2031–2032 patent expiry on semaglutide matters so much: the trial that made the category valuable was run on the molecule that goes generic.
Then came the supply crisis, which is the part of the story most relevant to what happened next. From 2022 the FDA listed semaglutide as being in shortage. Novo ran its filling lines continuously and still could not meet demand. For roughly two years the binding constraint on the world's fastest-growing pharmaceutical franchise was not science, not regulation, and not competition. It was the number of sterile syringes and pens the company could physically fill.
That is an enviable problem and a dangerous one. Enviable because a demand curve you cannot serve looks, on a spreadsheet, like infinite pricing power. Dangerous because a constraint made of stainless steel and cleanrooms is a constraint any sufficiently capitalised rival can also buy — and because the shortage created an opening for compounding pharmacies, which under US rules may produce copies of drugs in official shortage. A grey market grew up inside the gap between what Novo could make and what patients wanted, and it did not politely disappear when the shortage ended.
By mid-2024 the shares had peaked just under €140 and Novo Nordisk had become Europe's most valuable listed company.1 It is the mark against which everything that follows is measured. And the decision that defined that peak was not a scientific one. It was a capital allocation decision, made at the top of the cycle, about how to buy the one thing the company could not manufacture fast enough: capacity.
V. Capital Deployment at the Top of the Cycle: The Catalent Deal and the Manufacturing Bet
On February 5, 2024, with semaglutide still rationed, Novo Holdings — the Foundation's investment arm, not the operating company — announced it would acquire Catalent, one of the world's largest contract drug manufacturers, for an enterprise value of about $16.5 billion.18 In the same breath, Novo Nordisk announced it would buy three of Catalent's fill-finish plants from its own parent for $11 billion: Anagni in Italy, Brussels in Belgium, and Bloomington, Indiana, together employing over 3,000 people.19 The parent deal closed on December 18, 2024.18
The structure deserves a moment. This was a related-party transaction of unusual size: the controlling shareholder bought a company and immediately sold two-thirds of the purchase price back to the listed entity it controls. There is a coherent commercial logic — Novo Holdings wanted the CDMO business, Novo Nordisk wanted the sterile filling lines, and splitting the asset let each take what it valued. There is also an obvious governance question about price discovery when the buyer and seller share a controlling owner, and the FTC's clearance addressed competition rather than fairness of consideration.
On the price itself, the fair verdict is "reasonable, not cheap." Catalent had spent more than a year as a troubled asset — execution problems, leverage concerns, a depressed share price — before the bid, so $16.5 billion bought a business at a premium to a distressed price rather than at a premium to a healthy one. Novo Nordisk was buying certainty at the exact moment certainty was most expensive to it, which is precisely when buyers overpay. The company itself framed the deal as providing "strategic flexibility."19 Management guided that incremental filling capacity from the sites would arrive "in 2026 and beyond."19
That timing is the crux, and it is where the deal should be benchmarked rather than admired. Eli Lilly faced the identical constraint and chose to build rather than buy, committing to a multi-site US manufacturing programme across 2024 and 2025 on a scale Novo did not match — including, under its own November 2025 agreement with the US administration, at least $27 billion of new US manufacturing investment against Novo's $10 billion.9 Novo also built: a $4.1 billion second fill-finish plant in Clayton, North Carolina, announced June 24, 2024, adding 1.4 million square feet and about 1,000 jobs, with construction running from 2027 to 2029, as part of $6.8 billion of manufacturing capex that year against roughly $4 billion the year before.20
Set the two approaches against what actually happened to demand. Novo bought capacity that began contributing in 2026 — the same year US branded volumes disappointed, realized prices began compressing under the pricing agreement, and the company guided to its first sales decline in nearly a decade.1 The capacity is arriving into a softer market than the one it was underwritten against. That is not the same as saying the deal was wrong: sterile fill-finish lines are fungible across Novo's injectable portfolio, and a company whose entire competitive position rests on manufacturing complexity is not obviously foolish to own more of it. But "we bought guaranteed capacity at the peak" and "we deployed $11 billion against a demand curve that has since bent" are both true, and any account that reports only the first is selling something.
There is a second, sharper capital-allocation episode that tests the same judgment on a shorter fuse. In late October 2025, Novo Nordisk gate-crashed Pfizer's agreed acquisition of Metsera, a 2022-vintage biotech with an injectable GLP-1 heading into Phase 3 and an amylin candidate in Phase 1 — precisely the mechanism class Novo was betting its own next generation on. Novo bid $56.50 per share in guaranteed cash plus up to $21.25 in milestones, valuing Metsera at up to roughly $9 billion.21 Metsera's board judged it superior to Pfizer's offer. Pfizer responded by attacking the deal structure as "an attempt by a company with a dominant market position to suppress competition in violation of law."21 On November 8, Metsera accepted a sweetened Pfizer bid worth about $10 billion, citing antitrust risk in Novo's proposal, and Novo declined to raise again.
Read that sequence carefully, because it cuts both ways. Novo's CEO had told investors he was "confident we will close the deal" shortly before losing it — a specific public prediction that did not survive contact with the outcome.22 Against that, walking away rather than paying a premium into a hostile antitrust review is the more defensible half of the episode. What the failed bid does establish is that Novo Nordisk, in late 2025, was willing to spend up to $9 billion on external innovation in a mechanism it already had in-house — which tells you how the company privately rated its own amylin pipeline.
The capital allocation record, taken as a whole, is neither the disciplined-compounder story the bulls tell nor a disaster. It is a company that spent heavily and late into the strongest demand signal it had ever seen, then tried and failed to buy insurance against its own pipeline. Whether the $11 billion of filling capacity earns its cost of capital is a question that will be answered by 2028 utilisation rates, not by 2024 press releases.
And the reason those utilisation rates are suddenly in doubt traces back to a single Friday morning in December 2024.
VI. The Fall: CagriSema's Disappointment and the Collapse of Guidance Credibility (December 2024–2025)
CagriSema was supposed to be the answer to Eli Lilly.
The idea was elegant. Semaglutide works on the GLP-1 pathway. Cagrilintide works on a different one — amylin, another gut-and-pancreas hormone that signals satiety through a separate route in the brain. Combine them in one weekly injection and, in theory, you get additive appetite suppression without simply escalating the GLP-1 dose and its gastrointestinal side effects. Novo had guided the market to expect roughly 25% average weight loss. Analysts had built it into models. The company had built it into its own strategic narrative as the successor franchise that would carry semaglutide's economics past the patent cliff.
On December 20, 2024, the REDEFINE 1 topline arrived: 22.7% mean weight loss at 68 weeks, against 16.1% for semaglutide alone and 2.3% for placebo. Clinically, a strong result. Commercially, a miss against the number management itself had pointed at. Novo Nordisk shares fell roughly 20% in a single session, erasing on the order of $72 billion of market value, while Eli Lilly's shares rose on the read-through.4
The more consequential detail was buried in the trial design. REDEFINE 1 used a flexible-dosing protocol under which patients could adjust their own dose, and only about 57% of participants reached the maximum. Novo's framing was that this reflected real-world tolerability. Investors' framing was that a headline efficacy number produced by a protocol where four in ten patients never reached the top dose is a materially different number from one where they did — and that this was a design feature investors should have been told about before the readout, not explained afterwards.
That argument is no longer a debating point. On July 29, 2026, Judge Robert Kirsch of the US District Court for New Jersey allowed a securities fraud class action against Novo Nordisk to proceed on exactly this theory: that the company concealed protocol modifications permitting patients to self-adjust dosing, that fewer than 60% consequently reached the highest dose, and that investors bought shares at artificially inflated prices as a result.2324 The judge dismissed the related claim that Novo had overstated CagriSema's efficacy, characterising the 25% weight-loss expectation as "aspirational" and therefore not actionable.23 Novo denies wrongdoing; a company vice president called the allegations "meritless" and said Novo intends to "vigorously defend" itself.23
The split ruling is analytically useful. A court declined to treat management's optimistic efficacy target as fraud — a reasonable outcome, and a partial vindication. It did not decline to treat the omission of a dosing-protocol change as potentially material. The distinction maps almost exactly onto the distinction an investor should draw: Novo's scientists were optimistic and wrong, which happens; Novo's disclosure of how the trial was actually run is a live legal and governance question, and it is the second one that bears on management credibility. It is a material legal overhang, and it remains unresolved.
The credibility damage compounded through 2025 in a way that had nothing to do with courts.
Novo Nordisk had spent two decades cultivating a specific reputation with the sell side: guide conservatively, beat modestly, never surprise. That reputation is worth real money — it lowers the risk premium investors attach to forecasts and dampens volatility around prints. In 2025 the company spent it. Management cut its 2025 sales-growth outlook three separate times, most visibly in July, when the range came down to 8–14%, and again on November 5, when it narrowed to 8–11%.622 Separately, alongside the September restructuring, the operating-profit growth outlook was cut from 10–16% to 4–10%.3
The stated cause was consistent across all of them: US branded GLP-1 volumes were penetrating more slowly than planned because compounded semaglutide was absorbing demand, and Eli Lilly was taking share. Both were true. Compounded copies had proliferated in the shortage window and did not vanish when it closed. By the third quarter of 2025 Lilly held roughly 58% of the US GLP-1 market against Novo's 42%, and the growth decay was stark: Wegovy's year-on-year growth fell from 67% in the second quarter to 18% in the third, while Ozempic's fell from 15% to 3%.22
But an explanation that is true can still be a forecasting failure. The compounding phenomenon was visible in prescription data for well over a year before the first cut. Lilly's tirzepatide launch trajectory was public. Novo's own commercial organisation was closer to US prescribing data than any outside analyst. Three downward revisions to a single year's sales guidance is not one bad break; it is a demonstration that the company's internal demand model was systematically wrong about its largest market and kept being wrong for three consecutive quarters. On the November call, CEO Mike Doustdar's framing — that "lower growth expectations for our GLP-1 treatments have led to a narrowing of our guidance" — described the arithmetic without explaining why the company had not seen it coming.6
The carry-forward verdict is specific rather than rhetorical. The claim that Novo Nordisk's guidance is conservative and its clinical communication trustworthy is not permanently rejected — the CagriSema readout was a scientific disappointment more than a deception, and the court threw out the efficacy claim. But it is narrowed hard. Through 2024 the claim was supported by a long record; after 2025 it is supported by nothing but management's assertion that the base has been reset. The falsifiable test is unambiguous: two consecutive quarters in which guidance issued is guidance met, without revision. Until that happens, "we have reset the base" is a hypothesis, not evidence — and the Q2 2026 guidance raise, welcome as it was, came off a base that had already been cut twice.
The market's verdict on management arrived faster than the courts'. So did the Foundation's.
VII. Losing the Category: Eli Lilly's Ascent and the New Competitive Landscape
The obesity market of 2022 had one serious supplier. The obesity market of 2026 is a two-horse race with a growing tail of insurgents, and Novo Nordisk is no longer the horse in front on the measure that matters most to shareholders.
Start with the science, because the share shift is not a marketing story. Eli Lilly's tirzepatide — sold as Mounjaro for diabetes and Zepbound for obesity — hits two receptors instead of one. It activates GLP-1, like semaglutide, and also GIP, a second gut hormone. The clinical consequence is straightforward: in a head-to-head trial, tirzepatide produced roughly 20% weight loss against just under 14% for semaglutide over 72 weeks — about 47% greater relative weight loss. When two drugs in the same class are prescribed by the same physicians for the same indication and one is meaningfully more effective, share moves. There is no brand loyalty in obesity medicine that survives that gap.
The commercial result is visible in the revenue line. In 2025, combined Mounjaro and Zepbound sales reached roughly $36.5 billion, making tirzepatide the best-selling medicine in the world, against roughly $33 billion for Ozempic and Wegovy combined.25 Novo's Diabetes and Obesity segment was larger in total, at about $44 billion, because it still carries a century of insulin behind it — but on the growth engine itself, Lilly passed Novo.25
Now the counter-evidence, which is real and usually omitted from the declinist version of this story. Novo Nordisk's own 2025 annual report claims global branded obesity leadership on a volume basis at 59.6% share.26 Both statements can be true simultaneously: Lilly leads by revenue, particularly in the United States, while Novo leads by patients treated globally, because it sells more units into more markets at lower average prices. That is not a rounding difference; it is a description of two different business models converging on the same disease. Lilly is monetising efficacy at premium US prices. Novo is monetising reach.
The most interesting thing Novo has done in this fight is the Wegovy pill. The FDA approved once-daily oral semaglutide 25mg for chronic weight management on December 22, 2025, on the strength of the OASIS 4 trial showing 16.6% mean weight loss among adherent patients — comparable to the injection.27 Doustdar's line on approval day was characteristically blunt: "The pill is here."27 It launched in the US in early January 2026 at a self-pay price of $149 a month.2728
The launch has been the strongest commercial evidence in Novo's favour in two years. Prescriptions passed three million within roughly five months, and the pill contributed DKK 5.5 billion of sales in the first half of 2026, including DKK 3.2 billion in the second quarter alone.10 Management reported the Wegovy franchise held roughly 60% of new-to-brand prescriptions in the US in July 2026 and that Novo remained volume leader outside the US with about 58% GLP-1 volume share.29
Read that carefully before celebrating it. New-to-brand share measures where new patients are starting, not where the installed base sits, and a share of a fast-growing but still small oral segment is not the same as a share of the total market. More revealing is the pricing signal underneath: the pill's traction is concentrated at the cheapest, lowest-strength tier, and Novo has been testing lower doses precisely because self-paying patients gravitate to the cheapest option. Convenience is selling, but so is price — and price-led demand is a fundamentally different asset from efficacy-led demand, because it can be competed away by anyone willing to charge less.
Which brings in the third combatant: the copycats.
Compounded semaglutide is the strangest feature of this market. During the official shortage, US compounding pharmacies were legally permitted to make copies, and telehealth platforms industrialised the distribution. Enforcement tightened as the shortage ended, but the demand it revealed did not go away. On February 9, 2026, Novo Nordisk sued Hims & Hers in Delaware federal court for infringing US Patent No. 8,129,343 — the composition-of-matter patent on semaglutide, which runs to December 2031 — over compounded semaglutide products.2830 Days earlier Hims had launched a compounded oral semaglutide at $49 for the first month and $99 thereafter, undercutting Novo's own pill by a third or more; Hims pulled the product within days under regulatory pressure.2831 In March 2026 Novo voluntarily dismissed the patent claims without prejudice as part of a new commercial arrangement under which Hims stopped advertising compounded GLP-1s and began selling Novo's approved products on its platform.31
Novo won that skirmish, and the terms — a competitor converted into a distribution channel — were good ones. But the episode revealed the price elasticity beneath the branded market with uncomfortable clarity. A telehealth company priced an unapproved copy at a third of Novo's price and immediately found buyers.
Then there is genuine generic entry, which arrived earlier than anyone expected in one G7 market through an administrative failure. Novo Nordisk allowed Canadian patent CA 2,601,784 — covering acylated GLP-1 compounds — to lapse by failing to pay a maintenance fee of CAD 250, after a last payment in October 2018 and through a one-year grace period that expired in 2020.3233 Health Canada approved Dr. Reddy's generic semaglutide on April 28, 2026, the first in a G7 country, with Apotex following three days later.32
The instinct is to call this a catastrophic unforced error, and it is genuinely embarrassing for a company of this size. But the magnitude should be stated accurately: the underlying patent was filed in March 2006 and would have expired in March 2026 on its own, or March 2028 with a supplementary protection certificate.32 The lapse therefore cost Novo roughly two years of Canadian exclusivity plus the ability to enforce during the intervening period — not a decade. Canada matters less as lost revenue than as a live experiment in what happens to volumes and prices when the wall falls, and the answer so far is that generics have entered at a fraction of branded pricing. Semaglutide exclusivity also lapsed in Brazil, Canada and China in the same window, and Novo cited those expiries directly in its 2026 guidance.1 The core US, European and Japanese cliff still sits in 2031–2032.
The bear case on all of this is not hypothetical. On August 27, 2026, Deutsche Bank downgraded Novo Nordisk to Sell and cut its target by 9% to DKK 265, with analyst Emmanuel Papadakis citing ziltivekimab being "effectively out of the picture," a limited Medicare prescription bump, and "persisting concerns on the scope for a return to growth in 2027 and a large cliff problem further out."34 The shares fell more than 3% in Copenhagen.34
That is a coherent, specific bear thesis, and it deserves to be argued against on evidence rather than dismissed. The strongest counter is the international business, which Section X takes up. But the competitive conclusion is hard to soften: Novo Nordisk's advantage in obesity was a multi-year head start and a manufacturing constraint that bound its rival as much as itself. Neither was a structural moat. Once Lilly matched the capacity and beat the efficacy, patients and prescribers moved with almost no friction — which is exactly what you would predict for a category with no switching costs, no network effects, and a substitute one prescription pad away.
The people who ran the company through that transition did not survive it.
VIII. The Boardroom Reckoning: CEO Ouster, the Foundation's Coup, and What It Means for the Governance Thesis
Lars Fruergaard Jørgensen joined Novo Nordisk in 1991 and never left. He ran IT, he ran corporate development, he ran the business through the semaglutide supercycle, and on August 6, 2025 — after 34 years and eight as chief executive — he stepped down.3536 The announcement quoted then-chairman Helge Lund thanking him for "34 years of unstinting commitment."35 Nobody used the word fired. Everybody understood.
The exit terms are worth naming rather than glossing, because severance economics reveal how a board actually weighs accountability. Jørgensen received DKK 22.2 million for his period of service in 2025, DKK 36.5 million covering his notice period, a DKK 42.9 million severance payment, and DKK 22.0 million in non-competition compensation — over DKK 101 million in departure-related payments, on top of retained rights under the 2023–2025 long-term incentive programmes and pro-rata participation in the 2026 plan.36 Reasonable people can argue Danish notice-period conventions made much of this contractual. The observation stands regardless: a chief executive departed after a stretch in which the equity lost most of its value and left with more than DKK 100 million of exit-related compensation.
His replacement, effective August 7, 2025, was Maziar Mike Doustdar — also a lifer, with 34 years at the company.35 Doustdar had run International Operations since 2013, overseeing about 80 commercial affiliates outside the US, and under his leadership that business more than doubled to roughly DKK 112 billion of sales by 2024, reaching about 35 million patients.35 He was, by background, a commercial operator rather than a scientist, and by geography an outsider to the US market that was breaking.
His stated posture on appointment was urgency: "a sense of urgency, a laser focus on high performance, and a fierce determination for Novo Nordisk to aim higher than it's ever done."35 The structural change he made alongside it was telling — merging Research & Early Development into a single R&D unit under Martin Holst Lange, with the previous chief scientific officer retiring.35 Consolidating research and development under one executive speeds decisions and shortens the distance between the lab and the P&L. It also removes an internal check.
The first substantive move came a month later. On September 10, 2025, Novo Nordisk announced it would cut 9,000 jobs — about 11% of a 78,400-person workforce, with 5,000 of those in Denmark — targeting DKK 8 billion, roughly $1.26 billion, of annual savings by the end of 2026.337 Doustdar framed it as requiring "a shift in our mindset and approach so we can be faster and more agile."3
The execution has been real rather than announced: headcount fell to 68,794 by the end of 2025 and about 66,700 by mid-2026, with roughly DKK 8 billion of one-off restructuring costs booked in the third quarter of 2025.210 That is a company doing what it said it would do, on schedule. It is also, unavoidably, a cost response to a demand and competition problem. Cutting DKK 8 billion of expense does not add a patient or beat a competitor's molecule. It buys time.
Then, in October 2025, the governance structure that had been sold for thirty years as Novo Nordisk's quiet advantage did something loud.
Chairman Helge Lund, vice chair Henrik Poulsen, and board members Laurence Debroux, Andreas Fibig, Sylvie Grégoire, Christina Law and Martin Mackay all agreed to step down after an open rift with the Novo Nordisk Foundation.78 The dispute was not about strategy in the abstract. The Foundation wanted a far more sweeping reconstitution of the board than the sitting directors were prepared to accept, could not reach agreement, and rather than wait for the scheduled March 2026 annual meeting, forced an Extraordinary General Meeting.7
At that meeting on November 14, 2025, shareholders elected Lars Rebien Sørensen as chair, Cees de Jong as vice chair, and Britt Meelby Jensen and Stephan Engels as directors, all serving until the March 26, 2026 AGM.838 Sørensen is not an outsider. He ran Novo Nordisk as chief executive from 2000 to 2016, and he chairs the Novo Nordisk Foundation itself. The controlling shareholder's own leader now also chairs the operating company's board. His stated mandate on election was "to support the CEO and the management."8
Minority shareholders objected in the only way available to them, which was symbolically. Proxy adviser ISS recommended abstaining on the slate, citing a unilateral overhaul with limited accountability to minority shareholders. Norway's sovereign wealth fund — one of the largest institutional holders in Europe — publicly abstained from voting on the new directors, including the chair. Several pension funds criticised the process in the press ahead of the meeting.39 The resolutions passed regardless, because with 77.3% of the votes the outcome was never in question.1438
This is the passage where the long-standing governance thesis has to be tested rather than repeated, and the honest conclusion is a narrowing rather than a rejection.
What the record supports: foundation control has funded genuinely patient science. The arc from insulin extraction in 1923 to a once-weekly peptide that reduces cardiovascular events is not the kind of programme a quarterly-driven company reliably completes, and the Foundation's willingness to keep funding R&D through the 2025 collapse — R&D spending rose 10% at constant currency to DKK 52 billion in a year the share price halved — is real evidence of capital patience that a conventional shareholder base would likely not have tolerated.2
What the record does not support, and what 2025 falsified: the claim that this structure protects shareholders. It protects the company's long-term programme, which is a different thing. In the space of thirteen months, the controlling owner removed a chief executive and then a majority of the independent board on its own timetable, against the sitting board's stated preference, and the outside investors who owned roughly 72% of the economics could do nothing but abstain in protest.14 "Insulated from short-term market pressure" and "accountable to minority owners" were always two separate promises. Only the first is evidenced.
An activist did try. In June 2025, London-based Parvus Asset Management — known for campaigns at Ryanair, UniCredit and Flutter Entertainment — was reported to have built a stake in Novo Nordisk, explicitly aiming to influence the choice of the next chief executive.40 Parvus never disclosed a size; Danish law only compels disclosure above 5%.40 Whether it materially affected the outcome is unproven and should not be overstated — the CEO chosen was a 34-year insider, which is not the archetypal activist outcome. What the episode does show is that sophisticated capital looked at Novo Nordisk in 2025 and concluded there was an opening. Against 77% voting control, there was not.
The forward test is concrete. Does a board chaired by the Foundation's own chairman, working with a CEO the Foundation effectively installed, produce demonstrably better decisions — cleaner guidance, sharper pipeline prioritisation, better capital allocation — than the board it replaced? Or does it simply consolidate control? The first full year of Doustdar-Sørensen decisions is the evidence, and the Capital Markets Day scheduled for September 21, 2026 in London is the first structured opportunity to judge it.41
Because on the pipeline, the news arriving in the days before that meeting has been bad.
IX. The Current Pipeline: Real Wins, and a Diversification Bet That Is Failing
Every pharmaceutical company tells investors a story about optionality. The discipline required is to separate the parts of that story that are revenue, the parts that are probability, and the parts that have already been disproven. Novo Nordisk's pipeline in September 2026 contains all three, and blending them is how investors get hurt.
Start with what is already revenue. The Wegovy pill is a genuine commercial win, sized correctly in Section VII. Alongside it sits Awiqli, approved by the FDA on March 27, 2026 as the first and only once-weekly basal insulin for adults with type 2 diabetes, based on four ONWARDS trials covering about 2,680 patients, with US launch guided for the second half of 2026.42 Reducing basal insulin injections from seven a week to one is exactly the kind of incremental improvement this company has made for a century. It is a diabetes-care extension, not a category-changer, and it should be sized that way.
Awiqli also carries an instructive scar. The FDA rejected the same drug on July 11, 2024, issuing a complete response letter over manufacturing questions and the type 1 diabetes indication, after an advisory committee in May 2024 concluded the benefit-risk balance did not favour approval in type 1 patients because of hypoglycemia risk.43 It took Novo twenty months to convert that rejection into a narrower type 2 approval. That is the base rate this company should be judged against when it describes pipeline assets: capable of eventually getting there, not reliably fast.
Now the probability. Amycretin is Novo's real next-generation obesity candidate — like CagriSema, a combination of GLP-1 and amylin activity, but engineered into a single molecule rather than co-formulated from two. In a Phase 1b/2a study of 125 participants, the subcutaneous version at doses up to 60mg produced 24.3% weight reduction at 36 weeks against 1.1% on placebo, with no plateau observed by the end of the study.44 The oral version, in a 144-participant Phase 1, produced 13.1% mean weight loss at 100mg daily over just 12 weeks.44 Both formulations moved directly into Phase 3, with the results published in The Lancet in June 2025 and the obesity Phase 3 programme starting in 2026.44
The efficacy signal is genuinely strong — a single molecule matching or beating what CagriSema achieved with two, and doing it without a plateau, is the most encouraging scientific data Novo has produced since SELECT. But the honest framing is a timing one. Phase 3 obesity programmes run for years, filings take a year, and independent estimates put a first US approval around the fourth quarter of 2030. Amycretin therefore cannot help the 2027–2029 growth gap that the market is actually worried about, no matter how good the data turns out to be. It is optionality on the far side of the problem, not a solution to it. And 125 patients in Phase 1b/2a is a small base from which to extrapolate; CagriSema also looked excellent before its Phase 3.
Then the disproven part, which is why this section exists as its own chapter.
Ziltivekimab was the single largest expression of Novo Nordisk's ambition to be more than a metabolic-disease company. The scientific premise was serious and well-credentialed: chronic low-grade inflammation drives atherosclerosis independently of cholesterol, and an antibody that blocks interleukin-6 should therefore reduce heart attacks and strokes in patients whose inflammation is elevated. If it worked, Novo would have owned a cardiovascular franchise built on a mechanism entirely separate from GLP-1 — genuine new therapeutic real estate, with a patient population far larger than obesity.
On July 31, 2026, the Phase 3 ZEUS trial reported that ziltivekimab lowered markers of inflammation but did not reduce major adverse cardiovascular events in patients with atherosclerotic disease, chronic kidney disease and inflammation.1011 The primary endpoint was missed. The biomarker moved and the patients did not benefit — the specific, brutal failure mode that has claimed anti-inflammatory cardiovascular programmes before.
Then, on September 4, 2026, Novo informed investigators it was ending two more Phase 3 trials early — HERMES and ATHENA, both testing ziltivekimab in heart failure with inflammation — after an independent data monitoring committee concluded they were unlikely to reach a different conclusion than ZEUS.1112 Only ARTEMIS, testing the drug in the acute post-heart-attack setting, continues, with a readout expected in the first half of 2027.12
The financial consequence is smaller than the strategic one. What has been destroyed is not a large revenue line — ziltivekimab never had one — but the credibility of the claim that Novo Nordisk has a funded, credible path to a third major disease area. As of today, it does not. The near-term diversification story is back to approximately zero, and the growth case rests almost entirely on defending and extending a position within GLP-1-adjacent metabolic disease.
This is worth connecting to a pattern rather than treating as one bad trial. In the same second quarter of 2026, Novo booked DKK 6.3 billion of non-cash impairment charges, of which DKK 4.0 billion related to monlunabant — another obesity-adjacent asset written down.10 CagriSema missed its target, then in February 2026 failed to demonstrate non-inferiority against Zepbound in the head-to-head REDEFINE 4 trial, delivering 23.0% weight loss against Zepbound's 25.5% at 84 weeks, and 20.2% against 23.6% on the more conservative treatment-regimen measure.5 The shares fell 16.5% over that weekend.5 Novo filed CagriSema with the FDA in December 2025 on the strength of REDEFINE 1 and 2, with a decision expected late in 2026 — but it will arrive as a product that has been publicly beaten by the incumbent competitor rather than as the successor franchise it was designed to be.
The conclusion an investor should draw is not that Novo Nordisk's science is bad. It is that this company's recent base rate for converting late-stage clinical progress into commercial value has been poor — one clear win (the Wegovy pill, from an already-approved molecule), one delayed approval, one outright Phase 3 failure, one impairment, and one flagship candidate that missed its own target and then lost a head-to-head. "Pipeline optionality" should be discounted against that record, not quoted at face value.
Which raises the obvious question: if the pipeline is not carrying the story, what is the actual business doing right now?
X. The Business Today: Segments, Margins, and the Price of TrumpRx
Here is the fact that gets lost inside the crash narrative, and it is important: Novo Nordisk is not a broken business. It sold DKK 309 billion in 2025, grew 10% at constant exchange rates, earned DKK 128 billion of operating profit and DKK 102 billion of net profit.2 For scale, that operating margin is above 41% — a level almost no industry on earth sustains.
The segment composition surprises people who only know the headlines. Diabetes Care was DKK 207 billion, growing 4% at constant currency. Obesity Care was DKK 82 billion, growing 31%. Rare Disease was DKK 19.6 billion.2 Obesity dominates the narrative and drives essentially all the growth, but in absolute revenue it remains less than half the size of the diabetes franchise that has been compounding quietly for a hundred years. When investors describe Novo Nordisk as "the Ozempic company," they are describing about a quarter of its revenue.
Geographically, the two halves of the business have decoupled. In 2025, US Operations were DKK 173 billion growing 8% at constant currency, while International Operations were DKK 136 billion growing 14%, with Asia-Pacific compounding fastest.2 By the second quarter of 2026 the gap had widened into a genuinely different story: International Operations grew 10% at constant currency and GLP-1 sales there grew 13%, with the obesity franchise up 37%, while US Operations on an adjusted basis grew 4%.1029 Novo retained roughly 58% GLP-1 volume share outside the United States.29
That divergence is the single most important structural fact in the current business, and it deserves a plain-English conclusion: the obesity opportunity is not shrinking, and Novo Nordisk is not losing globally. What is happening is that the American profit pool is being repriced while the rest of the world is still in the volume-expansion phase. Those are opposite forces hitting the same P&L, and whether the second can outrun the first is the whole investment question.
The repricing has a name and a date. On November 6, 2025, the White House announced agreements with both Novo Nordisk and Eli Lilly to align US prices with the lowest prices paid in other developed countries — the most-favoured-nation principle — in exchange for commitments to expand domestic manufacturing.9 Novo committed $10 billion of US manufacturing investment; Lilly committed at least $27 billion.9 All state Medicaid programmes get access to MFN prices, and the companies agreed to deep discounts on direct-to-consumer sales through a government-run platform, TrumpRx, which launched in January 2026.9 Monthly prices that had been over $1,000 came down toward as low as $245 for the covered injectables, with starting doses of approved oral GLP-1s set around $150.45
Novo Nordisk's own disclosure has since made the permanence of this explicit. In its half-year 2026 report the company stated that effective January 1, 2027 it will cut list prices by approximately 50% for Wegovy and approximately 35% for Ozempic.10 That is not a promotional discount that lapses. It is a reset of the price the company's largest market pays for its two biggest products, and it is the reason "volumes are growing" and "revenue is declining" can both be true at once. Management's 2026 guidance — adjusted sales and operating profit both between flat and down 6% at constant currency, upgraded in August from down 4–12% — is the arithmetic of that trade.10
Two second-order observations belong here, because they change how the reported numbers should be read.
The first is an accounting judgment that materially flatters headline 2026 growth. Reported first-half 2026 sales rose 18% at constant currency; adjusted sales rose 2%.10 The difference is a DKK 26.8 billion reversal of sales rebate provisions related to the US 340B Drug Pricing Program, booked in the first quarter, worth about $4.2 billion — non-cash, non-recurring, and large enough to swing reported US Operations growth from negative to strongly positive.1046 Novo disclosed it clearly and guides on the adjusted basis, which is the right practice. But any headline citing Novo Nordisk's 2026 reported growth without that adjustment is describing an accounting entry rather than a business. A smaller version of the same reversal, DKK 2.6 billion, flattered the second quarter of 2025.10
The second is that the cash economics remain formidable despite everything. First-half 2026 free cash flow was DKK 55.3 billion, up 44% year on year, funding DKK 35.3 billion of dividends and DKK 5.9 billion of buybacks alongside DKK 24 billion of capital expenditure.10 For all the narrative damage, this is not a company with a financing problem. It is a company with a growth and pricing problem, which is a materially different thing — and it means the near-term risk is to the multiple and the growth rate, not to solvency.
On compensation, the incentive system did at least respond to the results. Total executive management remuneration fell 38% in 2025, from DKK 311.1 million to DKK 193.3 million, and Doustdar's short-term incentive was assessed at 24.7% of maximum.36 His DKK 20.7 million for roughly five months annualises to about DKK 34.6 million, well below his predecessor's scale.36 Pay tracking performance downward is a modest positive signal about board discipline. It should not be oversold: Doustdar's 107,569 shares, worth about DKK 35 million at year-end, satisfy Novo's internal shareholding requirement but are a negligible fraction of the company, so alignment here runs through incentive design rather than through meaningful personal ownership.36
Doustdar's own retrospective diagnosis, offered in a September 2026 interview, was that Novo Nordisk "sold health when people wanted weight loss."47 It is a candid line and probably a correct one about the 2021–2023 marketing posture. It is also the kind of framing that locates the problem in messaging rather than in molecule efficacy or manufacturing timing — and on the evidence of the head-to-head trial data, messaging was not the binding constraint.
XI. Playbook: Business & Investing Lessons — Revised for What 2025–2026 Actually Showed
Capacity moats are rentable, not owned. For two years, Novo Nordisk's binding constraint was sterile filling capacity, and that constraint looked like a moat because no competitor could serve the unmet demand either. It was not a moat. It was a temporary shortage of a commodity input that any well-capitalised rival could buy or build, and Lilly did both. The general lesson: when a company's advantage is that it has more of something physical than anyone else, ask what it costs a determined competitor to match it and how long that takes. If the answer is "a few billion dollars and three years," it is a head start, not a moat.
Guidance credibility is a balance-sheet asset that can be spent in a single year. Novo's reputation for conservative forecasting lowered its cost of capital and dampened volatility for two decades. Three cuts to one year's sales outlook consumed it. Rebuilding takes several consecutive clean quarters, and until then every forward number the company issues carries a discount that has nothing to do with the underlying business.
Foundation control funds patient science; it does not protect minority shareholders. These are separate promises, and 2025 separated them in public. An investor buying into a foundation-controlled company is buying genuine R&D patience — evidenced by R&D spending that rose through the collapse — and simultaneously accepting that they have no meaningful say if the controlling owner decides to reconstitute the board. Both facts should be priced.
A category-defining drug is a head start, not a franchise. Semaglutide created a market worth more than $100 billion. It did not create switching costs, network effects, or counter-positioning. Patients and prescribers moved to a better molecule with almost no friction, which is what always happens in therapeutic categories where the substitute is a different prescription for the same visit.
Clinical progress and revenue are different claims, and companies have different base rates for converting one into the other. Ziltivekimab reached Phase 3 and produced nothing. Insulin icodec reached approval only after a rejection and a twenty-month delay. CagriSema reached filing but lost head-to-head. Against that record, "we have a deep pipeline" is a statement about probability distributions, not about future cash flows.
Related-party transactions in controlled companies deserve their own diligence. The $11 billion purchase of three plants from a parent that had just bought them may well have been fair value. The point is that the ordinary market test for fairness — an arm's-length negotiation between unrelated parties — was absent, and in a company where one shareholder holds 77% of the votes, the internal check is structurally weaker than it looks on an org chart.
XII. Competitive Strategy Analysis and the Bear vs. Bull Case
The five forces, read honestly
Buyer power has risen faster than any other variable in this business. Pharmacy benefit managers were always tough negotiators, but the November 2025 agreement introduced a buyer of a different kind: the US federal government, negotiating on behalf of Medicare and Medicaid while holding tariff and regulatory leverage. When your largest customer can set your list price as a condition of market access, "pricing power" is no longer a meaningful description of your position. The January 2027 list-price cuts are the proof.10
Substitution is high and rising on three separate fronts — Lilly's more effective injectable and its oral small molecule, compounded copies whose demand elasticity was demonstrated at $49 a month, and now approved generics in Canada, Brazil and China ahead of the 2031–2032 core cliff.132
Rivalry has changed character entirely. From 2021 to 2023 Novo competed against a shortage. It now competes against a peer with comparable R&D resources, superior head-to-head efficacy data, and a larger US manufacturing commitment.
Supplier power has genuinely fallen for Novo specifically, and this is the one force that improved: owning the former Catalent fill-finish sites converted a third-party dependency into an internal asset.19
Barriers to entry remain real but demonstrably insufficient. Regulatory approval, peptide manufacturing at scale, and device engineering are hard. They stopped nobody who mattered.
Seven Powers, applied
Novo Nordisk's strongest historical powers were a cornered resource — filling capacity during the shortage — and branding, where "Ozempic" became a generic term for weight loss before Wegovy existed. Both were real and both are decaying. The cornered resource has been matched. The brand is now attached to a product that is publicly less effective than its main competitor, which is a brand liability rather than an asset.
What Novo Nordisk does not have is more important. There is no counter-positioning: Lilly is not constrained by a legacy business model from competing directly. There are no meaningful switching costs in obesity: unlike the insulin franchise, where device familiarity created stickiness, a patient switching from Wegovy to Zepbound faces a new pen and a new titration schedule and little else. There are no network economies. There is arguably scale economies in peptide manufacturing and process power in a century of formulation science — those are the durable ones, and they are cost advantages rather than revenue advantages, which matters enormously in a market that is being repriced downward. A cost leader in a price war is a better place to be than a premium brand in a price war.
How this compares to the rest of large-cap pharma
It is worth situating Novo Nordisk against the industry it belongs to, because the current distress reads differently in context. Most large pharmaceutical companies spend their lives managing a portfolio of a dozen or more franchises with staggered patent expiries, precisely so that no single cliff is existential. Novo Nordisk deliberately did the opposite: it narrowed to metabolic disease, went deep on one mechanism, and was rewarded with the fastest revenue ramp in the industry's history. The cost of that concentration is arriving now. A diversified peer facing a 50% list-price cut on one product would report a bad year; Novo is reporting a bad era, because Wegovy and Ozempic together are the majority of the growth and a large share of the profit. Concentration is a strategy that pays for a decade and bills for one, and this is the bill.
The comparison to Eli Lilly is also less lopsided than the share-price charts suggest. Lilly is winning the current round on efficacy and on US revenue, but it is running the same concentration risk, in the same disease area, against the same eventual patent expiries, and with a far larger fixed-cost manufacturing commitment. If the US repricing that hit Novo in 2026 continues to broaden, it will not stop at one company's door. What separates them today is not business-model quality but position in the product cycle — and product cycles turn.
The bull case, with the evidence behind each claim
The business is still growing and still enormously profitable, with double-digit constant-currency sales growth in 2025 and operating margins above 40%.2 The oral franchise is a verified commercial win with three million prescriptions inside five months and DKK 5.5 billion of first-half sales.10 International Operations demonstrate that the US pricing shock is a US phenomenon rather than a global one, with ex-US obesity growth of 37% in the second quarter.29 Free cash flow of DKK 55 billion in a half-year gives the company complete freedom to fund the Phase 3 amycretin programme, the restructuring and the dividend simultaneously.10 Management raised 2026 guidance in August rather than cutting it again.10 And after a roughly 70% derating, the valuation embeds a great deal of the pessimism: the shares trade at a large discount to Eli Lilly on forward earnings, for a company that remains one of the most profitable large-cap pharmaceutical businesses in the world.
The bear case, with the evidence behind each claim
Lilly leads on efficacy in head-to-head data and on revenue in the category Novo created, holding roughly 58% of US GLP-1 share as of late 2025.2522 The US repricing is structural and self-disclosed, with list prices falling roughly 50% on Wegovy from January 2027.10 The core patent cliff arrives in 2031–2032 with three significant markets already open. The diversification bet has failed outright and the replacement, amycretin, cannot contribute revenue before roughly 2030.1244 The guidance record from 2025 is unrepaired. A securities class action alleging concealed trial-protocol changes survived a motion to dismiss.23 And the governance structure has just demonstrated, with minority holders abstaining in protest, that it can reconstitute its own board at will.39
The activist stress test
A skeptical investor would press on four things. First, capital allocation: $11 billion for filling capacity at the demand peak, a further $10 billion committed to US manufacturing as the price of a pricing deal that cuts revenue, and a $9 billion attempted acquisition of a competitor's amylin asset that failed on antitrust grounds — all in twenty-one months, from a company whose brand is patience.19921 Second, the related-party structure of the Catalent transaction. Third, the gap between reported and adjusted 2026 results created by the 340B provision reversal, which is disclosed but easily misread.10 Fourth, and most pointedly, board accountability: the board that presided over the CagriSema disclosure and three guidance cuts was replaced not by shareholder action but by the controlling owner, and the new chair is the controlling owner's own chairman.
Net framing
This is not a broken business, and the crash narrative overstates the operational damage. It is a highly profitable, still-growing company whose valuation and narrative had run well ahead of an execution risk it had never been tested against — and 2024 through 2026 was that test. On the evidence available in September 2026, the company has failed the competitive test in the United States, passed the operational-execution test on cost and on the oral launch, and produced no resolution at all on the two questions that matter most: whether it can grow again after 2027, and whether it can convert its remaining pipeline into revenue at a better rate than the last three years suggest. Anyone claiming certainty in either direction is reading a conclusion into evidence that does not yet support one.
XIII. Epilogue: What to Watch
Thirteen days from the writing of this piece, on September 21, 2026, Novo Nordisk's executive management will stand up in London for a Capital Markets Day and present what the company describes as a comprehensive overview of strategy, pipeline, operations and performance.41 It is the first structured opportunity Doustdar and Sørensen have had to lay out a growth case rather than a cost case, and it comes seventeen days after the ziltivekimab trials were stopped. What management chooses to put at the centre of that presentation — amycretin, international expansion, cost structure, or something not currently visible — will say more about the strategy than any quarterly print.
Three KPIs matter more than everything else an investor could track.
First, US branded prescription share versus Eli Lilly, quarterly. Not new-to-brand share, which flatters a company launching a new formulation, but total prescription share across the GLP-1 category. This is the direct measure of whether Novo is defending the market it created or continuing to cede it. It is published frequently enough to be a real-time scoreboard.
Second, realized net price per prescription in the United States after the January 2027 list-price cuts. List prices are announced; realized prices are what actually lands in revenue after rebates, and the gap between them is where the entire margin story lives. If volume growth more than offsets a roughly 50% list cut on Wegovy, the international-volume thesis holds. If it does not, the US profit pool shrinks structurally and the growth reacceleration story has to come from somewhere else entirely.
Third, amycretin Phase 3 readouts. With ziltivekimab gone and CagriSema arriving as a beaten product, amycretin is the only remaining candidate that could restore a genuine next-generation franchise. The data that matters is whether the absence of a weight-loss plateau observed in Phase 1b/2a survives into a larger, longer, more heterogeneous Phase 3 population — because that, and not the headline percentage, is what would differentiate it from what already exists.
Two open questions round out the watch list. Whether the securities litigation in New Jersey produces disclosure that changes what is publicly known about how REDEFINE 1 was designed and communicated. And whether any outside investor attempts a further governance challenge, or whether November 2025 settled the question permanently in the Foundation's favour.
Novo Nordisk spent a century demonstrating that patient, foundation-backed science could out-compound quarterly-driven rivals, and the demonstration was genuine. The 2024–2026 stretch is the first real test of a different proposition: whether that same structure serves outside shareholders when things go badly wrong. The record so far is mixed, the company remains formidable, and the story is nowhere near finished.
XIV. Recent News
Ziltivekimab heart-failure trials terminated, September 4, 2026. Novo Nordisk notified investigators that HERMES and ATHENA would end early after a data monitoring committee concluded they were unlikely to differ from ZEUS, which missed its primary cardiovascular endpoint on July 31, 2026.1112 ARTEMIS, in the post-heart-attack setting, continues with a readout expected in the first half of 2027.12
Deutsche Bank downgrade, August 27, 2026. The bank cut Novo Nordisk to Sell and reduced its target to DKK 265, citing doubts about a return to growth in 2027 and the patent cliff beyond it; the shares fell more than 3% in Copenhagen.34
Second-quarter 2026 results, August 4, 2026. Adjusted sales grew 7% at constant currency to DKK 78.5 billion, adjusted operating profit grew 11%, and full-year guidance was raised to between flat and down 6% on both lines.1029 Reported figures across the half were inflated by the DKK 26.8 billion 340B provision reversal booked in the first quarter.1046
January 1, 2027 list-price reductions confirmed. Novo disclosed it will cut US list prices by approximately 50% for Wegovy and approximately 35% for Ozempic.10
CagriSema regulatory decision pending. Filed with the FDA in December 2025 on REDEFINE 1 and 2, with a decision anticipated late in 2026, following the February 2026 REDEFINE 4 head-to-head result against Zepbound.5
Capital Markets Day, September 21, 2026, London. The company's first full strategy presentation under the current leadership.41
XV. Links & Resources
For an investor building an independent view of Novo Nordisk, the primary materials are unusually accessible and considerably more informative than the secondary coverage.
The company's annual report portal and investor relations hub carry the full-year reports and strategic-aspiration disclosures, including the segment and market-share detail that most summaries omit.2648 The Form 20-F filed with the SEC on February 4, 2026 is the most complete single document on risk factors, patent expiry schedules by market, and legal proceedings.4950
The quarterly Form 6-K financial statements are where the adjusted-versus-reported distinction becomes visible, and the half-year 2026 filing is essential reading for anyone trying to understand the 340B provision reversal and the January 2027 pricing commitments.10462
The 2025 remuneration report is the primary source on executive departure terms and incentive outcomes, and it is more candid about the relationship between pay and performance than most European equivalents.36
On governance, the notice and minutes of the November 14, 2025 Extraordinary General Meeting, together with the resolutions announcement, document the board reconstitution in the company's own words.83851 The Novo Nordisk Foundation's own ownership disclosures set out the share-class mechanics that make that episode possible.14
For the competitive picture, the quarterly earnings calls of both Novo Nordisk and Eli Lilly, read against each other, are more useful than any third-party market-share estimate, and prescription-tracking coverage of the oral GLP-1 launches provides the highest-frequency read on where new patients are actually going.2952
References
-
Novo Nordisk shares tumble 18% after 2026 sales dip warning — Pharmaceutical Technology, 2026-02-04 ↩↩↩↩↩
-
Novo Nordisk A/S Form 6-K — Company announcement, financial report for 2025 and 2026 outlook, SEC EDGAR, 2026-02-03 ↩↩↩↩↩↩↩↩
-
Novo Nordisk to lay off 9,000 workers in major restructuring — BioPharma Dive, 2025-09-10 ↩↩↩↩↩
-
Novo Nordisk shares plunge 20% after disappointing CagriSema trial results; Lilly jumps — CNBC, 2024-12-20 ↩↩
-
Novo Nordisk's CagriSema bested by Lilly's Zepbound in head-to-head trial — Clinical Trials Arena, 2026-02 ↩↩↩↩
-
Novo Nordisk cuts guidance again on weaker GLP-1 growth — pharmaphorum, 2025-11-05 ↩↩↩
-
Novo Nordisk chair and directors quit after boardroom rift — CNBC, 2025-10-21 ↩↩↩
-
Resolutions from the Extraordinary General Meeting of Novo Nordisk A/S — GlobeNewswire, 2025-11-14 ↩↩↩↩↩
-
White House announces deals with Eli Lilly, Novo Nordisk to lower drug costs — American Hospital Association, 2025-11-06 ↩↩↩↩↩↩
-
Novo Nordisk A/S Form 6-K — Financial report for the period 1 January 2026 to 30 June 2026, SEC EDGAR, 2026-08-04 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
Novo Nordisk stops two cardiovascular trials of drug aimed at lowering inflammation — STAT News, 2026-09-07 ↩↩↩↩
-
Novo scraps two more heart drug trials, further dimming growth beyond obesity — Reuters, 2026-09-07 ↩↩↩↩↩↩
-
Novo Nordisk Agrees to Pay $58 Million for Failure to Comply with FDA-Mandated Risk Program — U.S. Department of Justice, 2017-09-05 ↩
-
Novo Nordisk settles claims related to Victoza marketing — BioPharma Dive, 2017-09-06 ↩↩↩
-
Novo Nordisk A/S: Semaglutide 2.4 mg reduces the risk of major adverse cardiovascular events by 20% in adults with overweight or obesity in the SELECT trial — Novo Nordisk, 2023-08-08 ↩↩
-
Novo Holdings completes acquisition of Catalent — Novo Holdings, 2024-12-18 ↩↩
-
Novo Nordisk $11b acquisition to support manufacturing capacity — European Pharmaceutical Review, 2024-02-05 ↩↩↩↩↩
-
Novo Nordisk to build $4.1 billion North Carolina facility to boost output of Wegovy, Ozempic — NBC News, 2024-06-24 ↩
-
Novo tops Pfizer with $6.5B bid for Metsera — BioPharma Dive, 2025-10-30 ↩↩↩
-
Slower-growing GLP-1 drug sales force Novo Nordisk to cut forecast again — eMarketer, 2025-11 ↩↩↩↩
-
Novo ordered to face CagriSema fraud claims from shareholders: New Jersey court — BioSpace, 2026-07-29 ↩↩↩↩
-
Why shareholders are suing Novo Nordisk over next-generation weight-loss drug — CNBC, 2026-07-29 ↩
-
Eli Lilly's GLP-1 growth is only getting started as Novo Nordisk braces for a decline in 2026 — CNBC, 2026-02-04 ↩↩↩
-
Wegovy pill FDA approval — Novo Nordisk company announcement, 2025-12-22 ↩↩↩
-
Novo Nordisk sues Hims for GLP-1 patent infringement — Drug Discovery Trends, 2026-02-10 ↩↩↩
-
Q2 2026 Novo Nordisk A/S Earnings Call Transcript — GuruFocus, 2026-08-05 ↩↩↩↩↩↩
-
Novo Nordisk sues Hims & Hers over compounded obesity drugs — CNBC, 2026-02-09 ↩
-
Inside the Legal Battle Between Novo Nordisk and Hims & Hers — The Fashion Law, 2026 ↩↩
-
Canada approves generic semaglutide from Dr. Reddy's, a G7 first enabled by Novo Nordisk's lapsed CAD$250 patent — Drug Discovery Trends, 2026-05 ↩↩↩↩
-
Semaglutide patent expiry opens door to GLP-1 generics in Canada — Labiotech ↩
-
Novo Nordisk Shares Drop as Bank Downgrade Reflects Growth Concerns — The Wall Street Journal, 2026-08-27 ↩↩↩
-
Novo Nordisk appoints new President & CEO — Novo Nordisk company announcement, 2025-08-06 ↩↩↩↩↩↩
-
Novo Nordisk A/S Form 6-K — Remuneration Report 2025, SEC EDGAR, 2026-02-04 ↩↩↩↩↩↩
-
Novo Nordisk to lay off 9,000 workers as new CEO aims to save $1.3B per year by late 2026 — Fierce Pharma, 2025-09-10 ↩
-
Novo Nordisk A/S: Minutes and voting results from Extraordinary General Meeting 2025 — MarketScreener, 2025-11-14 ↩↩↩
-
Novo Nordisk's strategy tested as investors push back on board revamp — CNBC, 2025-11-14 ↩↩
-
Activist Parvus builds stake in Novo Nordisk — Hedgeweek, 2025-06-10 ↩↩
-
Novo Nordisk A/S: Awiqli approved in the US, the first and only once-weekly basal insulin treatment for adults with type 2 diabetes — GlobeNewswire, 2026-03-26 ↩
-
Novo's once-weekly insulin rejected by FDA — BioPharma Dive, 2024-07-11 ↩
-
Novo Nordisk advances early-stage obesity medication, amycretin, to phase 3 clinical development — PR Newswire, 2025-06-20 ↩↩↩↩
-
Novo Nordisk A/S Form 6-K — Financial report for the period 1 January 2026 to 31 March 2026, SEC EDGAR, 2026-05-06 ↩↩↩
-
Ozempic maker: "We sold health when people wanted weight loss" — CEO Mike Doustdar interview, Yahoo Finance, 2026-09-07 ↩
-
Novo Nordisk files annual report with the SEC — GlobeNewswire, 2026-02-04 ↩
-
Novo Nordisk A/S Form 20-F for the fiscal year ended 31 December 2025 — SEC EDGAR, 2026-02-04 ↩
-
Minutes of Extraordinary General Meeting, Novo Nordisk A/S, 14 November 2025 — Novo Nordisk ↩
-
The Oral GLP-1 Tracker: Novo's Wegovy pill, Lilly's Foundayo grow scripts — Fierce Pharma ↩
 LinkedIn
 WhatsApp
 Reddit
 Hacker News
 Email
 Kindle
 RSS Feed
 Spotify
 Apple Podcasts
 Amazon Music
 Audible
 YouTube