DaVita: The Great Share Cannibal and the Dialysis Duopoly
I. Episode Introduction & The Central Paradox
Start with the numbers that don't add up, because the whole story lives in the gap between them.
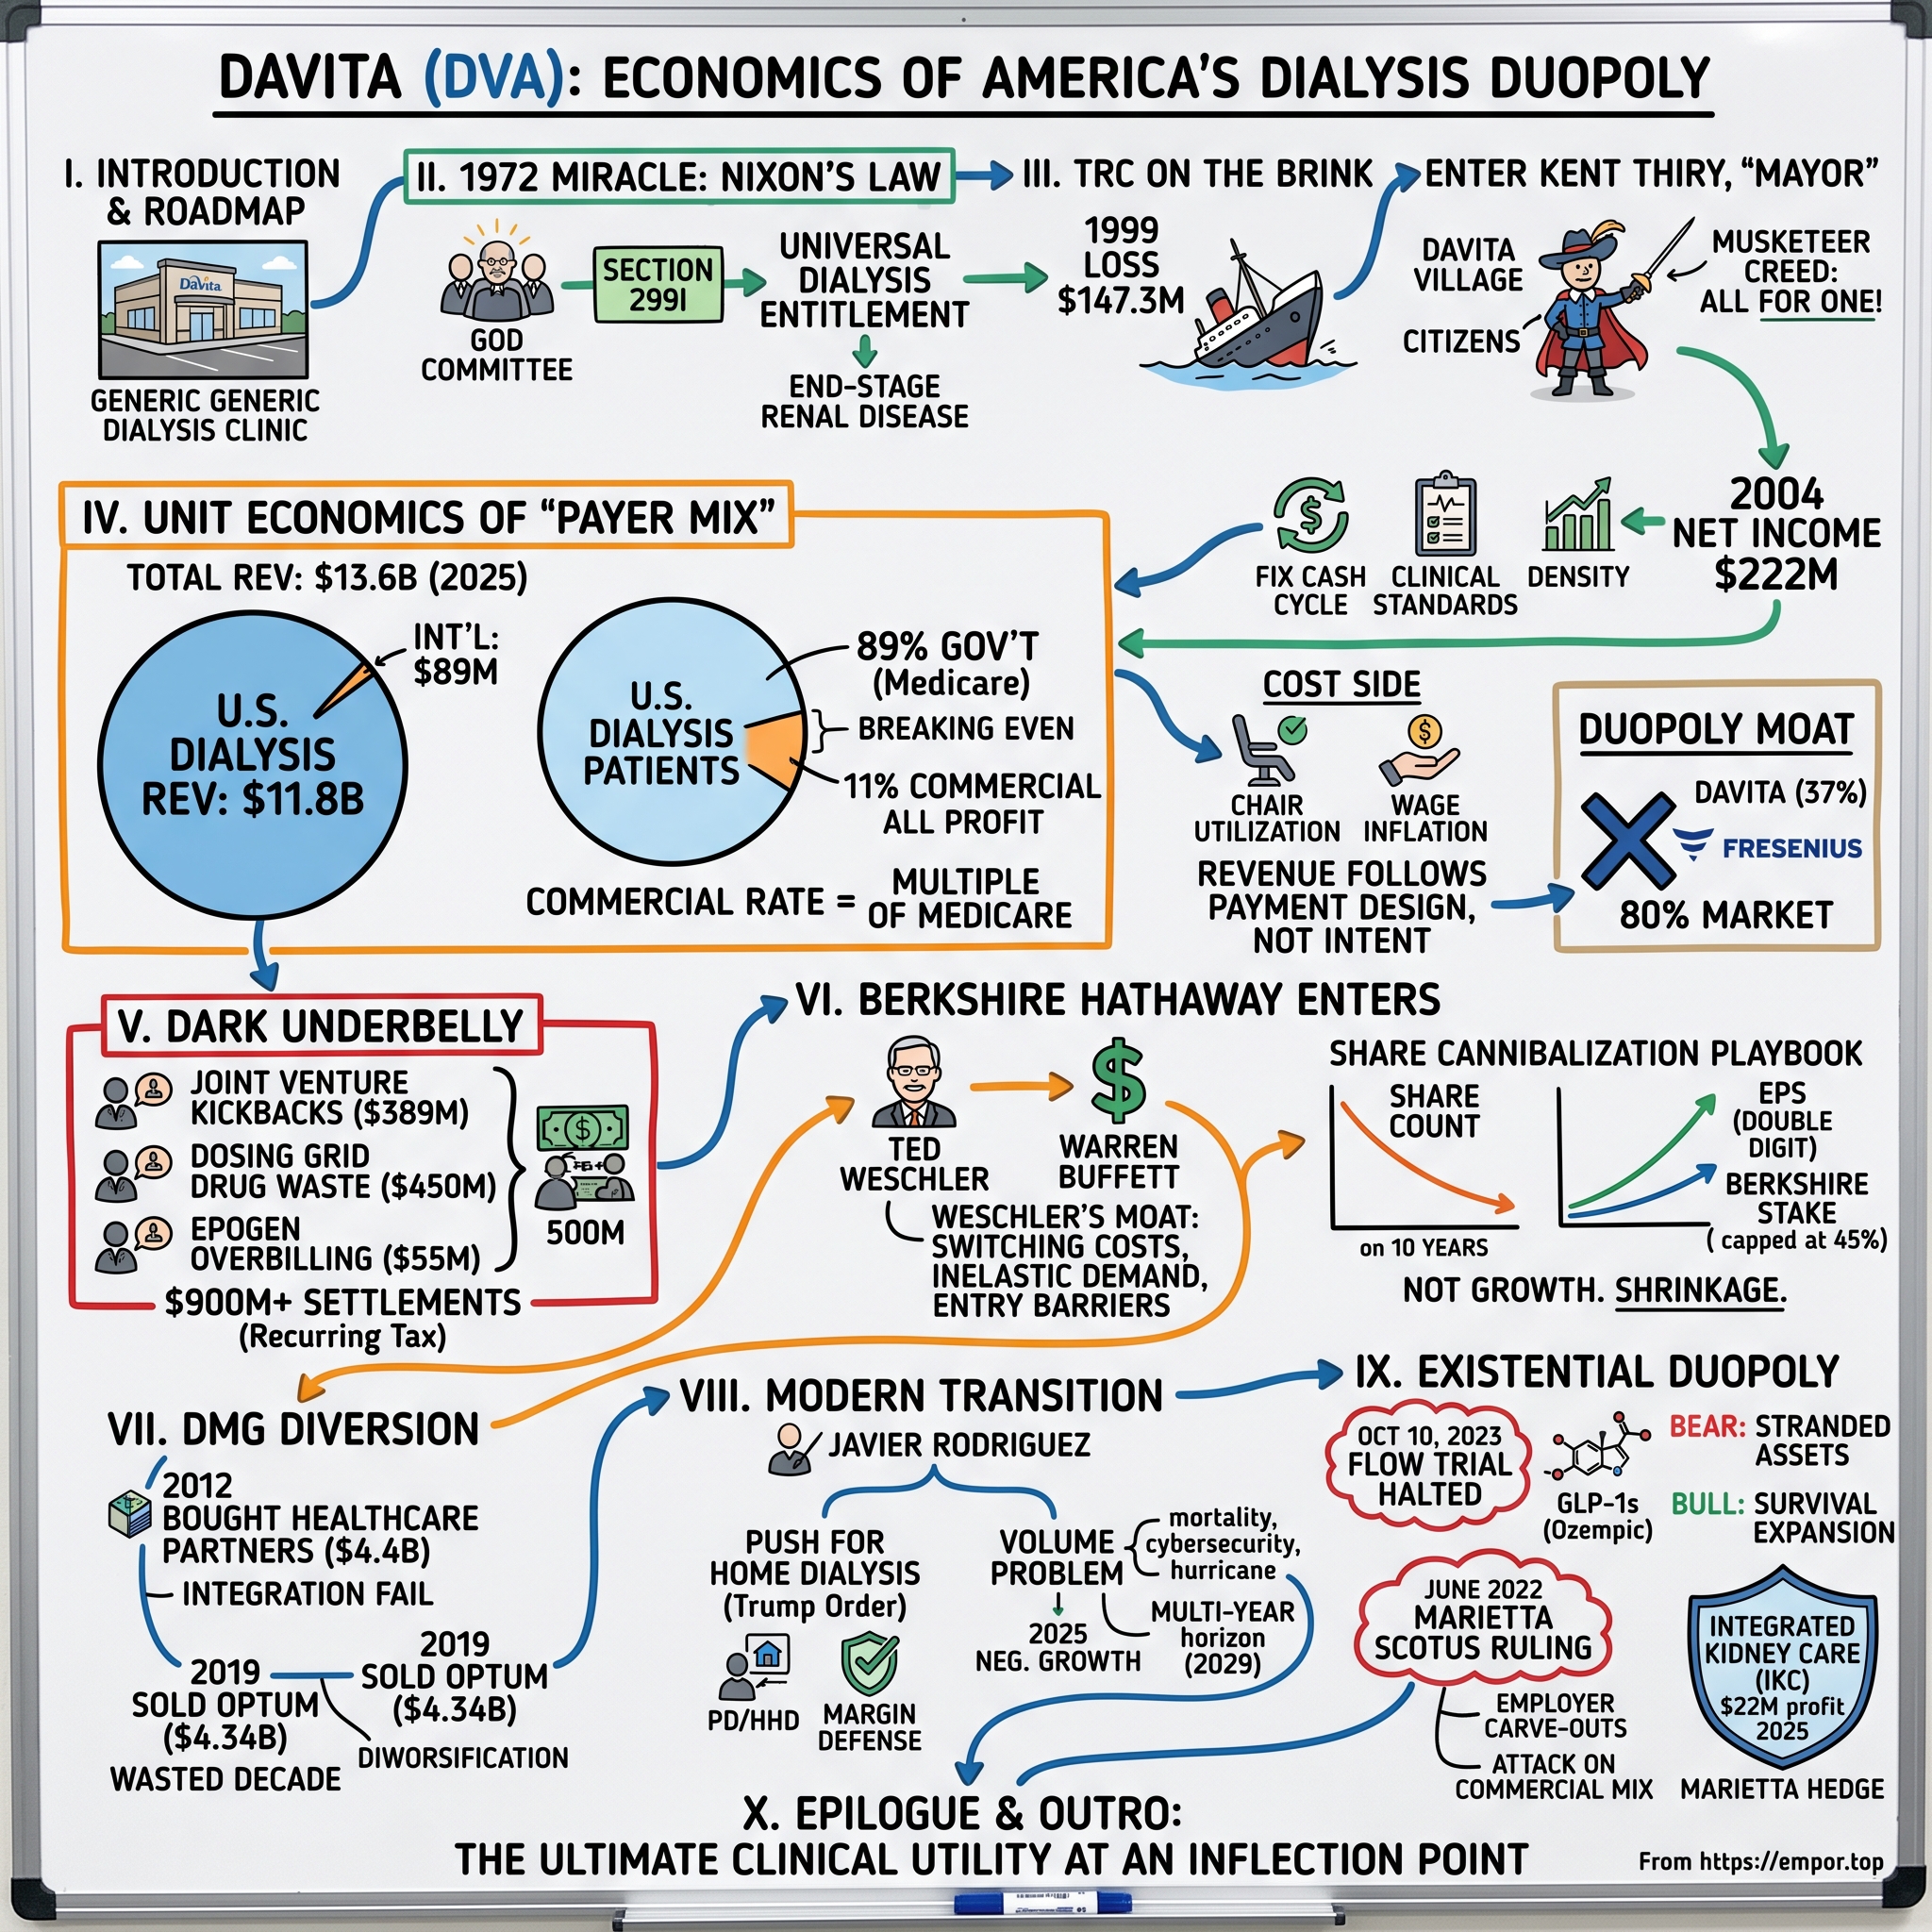
In fiscal 2025, DaVita generated consolidated revenue of about $13.64 billion and operating income of roughly $2.04 billion.1 In the first quarter of 2026, it delivered adjusted operating income of $482 million and adjusted earnings per share of $2.87, beating expectations and prompting management to raise full-year 2026 adjusted operating-income guidance to a range of $2.15 billion to $2.25 billion and adjusted EPS to $14.10 to $15.20.[^1]4 For a company whose organic treatment volumes have been essentially flat for years, those are the financials of something that should be growing much faster than it is.
The trick is not in the numerator. It's in the denominator. As of May 2026, DaVita had roughly 64.2 million shares outstanding — down from around 215 million in 2013.107 The company has, over a little more than a decade, retired something like seventy percent of its own equity. Every dollar of earnings gets divided among fewer and fewer owners. That is the engine. That is why a flat business throws off a rising stock.
To understand how DaVita earns those dollars in the first place, you need to understand four things, and this episode is built around them.
The duopoly. In-center dialysis in the United States is not a competitive market in any normal sense. DaVita and Germany's Fresenius Medical Care together control roughly 75–80% of U.S. dialysis stations. Two companies. One essential, life-sustaining service. That structure is the foundation of everything.
The cross-subsidy. Here is the asymmetry that funds the whole enterprise. The overwhelming majority of dialysis patients are covered by Medicare or Medicaid, which pay a flat, tightly capped rate that generally sits at or below DaVita's cost to treat them. A small minority are covered by commercial employer insurance, which pays multiples more. The commercial slice is where nearly all the profit lives. DaVita's job, reduced to its essence, is to protect that slice.
The Berkshire connection. Ted Weschler, one of Buffett's two investment lieutenants, understood this cross-subsidy math better and earlier than almost anyone. His conviction turned DaVita into a passive compounding position for Berkshire that has quietly grown to nearly half the company.6
The modern battlefield. And then there are the threats that make this more than a static utility: the GLP-1 drugs (Ozempic, Wegovy) that could, in theory, shrink the future pipeline of kidney-failure patients; the slow migration toward treating patients at home; and a years-long trench war with organized labor waged, of all places, on the California ballot.
Myth versus reality, up front
Before we go back in time, it's worth puncturing a few pieces of conventional wisdom, because DaVita is a company people think they understand and mostly don't.
The myth that it's a growth stock. It isn't, and pretending otherwise misreads the whole thesis. U.S. treatment volumes have been broadly flat for years; the FY2026 volume-growth guidance management was proud to raise landed at a whopping 25 to 50 basis points — a quarter to a half of one percent.4 The equity story is a per-share story, not a volume story.
The myth that dialysis is a great business because it's essential. Essential and profitable are different things. The government pays for the essential part at roughly breakeven; the profitable part is a narrow commercial slice that the company must fight to protect every single year. Essentiality is what makes demand durable, not what makes the business lucrative.
The myth that Buffett "bought" nearly half of DaVita. Berkshire largely drifted to ~45% ownership as the company retired its own shares underneath it — a distinction that turns out to be the most interesting mechanical fact in the entire story.69
Keep those corrections, and the paradox, in mind as we go: a business that barely grows, funded by a payer that loses it money, rescued by a payer that is only 11% of patients, owned nearly half by Berkshire, and compounding anyway. To see how something this strange got built, we have to go back to the wreckage it was built on top of.
 Subscribe on LinkedIn
II. The Dark Ages: Total Renal Care's Near-Death Experience
Picture Wall Street in the mid-1990s, drunk on a simple and seductive idea: the medical roll-up. Take a fragmented, mom-and-pop corner of healthcare — physician practices, imaging centers, dialysis clinics — buy up hundreds of them with cheap debt, bolt them together, and let the synergies and scale do the rest. The stock market loved these stories. They grew revenue on command. And they almost all ended the same way.
Total Renal Care (TRC) was one of them. Through the early and mid-1990s it did exactly what the playbook demanded: it acquired independent local dialysis clinics aggressively, financed by a rising tide of debt, expanding its physical footprint across the country at a furious pace. On a map, it looked like a triumph. Underneath, it was a time bomb.
Why dialysis, of all specialties? Because in the 1990s it looked like the perfect roll-up target. Demand was guaranteed by biology and subsidized by Medicare's ESRD entitlement. The clinics were owned in small local clusters by individual nephrologists — a fragmented cottage industry ripe for consolidation. And the revenue was recurring in the most literal sense: the same patients, three times a week, indefinitely. A financier looking at those characteristics saw an annuity waiting to be assembled. What that financier tended to underestimate was that an annuity only works if you can actually collect it — and collecting from a patchwork of government and commercial payers across hundreds of newly acquired clinics, each with its own systems and staff, is an operational problem of staggering complexity. The roll-up thesis was right about the demand and catastrophically wrong about the plumbing.
The problem with roll-ups is that buying a clinic is easy and integrating one is brutally hard. TRC grew its footprint far faster than it grew the plumbing to run it. The billing systems — the unglamorous back office that actually turns a dialysis treatment into collected cash — could not keep up. Centralized billing buckled. Receivables piled up uncollected. And in the cruelest irony for a company in the business of keeping people alive, clinics reportedly ran short on vital supplies while headquarters couldn't get its own money in the door. This is the classic roll-up death spiral: revenue that exists on paper but never converts to cash, layered on top of debt that demands cash on a fixed schedule.
By 1999 the reckoning arrived. Total Renal Care posted a staggering year-end loss of $417.3 million on revenue of about $1.45 billion, was in violation of its debt covenants, and carried roughly $1.4 billion of debt it had no obvious way to service.13 The stock, which had traded in the high $20s, collapsed toward the low single digits — a wipeout of more than ninety percent of shareholder value. Regulators circled. Patient-care complaints mounted. Executives left. This was not a turnaround situation; from the outside, it looked like a corpse that hadn't finished falling.
Into that scene, in October 1999, walked Kent Thiry.13
Thiry was not an obvious savior, and Wall Street didn't treat him as one. He was a Harvard MBA and a former Bain & Company partner — a consultant's consultant — who had run the dialysis business at competitor Vivra. Taking the top job at Total Renal Care looked, to most observers, like a career-limiting move: the salvage of a terminal asset, the kind of assignment you take when you have something to prove and little to lose. The prevailing view was that dialysis was a commoditized, government-price-controlled backwater, and TRC was its most broken player.
What almost nobody appreciated in 1999 was that the very things that made dialysis unglamorous — the flat government rates, the medical necessity, the fragmented local markets — were the raw materials of an extraordinarily durable business, if someone could impose operational discipline on it. The asset wasn't terminal. It was mismanaged. And the man walking in the door happened to believe, with almost religious intensity, that culture and operations were the same problem viewed from two angles. That belief was about to get one of the more unusual field tests in corporate history.
III. The "Village" Culture & Rebuilding from the Brink
To grasp how odd the next chapter was, you have to imagine a Fortune 500 CEO striding onto a stage dressed as one of the Three Musketeers, sword raised, leading thousands of dialysis technicians in a call-and-response chant of "One for all, and all for one!" That was not a one-off stunt. That was the operating system.
Renaming a corpse
Thiry's first radical act was symbolic. In 2000, the leadership put the company's identity to a vote, and Total Renal Care was reborn as DaVita — from an Italian phrase meaning roughly "to give life."13 It sounds like a marketing exercise, and cynics read it that way. But the renaming was deliberate psychological demolition. The old name carried the stink of near-bankruptcy, uncollected bills, and empty supply closets. Thiry wanted the tens of thousands of frontline workers who actually kept patients alive to feel they belonged to something being reborn rather than something dying.
He built an entire vocabulary around it. Employees became "citizens" of "the Village." Clinics were "neighborhoods." Thiry called himself the "Mayor." Company gatherings featured songs, chanting, and the Musketeer theatrics that became legendary — and, to plenty of outside observers, faintly ridiculous.13 The neutral read is that some of this was undeniably a cult of personality, and it deserves the raised eyebrow it usually gets.
But there was a hard-nosed logic underneath the pageantry. Dialysis is delivered by a distributed army of caregivers in thousands of separate buildings, most of whom will never meet senior management. Clinical quality and, crucially, billing accuracy depend on those people caring about doing it right. A shared identity — even a hokey one — is a genuinely cheap way to reduce turnover and error in a workforce that is otherwise almost impossible to supervise centrally. The Village was culture as a control system.
The unglamorous engine underneath
The chanting made headlines. The operational overhaul made the money. Thiry's team rebuilt the collapsed billing and compliance infrastructure — the boring machinery that had actually killed the old company — so that treatments reliably converted into collected revenue. They standardized clinical protocols and supply chains across the neighborhoods. This is the part that doesn't sing on stage: DaVita's turnaround was, at its core, a receivables-and-operations story dressed in a costume.
The most strategically brilliant move was structural: physician joint ventures. In dialysis, the person who decides where a newly diagnosed patient goes is the treating nephrologist. Control that referral, and you control the patient. DaVita's answer was elegant and durable — co-own the clinic with the local nephrologists, typically holding a controlling stake (often around 51%) while the doctors held the rest. Overnight, the physicians who steered patients were no longer independent gatekeepers to be courted; they were partners whose personal financial upside was welded to the clinic's efficiency and success. It aligned incentives, locked in referral pipelines, and made it economically painful for a competitor to peel a doctor away. We'll return to this as a formal "power" later — for now, note that it converted the single biggest external dependency in the business into an internal one.
The joint-venture model also sits on a permanent legal knife-edge, and any honest account has to say so. Federal law — the Stark Law and the Anti-Kickback Statute — sharply restricts financial relationships between providers and the physicians who refer patients to them, precisely to prevent referrals from being bought. Dialysis JVs operate within carefully constructed safe harbors, but the line between "aligning a physician-owner's incentives" and "paying a physician for referrals" is exactly the line the government polices. That tension is not theoretical; it is the seam that whistleblowers and prosecutors have repeatedly probed, and it is why the same structure that is DaVita's greatest competitive asset is also a recurring source of legal exposure. The moat and the liability are, uncomfortably, the same wall.
Consolidating the duopoly
By 2004, DaVita was healthy enough to go on offense, and it made the defining acquisition of its history: Gambro Healthcare for roughly $3.05 billion in cash.14 The deal added around 565 clinics and vaulted DaVita to roughly 96,000 patients across more than 1,200 centers, with combined revenue near $4.4 billion.14 More important than the scale was the market structure it created. Removing Gambro as an independent player left the United States with, in effect, two national dialysis companies — DaVita and Germany's Fresenius Medical Care AG & Co. KGaA. The Federal Trade Commission required DaVita to divest dozens of clinics to clear the deal, a tacit acknowledgment of exactly how concentrated the market was becoming.15 From 2004 onward, American dialysis was a duopoly, and it has stayed one.
The shadow
It would be dishonest to tell this as a pure redemption arc. The same aggressive, high-pressure culture that rebuilt the company also drove behavior that regulators and whistleblowers spent years unwinding. Under the False Claims Act, DaVita paid a series of large settlements: $450 million in 2015 (plus fees, reaching about $495 million) to resolve allegations that it deliberately overfilled vials of drugs like Amgen's Epogen and billed Medicare for the waste; and, in 2014, more than $350 million to settle claims that it paid kickbacks to physicians to secure patient referrals — the darker mirror image of the joint-venture model.1617 Cumulatively, DaVita's various fraud and kickback settlements ran well past $800 million over the years. And the company's hardball approach to labor and competition planted the seeds of the antitrust and union battles that would define the following decade.
That is the honest ledger of the Thiry turnaround: a genuinely great operational and cultural rescue, and a pattern of pushing the legal and ethical envelope hard enough to keep the lawyers permanently busy. Both are true. Both flow from the same intensity. And both set up the economic engine we need to dissect next — because the reason all of this was worth fighting over is a payment structure unlike almost anything else in American business.
IV. The Duopoly Economics & The Commercial Cross-Subsidy Moat
Walk into a DaVita clinic and it looks almost aggressively ordinary: a bright room, fifteen to twenty reclining chairs, each beside a machine roughly the size of a mini-fridge, a patient in each one with two needles in an arm and blood running out through tubing, into the machine, and back. A session lasts about four hours. Most patients come three times a week. The chairs run in two or three shifts a day, six days a week, because idle chairs are the enemy of the economics. It is, deliberately, an assembly line for keeping people alive. And that boring predictability is precisely what makes the financial structure sitting on top of it so powerful — and so strange.
What the machine actually does
It helps to understand, in plain terms, what that mini-fridge is doing, because the medicine explains the business. Healthy kidneys are the body's filtration and chemistry-balancing system: they pull waste products and excess fluid out of the blood continuously, twenty-four hours a day, and keep the body's salts and acids in a narrow safe band. When kidneys fail — the end stage of chronic kidney disease — that filtration stops, and toxins and fluid begin to accumulate. Left untreated, the patient dies within weeks. Hemodialysis is, essentially, an external kidney: the machine pumps the patient's blood through a filter called a dialyzer — a cartridge packed with thousands of hair-thin semipermeable fibers — that strips out waste and pulls off excess fluid, then returns the cleaned blood to the body. Peritoneal dialysis, the main home alternative, does the same job differently, using the natural membrane lining the abdomen as the filter and a sterile fluid to draw waste across it.
The clinical reason patients come three times a week is that the machine is a crude substitute for a continuous organ; you cannot skip sessions without letting toxins and fluid build to dangerous levels. That biological fact is the source of the business's most valuable trait — patients who literally cannot stop coming — and it is why a dialysis clinic, unlike almost any other retail-footprint healthcare business, enjoys near-perfect demand predictability. The company knows, weeks in advance, almost exactly how many treatments it will deliver.
Two companies, one market
The other half of the duopoly is worth a moment, because it shapes DaVita's competitive reality. Fresenius Medical Care occupies a genuinely different structural position: it is not only the largest dialysis provider alongside DaVita, it is also the world's dominant manufacturer of the machines and dialyzers that DaVita and everyone else buys. That vertical integration gives Fresenius a supply-chain vantage point DaVita lacks; DaVita, in turn, is the more focused U.S. clinic operator with the deeper joint-venture physician network in many of its markets. The important point for an investor is what the two companies do not do: they do not wage price war on each other. In a market where prices for the majority of patients are set by the government anyway, and where the profitable commercial rates are negotiated plan-by-plan, there is little to be gained and much to be lost from aggressive share-grabbing. The result is the calm, high-return equilibrium that two rational players tend to settle into — the textbook behavior of a stable duopoly, and the reason both companies can earn attractive returns on a service the government reimburses at cost.
The asymmetric payer mix
Here is the single most important fact about DaVita's economics, and it is worth slowing down for.
Roughly 89% of DaVita's patients are covered by the government — Medicare or Medicaid. This is not an accident of demographics; it is written into federal law. End-Stage Renal Disease (ESRD) is the only condition in America that automatically qualifies a person for Medicare regardless of age. A 34-year-old whose kidneys fail becomes Medicare-eligible. So over time, almost every dialysis patient ends up on federal coverage. Medicare pays a flat, tightly regulated rate per treatment — on the order of a few hundred dollars — that generally sits at or below what it actually costs DaVita to deliver the care.
Read that again: on nearly nine of every ten patients, the company's largest payer reimburses at roughly breakeven or a loss.
So where does the profit come from? The other ~11% — patients covered by commercial, employer-sponsored insurance. Commercial plans pay market-negotiated rates that are multiples of the Medicare rate, frequently in the range of four to ten times higher. The same four hours in the same chair delivered to a commercially insured patient can be worth many hundreds or a few thousand dollars more than it is worth when Medicare is paying.
This is the cross-subsidy, and it is the whole game. A thin sliver of commercially insured patients generates the profit that funds the structural losses on the vast government-covered majority. DaVita is not really a dialysis company in the way it presents itself; it is a company that harvests commercial insurance reimbursement and uses dialysis as the mechanism to do it. Everything strategic — clinic density, joint ventures, patient retention, the political fights — ultimately protects that 11%.
The 30-month golden window
Federal law even puts a clock on it. Under the Medicare Secondary Payer (MSP) statute, when a working, commercially insured person is diagnosed with kidney failure, their employer plan must remain the primary payer for the first 30 months. Only after that window does the patient roll onto Medicare as primary. So for every commercially insured patient, DaVita has a roughly two-and-a-half-year period of premium reimbursement before that revenue steps down to the government rate. The economic imperative that follows is blunt: keep those patients healthy, engaged, and enrolled through the full 30 months. A commercially insured patient who dies early, or drops coverage early, is not just a human tragedy — it is the loss of the single most valuable revenue stream the company has.
The existential legal threat: Marietta
If the entire profit structure hangs on that commercial sliver, then anything that lets employer plans pay dialysis providers less is an existential threat. In June 2022, that threat reached the Supreme Court.
The case was Marietta Memorial Hospital Employee Health Benefit Plan v. DaVita. An employer health plan had designed its benefits so that all outpatient dialysis providers were treated as "out-of-network" and reimbursed at a low, uniform rate. DaVita sued, arguing this was a thinly disguised way of singling out ESRD patients — who are overwhelmingly dialysis patients — and thus violated the MSP statute's anti-discrimination provisions. The stakes were enormous: if employer plans could freely cap dialysis reimbursement, the commercial cross-subsidy could unravel.
The Court ruled 7–2 against DaVita.[^3] Because the plan's low reimbursement applied uniformly to all dialysis patients regardless of whether they had ESRD, Justice Kavanaugh's majority reasoned, it did not "differentiate" and therefore did not violate the statute.[^3][^12] In plain terms: a neutral, across-the-board cap on dialysis is legal, even if in practice it lands almost entirely on kidney-failure patients.
Dialysis stocks sold off on the fear that employers would now rush to carve out or cap dialysis coverage en masse. But — and this is where the duopoly's physical moat did the talking — the feared wave never crested. The reason is instructive. An employer plan can cap dialysis reimbursement in theory, but its members still need somewhere to be dialyzed three times a week, and in most of the country the only somewheres are DaVita and Fresenius clinics. A plan that pushes rates too low, or tries to exclude the duopoly, risks leaving its members with no adequate in-network access to a life-sustaining service — a legal and practical problem of its own. The very market concentration that draws regulatory heat also functions as a shield: you cannot carve out a provider you cannot replace. Management's post-Marietta commentary leaned heavily on exactly this logic, and to date commercial mix has eroded gradually rather than collapsing. The threat is real and ongoing, but it has behaved more like slow water pressure than a dam break.
The 7 Powers view
It's worth naming DaVita's advantages in Hamilton Helmer's framework, because they're unusually clean.
Scale economies. National clinic density gives DaVita real purchasing leverage over dialysis machines, dialyzers, and drugs, and it spreads regional overhead across more treatments. In a business with tightly capped government prices, being the low-cost operator is not a luxury; it is survival.
Switching costs. These are close to absolute. A dialysis patient physically cannot skip treatment, has built relationships with the clinic staff who literally keep them alive, and would have to disrupt a life-or-death routine to change providers. Patient churn between clinics is structurally low — not because of a loyalty program, but because switching is genuinely hard and mildly terrifying.
Cornered resource. The joint-venture nephrologist network. By co-owning clinics with a large share of local kidney doctors, DaVita has effectively contracted with the gatekeepers who decide where patients go. A new entrant doesn't just need capital and real estate; it needs to pry loose physicians whose economics are already tied to the incumbent.
Put together, these powers explain why the duopoly is stable and why returns on the commercial slice are so high. What they do not do is generate growth — the U.S. patient pool grows slowly, and the government reprices the majority of it at breakeview. Which is exactly why DaVita's most important strategic decision turned out to be about capital allocation rather than operations, and why one investor in Virginia saw it before almost anyone.
V. The Ultimate Share Cannibal: Ted Weschler and the Berkshire Hathaway Playbook
In the late 2000s, a low-profile hedge-fund manager in Charlottesville, Virginia, was building an outsized position in an unloved dialysis stock. His name was Ted Weschler, and his fund was Peninsula Capital Advisors. Weschler ran a concentrated, deeply researched book — a handful of positions he understood better than anyone else on Earth. DaVita became one of his largest bets.
The thesis before it was a Berkshire thesis
What did Weschler see that the market discounted? Precisely the structure we just walked through. A regulatory duopoly in an essential, recession-proof service. Near-total patient lock-in. A commercial cross-subsidy that produced highly predictable free cash flow. And — critically — a business that did not need to grow its patient count to grow its per-share value, because management could take that predictable cash and shrink the share base with it. A slow-growth business with a fortress balance sheet of demand and a capital-allocation lever is, for a certain kind of investor, close to ideal. It doesn't need the future to cooperate. It just needs to keep buying back stock.
Weschler's path to Berkshire is itself part of the legend. A former investment banker who built Peninsula into a quietly spectacular record, he twice won Buffett's annual charity lunch auction — paying millions for the privilege of a meal — and those conversations helped lead to his hiring as one of Berkshire's two outside-recruited investment managers alongside Todd Combs. When Weschler joined in early 2012, he did not leave his best ideas behind; he brought his DaVita conviction with him. Berkshire began accumulating shares in 2011–2012 and kept building the position over the following years, until DaVita became one of the largest holdings that neither Combs nor Buffett himself had originated.6
What makes the DaVita position such a pure expression of the Weschler style is that it required no catalyst, no activism, and no cleverness after the initial insight. It was a bet that a well-run duopolist would keep doing the obvious thing — generating cash and retiring shares — for a very long time. The edge was not information; it was temperament and time horizon. Most investors cannot own a flat-volume business for a decade and call it a triumph. Weschler could, because he was underwriting the per-share outcome, not the top line.
How Berkshire ended up owning nearly half a company
Here is the quietly remarkable part. Berkshire never had to buy its way to ~45% ownership. It drifted there. Because DaVita was relentlessly repurchasing and retiring its own shares, the denominator kept shrinking. Berkshire could hold its share count roughly steady — or even sell a little — and watch its percentage ownership climb, simply because everyone else's shares were being canceled. It is ownership by attrition: stand still while the float melts around you, and your slice of the pie grows.
By 2025–2026, that drift had carried Berkshire to around 44–45% of DaVita — an extraordinary concentration for a passive position in a critical healthcare provider.69 To manage the obvious regulatory and governance discomfort of Berkshire controlling something so essential, the two sides operate under a standstill and repurchase arrangement: Berkshire has agreed to keep its stake below a ceiling near 45%, and — in a neat mechanical twist — it periodically sells shares back to DaVita as part of the buyback program precisely so that the shrinking float doesn't push it over the line. In 2026, for instance, Berkshire trimmed its holding to keep the stake around the mid-40s, selling into DaVita's own repurchases.9 The buyback machine and the standstill are locked in a slow dance: DaVita retires stock, Berkshire's percentage rises, Berkshire sells a sliver back, and the cycle repeats.
The masterclass, by the numbers
Now the headline act. In 2013, DaVita had roughly 215 million shares outstanding. By early-to-mid 2026, that number had fallen to about 64.2 million.710 That is a reduction on the order of seventy percent of the company's equity, retired in a little over a decade.
Think about what that does to per-share math. If you own the same business but divide it among one-third as many shares, each remaining share lays claim to roughly three times the earnings, all else equal. So even in years when the actual number of treatments was flat — or slightly down, as it was when COVID-19 inflicted excess mortality on DaVita's medically fragile ESRD population — earnings per share kept marching higher at a double-digit clip. The business stood still; the per-share value ran.
The strategic choice underneath this is the thing to admire and to interrogate. DaVita pays no dividend. It has largely sworn off big, splashy M&A (for reasons we'll get to in the next section, it learned that lesson the hard way). Instead, it funnels the overwhelming majority of its free cash flow into buying back its own stock. In the first quarter of 2026 alone, management repurchased 3 million shares during the quarter and another 2 million after quarter-end — the latter including shares bought directly from Berkshire.4 The company operates under board buyback authorizations that it refreshes as it exhausts them; in August 2025, the board added a fresh $2 billion of repurchase capacity on top of an earlier $2 billion authorized in September 2024.1110
The neutral analyst's question is the right one to sit with: is this brilliance or is it a company out of better ideas? The bull says DaVita has found the highest-return use of its cash — shrinking the equity of a fortress-like cash generator, magnified by leverage. The skeptic notes that aggressive buybacks funded partly by debt are also what a management team does when it cannot grow the underlying business and has no attractive place to reinvest. Both readings fit the same facts. What's not debatable is that share cannibalization is the strategy — not a sideshow to it. And the last time DaVita tried the alternative — actually spending its cash on growth — it produced the most expensive lesson in the company's modern history.
VI. The M&A Detour & The Great Optum Pivot
Every disciplined capital allocator has a story about the one time they weren't. For DaVita, that story is HealthCare Partners, and it is the crucial counter-example that makes the buyback religion make sense.
The $4.4 billion bet on the future of healthcare
Rewind to 2012. The Affordable Care Act had just been upheld by the Supreme Court, and the smart-money thesis in healthcare was that the future belonged to integrated, capitated care — organizations that would be paid a fixed fee per patient and rewarded for keeping people healthy rather than for running up procedures. Kent Thiry, never short on ambition, decided DaVita should ride that wave. In May 2012, DaVita agreed to acquire HealthCare Partners — a large operator of capitated medical groups and physician networks — for approximately $4.42 billion, a mix of roughly $3.66 billion in cash and about 9.4 million DaVita shares, with up to $275 million more in contingent earn-outs.18 The combined entity was briefly renamed DaVita HealthCare Partners.
The vision was genuinely grand. Instead of being a single-specialty dialysis operator — a narrow, if lucrative, slice of a patient's care — DaVita would become a "total care manager." Under capitation, if DaVita managed the whole healthcare needs of a population of chronically ill patients, it could pocket the savings from keeping those expensive patients out of hospital beds. Kidney patients are among the most complex and costly in the system; who better to manage them end-to-end than the company already seeing them three times a week? On a whiteboard, it was compelling.
Why it didn't work
The whiteboard lied, and the reasons are a clinic in how easily "adjacent" businesses turn out to be foreign ones.
Operational mismatch. Running broad primary-care physician groups is a fundamentally different, messier, lower-margin craft than running dialysis clinics. Dialysis is an assembly line: predictable patients, predictable protocols, predictable throughput. Managing the total care of a diverse patient population is sprawling, variable, and hard to standardize. DaVita's operating muscles were built for the former and strained at the latter.
Volatility. Capitation flips the risk model. In dialysis, DaVita gets paid per treatment. In capitated primary care, it accepts a fixed payment and eats the cost of whatever care the patient needs — exposing it to medical-loss-ratio swings. A handful of unexpectedly expensive hospitalizations in a region could vaporize that region's quarterly profit. The predictable cash flow that made DaVita investable was exactly what the HealthCare Partners model lacked.
The writedowns. Reality showed up in the accounting. The medical group repeatedly missed its profit targets, and DaVita was forced into restructuring charges and goodwill impairments — including a roughly $77 million goodwill impairment in 2016 — as the division's economics fell short of the optimistic deal model. Impairments are, in plain English, management admitting in the financial statements that it overpaid.
The course correction
To DaVita's credit — and this is the part that reflects well on the discipline it otherwise preaches — it did not double down on a losing hand. In late 2017 it agreed to sell the renamed DaVita Medical Group (DMG) to UnitedHealth Group's Optum. The deal was originally struck at about $4.9 billion, but the price was ground down before it finally closed in June 2019, landing at roughly $4.3 billion after adjustments and a regulator-mandated carve-out: the FTC required DaVita to divest DMG's Nevada operations (sold to Intermountain Healthcare) to preserve competition in the Las Vegas area.[^5] Round-trip, DaVita spent seven years and a great deal of management attention to end up roughly where it started, minus the opportunity cost.
But the divestiture did something strategically decisive: it turned DaVita back into a pure-play kidney-care company and freed up billions in cash. And where did that cash go? Not into another grand adjacency. It went into paying down debt and, above all, into the buyback machine. The HealthCare Partners detour is the reason the share-cannibal strategy has such conviction behind it — DaVita tried the alternative, measured the result, and chose to stop pretending it was a diversified healthcare platform.
There is an uncomfortable counterfactual worth sitting with, though, because it complicates the tidy "discipline restored" narrative. The years DaVita spent building, integrating, writing down, and then unwinding HealthCare Partners overlapped almost exactly with the period when Optum, the very buyer of DMG, was assembling one of the most powerful integrated-care platforms in American healthcare. DaVita arrived at the capitated-care thesis early and correct — and then handed the asset to the competitor who executed it. The lesson management drew was "stick to dialysis." An equally valid reading is that DaVita had the right idea and the wrong operating capability, and that its circle of competence is narrower than its ambitions were. Both readings argue for the same present-day strategy — return the cash — but they imply very different things about the ceiling on the business. Enforcing that discipline would fall to a new CEO, because by the time DMG was sold, the Thiry era was ending.
VII. The Javier Rodriguez Era & The Future Business
In June 2019, the Musketeer took off the costume for the last time. Kent Thiry stepped down as CEO after roughly two decades, closing the most theatrical chapter in the company's history.13 His successor could hardly have been a sharper contrast.
The operator takes over
Javier Rodriguez joined DaVita in 1998 — meaning he had been in the building through the near-death experience, the renaming, the Village, the Gambro consolidation, and the HealthCare Partners misadventure. He rose through the core Kidney Care business, running it as president before taking the top job. Where Thiry was theatrical, evangelical, and culture-first, Rodriguez is analytical, numbers-driven, and operations-first. Wall Street's shorthand is that Thiry sold the vision and Rodriguez runs the spreadsheet. He is respected precisely for the unglamorous things — labor scheduling optimization, cost-per-treatment discipline, and unbending capital allocation. In a mature business whose value creation now lives in per-share math, that is arguably exactly the temperament the company needed.
Clearing the antitrust cloud
Rodriguez's transition did not begin cleanly. In 2021, the Department of Justice took the extraordinary step of criminally indicting both DaVita and Kent Thiry personally, alleging that DaVita had entered into "no-poach" agreements with competitors — including Surgical Care Affiliates — not to solicit each other's senior employees, in violation of the Sherman Act.[^4] This was a marquee case in the DOJ's then-new campaign to treat labor-market collusion as criminal antitrust, and a conviction would have hung a lasting cloud over the company and its former leader.
In April 2022, a federal jury in Denver acquitted both DaVita and Thiry on all counts. It was a landmark defeat for the DOJ's criminal labor-market enforcement theory, and for DaVita it removed a serious regulatory and reputational overhang just as Rodriguez was consolidating control. The neutral point worth flagging: an acquittal means the government failed to prove a crime beyond a reasonable doubt, not that nothing happened — the very existence of the alleged non-solicitation understandings is part of the broader pattern of aggressive competitive conduct that has followed DaVita for years. But legally, the matter was closed, and it cleared the runway.
Skin in the game
On management alignment, the picture is favorable. According to DaVita's 2026 proxy materials, Rodriguez holds a substantial personal stake — on the order of 840,000-plus shares, worth well over $190 million and representing more than one percent of the company — and the large majority of his annual compensation (over 70%) is equity-based and tied to multi-year operating and EPS performance rather than paid in cash.12 For an investor, that structure is roughly what you want: a CEO whose personal wealth rises and falls with the same per-share metrics the buyback strategy is engineered to drive. It's not a guarantee of good decisions, but it makes bad, self-serving ones costlier to him personally.
The numbers man beside the numbers man
Rodriguez does not run the capital allocation alone. CFO Joel Ackerman has become the public voice of the financial machine, and his commentary on earnings calls is notably plain-spoken about the mechanics that matter: how many shares were repurchased, where commercial mix is heading, and why revenue per treatment will move the way it will. On the Q1 2026 call, it was Ackerman who confirmed the company had bought back 3 million shares in the quarter and 2 million more afterward — including the block purchased from Berkshire — and Ackerman who told analysts, without varnish, to expect commercial mix to decline over the year and pressure revenue per treatment.4 That willingness to pre-announce a headwind rather than let analysts discover it is, in the neutral analyst's ledger, a modest but real credibility marker. Management that narrates its own pressure points tends to be more trustworthy than management that only narrates tailwinds.
Where growth is supposed to come from
Rodriguez inherited a business with flat U.S. volumes and a repriced government majority. So where does any growth come from? Management points to three pillars, and each deserves a clear-eyed look at both the promise and the proof.
Home dialysis. This is the most strategically important operational shift. Instead of coming to a clinic three times a week, patients dialyze at home — either home hemodialysis or peritoneal dialysis, a gentler modality that uses the lining of the abdomen to filter blood, often done overnight. The appeal is real on multiple axes: home treatment avoids the capital cost of building and staffing physical clinics, tends to carry higher operating margins, and is associated with better clinical outcomes and fewer hospitalizations. DaVita has set aggressive long-term targets to move a large share of eligible patients — management has pointed at figures around a quarter or more of its population — toward home modalities. The honest caveat: home dialysis has been "the future" for many years, adoption depends on patient suitability and training capacity, and progress has been steady rather than explosive. It is a genuine margin and growth lever, but a gradual one.
Value-based care. Here DaVita is taking a second, more disciplined run at the idea that broke it with HealthCare Partners — but narrowly, inside its own specialty. Through arrangements with Medicare Advantage plans and government programs, DaVita takes on downside risk for the total cost of care of chronic-kidney-disease and ESRD patients. Because it already coordinates their dialysis, and can now layer in pharmacy, diet, and clinical management, it aims to reduce hospitalizations and share in the savings. The logic is sound and the scope is far more contained than the sprawling primary-care bet was. But it reintroduces medical-loss-ratio volatility, and the results so far are early. It's an option worth watching, not yet a proven profit engine.
International. DaVita has been exporting the clinic playbook abroad — across parts of Europe, Latin America, and Asia. This has become a genuine source of volume growth precisely because the U.S. is saturated: in 2025, consolidated patient census grew about 5%, driven substantially by international acquisitions, notably in Brazil, and international revenue grew roughly 38% year-over-year on those deals.1 International is where the unit-count growth actually is, though it comes without the American commercial cross-subsidy and at different, generally lower, margins.
Taken together, the future business is less a growth story than a mix-improvement and optionality story: shift patients to cheaper home settings, capture care-coordination savings, and buy volume abroad, while the buyback does the per-share heavy lifting. That is a coherent plan for a mature duopolist. But it operates against a backdrop of two adversaries who would very much like to break the model — one wearing a union pin, the other holding a syringe of semaglutide.
VIII. The SEIU War & The California Ballot Initiative Battles
Some corporate fights happen in courtrooms and boardrooms. This one happened at the ballot box, and it cost more than a quarter of a billion dollars.
The adversary was the Service Employees International Union–United Healthcare Workers West (SEIU-UHW), one of the most aggressive healthcare unions in the country. Its problem was structural: DaVita's clinical workforce is spread across thousands of small clinics, which makes traditional union organizing — one facility at a time — slow, expensive, and easy for the company to resist. So the SEIU changed the battlefield. If it couldn't organize the workers directly, it would use California's direct-democracy ballot-initiative system to attack the economics of the business until the company came to the table.
What followed was three straight election cycles of costly trench warfare.
Proposition 8 (2018) was the most economically pointed. It sought to cap dialysis clinics' revenue at 115% of the direct cost of patient care, forcing any "excess" to be rebated to insurers. Read against everything we've established about the commercial cross-subsidy, this was a dagger aimed at the heart of the model — it would have effectively confiscated the high-margin commercial reimbursement that funds the entire enterprise. Voters rejected it.
Proposition 23 (2020) took a different angle: it would have required a licensed physician to be physically present at every clinic during all treatment hours. That sounds like a patient-safety measure, but dialysis is normally supervised by nurses and technicians under a physician medical director who isn't on-site every hour; mandating a doctor in every chair-room at all times would have loaded enormous, arguably unnecessary cost onto each clinic. Voters rejected it too.
Proposition 29 (2022) was essentially the sequel to 23 — on-site clinician requirements plus a mandate that clinics get state approval before closing or reducing services. Same logic, same result: rejected.3
The economics of the defense were staggering. Across these cycles, DaVita and Fresenius together poured well over $300 million into opposition campaigns — among the most expensive ballot-measure fights in American history.3 Their argument was consistent: these were not genuine patient-safety reforms but "hardball" organizing tactics dressed up as regulation, whose real effect would be to make clinics uneconomic and force closures, especially in rural areas where a single clinic might be the only option for hours in any direction.
California voters sided with the companies all three times, and by decisive margins. But the neutral read cuts two ways. The duopoly demonstrated overwhelming resolve and financial firepower to defend its margins — a real asset. Yet the sheer fact that the entire California business model could be put to a popular vote, three times in five years, is itself a flashing indicator of how politically and regulatorily exposed this company is. The moat is wide, but part of its wall is made of ballot-measure outcomes and Medicare rate-setting decisions — things DaVita influences but does not control.
There is a subtler lesson in the SEIU campaign for anyone modeling the business. The union chose ballot initiatives because the workforce is too distributed to organize conventionally — the same distribution that makes DaVita's labor costs hard to unionize also makes them hard to control when the labor market tightens. The company won the political battles but cannot win the demographic one: dialysis requires trained nurses and technicians, those workers are in structurally short supply across U.S. healthcare, and their wages set the floor under cost per treatment. The union wars, in other words, were a visible skirmish over a permanent, invisible pressure. The next threat wouldn't come from a picket line or a petition at all. It would come from a blockbuster drug, and for a few hours it looked far more dangerous.
IX. The GLP-1 Panic & Actuarial Stress Test
On October 11, 2023, dialysis investors got a jolt that had nothing to do with dialysis. Novo Nordisk announced it was halting its Phase 3b FLOW trial early — not because the drug had failed, but because it had worked so well that continuing was no longer justified. The drug was semaglutide, sold as Ozempic and Wegovy, and the trial showed it meaningfully slowed the progression of chronic kidney disease in patients with type 2 diabetes.28
The logic the market ran was instantaneous and brutal. If a widely used, wildly popular class of drugs slows kidney disease, then fewer people will progress to kidney failure, which means a shrinking future pipeline of dialysis patients, which means DaVita's terminal value — the assumption that there will always be more patients — was suddenly in question. Dialysis stocks cratered overnight. DaVita fell roughly 15%, and Fresenius dropped around 24%.2 In a single session, the GLP-1 revolution had reframed DaVita from a fortress into a melting ice cube.
Then management did something more useful than panic: it did the actuarial math out loud, on earnings call after earnings call from late 2023 through 2026. The defense CEO Javier Rodriguez and CFO Joel Ackerman mounted is genuinely worth understanding, because it is a rare case of a company's counter-narrative resting on clinical epidemiology rather than spin.
The cardiovascular survival paradox
Here is the counterintuitive core of it. The overwhelming majority of people with Stage 3 or Stage 4 chronic kidney disease never actually reach dialysis — because they die first, usually of cardiovascular events, before their kidneys fully fail. Kidney disease and heart disease are traveling companions; the heart tends to kill the patient before the kidneys finish quitting.
Now layer in what GLP-1 drugs do. They are strongly cardioprotective — they reduce heart attacks, strokes, and cardiovascular death. So the mechanism cuts in an unexpected direction: by keeping fragile CKD patients alive longer and preventing the premature cardiac deaths that used to remove them from the pool, GLP-1s could actually allow more of them to survive long enough for their kidneys to reach end-stage failure — where dialysis becomes the only option. In this framing, a drug the market treated as a demand-killer might, on a long enough horizon, be demand-neutral or even demand-expanding. The market had modeled only the numerator (slower kidney decline) and ignored the survival denominator.
The timeline and the fine print
Management's second argument was about time. Kidney disease progresses over years and often decades. Even if GLP-1s do modestly shrink the eventual dialysis pool, that effect would show up gradually, far in the future — easily swamped in the near and medium term by the powerful tailwinds already baked in: an aging baby-boomer population and rising rates of obesity and type 2 diabetes, the very conditions that drive kidney failure. And the third argument was clinical precision: management repeatedly pointed out that the FLOW trial studied a specific patient profile (type 2 diabetics with existing CKD), and that only a portion of the broad dialysis-bound population matches those exact criteria — so extrapolating FLOW's results to the entire future patient pipeline overstated the effect.
Reading the credibility
For an independent analyst, the tell is not whether the story is comforting but whether it holds up under adversarial questioning — and here the earnings-call dynamics are informative. In prepared remarks, management leaned on stable near-term clinical metrics and, crucially, kept raising guidance rather than cutting it: through Q1 2026, DaVita lifted full-year adjusted operating-income guidance to $2.15–$2.25 billion and nudged its full-year treatment-volume growth expectation up from flat to a 25–50 basis-point increase, with CEO Javier Rodriguez noting the raise was split between underlying performance and patients transferring in from competitor Fresenius clinics.[^1]4 A company genuinely watching its patient pipeline dry up does not repeatedly raise volume guidance.
The consistency across calls is itself the evidence. From the Q3 2023 call when the FLOW news broke, through the Q4 2025 and Q1 2026 calls, management's framing of the GLP-1 question did not lurch or contradict itself; the cardiovascular-survival argument and the clinical-criteria argument appeared in roughly the same form each time, supported by the same direction of reported results.5 Narrative consistency under repeated, skeptical questioning is one of the more reliable signals an analyst has that management believes its own story rather than improvising reassurance. It is not proof the story is right about the distant future — but it is the opposite of the evasive, shifting explanations that usually accompany a management team quietly losing confidence. In Q&A, analysts pushed on the specifics — the actual GLP-1 penetration rates among newly admitted patients — and management's answers stayed grounded in the trial's clinical criteria rather than hand-waving. That consistency, sustained across multiple calls and matched by rising rather than falling reported volumes, is the kind of behavioral evidence that lends the actuarial argument real credibility.
The honest caveat is that this is a long-duration question that cannot be settled in 2026. GLP-1 adoption is still ramping; the multi-decade effect on ESRD incidence is genuinely unknown; and management, however credible, is not a disinterested party. The fair conclusion is narrower than either the panic or the all-clear: the market's initial reaction — pricing in an imminent collapse of the patient pipeline — was not supported by the underlying epidemiology, and the reported operating results since have vindicated the near-term calm. Whether the very long-term terminal value is impaired remains an open, unfalsified question. Which is exactly the kind of ambiguity that belongs in a proper bull-and-bear reckoning.
X. The Playbook: Lessons, Risks, and Bull vs. Bear Case
Step back from the individual battles and the shape of the whole thing comes into focus. DaVita is a mature, cash-generative duopolist in an essential service, whose growth in value comes not from growth in the business but from relentlessly concentrating ownership of a stable cash stream. That single sentence contains both the bull case and the bear case, depending on which word you emphasize.
The durable lessons
Two lessons generalize well beyond dialysis.
First, extreme share cannibalization is a legitimate — and underrated — form of value creation when, and only when, the underlying business is genuinely durable and predictable. DaVita's regulatory duopoly, near-total patient lock-in, and recession-proof demand are what make buying back seventy percent of the equity a rational act rather than a reckless one. Buy back the stock of a fragile, cyclical, or disrupted business and you simply lever up a melting asset. Buy back the stock of a fortress and you compound it. The prerequisite is the fortress; the buyback is the amplifier.
Second, stay inside the circle of competence. The HealthCare Partners detour cost years and billions to prove that DaVita's edge is specifically in the assembly-line economics of dialysis density, not in the general business of managing healthcare. The most disciplined thing management did in the last decade may have been reversing its own grand strategy and returning the cash to shareholders rather than chasing the next adjacency.
The bull case, tested
Why does DaVita win from here? The strongest version: the barriers to entry are physical and human, not just financial. A challenger would need to build clinics at scale, pry nephrologists out of joint ventures whose economics already favor the incumbent, and somehow match the low-cost position of a national operator — all to compete for a government-priced patient base where the only real profit sits in a commercial sliver the incumbents already dominate. On Porter's five forces, this scores unusually well: the threat of new entrants is very low; rivalry is muted because two rational players split the market; buyer power is split (the government is powerful and pays little, but individual employer plans struggle to carve out an irreplaceable provider, as Marietta's aftermath showed); and substitutes are limited to a kidney transplant (supply-constrained) or death. Layer on a buyback machine funded by predictable free cash flow and refreshed by a fresh $2 billion authorization in 2025, plus genuine margin optionality from home dialysis and value-based care, and you have a credible mechanism for continued per-share compounding even with flat volumes.11
The bear case, tested
Why might the case break? The bear points at the exact seams in the bull's armor.
Commercial mix erosion. The whole profit structure balances on ~11% of patients. Every year, employer plans and insurers push to negotiate rates down or exploit the legal room Marietta opened. On the Q1 2026 call, CFO Ackerman himself guided that commercial mix would decline over the course of the year, putting pressure on revenue per treatment.4 That is not a hypothetical risk; it is management's own base case, and it grinds slowly against the most valuable revenue the company has.
Labor and cost inflation. Dialysis is labor-intensive, and clinical staffing shortages drive up cost per treatment. Because the government reimbursement side is capped, the company cannot simply pass rising nurse and technician wages through to its largest payer. The spread between revenue per treatment and cost per treatment is where clinic-level profit lives, and labor inflation attacks it directly.
Government reimbursement. DaVita is structurally dependent on the annual Medicare ESRD Prospective Payment System update. If those rate increases fail to keep pace with clinical cost inflation — a persistent risk in a budget-constrained federal system — the breakeven-to-loss government business gets worse, and more weight shifts onto the shrinking commercial subsidy.
To this an activist or short-seller would add a governance-and-capital-structure critique worth stating plainly: DaVita's buybacks have been substantial, and funding aggressive repurchases while carrying meaningful debt means the strategy is, in part, a leveraged bet on the stability of the commercial cross-subsidy. If that subsidy erodes faster than expected while leverage stays high, the per-share magic can run in reverse. The Berkshire standstill also creates an unusual overhang: a single holder near 45% whose periodic, mechanical selling into the buyback is a permanent feature of the float. None of these are scandals; they are the structural tensions a skeptical investor should keep in view rather than wave away.
A brief second-layer diligence note belongs here, of the kind that doesn't show up in a headline P&L. First, credit and leverage: a company that spends most of its free cash flow retiring equity rather than reducing debt is deliberately keeping its balance sheet levered, which is fine while cash flow is stable and refinancing is cheap but converts into a genuine vulnerability if capital markets tighten or the commercial mix deteriorates at the same time — the two risks are correlated, which is what makes them worth watching together rather than separately. Second, the long tail of legal and regulatory exposure: between the historical False Claims settlements, the JV structure's permanent Stark/Anti-Kickback sensitivity, and the recurring political attacks on the reimbursement model, this is a business that will always carry a non-trivial legal reserve and a headline-risk premium. Neither of these is a reason to dismiss the company; they are reasons to underwrite it with clear eyes about where the fragilities sit. In April 2025, a ransomware incident that encrypted parts of DaVita's network, disrupted some operations, and ultimately affected the data of roughly 2.7 million individuals was a reminder that even a physical, low-tech-seeming service now carries real cybersecurity exposure — one more line item on the risk radar for an operation running thousands of connected facilities.19
The three KPIs that actually matter
Cut through everything and there are three numbers that tell you whether the thesis is intact. An investor doesn't need to model the whole company — just watch these.
-
Commercial payer mix and average commercial reimbursement rate. This is the master variable. It is where nearly all the profit comes from, and it is the thing under the most sustained pressure. Watch the mix percentage and the negotiated rate; if they slide faster than volumes and cost control can offset, the whole per-share story slows.
-
Home dialysis penetration. This tracks whether the margin-and-capital-efficiency shift is real or perpetually "next year." Rising penetration validates the future-business narrative; stalled penetration means the growth story is mostly buybacks.
-
Revenue per treatment versus cost per treatment. The fundamental spread. Revenue per treatment is driven by payer mix; cost per treatment is driven by labor and supply inflation. The gap between them is clinic-level operating leverage, and it is the cleanest single read on whether the core machine is getting more or less profitable per chair.
Watch those three, and you are watching the company. Everything else — the drama, the ballot measures, the drug scares — ultimately shows up in that trio.
XI. Epilogue & Outro
Return, at the end, to where we began: a machine that keeps a quarter-million people alive, wrapped inside a machine that shrinks its own share count. DaVita's journey from the brink of insolvency in 1999 — a $417 million loss, covenants broken, a stock left for dead — to a lean, cash-compounding duopolist is one of the more improbable turnarounds in American healthcare.13 But the deeper lesson is not about the rescue. It is about what the rescued asset was for.
Kent Thiry saved the company with culture and operations. Javier Rodriguez has run it with a spreadsheet and a scalpel. Yet the person who arguably extracted the most value from DaVita never worked there. Ted Weschler simply understood, earlier than the market, that a slow-growing business built on an ironclad duopoly and a predictable commercial cross-subsidy did not need to grow to make its owners wealthy — it needed only to keep buying itself back, patiently, for years. Berkshire's drift to nearly half the company was the reward for holding still while the float melted away.6
That is the quiet genius and the lurking fragility of DaVita in a single frame. The genius is that flat can compound, if the moat is deep enough and the capital allocation is disciplined enough. The fragility is that the entire edifice balances on an eleven-percent sliver of commercial patients, a Medicare rate set in Washington, and the political tolerance of the states it operates in. The share cannibal has feasted well. Whether it can keep eating depends, as it always has, on whether the commercial subsidy holds — and that is a story still being written, three treatments a week.
References
-
DaVita Inc. 4th Quarter 2025 Results (Full Year 2025 Financial Results) — DaVita Investor Relations, 2026-02-02 ↩↩
-
Novo Nordisk's Ozempic shows early success in kidney trial, plunging dialysis stocks — Reuters, 2023-10-11 ↩↩
-
California voters reject measure to regulate kidney dialysis clinics again — Reuters, 2022-11-09 ↩↩
-
DaVita (DVA) Q1 2026 Earnings Call Transcript — The Motley Fool, 2026-05-06 ↩↩↩↩↩↩
-
DaVita Q4 2025 Earnings Call Transcript — The Motley Fool, 2026-02-03 ↩
-
Warren Buffett's Berkshire Hathaway Ownership Stake in DaVita — Stockcircle ↩↩↩↩↩
-
How DaVita Shrank Its Share Count and Became a Serial Cannibal — GuruFocus, 2025-10-24 ↩↩
-
Effects of Semaglutide on Chronic Kidney Disease in Patients with Type 2 Diabetes (FLOW Trial Results) — New England Journal of Medicine, 2024-05-24 ↩
-
Berkshire sells some DaVita shares, cuts stake to 45% — Reuters via Investing.com, 2026 ↩↩↩
-
DaVita Inc. Form 10-K, Fiscal Year 2025 (shares outstanding and repurchase authorizations) — U.S. Securities and Exchange Commission, 2026 ↩↩↩
-
DaVita Inc. Form 8-K: $2 Billion Additional Share Repurchase Authorization — U.S. Securities and Exchange Commission, 2025-08-20 ↩↩
-
DaVita Inc. Form DEF 14A Proxy Statement (executive compensation and ownership) — U.S. Securities and Exchange Commission, 2026-04-22 ↩
-
DaVita to Acquire Gambro Healthcare, a Renal Dialysis Services Company — DaVita Investor Relations, 2004-12-07 ↩↩
-
FTC Accepts Settlement to Remedy DaVita's Acquisition of Rival Outpatient Dialysis Clinic Provider Gambro — Federal Trade Commission, 2005-10 ↩
-
DaVita Kidney Care Agrees to Pay $495 Million to Settle Whistleblower Case — Nelson Hardiman LLP, 2015 ↩
-
Whistleblower ('qui tam') case against DaVita alleging kickbacks to doctors — Phillips & Cohen, 2014 ↩
-
DaVita and HealthCare Partners Announce Merger Agreement — DaVita Investor Relations, 2012-05-21 ↩
-
DaVita Inc. Form 8-K: Ransomware Incident Disclosure — U.S. Securities and Exchange Commission, 2025-04-14 ↩
 LinkedIn
 WhatsApp
 Reddit
 Hacker News
 Email
 Kindle
 RSS Feed
 Spotify
 Apple Podcasts
 Amazon Music
 Audible
 YouTube